From Memory to Meaning: How Mirae Is Changing the Way We Manage IBD

This is a sponsored blog post; all thoughts and opinions are my own.

Living with Inflammatory Bowel Disease (IBD) means constantly reading the signals your body is sending you. What you eat, how you sleep, your stress level, your energy, and even the seemingly small changes in your routine can influence how you feel. After more than 21 years with Crohn’s disease, I’ve learned that this internal conversation never completely goes away, even during remission.

The challenge is that when symptoms become part of everyday life, gradual changes can be surprisingly difficult to recognize. Whether you’re newly diagnosed or have been living with IBD for decades, knowing your personal baseline can be one of the most valuable tools in managing your disease.

That’s where the Mirae Health app comes in. Rather than relying on memory or trying to piece together months of symptoms and lifestyle patterns before an appointment, Mirae helps patients see their own patterns and recognize when something starts to shift. This week on Lights, Camera, Crohn’s, we hear from Mirae’s founders about the inspiration behind the app and why understanding the connection between our daily lives and how we feel could change the way we approach IBD care.
Mirae’s founding designer, Sayoko Yoshida, chose to use a bear because they wanted something that felt:

  • Warm and inviting
  • Steady and dependable
  • Protective
  • Human and personal

The Mirae team specifically didn’t want the app to feel like a cold clinical dashboard or an overly cheerful “health app” mascot. They wanted the bear to represent a reassuring guide, something that helps people living with IBD understand what’s happening and feel supported as they navigate their care.

The inspiration behind Mirae

Mirae’s three founders, James Finucane, David Clifton, and Anuj Patel, have spent their careers using technology to improve access to healthcare. For Anuj, Mirae’s CEO, the mission is also personal. His father was a GI clinician in rural upstate New York, where he saw firsthand how critical and unequal access to specialty care can be, something Anuj recently wrote about on Mirae’s blog.

The team behind Mirae

“It was very clear how unique and how critical having high-quality specialty GI care in a rural market helped patients and how unequal access to care across the US is,” Anuj explains. “It was important that we use technology to help patients that are at the intersection of a chronic, acute and complex condition, of which Crohn’s and ulcerative colitis were the obvious fit.”

Mirae grew from a shared desire to use technology to solve two connected challenges: the burden patients carry to track and remember their disease, and the limited snapshot clinicians often have when making important care decisions.

The “Aha” Moment

The realization wasn’t about one patient story, but where the most valuable information lives. In IBD, important signals are often small and daily: a change in urgency, creeping fatigue, or escalated symptoms when eating certain foods.

I know when my symptoms increase, I can become hypervigilant, quickly jumping to the worst-case scenario. Much of that internal battle happens privately, between me and the bathroom walls or in conversations with my mom and husband.

Yet very little of it makes it into the medical record. Instead, months of experiences get distilled into a few sentences during a clinic visit, filtered through stress and imperfect memory.

“The gap in IBD care is not a lack of good doctors or good treatments. It is that the richest data about the disease is generated by patients outside of a lab, colonoscopy or doctor’s visit and then mostly lost,” says Anuj. “Building something to capture that gently and carry it into the clinic in a useful form felt like the most obvious unsolved problem in the field.”

Anuj Patel, co-founder and CEO of Mirae Health

The Missing Puzzle Piece in Patient Management

As Mirae’s creators examined the gaps in IBD care, they saw one major problem: there was no single place connecting the pieces.

“People track symptoms in a Notes app, photos of meals on their phone, questions on scraps of paper, and half of it in their head. Most existing tools were built like diaries. They demand daily discipline, which is exactly what you do not have during a flare, so people abandon them when things get hard, when the data matters most. Most importantly, nothing connected the tracking to actual care,” says Anuj.

You can track symptoms for a year, but if your gastroenterologist never sees that information, it’s pointless. And when living with a chronic illness already feels like a full-time job, adding more work to disease management is the last thing those with IBD need.

Mirae aims to change that.

“We wanted to make day-to-day management delightful and to use the AI models developed by our team to better understand disease progression and connect that information to clinicians that can make more informed decisions on a patient’s care.”

Answering the Call as Patients Feel Overwhelmed and Unheard

Feeling unheard usually isn’t about clinicians not caring. It’s about trying to fit months of lived experience into a 15-minute appointment, with the patient expected to remember and explain it all on the spot. That’s an unfair expectation of someone who is unwell.

“Mirae is designed to carry that burden instead. The app does the organizing, the remembering, and the summarizing, so the patient does not have to perform their own case in the room,” says Anuj. “We kept the language plain, the daily effort small, and made forgetting or skipping days completely fine. The goal is that when you walk into a doctor’s visit, your patient experience is clearly summarized for a clinician, allowing the visit to be more humane and genuine, while helping clinicians make more informed treatment decisions.”

At home, Mirae is designed to make living with IBD feel a little lighter. You can think of it as a quiet companion while navigating an often-isolating disease.
“In the clinic, we want people to feel prepared and taken seriously. There is a real difference between walking in trying to remember everything and walking in with a clear summary of the last three months in your hand. One feels like being tested. The other feels like being a partner in your own care,” says Anuj.

A Step Toward Personalized Medicine and Treatment Options

Personalized medicine in IBD starts with recognizing that Crohn’s disease and ulcerative colitis are not one-size-fits-all. Mirae’s technology looks for patterns that can help identify patient subgroups and better understand how individuals respond to treatment.

“Knowing how patients in each subgroup respond to treatment or how symptoms manifest can help a care team recognize earlier when someone may need attention, rather than waiting for the next scheduled visit,” explains Anuj. “It can also make treatment discussions more grounded, starting with months of real-world data and experience that our tools can translate into clinical insight, rather than a few minutes of recollection.”

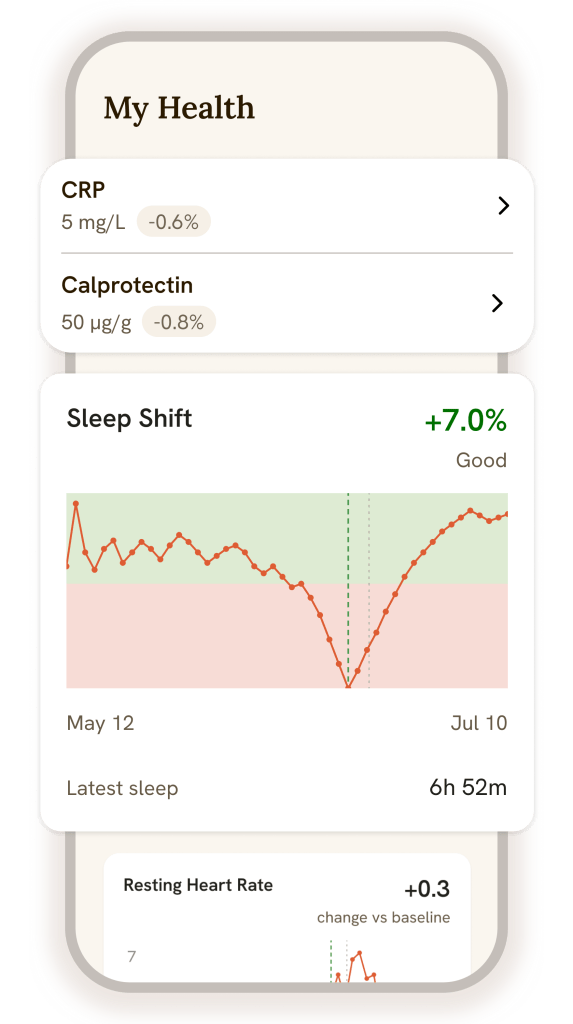
Mirae builds that picture from what patients choose to share over time: symptoms such as pain, urgency, bowel habits, fatigue, and energy; medications and how they’re tolerating them; lifestyle factors like sleep, food and activity; and free-form notes and questions captured in the moment.

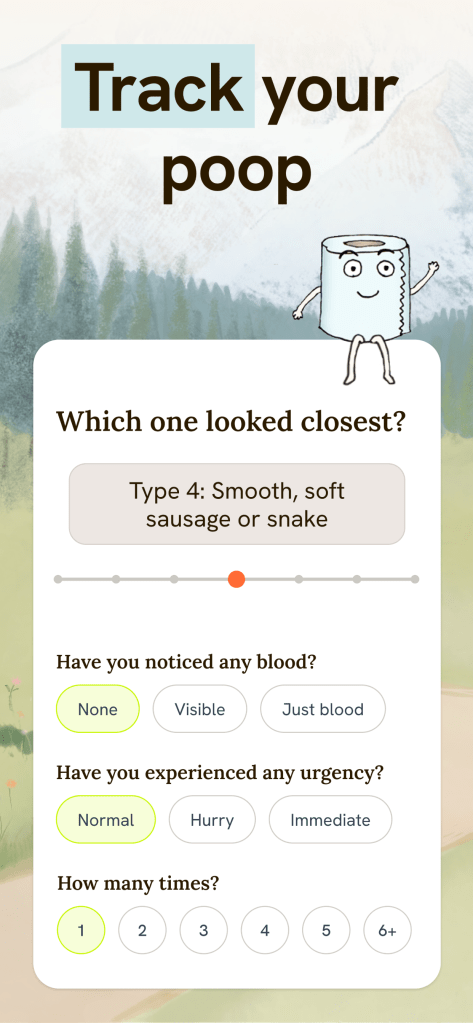
The app looks for what has changed and what you’ve flagged. Mirae suggests; you decide. The goal is to make sure the things that matter most to you are at the center of the conversation. Mirae supports clinical judgment; it doesn’t replace it.

The App Is Free—How?

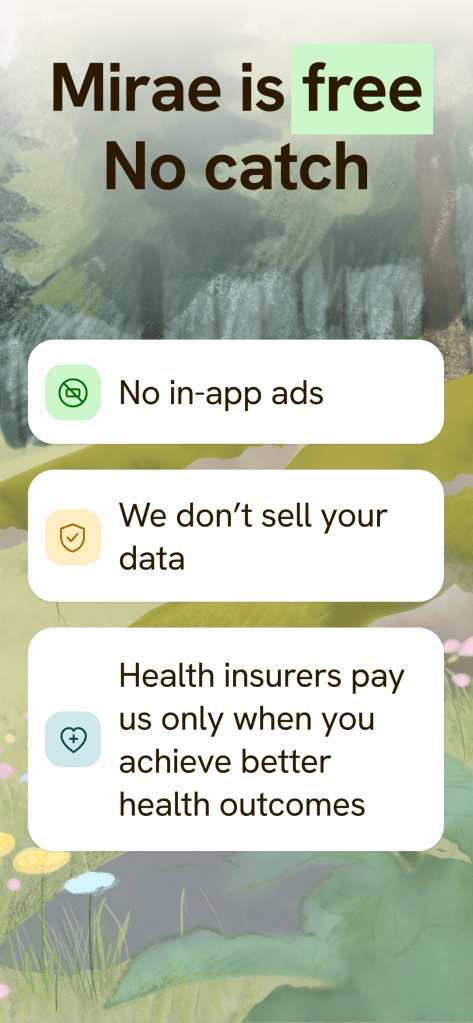
Living with IBD is expensive. Between medications, procedures, time off work, and everything in between, patients already carry a significant financial burden. Mirae’s creators didn’t want to add a subscription fee or rely on ads that could compromise the trust they’re building with patients.

“At a high level, our model works with the healthcare system for payment when patients enter remission sooner. Health systems and care programs benefit when patients arrive prepared, problems are caught earlier, and care between visits is more visible. All of this can help patients get on the right medication sooner while reducing future medical costs, such as surgery or ER visits,” says Anuj.
Making Patients Active Participants in Their Care

The biggest barrier to participating in our own care isn’t motivation, it’s preparation and organization. Too often, we leave appointments remembering the question we forgot to ask or downplaying what daily life with IBD feels like because suffering in silence has become our normal.

“Throughout the weeks between visits, the app makes it easy to capture questions and concerns as they come up, instead of hoping to remember them later. Before an appointment, it helps pull everything together into pre-visit notes: what has changed, what’s worrying you, what you want to ask, and what you want out of the visit,” explains Anuj.

When you arrive with that information in hand, the dynamic shifts. You’re no longer a passive recipient. You have an agenda backed by your own experience. That’s active participation in your care.

The Power of Pre-Visit Notes

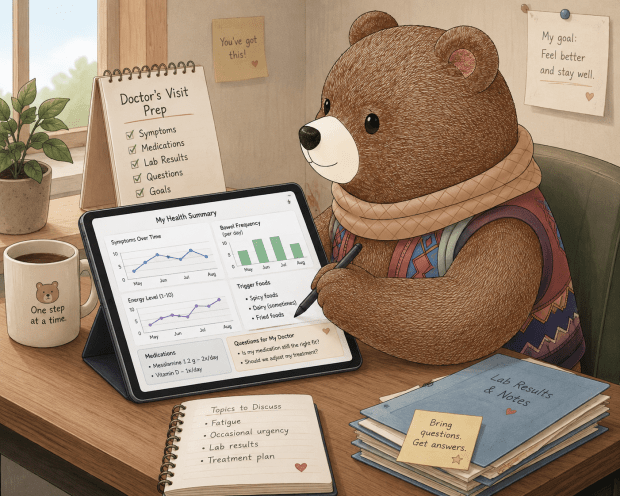
One of my favorite Mirae features is the pre-visit process. You can capture observations about your health, answer targeted questions, and, most importantly, identify your biggest concerns going into the appointment.

Mirae then turns that information into a plain-language summary: what has changed, what has stayed stable, what’s worrying you, and the questions you want to address.
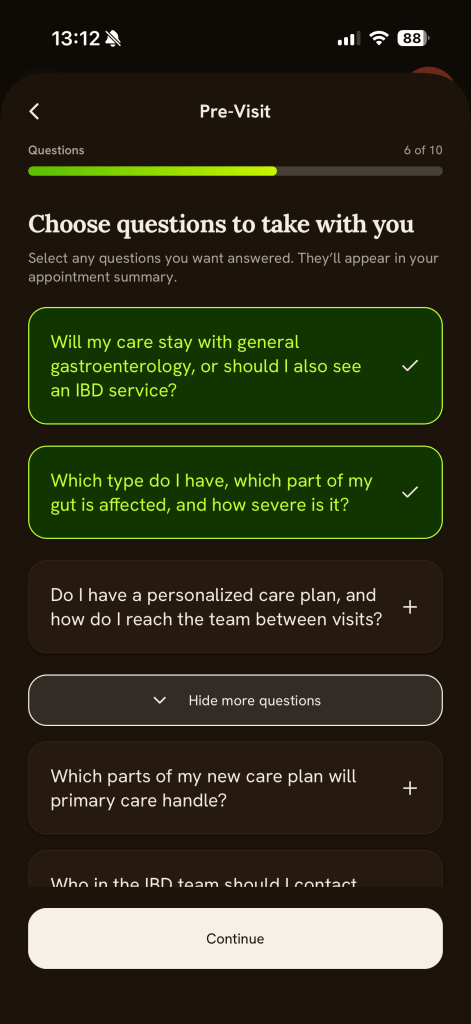
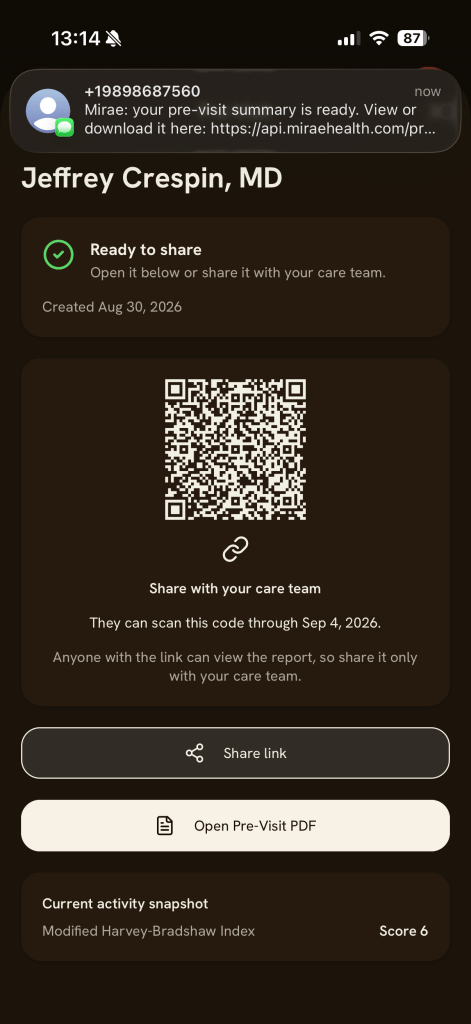
“You can edit anything, remove what doesn’t matter to you, and rank what you most want to discuss. You stay in control of what is shared. When you’re done, you have a short, clear document you can bring into the room or share ahead of the visit,” says Anuj.

An educated patient is an empowered patient. Taking a few minutes to prepare can help both you and your provider make the most of limited appointment time, something especially valuable when we’re juggling multiple specialists.

“The core principle is to change from your own baseline. A symptom level that is normal for one person may be a red flag for another, so relevance is always personal,” says Anuj. “The app looks at what is new since the last visit, what has been trending in either direction, or what has been persistent. Mirae also gives weight to things you have marked as important, medication changes and how they have gone, and anything that has come up repeatedly in your notes. Repetition is a strong signal that something deserves airtime.”

Input from Medical Providers and IBD Patients

Mirae was shaped with input from IBD clinicians, including advisors at Oxford and across the United States.

A consistent theme was where the appointment begins. Too often, the first minutes are spent reconstructing months of symptoms from memory. With organized pre-visit notes, that work is done, allowing more time for meaningful discussion, decisions, and care planning.

“Clinicians have also been clear with us about what they do not want: another screen, more unfiltered data, or anything that adds time. That feedback pushed us to keep the clinician-facing side short and structured. As the pilot progresses, we will let the results speak rather than getting ahead of them,” explains Anuj.

Dr. Simon Travis, Professor of Clinical Gastroenterology at the University of Oxford, sees Mirae as ‘stepping stones across a river, sometimes widely apart.’

He says, “Mirae acts as a bridge. It provides depth, credible advice, links to the evidence, informed comment, and guidance. It complements specialist advice by addressing complex factors such as fatigue or diet in detail, way beyond what is possible to cover during a consultation.”

Dr. Alissa Walsh, a Gastroenterologist at the Oxford University Hospitals NHS Trust and Nuffield Health, The Manor Hospital, Oxford, agreed to support Mirae because she believes people living with IBD deserve to be active partners in their own care, not passive recipients to it.

“Too often patients feel they’re navigating this condition alone, without the information or confidence to ask the right questions,” she says. “Mirae’s work has the potential to change that — empowering patients at every stage of their journey and, ultimately, improving the quality of care they receive.”

As an IBD patient advocate, I’m one of many who have helped to provide feedback and guidance through the app development process. Having patient and provider input is paramount to making sure the app works for us in real time. Multiple members of the Mirae team also have IBD themselves.

“It is hard to advocate for yourself on subjective terms such as “I feel like things have been worse lately.” It is much easier when you can say things have been different for six weeks, here is the pattern, and here is what I would like us to consider,” says Anuj. “When patients see their experience taken seriously, written down, reflected back, and brought into the clinical conversation, it reinforces that their observations matter.”

What Sets Mirae Apart from Other IBD Apps?

Most health apps are islands: you track diligently, but the information rarely goes anywhere. Mirae aims to close that gap in three ways:

  • Connected to clinical care. Mirae is designed to work with a patient’s existing care team. The information gathered is intended to inform care rather than sit in a silo. Its first deployment is within a large academic medical center.
  • Built specifically for IBD. This isn’t a general wellness app with an IBD mode. Mirae was incubated at Oxford’s Computational Health Informatics Lab and shaped by IBD specialists and patients.
  • Designed for both patients and clinicians. Rather than making patients pay for premium features or clinicians pay costly software fees, Mirae is built to serve both sides of the care relationship.

The Goal Five Years from Now

Looking ahead, Mirae’s creators hope the platform will build something that doesn’t currently exist at scale: a rich repository of patient-reported symptoms connected to clinical data that could improve treatment recommendations and eventually inform drug discovery. Longer term, they envision expanding beyond IBD to other autoimmune conditions, where many of the same challenges exist.

“The goal for us is in five years, is that “Maya”, a newly diagnosed Crohn’s patient, is able to use our platform to have a trusted companion that helps her understand her condition and, alongside her gastroenterologist, precisely identify the specific type of Crohn’s she has, find the best therapy for that type, and get on her way to remission and stay there.”

For Mirae’s founders, success means making that experience the norm, so Crohn’s becomes one part of Maya’s identity, not something that consumes her life.

Final Thoughts

Mirae’s goal is to end the era of memory-based appointments where patients carry months of their lives in their heads, then try to summarize it all under pressure. For gastroenterologists, it’s a similar challenge: extracting that information while balancing an enormous amount of clinical knowledge.

Mirae is designed to fit into patients’ lives, especially during the hard weeks, helping turn real observations into a clearer picture of their health and a more personalized care plan.

“We hope Mirae shifts some weight off patients’ shoulders. Managing IBD will never be effortless, but the administrative and cognitive load, the tracking, remembering, and preparing is something technology can genuinely carry. If patients spend less energy managing their disease and more living their lives, we have done our job.”

Download Mirae for FREE! Learn more about Mirae here.

Apple Store

Android

Eighteen Years of Humira: The Treatment That Helped Me Build a Life, Not Just Manage a Disease

Eighteen years ago, when I was 24 years old, I gave myself my very first Humira injections following a hospitalization for an abscess the size of a tennis ball in my small intestine. The loading dose involved four painful injections, in my GI office. While much of my patient journey tends to be a blur, the day I started Humira is crystal clear in my memory. I remember how I was sitting, what it felt like, the emotions, the tears, the worry about starting a biologic medication, and the desperation to be well.

I don’t have any photos of the day I started on Humira, but this was the month after my loading dose, while still on 60 mg of prednisone.

At the time, I wasn’t thinking about anniversaries or milestones. I wasn’t wondering if I’d still be taking this medication nearly two decades later. I was simply hoping it would work. This week on Lights, Camera, Crohn’s I reflect on what I’ve learned and what I wish I knew all those years ago.

Would life ever be the same?

When you live with Crohn’s disease or ulcerative colitis, hope can sometimes feel like the most powerful prescription of all.

Back then, my disease had already taken so much from me. I had endured three years of on and off flares, hospitalizations, procedures, uncertainty, and the emotional weight that comes with wondering if you’ll ever feel like yourself again. I went from being a perfectly healthy person to being diagnosed with Crohn’s at age 21, put on 22 pills a day, and not knowing what the future would hold.

Humira didn’t cure my Crohn’s disease. There is still no cure, of course. But it gave me something I desperately needed: stability. Over the past 18 years, this injection has quietly stood beside me through nearly every major chapter of my adult life.

It helped me continue my career as a television journalist and keep my IBD private from the public, thanks to the medication being a self-injection. It was there as I found my voice as a patient advocate and launched Lights, Camera, Crohn’s. It was there when I fell in love, got married, and became a mom to three children. It’s been there through pregnancies, postpartum life, sleepless nights, school drop-offs, family vacations, soccer/baseball/basketball games, dance recitals, and countless ordinary moments that aren’t ordinary when you’re living with a chronic illness.

Because chronic illness has a way of making the ordinary feel extraordinary.

My youngest child was ironically born on the anniversary of when I started Humira (July 14th)!

Not all sunshine and rainbows

There have certainly been bumps along the way. People are often surprised to hear that I still had multiple bowel obstructions and hospitalizations prior to my bowel resection surgery in 2015, despite being on Humira. More recently, I experienced firsthand how disruptive a forced switch to a biosimilar in 2024 was before successfully appealing to return to Humira. And like anyone living with inflammatory bowel disease, I still have difficult days, anxious moments, unexpected symptoms, and reminders that remission doesn’t always mean life is symptom-free.

But through it all, Humira has remained the foundation of my treatment and a crutch in my life. I recognize how fortunate I am to still be on the same therapy all this time.

No two journeys look the same

One of the greatest lessons patient advocacy has taught me is that no two IBD journeys look alike.

I know many people who have cycled through medication after medication searching for relief. Reminder: The medications are failing you; you aren’t failing anything. Others have exhausted every available therapy, no fault of their own. Some are preparing to start clinical trials because approved treatments have stopped working. Many have endured multiple surgeries, ostomies, prolonged hospital stays, or years of uncontrolled inflammation despite doing everything right.

Their stories matter just as much as mine.

When I share that one medication has managed my disease for 18 years, I don’t do so to suggest this is typical or attainable for everyone. I share it because it represents what every person living with IBD deserves: a treatment that allows them to live life fully. When I started Humira 18 years ago, I had no idea if it would help control and manage my Crohn’s.

I never take that for granted. I don’t know if a year from now I’ll still be in the same boat or if this is a medication I will be on for the rest of my life. I’ve gotten to the point where it’s difficult to imagine life without it, which can feel a bit daunting.

Science changes lives

Every injection is a reminder that science changes lives.

Years ago, biologic medications transformed what was possible for people like me. Back in 2008, there were only two options for IBD patients (Remicade or Humira), now the landscape for treatment options is so vast. Before these therapies existed, many patients faced repeated surgeries, lengthy hospitalizations, and significantly fewer treatment options. Steroids were the go-to. Today, the landscape continues to evolve with new biologics, biosimilars, small molecules, and research that offers hope to the next generation of patients.

I’ve had a front-row seat to that evolution, not only as a patient but as an advocate and journalist interviewing physicians, researchers, and fellow patients around the world. I’ve learned that medicine isn’t just about controlling inflammation.

It’s about allowing someone to chase a career.

To become a parent.

To celebrate birthdays.

To travel.

To make memories.

To simply say yes to life more often than no.

Final thoughts

For me, Humira became more than a medication. It became a bridge between the life Crohn’s disease tried to take away and the life I was determined to build.

If you’re reading this and your current treatment isn’t working, please don’t lose hope.

I’ve met far too many people who found the right therapy after believing they’d run out of options. Research continues to move forward. New medications continue to emerge. Physicians are learning more every year about how to personalize treatment and truly target our disease. Your next chapter may look very different from the one you’re living in today.

And if you’ve found a treatment that works, whether it’s been six months, six years, or eighteen years, I hope you pause to appreciate what an incredible gift that is. Not because the journey is easy. But feeling well enough to live your life and discover a new normal is something worth celebrating.

Today, I’m incredibly grateful.

Grateful to the physicians who believed in biologic therapy long before it became commonplace. Grateful to researchers who dedicate their careers to continuing to advance IBD care. Grateful to my family for standing beside me through every injection and every flare. And grateful for a medication that has helped me experience so many beautiful moments I once feared Crohn’s disease would steal.

Eighteen years later, I’m still here. Still advocating. Still telling stories. Still raising my family. Still chasing dreams. Still injecting every other week.

And I am still profoundly thankful that this self-injection that I’ve given myself 480 times, has helped me live a life that has been so much bigger than my diagnosis.

Out-of-Pocket Costs Nobody Warns You About With IBD

When most people hear about inflammatory bowel disease (IBD), they think about symptoms—abdominal pain, urgency, fatigue, flares. What they don’t think about? The financial toll.

Living with IBD, whether it’s Crohn’s disease or ulcerative colitis, comes with a lengthy list of out-of-pocket costs that rarely get discussed at diagnosis.

IBD patients experience 3 times higher healthcare-related work loss than non-IBD peers. And for many patients and families, those costs become a constant, underlying stressor that shapes daily decisions.

This week on Lights, Camera, Crohn’s a deep dive into the cost of living with IBD and why you’re not alone if financing your health is a constant concern.

Medications (Even When You’re Insured)

Biologics, immunosuppressants, steroids, you name it… IBD medications are often life-changing, but they’re also expensive. Before insurance comes into play it’s shocking when you hear how costly these medications are without coverage:

To break it down, without insurance, two auto-injector Humira pens cost an average of $10,782.36.

Without insurance, a Remicade infusion could cost you anywhere from $4,000-$7,000.

The list price of Skyrizi without insurance is approximately $32,566 per 150 mg injector pen, with variations depending on pharmacy and dosing method.

A 30-day supply of Rinvoq pills without insurance would cost between $7,000-$9,600, depending on dosage and pharmacy.

Without insurance, Stelara costs approximately $21,191 for a 45 mg syringe or $25,497 for a 90 mg syringe, with potential savings through discount programs and patient assistance.

… you get the idea.

And even with insurance, we deal with:

  • Monthly copays
  • Specialty pharmacy fees
  • Deductibles that reset every year
  • Prior authorization delays that interrupt treatment

And sometimes, the biggest cost isn’t financial, it’s physical and emotional when we’re forced to switch medications due to insurance, even when a medication is keeping our disease stable. There’s also the stress we face when switching employers and having to restart the process of getting coverage for our heavy-duty medications with a different insurance and specialty pharmacy.

 The Cost of Staying “Stable”

Routine monitoring is a non-negotiable part of IBD care. Annual lab tests, scans, and scopes add up.

This includes:

  • Bloodwork (often every 3-6 months and sometimes more depending on whether you’re flaring)
  • Stool tests
  • Colonoscopies and endoscopies
  • Imaging like MREs, CT scans, intestinal ultrasounds

These aren’t one-time expenses; they’re repeated regularly to track inflammation and prevent complications. And while they’re essential, they often come with recurring out-of-pocket costs that add up over time. Even after living with Crohn’s for nearly 21 years, it’s always a surprise how much my labs are going to cost. I try and get my colonoscopies in December before my deductible starts over at the start of the year.

Along with managing our disease with those costs, there are also the copays to see specialists to manage our care. A $40 copay to see a dermatologist, bone health doctor, ophthalmologist, primary care doctor, gynecologist…the list goes on, adds up quickly.

Travel, Parking, and Time Away

IBD care isn’t always close to home. My GI office is about 40 minutes away, compared to many people I know, that’s close by. Due to lack of access, many patients must travel to see specialists, infusion centers, or undergo procedures. That can mean:

  • Gas, tolls, and parking fees (I know some patients who take an airplane to appointments!)
  • Hotel stays for early morning procedures and out-of-state appointments
  • Time off work (for patients and caregivers)

These logistical costs are rarely acknowledged, but they’re part of the reality. There have been countless times through my patient journey when I’m stuck in traffic and resent the fact that I have to waste so much time just to manage my disease.

The Cost of “Safe” Food

Food is one of the most personal and frustrating parts of living with IBD.

There’s no one-size-fits-all diet, and many patients rely on trial and error to figure out what works. Often:

  • “Safe foods” can cost more
  • Specialty items aren’t always covered by assistance programs
  • What works one month may not work the next

The financial burden of constantly adapting your diet is real and ongoing. Working alongside a registered dietitian for nutritional guidance may or may not be covered by your insurance. Many insurers cover medical nutrition therapy for digestive diseases, so make sure to look into this.

The Everyday Essentials

Then there are the items no one puts on a medical bill, but every patient knows are necessary:

  • Extra toilet paper and wipes
  • Heating pads
  • Backup clothes and supplies for emergencies
  • Over-the-counter medications and supplements
  • The cost of colonoscopy prep (buying clear liquids, Miralax/Dulcolax, SUTAB pill prep is about $50 depending on insurance, etc.)

Individually, they may seem small. Together, they’re part of the cost of living with IBD every single day.

The Hidden Cost of Missed Work

IBD doesn’t follow a schedule. Flares, fatigue, appointments, and recovery time can all impact a person’s ability to work consistently. That might look like:

  • Missed work days
  • Reduced hours
  • Limited career flexibility
  • Lost income over time

For many, this is one of the most significant and least visible financial burdens. After my bowel resection surgery, I had to be on short-term disability for 2 months which was only 60% of my salary.

Mental Health Support

The emotional weight of IBD is just as real as the physical symptoms.

Therapy, stress management tools, and mental health support can be critical for coping, but they’re not always fully covered by insurance. Many patients pay out-of-pocket for care that helps them navigate:

  • Anxiety around flares
  • Medical trauma
  • The daily uncertainty of chronic illness

For many of us, this is not optional, it’s part of comprehensive care.

Even in Remission, the Costs Don’t Disappear

One of the biggest misconceptions about IBD is that remission means everything goes back to normal. But financially, that’s rarely the case.

Even in remission, patients are still:

  • Taking medications
  • Attending regular appointments
  • Monitoring for signs of inflammation
  • Planning for the unexpected

The disease may be quiet, but the costs are not. As chronic illness patients, we know how delicate our remission is and that on any given day we can be back in a hospital bed trying to navigate an obstacle that wasn’t on our radar a week prior.

Why We Need to Talk About This More

The financial burden of IBD is often invisible, but it affects real-life decisions every day:

  • Can I afford this medication?
  • Should I delay this test?
  • Is it worth taking time off work for this appointment?

These aren’t just healthcare questions, they’re quality-of-life questions. Often, we can feel like a burden to our partner and our family as the medical bills come in, with no end in sight.

And until we talk more openly about the economic impact of chronic illness, patients will continue to carry this weight quietly.

What Can We Do About It?

  • Ask about patient assistance programs
    Many drug manufacturers offer copay cards or financial aid.
  • Request itemized bills
    Errors happen more often than you think and can be corrected.
  • Talk to your care team about costs
    Doctors can sometimes adjust testing frequency or suggest alternatives.
  • Time big procedures strategically
    If possible, schedule costly tests after hitting your deductible.
  • Use HSA/FSA accounts if available
    These can help offset out-of-pocket expenses with pre-tax dollars.
  • Don’t skip mental health support—ask about coverage options
    Some therapists offer sliding scale fees.

Final Thoughts

IBD is more than a diagnosis. It’s more than symptoms. It’s a lifelong condition that comes with physical, emotional, and financial layers, many of which no one warns you about. But acknowledging those realities doesn’t make patients weak. It makes the conversation more honest. And that’s where change begins.

More Information:

4 Tips for When Insurance Doesn’t Cover Your Medication – GoodRx

How to save money on prescription medication: 13 tips

The Cost of Inflammatory Bowel Disease Care: How to Make it Sustainable – Clinical Gastroenterology and Hepatology

AGA-Economic-Burden-Infographic.pdf

The economic burden of inflammatory bowel disease – The Lancet Gastroenterology & Hepatology

Managing inflammatory bowel disease: what to do when the best is unaffordable? – The Lancet Gastroenterology & Hepatology

Global, regional, and national burden of inflammatory bowel disease from 1990 to 2021: findings from the Global Burden of Disease 2021 | Gastroenterology Report | Oxford Academic

Out of Network, In This Together: Chronic Illness, Humor, and Healthcare Reform Through Cartoons and Community

What do you get when you mix chronic illness, dark humor, artistic storytelling, and a deeply broken healthcare system?

You get The Out-of-Network Network — a sharp, satirical, and heart-achingly relatable newsletter born from the experiences of patients who’ve seen (and survived) the absurdities of the American healthcare system firsthand.

Founded by Ian Goldstein, a Crohn’s disease patient and comedy writer, and Amanda Lehr, a writer navigating ankylosing spondylitis (AS) and mast cell activation syndrome (MCAS), OONN is more than a newsletter. It’s a lifeline. A laugh. A community. And most importantly — it’s a call to action, cloaked in clever cartoons and short, punchy stories that make you feel less alone in the madness of it all.

Meet the Founders

Amanda Lehr may not have Crohn’s, but as she puts it:

“I’m a fellow member of the ‘My Body is an Autoimmune Fight Club’ community.”

She’s lived with ankylosing spondylitis since her teens and recently received a diagnosis for MCAS — a condition that turns everyday encounters into allergic warzones.

“Being in my body is like trying to live in the booby-trapped Home Alone house: if there’s not a real intruder around, I’m the one getting hit by swinging paint cans and having my head set on fire.”

For Ian Goldstein, Crohn’s has been a two-decade battle, from bowel resections and obstructions to navigating biologics like Humira, Skyrizi, and Rinvoq. His life revolves around the proximity to hospitals, navigating insurance loopholes, and, like many chronic illness patients, learning to laugh at the chaos.

“I find so much humor in the world of healthcare. Not in the pain we patients deal with. But in the absurdity of interactions and situations that doctors, insurance companies, and people ignorant to our plights bring.”

How Out-of-Network Network Was Born

It all started with what Amanda and Ian lovingly refer to as “The Luigi Incident.”

A moment of internet virality around a meme, combined with a groundswell of people sharing stories about healthcare trauma… it lit a spark. They saw an opportunity to make something lasting.

“Knowing how fast the news cycle moves, we didn’t want this conversation to get lost in the shuffle,” Amanda shared.

So, they built OONN: A weekly Substack newsletter that pairs short healthcare horror stories with custom illustrations — funny, heart-wrenching, eye-opening, and artfully absurd.

“The situations we face aren’t inherently funny,” Ian says. “But how incompetence plays out — lazy doctors, power-hungry insurers, $70,000 hospital bills for inedible food — that’s darkly hilarious.”

Community Through Cartoons

Some of Ian’s favorite entries include:

Amanda, meanwhile, loves the diversity in voice and style across their contributors.

“As a writer, I enjoy collaborating with such distinct voices and artistic styles. As a human, I’m moved by how we all come together around this common belief: healthcare should not be a luxury product.”

The Common Denominator

So, what’s the throughline in the stories they receive?

“It’s a combination of incoherence, incompetence, and institutional hostility,” Amanda explains. “Sick and disabled people end up spending hours fixing mistakes that could bankrupt them.”

“People are crushed by sky-high bills and red tape,” Ian adds. “And those burdens pile onto lives already made difficult by chronic illness.”

More Than Just a Newsletter

For both Ian and Amanda, OONN is as therapeutic as it is informative.

“The first word that comes to mind is catharsis,” Ian says. “Reading someone else’s story — and laughing through it — tells me I’m not alone, and I’ll get through it.”

Amanda agrees, “It’s not better medicine than my biologics, but it’s still pretty damn good.”

Want to Share Your Story?

The Out-of-Network Network is always looking for contributors — writers and illustrators alike. If you’ve got a healthcare horror story, a cartoon-worthy insurance mishap, or just want to laugh (and cry) with the community, you can email Ian: ianscottgoldstein@gmail.com or Amanda: amanda.lehr@yahoo.com.

Final Advice from the Frontlines

Ian shares one last nugget of wisdom — a survival tip for navigating healthcare:

“Record everything. Record your doctor when they give you results. Record your call with your health insurance. Just make sure you’re legally allowed to. It helps you remember things, and it protects you if you need proof later.”

You’re Not Alone

Whether you’re battling Crohn’s, AS, MCAS, or just trying to make sense of a $3,000 copay for a basic test, Out-of-Network Network reminds us that laughter really is the best medicine (after your biologic infusion, of course). And that in this broken, bureaucratic mess of a system, solidarity and storytelling might just help us all stay sane, one cartoon at a time.

You can also subscribe to their weekly newsletter on Substack and follow them on Instagram: @out_of_network_network, @iangoldsteinyes, and @amandamlehr.

Empowering Teens: A Guide to Scholarships for College-Bound Students with Inflammatory Bowel Disease

Millions of people worldwide live with IBD. For teenagers with Crohn’s disease or ulcerative colitis, the challenges are multi-faceted—not only must they manage their health, but they also face the pressures of academic life, dealing with physical and emotional challenges their peers can’t relate to, and the daunting costs of higher education. Thankfully, several scholarship programs exist to support students dealing with IBD, offering financial assistance, and fostering a sense of community and empowerment.

This week on Lights, Camera, Crohn’s a look at what scholarships are available and tips for applying. This story idea was inspired by a caregiver who sent me a direct message on Instagram asking if her teenage daughter could be awarded a scholarship for going above and beyond scholastically despite having IBD. I wasn’t aware of what is available—and in working on this article I did my research as though I was a teen/caregiver looking up scholarships geared towards those with IBD.

Why IBD Scholarships Matter

Teens with IBD often navigate difficult symptoms, frequent medical appointments, and hospitalizations. Despite these challenges, many young people with IBD excel academically, participate in extracurricular activities, and remain determined to pursue higher education. Scholarships tailored to their needs can ease the financial burden of college tuition and provide a sense of validation for their hard work and resilience.

In addition to financial relief, these scholarships can help build a sense of camaraderie among students with similar experiences. IBD scholarships are a powerful way for these teens to connect, share their stories, and feel supported and empowered in their journey toward college and beyond.

Notable Scholarships for Teens with IBD

Abbvie Immunology Scholarship: The AbbVie Immunology Scholarship aims to reduce the financial burden for students impacted by inflammatory diseases. It is awarded to 45 students. Recipients pursuing an associate degree will receive a $5,000 scholarship. Those pursuing a bachelor’s or master’s degree/PhD will receive a $15,000 scholarship.

The Salix Gastrointestinal Health Scholarship Award: Ten scholarships to 10 outstanding students living with gastrointestinal (GI) diseases and disorders who are pursuing their higher education goals. The 2025-2026 application period opened February 10, 2025, and the end date to apply is May 5, 2025.

Patient Advocate Foundation – Scholarship” In 2000, PAF established the Scholarship for Survivors program to honor these individuals by offering educational scholarships to students who have suffered (or are suffering) from cancer or a chronic illness. The deadline for submissions is March 7, 2025.

180 Medical Scholarship Program: The 180 Medical Scholarship Program is open to full-time college students living with specific medical conditions, including spinal cord injuries, spina bifida, transverse myelitis, neurogenic bladder, or an ostomy (ileostomy, colostomy, and/or urostomy). They offer seven $1,000 college scholarships annually to seven recipients. Accepting applications through June 1, 2025. Recipients are announced in August.

AAHD Frederick J. Krause Scholarship on Health and Disability: Awarded annually to deserving students with a disability who are pursuing undergraduate/graduate studies in an accredited university and who are pursuing studies related to health and disability. Scholarships are generally $1,000.

Buckfire & Buckfire, P.C. Disability Scholarship Program: The Disability Scholarship was established in 2014 as part of the law firm’s commitment to helping students with disabilities or injuries who need financial assistance for educational purposes. The scholarship awards $1,000 to one student. The deadline to apply is October 1, 2025.

Defining the Disability Scholarship: The attorneys at the Berkowitz Hanna Malpractice and Injury Lawyers offer a $1,000 scholarship to help a student overcome a disability. Students define what disability means to them and explain how disability has been part of their life. Applications are not being accepted right now but stay tuned for 2025.

Lawrence Madeiros Scholarship: The Larence Madeiros Scholarship Fund was formed to provide awareness of chronic disorders to the public and to stimulate, foster, and encourage interest, awareness, and activism at the state and national level with reference to the fight against chronic disorders. The scholarship is awarded to high school seniors living with a chronic disorder and continuing their education at a college or university. The deadline for applying is May 1, 2025.

Overcoming Disability Scholarship: The Law Offices of Coats & Todd Overcoming Disability Scholarship awards $2,500 scholarships twice a year to college students who are managing a disability while attending school. To qualify, students must have a physical or psychological disability that affects their ability to work. The deadline for applying is March 26, 2025. Their team can be reached at: scholarships@coatsandtoddlaw.com

IBD Connects Scholarship Program: To support the educational aspirations of students impacted by IBD, IBD Connect awards two annual scholarships, each valued at $1,000, to eligible applicants enrolled in a U.S. college, university, or trade/vocational school for the upcoming academic year. The application program opens March 1, 2025, and ends May 31, 2025. For any questions regarding the Scholarship Program, email Lisa Fournier: lisafournier@ibdconnectinc.org.

It’s important to note there may be other IBD-related scholarships available, this list reflects what I discovered upon researching this article.

Additional Scholarship Resources

Beyond disease-specific scholarships, many general scholarships and grants are available to students with disabilities or health conditions. Websites like Scholarships.com, Niche, and Unigo allow users to search for scholarships based on specific needs, including chronic illness or disabilities.

To search for more scholarships that you may qualify for, visit the U.S. Department of Education’s Federal Student Aid website and the U.S. Department of Labor’s free scholarship search database. You can search for scholarships based on the state you live in, your degree program, and your future goals.

Additionally, some universities even offer their own scholarships for students with disabilities, including those affected by IBD. It’s always a good idea to contact the admissions or financial aid office of the school you’re interested in to inquire about any opportunities.

Tips for Applying for IBD Scholarships

  • Start Early: Many scholarships have early deadlines, so it’s important to start the application process well in advance of the due dates.
  • Tell Your Story: Your personal experience with IBD is what sets you apart. Be honest and heartfelt in your essays, sharing how IBD has shaped you as a person and student.
  • Gather Documents: Be prepared to provide documentation of your diagnosis, along with transcripts and letters of recommendation.
  • Stay Organized: Keep track of all deadlines, required documents, and any special instructions for each scholarship.

Final thoughts

For teens living with IBD, pursuing a college education can be a difficult but achievable goal. Scholarships specifically designed for students with IBD can alleviate financial stress, validate personal resilience, and provide a network of support. I was “lucky” in the respect that I was not diagnosed with Crohn’s disease until two months after college graduation, so I did not have to navigate these challenges while furthering my education and moving away from home. Along with scholarships, it’s important for caregivers and students with IBD to communicate the need for accommodations on the college campus—this can range from having a bathroom in or near your dorm room to having extra time to complete assignments. Click here to read another Lights, Camera, Crohn’s article that digs deeper into this topic.

As more awareness is raised about the challenges of IBD, opportunities for scholarships and grants continue to grow, ensuring that students with IBD can thrive academically without being held back by their condition.

Additional Resources

Taking IBD to School | Crohn’s & Colitis Foundation

Disability Support Services | Crohn’s & Colitis Foundation

10 Tips for Dealing with IBD in College – Managing IBD at School | Michigan Medicine

Starting College with Ulcerative Colitis

College Students with Inflammatory Bowel Disease: A Qualitative Study of Challenges Associated with College Transition and Self-Care – PMC

A Guide for How to Thrive in College With Crohn’s Disease

Navigating College with IBD – IBD Connect

How to Handle College if You have Crohn’s or UC

College and IBD Handbook – ImproveCareNow

Back to school tips

Preparing for College Life with Crohn’s Disease

Talking to Your Boss and Coworkers About Inflammatory Bowel Disease

Living with IBD can be especially challenging in a professional setting. Prior to becoming a stay-at-home mom and freelance/blogger, I worked full-time for 12 years. For 10 of those years, my Crohn’s was not in remission. This week on Lights, Camera, Crohn’s, guidance on how to approach conversations with your boss and co-workers effectively so you can feel supported.

The more they know

Before I became self-employed, I worked at three television stations, a public affairs PR agency, and in Corporate America as a communications specialist for a natural gas utility. With each interview and onboarding process, I waited until I was hired to disclose that I had Crohn’s disease to my boss. The first week of work, in a one-on-one meeting I openly shared about my disease and tried my best to educate my boss and my team about my health. Since I did not start blogging or any patient advocacy work until 2016, there was nothing online about my journey with Crohn’s. If I were trying to get a job nowadays, I wouldn’t have that luxury since my story is publicly shared. Every single boss, all my co-workers, and each employer were extremely understanding and empathetic about my struggles. I was incredibly lucky in that regard.

While working full-time I had several hospitalizations and bowel resection surgery that kept me out of work for 2.5 months. I was grateful for bosses who were generous with sick time and that my corporate job had a solid short-term disability plan I was able to utilize.

Everyone has a different opinion about when and how to best disclose your health or disability status. While some people consider their IBD a “disability,” others do not. I’m often asked how to navigate answering that question on a job application. I personally do not consider my IBD to be a disability, but it’s understandable if you do. Answer as you see best fit and most comfortable.

Why It’s Important to Share

  • Accommodation Needs: Explaining your condition can help you receive necessary accommodations, such as flexible work hours or the ability to work from home during flare-ups. One of the major benefits of the pandemic is how it altered how we work. Back when I was in the workforce, working from home wasn’t utilized as much as an option. I had high symptom days where I worked from home once or twice every few months, but it wasn’t a weekly occurrence. Hybrid working environments or remote jobs are ideal for those with chronic illness.

The flexibility work from home jobs provide is huge—whether it’s being able to work from your couch if you’re dealing with abdominal pain and it hurts to sit at a desk, being able to work in comfortable clothes or pajamas if the fatigue makes showering a challenge, or worrying about the commute and being able to travel without a bathroom mishap or having to go multiple times in a public employee bathroom…the list can go on and on.

  • Understanding: Colleagues aware of your condition are more likely to be supportive and understanding during challenging times. One of the most important aspects of IBD to share with others who do not have our disease is the unpredictability of our health. Since we’re able to look perfectly normal on the outside, it can be difficult for an average person to fully grasp or believe the pain we’re dealing with. I remember countless days in Corporate America having to unbutton my work pants and having to tell my co-workers I was on the struggle bus. I can still envision myself on the news desk when the camera shifted to a weather segment and slumping over in pain. Everyone I worked with was aware of when I was having an “off” day. I’ve had co-workers drive me to the emergency room during the workday. I always felt supported and was never made to feel like I was less than because of my Crohn’s and for that I am still grateful.
  • Reduced Stigma: Talking openly about Crohn’s and ulcerative colitis can help reduce the stigma associated with chronic illnesses and foster a more inclusive workplace. People may question or wonder why you may have unique work accommodations, while it’s none of their business, being transparent, and really stepping up to the plate and going above and beyond when you’re able will show others that you never use your disease as an ”excuse”. If you have an infusion or a doctor’s appointment that makes you arrive late, it’s helpful to inform your boss and co-workers so they know why you may be strolling in during the middle of the day.

Preparing for the Conversation

  • Know Your Rights: Familiarize yourself with your workplace’s policies on medical conditions and accommodations. Understanding your rights under laws such as the Americans with Disabilities Act (ADA) can provide a framework for your discussion. Check out these tips from the Crohn’s and Colitis Foundation.
  • Plan Ahead and Explain Your Needs: Choose an appropriate time and setting for the conversation. Ensure privacy and sufficient time to discuss your needs without interruptions. I always had a face-to-face conversation with my bosses, and they were appreciative of knowing. Clearly state what accommodations you need to manage your condition effectively. This could include flexible hours, a work-from-home arrangement, or having a desk closer to the restroom. Emphasize your dedication to your job and how these accommodations will help you remain productive. For example, “Having the ability to adjust my work schedule during flare-ups will help me stay on top of my responsibilities.” If I was prepping for a colonoscopy or having a scan, I let my team know.
  • Gather Information: Be ready to explain what IBD is, how it affects you, and what accommodations or support you might need. A high-level explanation is often sufficient.Your boss doesn’t need to know your entire patient journey. For example, “I have a chronic condition called Crohn’s disease/ulcerative colitis that affects my digestive system. This can sometimes cause severe abdominal pain and fatigue.”
  • Offer Solutions: Suggest practical ways to implement accommodations. For example, “During flare-ups, I could work from home and communicate via video calls and emails to stay connected with the team.” Your boss may have questions or concerns. Be prepared to address them calmly and provide any necessary documentation from your healthcare provider.

Communicating with Coworkers

You don’t need to share all the details. A brief explanation like, “I have a medical condition called Crohn’s disease/ulcerative colitis, which sometimes causes me to feel unwell,” can suffice. Explain how your condition might impact your work or interactions. For example, “There may be times when I need to step away from my desk more frequently.”

Reassure coworkers that while you have a chronic condition, you are still capable of performing your job. For example, “Most days, it doesn’t affect my work, but there might be times when I need a bit of flexibility.”

Encourage an open dialogue. Let them know they can ask questions if they want to understand better, but also respect your privacy. While I was hospitalized, I would often send an email to my team at work to provide them with a high-level update, so they heard the information from me versus someone else. For example, “Hi team! I appreciate all your well wishes. It’s been a difficult few days, but I’m hanging in there. I hope to be discharged from the hospital by the weekend and look forward to seeing you soon.”

Final Thoughts

Talking about IBD with your boss and coworkers can seem daunting, but it is a crucial step toward ensuring you have the support you need in the workplace. By being honest, clear, and proactive, you can foster a more understanding and accommodating work environment. Remember, your health and well-being are paramount, and having open discussions can help you maintain your health, while staying on top of your professional responsibilities. When interviewing for jobs, pay close attention to how an employer manages insurance benefits, short-term/long-term disability, and whether you feel like your boss and co-workers would be people you feel comfortable sharing your health struggles with. You aren’t married to your job, if you ever feel unsupported, seek employment elsewhere. Along with your boss, it’s helpful to talk with Human Resources, so you’re aware of all the medical benefits and support that is available for employees.

While IBD complicates life, I hope you continue to go after your dreams. Sure, there are going to be setbacks and roadblocks along the way, but you are worthy of whatever job or career you want to set out and do. Less than 3 months after my diagnosis, while on 22 pills a day, I landed a job 8 hours away from all friends and family and went after my dream of working in TV news. I’m proud of that and it’s a reminder that this disease doesn’t need to rob you of all you hope to be and all you hope to do. You are not a burden on employers and the sky is the limit for you.

Helpful Resources:

Employee and Employer Resources | Crohn’s & Colitis Foundation (crohnscolitisfoundation.org)

Inflammatory Bowel Disease Coverage Under the ADA (verywellhealth.com)

Navigating the workplace – My IBD Life (gastro.org)

How To Cope With Ulcerative Colitis at Work (clevelandclinic.org)

10 patient-backed tips for dealing with IBD at work – Oshi HealthCrohn’s and Work: Your Rights, The ADA, Statistics & More (healthline.com)

Everything you need to know about Chronic Boss Collective

Chances are you’ve heard the song, “Who Runs the World (GIRLS)” by Beyonce. Think of that song and then imagine all the incredible women in the world juggling chronic illness, their careers, and their personal lives. It’s no small feat.

Until recently, there wasn’t a group to celebrate and support us. But now that’s changed thanks to the Chronic Boss Collective. It’s the first and only professional membership designed for ambitious businesswomen living with chronic health conditions to help women dream big in their careers while prioritizing their health without tradeoffs. The international networking membership includes monthly in-person and virtual programming rooted in three pillars: professional development, connection, and wellness. 

This incredible group is the brainchild of Lilly Stairs, a well-respected patient advocate and entrepreneur. At the age of 19, Lilly was diagnosed with psoriatic arthritis and Crohn’s disease.

Making the concept become reality

The concept for Chronic Boss Collective had been on Lilly’s heart long before everything came into fruition. As an ambitious businesswoman who prioritizes her health and self-care, she had yet to find a space that holds these two statements to be simultaneously true. So, she created it.

“Throughout my career, I’ve met remarkable women whose lives have been turned upside down by a chronic condition, but they choose to keep going. They choose to give back. They choose ambition in the face of adversity. Every time I encountered a new woman who fit this profile, I couldn’t help but wonder how powerful it would be to get them in a network together,” said Lilly.

Because of her unique lens as a driven businesswoman living with chronic conditions and working in healthcare, she identified a gap that most people didn’t realize existed.

“For the past decade, I’ve had the privilege of watching extraordinary women transform their struggle into their strength. There’s an undeniable magic to these women living with chronic conditions who choose ambition. By harnessing that collective power, the Chronic Boss Collective is taking off like a rocketship.”

Currently there are 100 Founding Members. There’s an open enrollment period going on right now and new members are being accepted. Lilly tells me she expects to triple the membership over the course of this year. You can learn more and apply on the CBC website.”

Let’s talk Member Benefits

The Collective Membership is jam packed with benefits designed to help you level up in your health and wealth. Rooted in professional development, connection, and wellness, the Chronic Boss Collective offers the following benefits:

✔ Chronic Boss Mastermind

✔ Boss Boosts: Professional Development 

✔ Boss Breaks: Wellness Events

✔ Monthly in Person Meetings (Boston Only)

✔ Private Online Community 

✔ Member Directory

✔ Member Feature 

✔ Affiliate Program

✔ Exclusive CBC Curated Resources

Detailed Benefits

Private Community

A custom online platform is complete with a private member directory, resource library, and buzzing chat rooms for you to network away with fellow ambitious members. 

Chronic Boss Mastermind

Virtual mastermind with the entire membership! This jam-packed event includes:

  • Kickoff: Led by our Founder designed to amp you up and set intentions to get after your health and career goals this month.
  • Networking: Expand your reach and visibility and deepen your connections with the Chronic Boss Collective membership
  • Mastermind: Opportunity to submit a challenge you’re facing ahead of the meeting and then break into small groups to harness the power of the collective and mastermind it.
  • “Boss Round”: Lightning round of your top “ask” to get support where you need it most!

Boss Boosts: Professional Development 

Monthly Boss Boost webinars lead by members and industry leaders presenting in their “Zone of Genius” designed to help you level up in your career. Think building your brand, negotiating your salary, starting a business while living with a chronic condition…and so much more.

Connection

Monthly in-person meet-up for chapter-based members – a mix of networking and fun! 

Boss Breaks: Wellness 

Quarterly wellness event centered on taking care of you. From mindful movement to gluten-free bake-alongs!

Member Spotlight

Get featured on the CBC social media and have the exclusive opportunity to contribute to media stories.

Resources

Proven methods, tools, and guides to help you level up in your career while maintaining your health.

Affiliate Program

Earn 10% commission when you refer new members to join!”

The priceless power of community

The Collective launched this past January (2023), and it is remarkable the impact it is already making on the lives of members.

“Every day, members are buzzing about the magic happening in Chronic Boss Collective. Women are connecting online and IRL to give each other valuable health support and share their best career and business advice. Our conversations skip the small talk and get straight to a point of vulnerability. The coolest part is that now our members are collaborating on projects that will make a real difference in people’s lives, like mental health resources and patient platforms.”

While CBC is seeking women who are ambitious, high achievers, and making an impact, fitting that description does not mean you have to be working as a full-time professional or running a large-scale business.

“For example, stay at home moms and chronic illness advocates who have monetized their advocacy work or built a side hustle (think Etsy shop, Amazon storefront, social media influencer, etc.) could be fabulous members,” said Lilly.

Requirements and cost to participate

The Collective is an exclusive membership for high achieving career women and all members go through an application and screening process before being accepted.

“Our virtual international membership is $397/year. Our chapter-based membership, which includes a once per month in person meeting, is $497/year. This is currently only available in the Boston area, but we have ambitious plans to scale to new cities in the coming years.”

Hopes and dreams for the future

Lilly says plans are in the works to massively scale the Chronic Boss Collective.

Not only do we plan to scale the membership, but we plan to scale our offerings. In addition to the membership, we’ve already launched the Chronic Boss Scholarship which has awarded $31,000 to 31 students living with chronic conditions who have persevered and succeeded. We have big plans to usher in impactful programming that will serve the millions of women who choose ambition in the face of living with a chronic condition. Stay tuned…we’re just getting started!”

Feedback from CBC members

“The Chronic Boss Collective has changed my life in many ways. Since becoming a founding member and acknowledging my worth, my life has changed in ways I never could have imagined. The connections, opportunities, and immediate camaraderie amongst intelligent, inspirational, and courageous women has been my biggest blessing in 2024! The degree to which we draw strength from each other is something I have never witnessed in my life and I’m profoundly grateful to share my Chronic Boss journey with so many astonishing women.” – Lisa Z.

“This group is amazing. Thank you for launching this. I feel like this is the sisterhood that I didn’t know I needed whether for my health, business, or career and I’m just so thankful for it especially at this time in my life.” – Erika P.

“I can tell in just a month that I made the right decision to join. The connections I’ve made and leads already generated through the community will help me grow my design business and allow me to work with my people — authentic and adaptable chronically ill women who are changing healthcare.” – Sarah S.

Connect with Chronic Boss Collective

Instagram

Facebook

Website

An innovative app for all chronic illnesses: Meet Corra

This post is sponsored by Corra. All thoughts and opinions shared are my own.

For as long as Elya Lane can remember she had signs and symptoms of a health condition. It wasn’t until college that she received her official diagnosis of Ehlers Danlos Syndrome and POTS. She says her poor health started to spiral with other comorbidities popping up, the worst of which was chronic UTIs that left her whole body in crippling, burning pain and weak from the antibiotics. Elya’s personal journey with chronic illness inspired her to create the Corra App. This week on Lights, Camera, Crohn’s we learn about how she made her dream a reality and how she hopes to improve peoples’ lives.

The breaking point

“I was constantly plagued with fears of antibiotic resistance, infection complications, or complications from long term antibiotic use. I got to the point where I was so sick that I wrote letters to my kids and my family in case something happened to me. I started tracking all our passwords and making videos for my husband on where our important files were, how different things were stored, all the kids’ data, etc. While I tried to face this potential outcome bravely, I was devastated imagining my kids growing up without a mom,” said Elya.

As she navigated these dark and daunting days, the despair caused her to think about how she could fight back and regain control of her health.

“I started to religiously track my health in journals before transferring to Excel spreadsheets. I was so frustrated by how exhausting and impossible it felt to crunch that much data, so I turned to searching for a symptom track and correlative software to help me. I downloaded and tried every single one I could find – but none met my needs. Some even gave me back faulty data which made me angry. That’s when I decided to create a solution myself,” she explained.

In 2020, after losing access to all her healthcare management tools, and with her health declining rapidly, she decided to create Corra.

The meaning of Corra

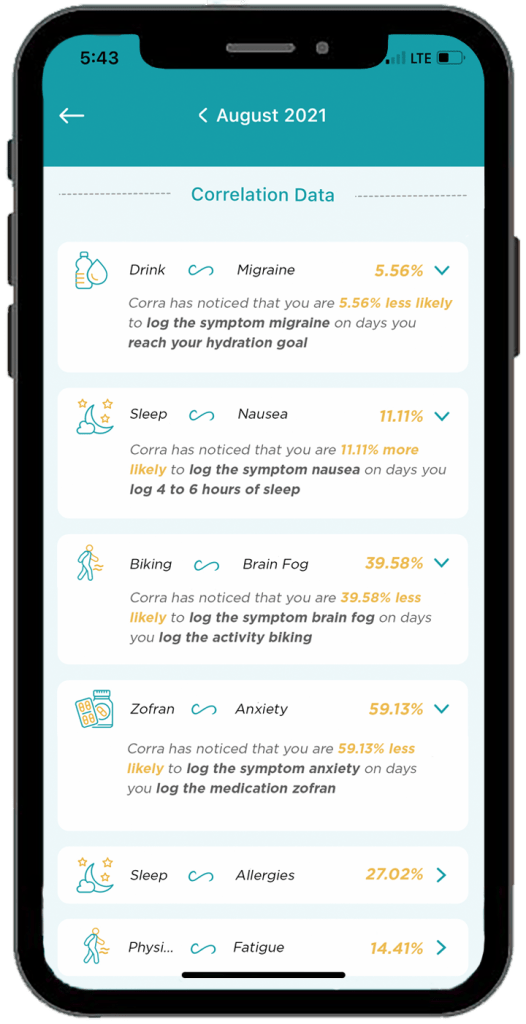
There are quite a few chronic illness apps on the market, some that even attempt to offer correlative insights. Corra is short for correlations. Elya wanted to identify correlations in her health so that she could find her triggers and optimize her lifestyle.

Here’s what sets Corra apart from other chronic illness apps on the market:

  • The algorithm was custom built by Corra’s chief data scientist, Simeon Wilson, who has a master’s in quantitative economics from UCLA. “We are not aware of any software that exists that compares to what Corra is currently offering with our correlative algorithm.”
  • Corra was designed by individuals with chronic illness. “Not just me! While the idea and original designs are all mine, we brought on more than 200 beta testers with various chronic illnesses to provide their feedback and help us tailor the app to the needs of the chronic illness community. Even now, we continue to rely on the insights and feedback from the community to enhance and adjust the app. I want Corra to always be designed by and created for our community.”
  • We correlate with nutrition in an accurate and helpful way. “I believe nutrition plays a massive role in our health so one of our key focuses with our algorithm was to be able to correlate seamlessly with nutrition inputs.”
  • Corra does not sell user’s data. “We don’t scrape your data from your device or browsing history, we don’t use your data to sell you anything, we don’t share your data with third parties. Your data is yours alone. As an individual with a chronic illness who often feels more like a commodity than a person, making sure people can receive personalized insights into their health without signing away their privacy is incredibly important to me.”

Corra’s bells and whistles to check out

  • The ability to track health data in one place without having to use five different apps to log information. “My favorite part of Corra is of course the correlations, because getting detailed insights like that about my health is equivalent to having a team of data scientists run extensive tests on my health and provide me reports. It’s life changing to be able to learn about my health overtime and create a custom-built lifestyle that caters to my future.”
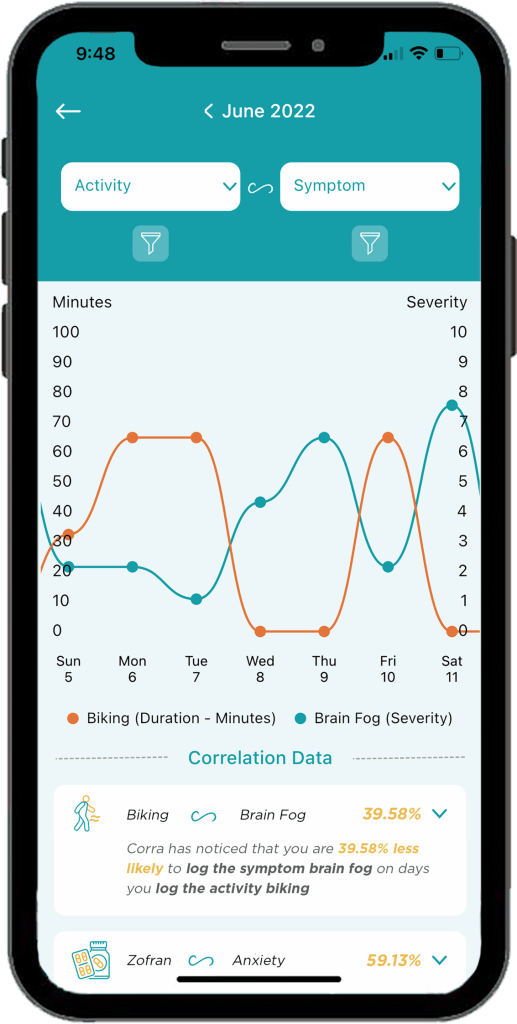
  • Discovering positive and negative correlations. “You may receive insight that something has x% chance of increasing or decreasing a symptom. I think being able to get data on the things that are helping is just as important as being able to identify triggers.”
  • The ability to log appointments, download PDFs of your data to share with my doctor, track medications and supplements, track mood and stress levels, etc. “I’m also extremely excited about all the upcoming integrations we have in the works! Soon we will be connected to Fitbit and Apple Health with Garmin, Cronometer, Weather data, and hopefully Oura coming shortly after! Over time we will continue to integrate with as many devices and apps as possible so users can have all their data in one location!”

A promising future

Elya says being able to learn what foods, activities, supplements, and medications help or cause symptoms has enabled her to have a much better understanding of how best to manage her health conditions.

“I’ve been told to go vegan, cut out red meat, don’t eat dairy, sugar, gluten, eat paleo, try a carnivore diet, go vegetarian, and try cutting out leafy greens… what I found with Corra is that I didn’t need to make these drastic nutrition changes, I only needed to cut out some foods in each of those categories. For example, I discovered that I have a high trigger correlation with ground beef. I can eat steak and other red meat, but not ground beef. Similarly, chicken thighs are a trigger for me, but chicken breast is not. Same with gluten, there are some gluten products that are triggering for me, but not all gluten triggers me. Being able to identify exactly which foods to cut out, rather than willy nilly cutting out entire food groups or going on drastic diet changes, has been an absolute game changer.”

Elya has also discovered that cold and flu medications like Mucinex are major triggers for her. This helped her realize why she would get a horrible flare a few days after coming down with a cold or flu.

“Now, I try to manage my colds and flus with other medicine to try to prevent the flare on top of the cold. It’s also important to note that I’m not cured! I have to manage my diet and my activities and my supplements every day. The difference is, I’m no longer throwing shots in the dark, I now have the information I need to manage my condition to the best of my ability.”

Information really is power, and it has given Elya control over her life and reduced her anxiety. Because of Corra, she is now coming up on two years without the need for daily antibiotics. It’s been over 2 years since she visited the emergency room.

I’ve found that medical providers are far more willing to accept unbiased data from an algorithm than trust my verbal expression of my experience, so in that way Corra becomes my advocate and backs up my statements,” said Elya.

She says her health conditions have caused her to go through depression, isolation, and hopelessness. But her hope for Corra is two-fold.

“First, I believe it can help others identify their triggers and optimize their life so that their conditions can become more manageable, but I also hope that Corra can be a beacon of light for those struggling to see they are not alone. There are so many steps between the start of symptoms and any kind of treatment let alone cure (depending on if your condition is even curable)… and I want to be the one that goes into the trenches and helps people who are suffering the most. So many people in the chronic illness community get forgotten or left with “your test results are normal” when they know there is something wrong with them. I want to create a company that comes alongside them and lifts them up and allows them to have their voices heard.”

Downloading Corra

You can download Corra directly from the App store or the Android playstore. There is a free version as well as premium access. The premium version is $7.99/month or $24.99 if you enroll for a 6-month subscription. Elya is looking for Corra Insiders who are interested in getting free access to the app. By joining the Insiders group, you get a first look at upcoming features. This provides you the opportunity to share feedback on what you do/don’t like or would like to see improved or added in the future. Sign up for the Corra Insiders program here.

Cedars Sinai’s IBD Dietitian Apprenticeship Program is Changing the Future of Nutritional Support for Patients

It’s the first of its kind program dedicated to training dietitians about IBD-focused nutrition. Cedars Sinai Hospital in Los Angeles, California launched its IBD Dietitian Apprenticeship in July 2023.

Registered IBD dietitian Stacey Collins was the first registered dietitian to be selected, participate, and complete the program. I’ve been amazed at all she does for our community and been excited to dig deep and learn what her key takeaways have been from this experience. As someone whose lived with ulcerative colitis since 2012, when she was 21-year-old, Stacey has a unique perspective and approach.

This week on Lights, Camera, Crohn’s we’ll hear about her firsthand experience and why this Apprenticeship program is just what our community needs. The hope is that registered dietitians who participate in the program can take their knowledge from the experience and be able to plug themselves into an IBD Center to build and strengthen an IBD program.

Going up against lack of education and funding

Stacey tells me there is little to no education that they receive in dietitian training on how to do nutrition specific to gastroenterology, much-less IBD, and she says this Apprenticeship program fills the gaps and then some.

“So much of what I learned was through self-study before this program. But in the Apprenticeship, whether I was part of the team rounding on patients in the hospital, or seeing a newly diagnosed patient in clinic, or sitting on the floor with a 3-year-old patient asking about their Paw Patrol toys, I left every encounter feeling that special kind of discomfort and gratification that comes with growth and learning. This was truly a hands-on learning experience from many different sides of the IBD rubix cube, and I’m so grateful I wasn’t learning it all by reading slides from a PowerPoint and taking a test- who learns that way anyway?!”

Addressing the unmet needs

Once registered dietitians complete the Apprenticeship they can work in an academic center or a private practice that values IBD nutrition and has the financial backing to justify the need for a dietitian.

“There are institutions and people in places of power who are advocates for the profession of IBD RDs, and this work is simply impossible without them. IBD RDs have the potential to support patients throughout their journey as an accessible, consistent member of their multidisciplinary care team. Unfortunately, a lot of this potential is systemically handicapped by the lack of funds: RDs are investments rather than quick money-makers for a clinic without physician advocates and creativity, and we NEED people at institutions to see our value,” said Stacey.

The main programmatic goals are to provide a structured, supervised training program for dietitians to learn a model wherein dietitians work together with physicians and advanced practice providers for the care of adults and children with IBD.

Places do exist (and many are coming) that support this multidisciplinary model of healthcare delivery, but there’s such an unmet need, especially for people who don’t have access to these IBD centers. The hope is for this Apprenticeship program to fill the gaps of that unmet need by signaling to physician advocates at these institutions that a nutrition professional with intense training and experience DOES exist, ESPECIALLY for more complex patients who have IBD.

So much to be done for patients
Registered IBD dietitians can assess people for malnutrition regardless of their stage of IBD, which is common even in remission and linked to poor health outcomes, along with so much more. Stacey says:

  • We can help catch micronutrient deficiencies or insufficiencies that many other care team members might miss, and we can correct and monitor them.
  • We can help patients experiencing food insecurity find ways to nourish themselves within their budget constraints with an eye toward prevention of other comorbidities.
  • We can help nutritionally prepare patients for surgery.
  • We can help patients in need of a medical or therapeutic diet intervention find a way to make it a sustainable intervention for themselves.
  • We can help patients nourish themselves using a whole-person approach, whether they are juggling multiple diagnoses, starting a new job, headed off to college, or too tired to eat: we have tools for helping patients feeling like they can handle it all
  • We can help prevent re-hospitalizations from small bowel obstructions or dehydration by giving patients IBD-specific tools for understanding their body.
  • We can save physicians time by inheriting questions about nutrition and/or supplementation regimens, and we can personalize these for each patient.
  • We can even show GI or IBD Fellows what it’s like to feel spoiled working with an IBD dietitian, and hopefully they’ll advocate to hire one of us wherever they make their final clinical stop

She’s confident IBD dietitians can make nutrition an accessible tool when it so often feels inaccessible with IBD!

Stacey’s top apprenticeship moments that left a lasting impression

Six months is a long time to pick up your life, move to another state temporarily, and fine tune your knowledge and expertise on nutrition and IBD. Here are the key takeaways Stacey says she took away from the experience:

1. Patience with patients is key; everyone is on their own timeline.

“I got to see a doctor celebrate with a patient who finally quit smoking cigarettes for good. After that encounter, he told me that he had been pleading with that patient for 20 years to stop, but he never blamed the patient for having a tough time stopping. He really was empathetic to the fact that they had a lot going on, and he knew they’d get around to it once life allowed. That was really enlightening to see: patients really are doing their best. How can I support them, especially if their timeline looks differently than the expectations that I have?” 

2. It doesn’t have to be all-or-nothing; don’t let perfection be the enemy of good nutrition.

“One day I was with Erin Feldman, RD (Cedar’s Pediatric GI and IBD RD). She was listening to a worried mom talk about how she didn’t want her kid to eat sugary cereal, but that’s ALL they would eat for breakfast: it was the sugary cereal, or it was nothing at all. The child was exercising their choice autonomy and exploring what that looked like around mealtimes, and it was a challenge for the parents. Erin had a rapport established with the family, and I could see that they really trusted her. Plus, Erin is a mom, too, so she speaks the same first language as parents, and she really empathizes with the fact that many IBD parents are blamed for their child’s symptoms or disease. She truly met the parents right where they were at that moment.”

“Instead of focusing on the PERFECT breakfast with beautifully-balanced macronutrients and color that the child certainly would refuse, she said, “What if you just added PLAIN Cheerios and a couple of raspberries to their sugary cereal, that way they’re getting some antioxidants from the berries and a more diverse source of grains into their breakfast?” It was TOO easy, and the parents were like, “YES. We can do that.” and just like that: not a perfect solution, but a practical intervention that would work for where the child is right now.”

And that’s the power in having multiple touchpoints to a dietitian: next time they see the doctor again, they’ll see Erin, too, and they can make more adjustments for how life is being lived around food at that stage, too. So often people have the ambitious idea of going from zero to specific carbohydrate diet (SCD) all in one encounter, and the reality is that often multiple conversations and coordination of resources are needed, and meeting patients where they are looks different for everyone.

3. Nutrition interventions can be hard, and multidisciplinary support really is key. 

“So often as dietitians, it’s easy to get stuck in the weeds of research and to get excited over interventions that have promising outcomes. This happened with a patient needing Exclusive Enteral Nutrition, but ~5-7 days into it, they were uncomfortable, and they really missed food. I was able to have a conversation with the patient alongside their doctor in the same room, who patiently reiterated our rationale behind the intervention and said, “not if it compromises your mental health. Let’s stop it if your brain is telling you we need to stop- we need to respect that. You should be proud that you tried this, and now you know!” And I could tell the patient was so relieved to have reassurance from their doctor that no matter what THEY chose for THEIR body they’d be supported by their doctor and by their dietitian. It really does take a team.”

4. GI Doctors REALLY do not get exposure to solid nutrition in their training

Kelly Issokson, MS, RD (Clinical Nutrition Coordinator, Course Director: DIET Executive program, Apprenticeship Director) arranged for Stacey to lead a learning session with the GI Fellows at Cedars, and in a room full of some of the smartest and most compassionate clinicians.

“They wanted to know all about the different nutrition interventions that we can recommend for patients. It felt like they had been rewarded for being the best of the best all by themselves their whole lives, and now they had an opportunity to learn more about how to collaborate effectively. They were all so enthusiastic.”

Stacey noticed after that session that the GI Fellows felt comfortable texting her while on rounds if she wasn’t there to ask if she’d stop by a patient’s room, or they’d text to ask about B12 supplementation after remembering to screen for a deficiency.

“They really understood the value that IBD RDs bring, and it’s not because I’m a great public speaker (I’m really not); it’s that they had this additional exposure to working with a dietitian with specialized training. This really made everything click for me: doctors don’t always know the right questions to ask patients about our nutrition needs, because most of them haven’t had the education OR the exposure to team members with the expertise to be truly helpful for patients. Working in silos keeps patients isolated, and I’m hopeful that the GI Fellows, when/if they leave Cedars become physician advocates to ensure that their patients have access to an IBD experienced RD.”

Plans for the future

When Stacey completed her Apprenticeship this winter, she did not envision returning full-time to her online private practice. She thought she’d start working at an academic institution, because the purpose of the program is for the dietitian to seamlessly integrate into a multidisciplinary GI care team.

I am still holding out on hope that one day I could have both (but I’ll never give up my private practice- I love it so much). Truthfully, I’m thrilled to be back with such a passion for teaching patients how to implement some of the skills that I’ve learned into their own life, plugging it into their existing care teams, even if I’m on my own in private practice. I already helped patients through perioperative nutrition before this program, but now I’ve got some RICH resources to help make IBD surgery and nutrition really make sense for patients now in a much clearer way,” Stacey explained.

She’s able to take the research that they did from the perioperative IBD Nutrition program that exists at Cedars and put it into practice with her patients, and it’s a bit of a full-circle moment for her, having lived through IBD surgery with limited support.

“I’m a much better listener than I was before this program, a skill I learned from Kelly Issokson, MS, RD (Clinical Nutrition Coordinator, Course Director: DIET Executive program, Apprenticeship Director). Additionally, I’m more practical in my approaches and meeting patients where they really are, too, a skill I learned from Erin. I’m working on some ways to expand IBD RD accessibility, too. I’m a much more confident advocate on behalf of my patients now, too.”

Advice for the newly diagnosed

If you’re reading this and you or a loved one was recently diagnosed with IBD, ask your GI doctor to hire an IBD Dietitian. Stacey knows this doesn’t exist in most places, and as a patient, she understands how silly it is to constantly be burdening patients with requests. But the field of IBD Nutrition exists because enough patients asked, “What can I eat?” and enough doctors paid attention to it to be documented research. This is the next piece of the puzzle.

If your care team provides a registered dietitian who doesn’t specialize in IBD, that’s not going to cut it. Be assertive in asking your GI office to hire an IBD Dietitian, or invest in training their Dietitian,  if they really want to help their patients.

Stacey advises patients and caregivers to stay off online forums. There’s so much food fear there, and life is bigger than that. Lastly, she advises reaching out for help. Even if Stacey may not be a good fit for you, she’s happy to provide patients with other RDs that she’d enthusiastically see, because an informed decision is a good one.

You can also utilize the directory on the Crohn’s and Colitis Foundation’s website to find some dietitians, and the AGA will have a directory available soon, too. 

Exciting research nuggets

During her Apprenticeship, Stacey chose to do a research project to examine the effects of malnutrition and perioperative nutrition supplementation on surgical outcomes in people getting IBD surgery, whether that be for j-pouch, permanent ostomy, lysis of adhesions, or a resection.

“We had a small sample size (n=25). Regardless, we found that perioperative nutrition supplementation had a statistically significant impact on decreasing the length of stay, meaning that greater adherence to the nutrition supplementation protocol was associated with a shorter time spent in the hospital. Regardless of nutrition status (malnourished or not), everyone seemed to benefit from the nutrition supplementation protocol that we recommended for before and after surgery.”

Stacey is hopeful that more research with an even larger sample size will help inform these results so that this can be a resource more widely available for patients!

The future is bright

“If I dared to dream about what this could look like in the future, the closest possible model in existence is at UCLA under Dr. Niru Bonthala who is the Director for Women’s Health in IBD. Basically, I see the RD’s role evolving to cover every nutritional aspect of IBD with specialized knowledge to support patients in each life circumstance: from surgical prehabilitation to home nutrition support (TPN or EEN) and transitioning back to eating; to the overlap of eating disorders; to fertility and perimenopause; from anywhere along the spectrum of LGBTQIA+ care and/or transgender care; from peds transitioning to adult care, and even adults to aging adults; even athletics and/or eating disorders.”

There’s a rich opportunity within all these Venn-diagrams for a specialist interest and training to exist in IBD Nutrition, and this learning opportunity exists at Cedars.

“I’d also love to see the RD in an outpatient clinic even able to do community outreach: teaching basic cooking skills, procuring menu items for their medical diet (and beyond), and even showing patients and their families what this could look like by partnering with local food banks. Again, this is just me dreaming here in a world that I think should exist for people who have IBD and for RDs who are trained in IBD Nutrition,” said Stacey.

The current IBD Apprentice Yi Min Teo (@herbsandfood) came from both clinical and private practice backgrounds like Stacey. Yi Min will finish her training in July 2024. The program is supported by a grant from Leona M. and Harry B. Helmsley Charitable Trust.

In addition to dietitians wanting more IBD nutrition education, there’s also an Executive Program for MDs/DOs, APPS, and includes both virtual and in-person learning opportunities. You can apply here.