It’s been 6,207 days since my life changed forever. On July 23rd, 2005, I was diagnosed with Crohn’s disease at age 21. Since that time, I’ve evolved and changed in ways I may not have if it weren’t for my IBD. After living in silence with my condition while working in television news for a decade, I decided to use my love for storytelling and speaking to be the voice I needed to hear upon diagnosis as I navigated the many crossroads of young adulthood (finding love, a fulfilling career, and having a family).
July 23rd also marks the day I launched my blog, Lights, Camera, Crohn’s. Since 2016, I have shared fresh content, every single Monday (sometimes even twice a week!). 336 articles on my site alone. More than a quarter-million visitors and more than 387,000 views.
It’s been a labor of love and a mission project that continues to fill my cup and implore me to constantly want to learn more and shed light on topics that are often not talked about. Every day of every week since my blog began, I’m constantly thinking about story ideas, topics of interest, people to interview, ways to word content, images that are needed…the list goes on.
This photo was taken at a wedding July 23, 2016, right after I pressed “Publish” on the first Lights, Camera, Crohn’s article. I found out I was pregnant two days later.
The weekend I started my blog in 2016, I was one month into married life and found out days later I was pregnant with my first child. Since then, I am now a stay-at-home mom of three children (ages 5, 3, and 1). Life has gotten way more hectic and busier with each year that passes, but I’ve held tightly onto fulfilling my promise to the patient community, and to myself, to deliver new content each and every week. I’ve been organized through the years—often having an article written days before my Monday deadline, but this past year, with another baby added to the mix, it’s been more of a stress on me. I’ve spent many Sunday nights finishing my articles. At times it’s felt like a lot to juggle. I haven’t wanted to let anybody down, including myself. And I haven’t wanted my content to start lacking in any way.
Don’t worry, Lights, Camera, Crohn’s is not going anywhere
My blog has grown into more than I ever thought possible. It’s so rewarding to know my words have helped comfort and guide so many in the IBD community. I need to cut myself some slack and give you a heads up that moving forward there may not always be an article on Mondays. It pains me to say that, but at this point in my life, in this season of IBD motherhood, I need to start taking time to rest and relax. Since having my third baby last summer, I get my kids down for the night and START to work around 830 pm. It’s just constant. I truly rarely get a break. I’ve been in remission since August 2015, and I don’t want the stress to get the best of me.
You may not be aware—but my blog is only one aspect of my advocacy work. I also spend a great deal of time working with digital healthcare companies, patient-centered non-profit organizations, sitting on advisory boards and patient engagement teams, communicating with patients in need online and over the phone, and do freelancing work on the side, all without childcare.
I laugh as I write this because I already have three articles lined up for August…so there will be months where there IS an article every Monday. Just not always. My commitment and desire to serve as a patient leader is not waning in any way—I just want to be honest with you, my loyal readers, that this mama needs to lighten the load and take a little self-imposed stress off my shoulders.
I started contemplating this a few months ago, and almost changed my mind this week about sharing, but it’s time. We had an AMAZING 6-year streak of constant new content. I’m excited to see what this coming year brings in the way of patient stories, research, and perspectives. Having extra time to work on articles will really allow me to do more special reports and expand my “IBD Motherhood Unplugged” and “Patient Experience” series.
Thank you for giving me so much to talk and write about, always. There are endless topics that need to be brought to the forefront and I love providing a platform for others to share their journeys and experiences with the community. As always, please reach out if you have a story idea you want me to cover. Lights, Camera, Crohn’s has truly evolved from being a blog about my IBD experience to an award-winning and well-respected site that has highlighted hundreds of different patient stories and physician perspectives—and I love that. There’s no greater compliment then when I hear a gastroenterologist uses my blog to educate their patients.
Excited to see what 2022-2023 brings! Thanks for the love, support, and understanding and for making the first six years of Lights, Camera, Crohn’s what it was.
Take yourself back to the very first time you needed medical attention for your IBD (but didn’t know it yet). Close your eyes for a moment. Who was that person? Do you know them anymore? How have you changed and transformed since that life changing day?
I was diagnosed with Crohn’s disease July 23, 2005, at age 21. I was blindsided by a chronic illness after growing up as a literal picture of health. A three-sport, in shape athlete, who had never even had an ear infection or been to an emergency room. As a recent college graduate, my world flipped upside down as I struggled to find my way in the real world.
Now, 17 years later, I can tell you firsthand what I, you, and so many others have endured on our patient journeys and how each experience (even the mundane) serves as monumental touchpoints for gaining independence and confidence in making you a more empowered and direct patient.
Let me paint the picture clearly for you
The first time you bravely laid in an emergency room bed and every time there after—not knowing the tests, pokes and probs, and physical scrutiny you were about to go through.
How it feels to be wheeled by a stranger through stark hallways to CT scans, MREs, and scopes, wondering what the results will be on the other side and the repercussions for more medications, a longer hospital stay, or surgery.
The difference a couple months makes–pre-diagnosis in May 2005 and 2 months after 60 mg of prednisone a dayand 22 pills a day.
What it’s like when you say goodbye to loved ones and they roll you into the OR and you’re shaking like a leaf, all alone and feeling frail and broken, alone with your thoughts and prayers.
The number of moments you’ve watched nurses and even rapid response nurses fumble with IV’s try after IV try and when it’s been more than five, you find your voice from that point forward and start only giving medical professionals two tries before it’s on to the next.
How it feels at the butt crack of dawn when the world is sleeping and the hospital is bustling, waking you abruptly to get more vitals and more labs and you lay alone, haggard, frustrated, and delirious.
The moment when your GI has a heart to heart with you about starting a biologic and having to determine for yourself what route is your preference—infusion or self-injection. Would you rather sit for hours hooked up to an IV drip or sit on your couch with your kids looking on as you inflict pain on yourself.
The times you’ve sat up in the middle of the night wide awake thanks to the prednisone kicking in while the rest of your world is asleep wondering if you’ll ever regain some semblance of control of life.
What it’s like trying to eat meals inconspicuously with your family while they not so subtly watch each bite and every trip to the bathroom with sadness and worry in their eyes.
How it felt driving to a first date or a job interview and feeling like your IBD is a dark secret looming over the conversation and not knowing when to take down your walls and share.
Listening to your friends make comments about health and energy without considering what your experience with a chronic, debilitating illness may be like since you look well on the outside.
What it feels like to look at your reflection in the hospital bathroom. Battered arms, sunken in eyes, a shell of who you used to be. But as soon as you walk out of the door, putting a soft smile on to protect your visitors from worry.
What it’s like to sit on an airplane or be on a road trip with others and silently worrying about whether you’ll be able to make it and what your game plan will be.
When you’re up in the middle of the night doing the second half of colonoscopy prep and wondering ‘why me’ in your 20s and 30s, feeling isolated in the physical, mental, and emotional anguish the process puts you through year after year.
What you’ve internalized each time someone dumbs down your IBD, offers up ridiculous remedies or goes into a discourse about their aunt’s brother’s cousin who “healed” their Crohn’s this way.
When you’ve waved the white flag and alerted family and friends that you needed help or to be seen in the hospital after doing as much fighting as you could against your own body.
The first time you bravely looked down at your incision and saw your body forever changed and came to see your scars as battle wounds.
Waking up each day not knowing what the next 10 minutes will feel like for you and getting after it anyway.
Not knowing if you’ll find your person, but meeting people and having the courage to share about your health issues, even if there are heartbreaks and disappointments along the way.
Deciding to have a baby and discussing family planning, despite all the what ifs and becoming a parent because that’s what you hoped for prior to your IBD.
Landing that dream job with your IBD in your back pocket, not letting the detours stop you from finding the path you were meant to go on.
Celebrate the independence you’ve discovered
The list goes on and on! No matter how old you are when diagnosed with IBD, in that moment we are robbed of our naivety and thoughts of invincibility, and we’re forced to go on a lifelong war and conquest. Our bodies no longer feel like ours. Our dreams feel in disarray. Our people may change and not be who you thought they were. Our hearts may break, but like a phoenix this disease can build you up just as much as it breaks you down.
The reprieve of remission, while not perfect or without symptoms has enabled me to breathe and regain my grounding. In 2015, after three back-to-back bowel obstructions and 18 inches of my small intestine, Meckel’s diverticulum, and appendix removed, there was only one way to go and that was up.
Give yourself grace. Celebrate the independence you’ve discovered that you may not be able to have realized until you’re years out like it took me. And when you’re in the hospital, in for a routine clinic visit or for labs, taking your meds and balancing every daily decision against how it will make your IBD feel, you’ll come to realize what you take on and all you accomplish every day just to survive and thrive, makes you something special. While you may feel dependent on others—and the support of caretakers and a support system can’t be understated, neither can the endless strength that lies within you.
Chronic illness forces you to wear many hats and approach life in ways you never thought possible. One of those hats is being an investigative journalist or sleuth. Each time something starts going awry with our health we immediately start the mental gymnastics about what could be going on and if the symptoms are linked to our IBD.
I find that even though my Crohn’s has been in remission since August 2015, that the next flare always looms in a cloud of worry when I’m not feeling my best.
This past week I experienced this firsthand when my eyes both started twitching nonstop, along with headaches. I started thinking about what I could have done to trigger this bodily response. Was it Crohn’s related? Hormonal from breastfeeding weening? A mineral deficiency? A problem with my eyes or vision? Sleep deprivation or stress? The laundry list of possibilities and worries weighed heavily on me. After consulting with my GI, OB, and having an appointment with my eye doctor, I learned the eye twitching was a result of allergies. I now do eye drops once a day to help. It was such a relief to get an answer and physically be able to do something to make myself feel better.
When you notice an uptick in IBD symptoms or health issues in general how do you get to the bottom of what’s going on?
Here are my top tips for getting answers:
•Be proactive. Don’t let things fester and let your anxiety get the best of you.
•Take physical notes, not just mental ones. As the hours turn to days it can be difficult to remember when symptoms began and if they progressed. Keep a simple log of what is happening, how often, the severity, etc.
•Reach out to care providers early and often. Send a quick message on the patient portal informing your GI about what is going on. With IBD, I find it helpful to always loop my gastroenterologist in since so many issues are often related to Crohn’s.
•Be seen. If symptoms don’t resolve in 3-5 days, it’s a good idea to be seen in person or at least a telehealth appointment. You can always get on the books and cancel an appointment if you start to feel better.
•Try not to Google too much. While this is always tempting and can feel like a quick way of gaining understanding, it also can lead to going down a dangerous rabbit hole of what ifs that possibly aren’t even relevant.
•Listen to your gut. You know when something feels off. Don’t drown out how your body is speaking to you through symptoms.
•Practice mindfulness and calming exercises. It’s not unusual to feel up against a wall or like you’re taking two steps forward and one step back with chronic illness. Remember to breathe. Take a walk outside to clear your head. Do all you can to rest your mind from stresses that can trigger your IBD.
I get how exhausting it is to constantly feel at odds with your body and worry about what could be going on. Suffering in silence and not communicating health challenges only sets you back from feeling your best. Be mindful of how you feel each day and feel empowered by collaborating with your care team and giving them all the necessary intel to have the full picture when figuring out your health story past and present.
Stay tuned for a special discussion on IBDLyfe, Wednesday June 29, 2022, at 1 pm CT about “How to Be Your Own Best Advocate in a Provider Setting.” I’ll be speaking alongside fellow patient advocate, Tina Aswani Omprakash. Register here.
This blog article is sponsored by Portal Instruments. All opinions and experiences shared are my own.
I’ll always remember how I felt the moment I was told I needed to go on a biologic drug to try and manage and control my Crohn’s disease. It was Fourth of July weekend 2008. My gastroenterologist walked into my hospital room and told me it was time to “break out the big guns,” meaning starting to get medication through an infusion or through a self-injection. I was a morning news anchor at the time in Wisconsin, three years into my patient journey. I knew without a doubt, for privacy reasons, and keeping my chronic health issue under the radar, that doing an injection in the comfort of my apartment was the best choice. As I watched the fireworks reflect off the hospital room window with my mom, tears flowed down my face. I didn’t know how on God’s green Earth I was ever going to be able to give myself an injection for the rest of my life.
I was never a huge fan of needles prior to my diagnosis. Once you have Inflammatory Bowel Disease, needles unfortunately are all part of it. While we may get desensitized, patients would give anything to be able to treat their disease without needles. When I started on my biologic, my mom and I went to my gastroenterologist office and a nurse told me I needed to do four, painful injections in my thighs because at the time I didn’t have enough fat on my stomach. I was shaking like a leaf. I had no idea what to expect, I was about to inflict pain on myself, the injector felt so foreign in my sweaty palms, and I was scared about not only how much it was going to hurt, but also the long-term side effects the medication could cause to my body.
I did the first injection and it felt like liquid fire burning through my skin. I couldn’t believe I had to sit there and do three more, back…to back…to back. The experience was traumatizing. When I finally did all four, my mom and I walked into the hallway and I embraced her, crying because of my reality, and knowing that in two weeks I would need to inject two more needles into my thighs for the final loading dose. Since July 2008, I’ve done a self-injection every other Monday and for a short time weekly, while I was flaring. That’s more than 2,600 shots.
Dreading “shot day”
The first few years I would absolutely dread my “shot day” and deal with the looming dread each week. Early on I would get emotional during the process and feel bad for myself. I was only 25 years old. It made me feel like I was a sickly person. My peers couldn’t relate. It was isolating and overwhelming. Every time I open my fridge, the box of injections is staring back at me as a constant reminder of what’s to come.
Doing my injections as an IBD mom
Fast forward to present day, I’m now a 38-year-old mom of three. Luckily, the formula for the medication was changed in 2018, making the drug virtually “pain-free”, but there are times I still feel the needle. Even though I have my medication process down to a science, I still wish I didn’t have to do it and I usually wait until Monday nights to do it. The timing is moreso out of habit, because when I was a morning news anchor there was no way I was going to deal with an injection at 2 a.m. I started a tradition of doing my injection while watching the Bachelor/Bachelorette, and that’s carried over now that I have three young children, often waiting until after their bedtimes. Each time after I’m done with my shot, I text my mom to let her know how it went. She’s a nurse and has been my greatest support with my IBD since the day I was diagnosed.
Sometimes my 5-year-old and 3-year-old watch me do my injection and each time they are intrigued. I’m sure my 11-month-old will be the same once he starts to gain an understanding of what I’m doing. It makes me sad that they often witness me doing my injection, but they are also my greatest motivation to be strong and smile through it. Watching me doing injections has made my kids incredibly brave at the pediatrician when it’s time for them to get their immunizations. Because I have little ones, I have to be mindful of disposing of my medication properly and keeping the Sharps disposal container out of harm’s way. We keep Sharps Containers up high in a cubby hole in our laundry room and I dispose of the injector pen immediately.
As an IBD mom, my greatest fear is passing along my Crohn’s to my children. While the risk is low, it’s there. I hope and pray my children won’t ever need to receive a biologic medication whether it’s through self-injection or infusion. For me, there’s no end in sight, I’m expected to be on my medication (if it remains therapeutic) for the rest of my life. Thinking of my babies having to deal with needles and being forced to inflict pain on them would be difficult for me and only add to the guilt.
The future holds so much promise when it comes to drug delivery without a needle. My hope is that in the years to come, other people won’t have to succumb to the same anxiety, pain, and worry I’ve had to deal with for more than a decade.
Saturday my husband and I celebrated our sixth wedding anniversary. Special milestones like this tend to make us all reminisce about the past, present, and the future. When you live with IBD many of those memories and the current reality are from flare ups, hospitalizations, procedures, recoveries, and simply navigating the day to day. While Bobby has been a part of my life for nine years (next month!), I spent the first eight years living with Crohn’s disease, without him—in my 20s.
During those eight years I experienced many heartbreaks and disappointments when it came to trying to find my person. To give you the cliff notes version—my boyfriend who I was dating when I was diagnosed never visited me during a week-long hospital stay and broke up with me while I was in a wheelchair over the phone after getting discharged and going into my parent’s car. Then, I dated a guy who refused to drive 3 hours when I was hospitalized for an abscess the size of a tennis ball in my small intestine, because “gas prices were too expensive” (can you imagine how he’s handling the prices now, HA!) and he wanted to go fishing. Another moment that makes me shake my head to this day is when I had to cancel a first date because I was doubled over in pain on the bathroom floor and was heading to the ER and he texted me that it was a poor excuse and laughed at me.
While I could have seen my Crohn’s disease as a scarlet letter and settled with a person who clearly didn’t have a genuine heart, I used my IBD to guide my decision making and it brought me to the relationship and the person I was meant to be with.
So, while I was out to dinner over the weekend looking across the table at my husband and the man I have three kids with—a man who has taken my disease journey and everything that’s come along with it in stride, I not only felt an immense sense of gratitude but also want you to know that your disease can give you superhuman clarity when it comes to helping you weed through the people who aren’t your person. This week on Lights, Camera, Crohn’s a close look at love and relationships and the tremendous support our romantic partners are, while also speaking to those who are single and struggling to see themselves as anything but a burden. I hope this article shows you the incredible relationships so many of us in the IBD community have been able to have, despite our disease—and remind you that you are worthy of all that love has to offer. Your disease does not make you less than. You deserve the same respect, consideration, compassion, and unconditional love as everyone else.
How does your partner go above and beyond?
I tapped into our community on Instagram and asked: “How does your partner support you?” By reading the countless messages it just goes to show, it is possible to find a partner who sees you for more than your IBD. Someone who loves you for all of you:
“Taking care of the house, speaking up for me at appointments, fighting insurance when I can’t anymore, and listening to me.”
“Knows what I can and cannot eat and makes sure there’s food available that I can tolerate.”
“I’ve got a winner, there’s too many things to type in this small box! Will make a late-night food run because of my limited options with a flare or let me pick a meal. Shows support by driving me to colonoscopies, even if it means missing work.”
“They listen when I “complain” and offer solutions when I don’t feel well.”
“Attends most of my doctor appointments with me.”
“When I’m ill he takes over with our son and cleaning, orders takeout, and rubs my back.”
“Encouraging me to rest, especially to flare and then taking care of the house and baby.”
“Dealing with insurance and appointment scheduling so I can focus on other stuff.”
“I could go on forever but knowing my needs even when I don’t want to ask for help.”
“Helps me believe good days are coming. Asked, “where are we going on our next adventure?” while walking me around the hospital unit. Listens. Is present. Helps without being asked. Considerate. Kind. Empathetic.”
“He takes on more responsibility around the house when I’m not feeling well and comforts me!”
“By listening, learning, laughing, and trusting me.”
“Ricky is my rock. He is steadfast and always levelheaded.”
“He takes care of the kids and keeps the household running when I’m out of commission.”
“Understands the importance of rest, diet, low stress, and medications.”
“He got a Crohn’s and Colitis shirt and wears it on my bad days or procedure days to show support.”
“My husband doesn’t “do sick” well. He has never been sick since I met him 10 years ago. So, it was very hard for me during my first flare up as his wife. He did not tolerate me being sick at all. He kept telling me not to “identify” with the illness and manifest good health. At the time it was torture. I felt so alone and didn’t feel any compassion from him. He is a “mind over matter” person and has been helping me manifest a strong, healthy body. He supports us by living a very healthy lifestyle. He gets me up every morning to work out with him, no holistic treatment is too expensive. He is giving. Sacrifices everything for his family. Even though he is different from me, I’m forever grateful for his approach because I have never been healthier!”
“When I’m in a flare he takes care of the kids and cleaning so I can rest and not stress while I’m sick. Helps me feel comfortable and confident managing my Crohn’s.”
“In ever way. He never asks more of me than I can give at that moment.”
“Being by my side before I even have to ask.”
“He’s my cheerleader on injection days!”
“He understands if I need to stop driving often.”
“Does more than his share of chores. Eats safe food dinners with me. Hugs me when I cry and so much more!!!”
“My husband is truly a miracle. Diagnosed as newlyweds, never in remission. His thoughtful intentionality and his presence make me so proud and lucky. I couldn’t do this without him.”
Fears about finding your person
Now on the contrary, those who are single and struggling to find their match may hesitate to put themselves out there for many reasons. Chronic illness and love can be overwhelming. I asked the following question on Instagram: What worries you about love and IBD?”:
“They will not accept my permanent ostomy and think it’s gross.”
“Thinking I’m less fun because I don’t want to go out as much and need to rest more.”
“Feeling less than. Who wants to deal with going IBD/fibromyalgia? ☹”
“Honestly, everything…like how and will they truly be there at my worst.”
“Being considered too much baggage!”
“Why would someone choose to love someone who’s sick all the time?”
“That my husband would get tired of my lifestyle and not feeling well all the time and leave.”
“That they won’t accept my ostomy—how long do I wait to tell them? It’s hard.”
“How to tell someone when you first start dating. Men not wanting to deal with it.”
“Fearful I won’t have the energy to keep up with activities, dates, etc.”
“My wedding day—how I will feel! I’m far from that stage of life, but I worry about this often.”
“It’s hard enough to find a man, let alone one that can handle IBD life.”
“That I won’t be accepted. I’ve had to get dentures because of Crohn’s.”
“They won’t accept me for my disease, and I will be a burden to them because I’m sick.”
“That someone will get tired of dealing with my health issues. That I will burden them too much.”
“I worry about rejection and being a burden to a potential partner.”
“I’m not single, but my biggest fear is one day my spouse will wake up and realize this isn’t the life he wants and that taking care of me is too big of a sacrifice. That he’s run out of energy to give and needs to take care of himself (do what makes him happy). I don’t know what I’d do without him.”
…
Woah. How heartbreaking and relatable are those comments?! First, I want you to read an article I wrote awhile back that addresses the term “burden” as it relates to love and IBD. While it can be incredibly intimidating to share the fact you have IBD and everything that comes along with your personal case (scars, ostomy, flaring, need for hardcore medications, etc.), it’s all a part of you and if someone you are dating is going to pass judgement or be “turned off” by that, I’m telling you now RUN FOR THE FREAKIN’ HILLS. As you date, don’t settle for anyone who makes you feel guilty for something that’s completely out of your control. Let your IBD shine a bright light on someone’s true colors. Same goes for friendships. In the moment it can be shocking to see who is there and who is not, many people will surprise you—and not in a good way, but take that intel and keep your inner circle made up of people who you can trust implicitly and be yourself completely with.
When it comes to disclosing—you’ll know when the moment is right. For me, I told my husband on our third date while we were out to lunch. You don’t have to get into the nitty gritty, just put it out there—a high level explanation—and let them ask questions. In that moment you will be able to gauge their interest. Bobby didn’t bat an eye. To this day he reminds me I’m a healthy person, aside from my intestines. Don’t wait too long to share about your IBD so you don’t invest time and energy if they aren’t going to be worth it. If you’re lying in a hospital bed and feeling neglected or alone as you face serious health complications, it’s time to take a serious look at what you want and what you need in a relationship. I promise you will not regret breaking up with someone who makes your life and emotions complicated.
I can still remember crying in my parent’s bedroom after being diagnosed with Crohn’s and dealing with a breakup during the same week. I was 21. It felt like my world was crashing and burning. I wish I could hug that girl and tell her not to worry and that she’d be a happily married mom of three kids who rose above and didn’t settle. Love and IBD doesn’t have to be scary, it’s something really special.
When something traumatic happens—like the mass shooting in Uvalde that left 19 children and two adults dead last week, the stress, sadness, and overwhelming grief can cause IBD to spiral out of control. You are not alone if the heavy nature of what’s happening in the world causes your mind to race and your GI symptoms to be amplified. As May (Maternal Mental Health month) comes to an end, a look at how we can best navigate these emotions and how our thoughts impact the gut-brain connection.
Looming threat of flares and violence
With the constant news cycle that bombards us, added into our reliance on social media, and seeing everyone’s opinions and posts, it’s the perfect storm for feeling suffocated by sadness. Life with IBD, whether you are in remission or not, is living with the looming thought of when your next flare or hospitalization is going to be. You know in your heart of hearts that it’s not a matter of if, but when your IBD is going to rear its ugly head. These days with violence happening left and right, it’s a challenge not to wonder and worry when you’re out in public if you’re going to be in the wrong place at the wrong time or if your children are in harm’s way.
The anxiety of worrying about the “what if” and the pain of grieving can often correlate to actual physical pain in our bodies that are already fighting an uphill battle. It’s difficult to try and make sense of what’s going on in the world. It’s impossible to try and wrap your brain around how people can be so evil. As a mom, I found myself crying putting each of my kids to sleep last week. Snuggling them a little longer. Worrying about their wellbeing and praying as hard as I could over them.
As a former news anchor and journalist, I vividly recall the moment the news of Sandy Hook broke. I was standing in the newsroom, about to head out to the studio to anchor the Midday show, when the heartbreaking news came over the newsfeed. It was incomprehensible then and it’s even worse now as a mom of three. I have only been able to watch the news in short snippets right now because I felt like the sadness of it all was consuming me in an unhealthy way. There’s a guilt that comes with trying to tune out the coverage and feeling like you’re not giving the reality of other peoples’ heartbreak the attention it deserves, while trying to protect your own mental state and heart.
Dr. Lindsay Hallett (Zimmerman), PsyD, is a clinical psychologist in Indiana. Here is her advice for coping:
Give yourself half the grace you give to others. This can make a significant difference in your overall well-being and stress level.
Reach out. If connection feels like what you truly need, enlist a friend or relative. The higher the level of personal connection, the better- seeing a friend is preferable to FaceTime, a phone call is preferable to texting, etc. But also, any connection is better than none.
Make time to move. Time is a premium to everyone and even 15 minutes will do. Listen to your body and give it what it needs – stretching, a walk, an intense workout, gardening… any kind of movement that respects your body’s own capabilities.
Give yourself permission to check out. If everything feels to be “too much,” avoidance can be healthy. Communicate healthy boundaries with others that you can’t talk about topic XYZ right now.
Seek therapy. Your emotional house doesn’t have to be “on fire” to benefit. Ask your primary care doctor, contact your insurance company, or research PsychologyToday.com to find a therapist. In-person with occasional virtual supplementation is best, but online therapy platforms can be helpful if you aren’t having luck otherwise.
Give yourself permission to unplug and stop doom scrolling. While there is no “right way” to cope with traumatic events like what happened in Uvalde and so many times before, give yourself permission to feel whatever complex emotions you are experiencing while also giving yourself space and time to take breaks and turns off screens. When you have IBD, being cognizant of what triggers you and recognizing how your symptoms speak to you, can allow you to stay one step ahead of the game in managing your illness. Focus on what’s tangible, what’s right in front of you, and what you are able to control.
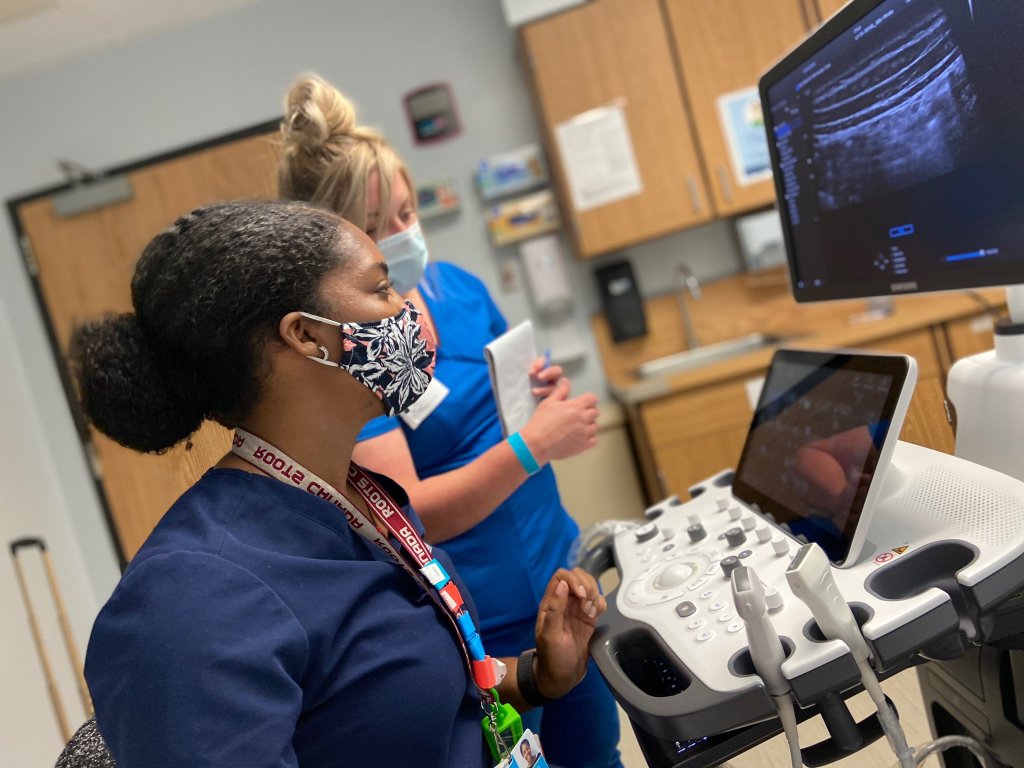
Innovation and changes in healthcare are propelled by patients and caregivers speaking up about improvements that can change the way IBD is treated and managed. This week on Lights, Camera, Crohn’s we hear from pediatric gastroenterologists Dr. Michael Dolinger, MD, MBA, Advanced Pediatric Inflammatory Bowel Disease Fellow, Ichan School of Medicine at Mount Sinai and Dr. Mallory Chavannes, MD, MHSc, FRCPC, Pediatric Gastroenterology, Hepatology and Nutrition, Children’s Hospital Los Angeles about the benefits of Intestinal Ultrasound (IUS) becoming a part of routine care, regardless of age.
The goal of IUS is to utilize a non-invasive method to monitor disease activity over time and it’s considered to be more precise than endoscopy in identifying both disease location and characterizing the severity of IBD. The IBD community—both patients and caregivers—can help fuel the adoption of IUS and gain access to receiving more information about their disease activity than ever before.
What is Intestinal Ultrasound (IUS)?
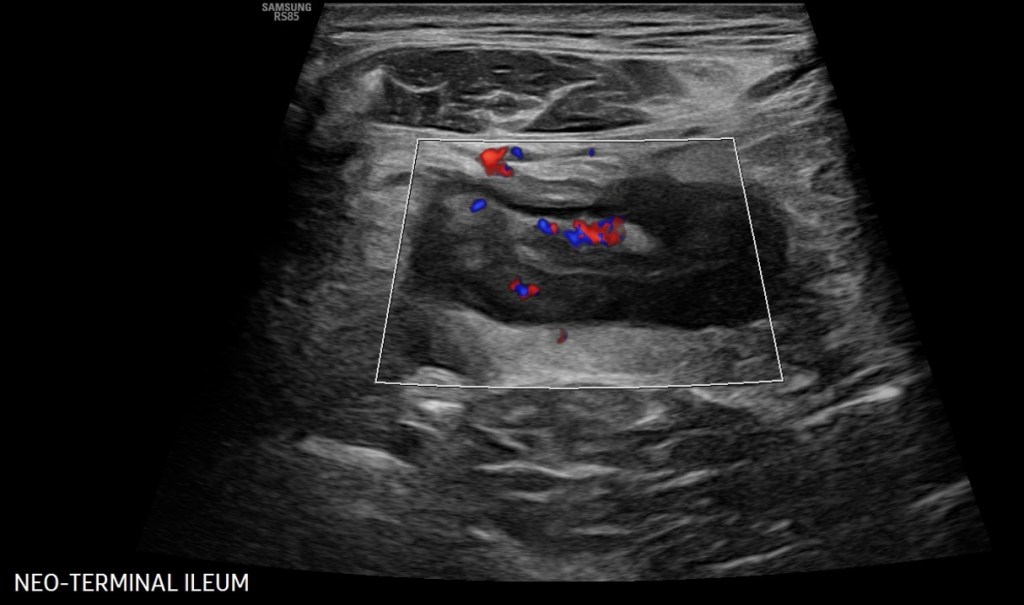
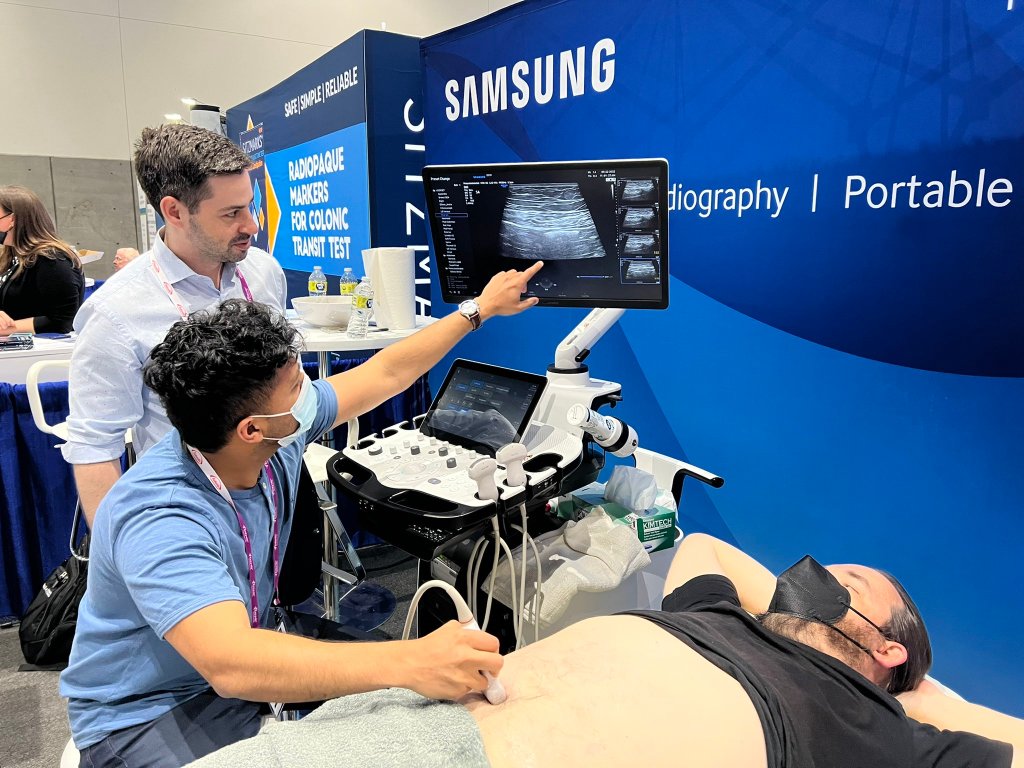
Intestinal Ultrasound (IUS) is an abdominal ultrasound performed during a routine clinic visit without preparation, fasting, or contrast to assess both the colon and the small intestine (terminal ileum most frequently) for the presence of disease activity. Probes are placed over the abdomen and the provider looks at images of the small and large bowel.
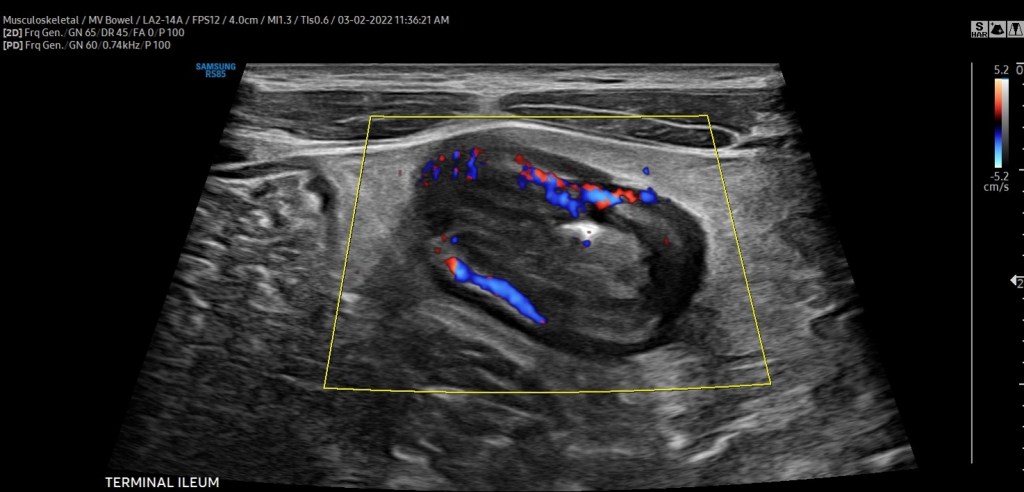
“The beauty is that, unlike procedures and other image modalities available to assess disease activity of inflammatory bowel disease, IUS can be performed without any preparation or fasting,” said Dr. Chavannes. “In the setting of active disease, patients can have a thickened appearance of the wall of the bowel (termed increased bowel wall thickness) in both the small intestine and the colon, which can be detected via ultrasound.”
In addition, by using color Doppler, a feature that assesses the velocity of blood flow within and around the bowel wall, gastroenterologists can demonstrate inflammatory activity in the bowel wall. IUS can also detect IBD complications, such as fistulas, abscesses, or strictures (narrowing) of the bowel.
“Our expectation is that, with effective therapies, the aforementioned features of disease activity should improve or even disappear over subsequent clinic visits. If they do not, we now have an objective tool available in the clinic that can assist clinical decisions, such as ordering further investigations or even optimizing or changing therapy. Improvement of bowel wall thickening or decrease in color Doppler signaling is a reassuring sign that treatment is working. Lack of improvement signifies that optimization or changes in therapy should be considered,” explained Dr. Chavannes.
“Intestinal ultrasound is precise, we monitor bowel wall thickness down to the 0.1 mm. We are now able to make informed decisions with patients together, assessing their disease objectively in real-time so we can be aligned with our treatment goals. This reduces misunderstanding and may lead to better treatment adherence and improved outcomes,” said Dr. Dolinger.
Why the delay in the United States?
While IUS isn’t the standard of care across the world, it is used in several Canadian IBD centers and in Europe (Germany, Italy, Norway, the Netherlands, and Australia to name a few). However, there are still many areas of Canada and countries in Europe where this is not used as part of routine IBD care.
“There have been several barriers to adoption in the USA, the biggest of which are reimbursement and the lack of training/expertise. However, that is changing, as there is a tremendous amount of interest from most major academic centers,” said Dr. Dolinger. “Through the International Bowel Ultrasound Group (IBUS) there is now a formal training, while intensive, that can be completed by anyone willing in the USA, which did not exist 5 years ago.”
IUS fits perfectly in the treat-to-target algorithm by adopting a monitoring strategy that helps to prevent flares and bowel damage.
“There is no other test for patients to see their disease dynamically with a gastroenterologist in real-time, which enhances shared understanding and informs decision making like never before. All of this will help break the barrier in the USA and around the rest of the world,” said. Dr. Dolinger.
A study conducted in 2016 explored why IUS is not standard of care in the United States. The
authors surveyed nearly 350 physicians, of which 40% were pediatric gastroenterologists. Although a minority of gastroenterologists were using ultrasound to assess and monitor IBD (either bedside or within the radiology department), over three-quarters expressed interest in using it more.
“The main limitation identified or perceived by gastroenterologists who responded to this survey was a concern for inter-observer variability, a lack of familiarity with ultrasound indications and techniques, and a lack of interest and access to pursuing additional specialized training. In addition, the survey identified a common message that I have received previously from some radiologists; that other modalities are more precise or effective in assessing IBD. All these reasons can hinder interest and implementation,” said Dr. Chavannes.
However, considering the multi-center effort in disseminating training, knowledge, and engagement that has been ongoing in the USA in recent years, Dr. Chavannes is hopeful that IUS will rapidly become the standard of care nationwide.
How Children’s Hospital in LA and Mount Sinai in New York Use the Technology
The Henry and Elaine Kaufman Intestinal Ultrasound Program at Mount Sinai is one of the first in the country to employ the training of gastroenterologists and regular use of intestinal ultrasound for both children and adults routinely in the IBD center for non-invasive disease activity monitoring.
“This would not be possible without the leadership of Dr. Marla Dubinsky, who has worked painstakingly hard to bring this to patients at Mount Sinai, overcoming every barrier to lead the way in the USA. We would like patients everywhere in the USA to be able to have tight control non-invasive monitoring with intestinal ultrasound and in turn, are working with International Bowel Ultrasound Group (IBUS) to host the first hands-on training in the USA at Mount Sinai in the fall. We have faculty from around the country signed up to learn and this will hopefully begin to fuel further adoption,” said Dr. Dolinger.
Intestinal Ultrasound was introduced at Children’s Hospital in LA in the summer of 2020. This was incredibly helpful during the pandemic when access to endoscopy time was difficult, considering cancellations due to active COVID infection and decreased daily procedures to allow for intensive cleaning protocols.
“We integrated using IUS for all patients coming to the pediatric IBD clinic. We have seen an immediate benefit in how we approach patient care and how timely clinical decisions can be made right at the time of the clinical encounter. One example is for patients presenting for a second opinion; these patients usually present with ongoing symptoms of varying degrees, yet incomplete or dated documentation of endoscopy, fecal calprotectin (a stool test helpful in indicating inflammation), and blood work,” said Dr. Chavannes.
During the visit, IUS gives an opportunity to understand the source of the symptoms experienced by patients and the degree of ongoing inflammation. Then, clinical decisions can be made that day, eliminating the need for additional testing. Dr. Chavannes says IUS even helps ease the discussions she has with parents and families.
“Many parents are stunned by the images they see and the changes over time. At the same time, they also notice when there is little difference from one appointment to the next, understanding the reason we are making the changes to the management plan that follows,” said Dr. Chavannes. “IUS has been invaluable for children under 6 years of age. This vulnerable population needs frequent objective reassessments, which is not possible otherwise. Using MR-Enterography would require general anesthesia, and access can be difficult. Similarly, for endoscopy, the prep can be poorly tolerated, and it also requires general anesthesia. IUS is non-invasive, painless, very well tolerated in young children, and available in real-time. Therefore, both parents and children are quite satisfied with their experience with IUS.”
Targeting treatment through IUS
Monitoring symptoms alone is not effective in reaching deep healing of disease in IBD, as many patients feel well despite having ongoing intestinal inflammation. IUS evaluates the inflammation that occurs within the thickness of the bowel wall (transmural inflammation).
“We often find that ultrasound is the only tool that shows continued inflammation when patients are in remission and labs have normalized. Optimizing therapies based on persistent inflammation seen on ultrasound may prevent us from falling into the trap of thinking our medications are working when our patients feel better and thus lead to better outcomes by not missing persistent inflammation that we have continued to miss with traditional monitoring strategies,” said Dr. Dolinger.
Although there are no fully established algorithms for the frequency of monitoring IBD using IUS, the best approach appears to have a baseline IUS at the time of IBD diagnosis or in the context of active symptoms or elevated inflammation markers on blood work (a flare).
“Then, the clinician can understand the features to follow over time. A repeat IUS can be performed at the end of induction treatment to assess how effective the management is. It would represent 6-8 weeks after the treatment was started. Provided that there is a marked improvement, the subsequent evaluations with IUS can be done every 3-6 months unless there are new concerns, with the closer timeline early in the disease course,” explained Dr. Chavannes.
In pediatric patients, this routine ends up matching most routine clinic visits. Therefore, as IUS becomes standard practice, and depending on how a patient is doing, their symptoms, and last assessed disease activity, patients can expect IUS as often as with each clinic visit. This modality would complement blood work and calprotectin stool tests in informing about disease activity and for complications of disease or flares.
What the future holds
Since a few IBD centers in the United States have already implemented regular IUS in their practice and have been disseminating knowledge about this technique, there is growing interest from pediatric providers to join the movement as well.
“Considering the challenges pediatric providers face in access to complementary imaging, operating room time, anesthesia exposure to endoscopy, and even the tolerance drinking contrast for radiology studies, IUS offers a fantastic way to assess disease activity in the pediatric IBD population. I am excited about the number of pediatric centers that have reached out about getting expertise in this field. The key is to promote buy-in from leaders in each institution to get the time and resources required for training and implementation,” said Dr. Chavannes.
Advice for patients and caregivers
It doesn’t hurt to bring up IUS at your next clinic appointment to gauge where your care team stands and if anything is in the works.
“If your provider is unaware of IUS and its benefit, it would be great to talk to them about the International Bowel Ultrasound Group. The curriculum for getting training involves three modules: an introductory module, a 4-week hands-on training at an expert center, and a concluding module and examination part of the European Crohn’s Colitis Congress,” said Dr. Chavannes.
She went on to say that hearing this request from patients may motivate administrators to provide the necessary time clinicians who are interested in getting expertise to implement the tool at their center would need.
Dr. Dolinger believes most major academic IBD centers in the United States will rely on IUS in the next 3-5 years.
“I would like to remind patients to be patient with their providers. Ensuring correct training and standardization is essential for adoption in the USA and this takes time and rigor to be done right and change the monitoring algorithm which has not been done in many years,” said Dr. Dolinger. “I began training in 2019 and it wasn’t until the second half of 2021 that we began using it very routinely for decision making, taking 2 years to become an expert. So, this will happen, but it will take some time.”
Patients and parents are big fans
The safety and efficacy of IUS can’t be matched. It’s also a big-time saver for everyone involved. A bedside ultrasound can be performed in a range of 20 minutes for the first thorough assessment, while an even more focused exam in a known patient can take less than 10 minutes.
“Both parents and children have been quite satisfied after their experience, as children can go back to school after the clinic despite undergoing this examination. Furthermore, the time saved in skipping additional appointments with the radiology department or procedures can be invaluable,” said Dr. Chavannes.
For parents, the imaging provides reassurance when there are improvements or when there are non-specific symptoms, yet the IUS is normal. IUS also bring validation when there are abnormal findings and helps to provide an explanation for why children are feeling a certain way.
“Children appreciate that it does not hurt and takes little time in addition to their clinic visits. In addition, they may not require additional appointments in radiology or endoscopy. Parents who had an opportunity of experiencing an ultrasound often request it afterward as part of their clinic visits. These families are more engaged and participate in shared decision-making. I am pleased and impressed at the engagement that actually “seeing” the disease together brings from families,” said Dr. Chavannes.
While the push is for IUS to be available to all IBD patients, both children and adults, it’s specifically beneficial for the management of pediatrics as it provides the unique opportunity to prevent bowel damage for a person’s entire life and reduce the need for invasive procedures, anesthesia, and sedation. IUS has the potential to alter scoping schedules in the future. While it will not replace the need for colon cancer screening or the assessment of mucosal and histologic healing, IUS can reduce the need for further follow-up scopes once those targets are achieved in between the need for cancer screening.
This week I was feeding my 9-month-old a smoothie in his highchair before I had to run to grab my older two from preschool. I realized it was an injection day, so I figured I would do my shot while the baby was in the highchair to get it out of the way. It seemed like no big deal in the moment. But as I sat there and saw the baby food next to my Humira on the kitchen table I started thinking about how life as an IBD mom may feel normal to us, but what we do each day goes above and beyond.
Then my mind started wondering. I thought about how I had taken my oldest to his outdoor fieldtrip last week and refrained from having my morning coffee or eating breakfast so I could curb my Crohn’s from causing me problems. I thought about how my 3-year-old is so intuitive if she thinks I’m in pain, she grabs my belly and pretends to put the pain into her belly, telling me “I love you mama, take a breath.”
Take a breath. Boy oh boy do mothers in general need to stop and take that advice or what? Motherhood whether you have IBD or not is the most beautiful, exhausting, and rewarding challenge. No matter what season you are in it comes with triumphs and challenges it comes with happy tears and sad ones, too. It’s a constant game of trying to manage your emotions and tap into your patience, or whatever is left of it each day. We come to forget that we are also growing up in many ways, just as our kids do.
Motherhood and IBD is a balance of wanting to be all the things but knowing that at any given moment your body can throw your life and plans upside down. There are unspoken limitations.
It’s silently worrying and praying what will happen to your family if you go down and end up in the hospital.
It’s trying to stand tall when all you may want to do is rest on the couch.
It’s seeing your children thrive and feeling so much pride you constantly feel like you can cry tears of joy at any moment.
It’s getting scared when your little one randomly says their tummy hurts.
It’s knowing that your disease robbed you of a great deal—physically, mentally, emotionally, but it didn’t rob you of the greatest gift of all, being a mom.
It’s recognizing all that is still possible, even with this grueling disease.
It’s showing up each day, not only for yourself but for your family.
It’s taking the pain and feel-good days and focusing on one moment in time that feels slow but is going by in a flash.
Take a breath. You deserve it. We weren’t meant to mother alone. Lean on your village. Voice your struggles. Cry if you want to cry. But also, don’t put yourself to unattainable expectations. You have a chronic illness and you’re a mom. Don’t push yourself to the brink. Some days will be adventure-filled, others will be spent on the couch—and that’s OK. Your children are learning from you and gaining innate intuition, and that’s a gift. They’re witnessing that health is not something to be taken for granted. They’re watching you even when you think they are not. What may feel mundane to you, is not. As an IBD mom you are juggling countless extra balls in the air that healthy mothers don’t have to think about. Give yourself credit where credit is due and take a breath.
Moving away for school. A future career. Relationships. Discovering your identity. Switching from a pediatric IBD care team to adult providers. All while living with a chronic illness. This is the stark reality for young adults living with Crohn’s disease and ulcerative colitis. Juggling all these major life milestones and having to get acclimated to new physicians while taking the lead on disease management is often met with anxiety and worry from young patients, their parents, and caregivers. IBD is a family disease. Even if only one person in the household personally lives with the issue, the disease impacts each person.
This week on Lights, Camera, Crohn’s we hear from patients and caregivers who have lived through the experience and from pediatric GI’s about how best families can be supported through the changes to make them as seamless as possible for everyone involved.
Input from those who have made the switch
Aging out of pediatric doctors can be a stressful time for everyone involved. Let’s start with input from those with IBD who have made the switch along with what some parents and caregivers had to say.
Start researching doctors early. Do your homework and see what insurance providers accept and what hospitals they are affiliated with.
Ask your current pediatric doctors for recommendations/referrals.
Before the first visit make sure the adult GI has received copies of medical records.
Have healthcare proxy and power of attorney papers on file.
“I just turned 20, but I’m still in pediatrics and plan on staying until I graduate from college, as that is the norm at my hospital. However, as an adult in peds, I found it important to have healthcare proxy and power of attorney papers on file so my mom can still help me and if something were to happen like while I’m away at school she is able to get information. I broke my arm this past fall and my body went into such shock that I couldn’t give the hospital any information. My friends were with me and contacted my mom, but because I was 19, the hospital couldn’t even confirm to her that I was in the building. This was a wake-up call. We started thinking about, “what if this was my IBD?” and decided it was necessary to have the papers on file just in case. I still ask my mom to be involved in my care, but we both have the understanding that I have the final say.”- Anna
Navigating the switch through college
Heidi was diagnosed with Crohn’s when she was 9. She’s now 41. When she reflects on the transition from a pediatric doctor to one who treats adults, she recalls the process being fairly simple and a change she welcomed with open arms.
“The best thing was being talked to directly and my opinions mattered more in my later teenage years with the new doctor. Of course, my parents had my best interests at heart, but appointments were so frustrating as a young girl. Another reason for the seamless transition was that my new doctors were amazing. I switched at 18 and then again at 22 when I graduated college and moved away from home. My care team listened to me and saved my life. I know I’m lucky to have found such a wonderful team of doctors.”
Katie wishes there had been a support group (even online) for teenagers back when she was phased into an adult GI. She says when she was diagnosed with IBD at age 15, she often felt uncomfortable discussing her symptoms and didn’t feel her pediatric GI was that great with kids.
“I felt detached from my GI until I was in my 20s and had the confidence to advocate for myself. I was so lost and refused to tell classmates what was wrong with me for fear of being made fun of. I ended up missing so much school I decided to drop out, get my GED, and go straight to college. It was a terrible time to be honest.”
The difference in pediatric vs. adult care
“The transition happened quite fast as I was being referred to an adult surgeon for my complications that the pediatric team were not experienced or educated enough to treat for Crohn’s. I was thrown in the water with no guidance when I started seeing physicians who treated adults with Crohn’s. The pediatric GI team would dumb some things down for me and make my problems not seem “as bad.” As soon as complications started arising, they threw the towel in and basically told me they couldn’t help me anymore and would be better off seeing a care team with more experience with my symptoms and complications.”-Chrissy
Natasha experienced the transition about 13 years ago. Her pediatric team helped her choose an adult GI. And the guidance didn’t stop there.
“My pediatric GI told me who she wanted for me and then went with me to interview the doctors in the adult team. Once I chose, my pediatric GI attended every appointment with me until we all agreed I was ready to move into the next step of my care, which luckily was quickly. And the two doctors stayed in communication. My advice—be open with your doctor.”
Natasha recommends asking yourself the following questions to help streamline the process and make it less nerve-wracking.
What are you looking for in your next step of care?
What are you looking for during the transition process?
What is important to you in a physician?
Do your own research
“I had an AMAZING pediatric GI when I switched, and I just went with who she recommended. Looking back, I wish I did my research because he is not who I would have chosen for myself. I would recommend doing your own research and make sure whoever you find is willing to work with you and thoroughly go through your medical history and all your results. Too many doctors seem to just think they know everything, but we know our bodies best and need to have a medical team who lets us advocate for ourselves.”-Danielle
Jennie has lived with IBD for nearly 20 years. She has a PhD, works in IBD care, and recognizes she has the privilege of a strong support network and insurance. As an IBD psychologist she recognizes how difficult the system and transition can be for everyone involved.
“I was diagnosed with IBD at 12 and transitioned to adult care around age 18. I was extremely sick at the time and ended up having a proctocolectomy within months of transitioning. I think the biggest things for me were the notable shift in culture between the peds and adult world, and the insurance pieces. It’s so much for kids and families. Lastly. I’ve noticed the transition is nuanced for my parents who were so good at being my advocates, they will still offer to call the doctor if I tell them I am not feeling well, and they have a tough time not having the same significant role they did when I was younger.”
Allie was diagnosed with Crohn’s disease when she was 12. Her mom attended all her appointments until she turned 18, and only stopped going then because she was out of state for college and seeing a pediatric GI there until she turned 22. Allie’s mom kept a medical binder of all her procedures, lab results, and details about her patient journey. She says when she phased out of pediatrics and started taking matters into her own hands, she found the binder her mom made to be beneficial—Allie found herself referring to it when she couldn’t remember everything.
“What helped the transition the most was going to appointments on my own when I turned 18. I felt more prepared to speak for myself when I switched to an adult GI.”
Allie’s mom also inspired her to ask the tough questions. After witnessing how her mom spoke up to doctors it empowered her to speak up and stop minimizing her struggles. By watching how her mom handled appointments, it inspired Allie to write down all her questions and concerns before doctor appointments, so she doesn’t forget anything.
“My mom asked me what fights I wanted her to fight for me and what I wanted to do myself. She guided me on what I might need to ask about when I had no clue—even as an adult she still offers to help call insurance companies to fight authorization battles. She gave me space to live my life when I turned 18. She worried, but she never hounded me for updates (are you taking your medication?, how are you feeling? Are you eating ok?”…but she always conveyed support (both my parents did) when I needed it most she showed up.”
Sari recommends young adults with IBD to ease into taking control of their care as early as possible.
“Things like refilling your own meds, scheduling your own appointments, and driving yourself to appointments goes a long way when it comes to learning how to stay organized and advocate for yourself. You don’t want to be doing all those things for the first time when you go to college or a start a new job—too many scary or unknown things at once!”
Check out what pediatric GI’s have to say about bridging the gap and ensure continuation of care.
Dr. Sandra Kim, MD, Associate Professor of Pediatrics, Director, Inflammatory Bowel Disease Center, UPMC Children’s Hospital of Pittsburgh, says, “Transition is the preparation process while the young adult/teens are still under the care of the pediatric team. Transfer of care is the actual “handoff” when the young adult moves from the pediatric GI team to the adult GI providers. Teens want independence but struggle with disease knowledge and self-management skills. Therefore, the pediatric GI team needs to help the teen (and the family, too!) by being active listeners, communicators, and educators. The healthcare team also should utilize things like transition tools.”
Dr. Kim went on to say that GI doctors need to assess how teens are doing on the road to greater independence and that shared decision-making helps build partnerships between adult and pediatric GI providers.
For the adult GI team:
Collaborate with the peds team in the initial stages of care transfer.
Anticipate existing gaps of knowledge and self – management skills
Prepare for more time during appointments for questions, additional education, and working with the family. Parents need help during this time of care transfer, too!
Woman patient signing medical documents discussing medication treatment with african american practitioner in hospital office during clinical consultation. Doctor physician explaining disease symptoms
Dr. Jonathan D. Moses, Assistant Professor of Pediatrics, Director, Pediatric Inflammatory Bowel Disease Program, UH Rainbow Babies and Children’s Hospital, explained how his hospital has a multidisciplinary pediatric IBD team that engages patients in a Health Maintenance Education Clinic as early as 11 years old.
“This allows them to build up the self-management skills needed for a successful transition to adult GI, when they are ready. In lieu of this resource, parents can engage their health care providers about ways to get their child more involved in their care and provide them with the autonomy, and support, to take over aspects of their care over a period of time.”
Dr. Hilary Michel, MD, Assistant Professor of Clinical Pediatrics, Nationwide Children’s Hospital, says a successful transition from pediatric to adult care requires that young folks have developed the knowledge and skills needed to understand and manage their disease independently.
“This knowledge and skill is not gained overnight, and ideally should be obtained gradually. Transfer to adult care should be planned in advance, when a patient is feeling well and has a good grasp on their disease management, so there are no gaps between peds and adult care. Parents and families can help the process by allowing teens to speak with their healthcare providers alone, gradually share care responsibilities, encourage them to learn about their disease, and highlight their successes.”
How this works in real time:
Patients can listen and participate in their visits.
Set goals with your healthcare team and work toward them, ask questions and share your opinions.
Healthcare teams can help by providing a non-judgmental space, listening attentively, encouraging young people’s success, engaging patients in decisions, checking for understanding, getting to know patients as people (talk about school, friends, activities), and connecting patients with resources
Dr. Whitney Marie Sunseri, MD, Pediatric Gastroenterologist, Assistant Professor of Pediatrics, UPMC Children’s Hospital of Pittsburgh, says “I always encourage a step-wise approach to transitioning to the adult world. I encourage patients to know their diagnosis, what medications they take and when, to recall their last scopes, and to be able to report all of their symptoms without the assistance of their parents. Then as they get older, and closer to the time of transition, I encourage them to look into different adult doctors. I give recommendations as well.”
Dr. Sunseri advises caregivers and patients to be proactive and look at reviews of doctors and who is in their insurance network. She says the most important visit is the one where patients follow up with her after their first adult visit to make sure it was a good fit and that they are in good hands.
“It’s bittersweet watching these children grow in so many ways and head off into the hands of another provider. Your heart swells with pride and breaks at the same time.”
Resources and Communities of Support
Sneha was diagnosed with Crohn’s at age six. She’s now 23 and still figuring out what her future will look like with IBD. As she grew up, she couldn’t find a community of young adults. This inspired her to create Generation Patient and the Crohn’s and Colitis Young Adults Network.
“Peer support during this transition is critical, so we host seven virtual community meetings. We have hosted over 250 of these peer support meetings over the last two years. I think peer support should be seen as essential during this transition period and it has been the best thing to come out of living with IBD.”
Generation Patient: Instagram–@generationpatient
CCYN: Instagram–@ccyanetwork
Join the American College of Gastroenterology Thursday, May 4, 2022 at Noon and 8 pm ET for a discussion about “Empowering Patients Through the Transition of Care in IBD”. Click here to register.
There’s no black and white approach when it comes to managing and treating inflammatory bowel disease. Newsflash—you don’t need to choose between medication and diet (nutrition). You can do both! This week on Lights, Camera, Crohn’s, we hear from registered dietitian and ulcerative colitis warrior, Ashley Hurst, about how her personal patient journey inspired her to look into targeted strategies for improving quality of life with IBD.
Ashley was diagnosed with ulcerative colitis at age 24, but she remembers symptoms starting when she was 7 years old. She lacked support for a long time, so her symptoms became her “normal” reality. When she was in college, she sought help for two years before she finally was able to get a diagnosis.
“I went to several doctors who dismissed my concerns thinking the bleeding was just fissures or hemorrhoids. It wasn’t until I was in a nutrition class in college, that I realized it might be something more. I remember reading about Crohn’s and ulcerative colitis and feeling like I was reading about all my symptoms.”
Finally, the fourth doctor she went to diagnosed her with IBD. She experienced a gamut of emotions ranging from relief to disbelief. More than anything, her diagnosis was a huge financial burden. At the time, she was working 2-3 jobs without health insurance. She couldn’t afford medication or even a colonoscopy bill.
“Since I couldn’t afford medications, I relied on nutrition and my own protocol. Once I was more financially stable, and had health insurance, I was able to start mesalamine rectal enemas and oral tablets, while sticking to my nutrition plan.
A preference for finding the balance between diet and medication
“Nutrition and medication have been lifesaving for me at times and I’ve found I prefer doing a bit of both (and so does my gut!). When choosing what route to go for IBD, often we feel a sense of guilt around taking medications. However, it’s important to remember that with whatever treatment route we go, we must weigh the risks versus the benefits.”
An uncontrolled flare is a risk and can impact our quality of life significantly. If you aren’t comfortable with medications your doctor has recommended, you can always ask what other options are available. It’s important to feel good about whatever treatment route you are taking and remember it’s your body, and your choice—just be prepared to face the consequences of active disease and hospitalization if you attempt to go against medical advice and take matters into your own hands. There is a fine balance distinguishing what triggers you and how best your disease is controlled.
The story behind The Crohn’s and Colitis Dietitians
When Ashley initially worked as a registered dietitian, she didn’t specialize in IBD. But as the years went by, she realized Crohn’s and Colitis patients were her favorite people to work with.
“I felt drawn to supporting IBD patients like myself and saw what a need there was for IBD specialized dietitians. Four years ago, I lost my cousin and close friend who had Crohn’s, and he left a lasting impact on me that further increased my desire to make a greater impact in the Crohn’s & Colitis community. He inspired me to be open about my diagnosis and get more connected with others who have IBD.”
Once Ashley decided to specialize in IBD, she quickly discovered how fulfilling it was to do work that has a lasting impact. Ashley says many people seek their support for IBD nutrition, but often feel like they need to choose one or the other.
“Most IBD research studies on both dietary strategies and targeted supplementation for IBD look at participants that are also on medications. Research continues to show that a combined approach using both medications and nutrition is the best path and can help increase chances of remission. It can be tempting to try and experiment by doing one thing at a time to see what works. However, there is currently no one cure for IBD, so treatments typically do involve a multi-faceted approach.”
As business started booming, rather than create a wait list, she brought on three other dietitians. Ashley and her team specialize in providing medical nutrition therapy for Crohn’s and Colitis patients, but also tackle SIBO, acid reflux, allergies, EOE, and much more. All four of the dietitians on the team have IBD, so they understand the patient perspective and the urgency to reach relief.
“As a team, we’ve had the privilege of working with hundreds of patients with digestive challenges, and we have witnessed the remarkable transformations that are possible. We are passionate about helping people not only find relief but make peace with food again.”
Like a fish out of water concerning diet
Many of the people with IBD who Ashley speaks with express that they were dismissed when asking their provider for a dietitian referral.
“The most common thing I hear is- “I Googled what to eat for IBD and Google left me with what NOT to eat for IBD and I feel even more confused with all the conflicting information!” It’s true, the internet is filled with conflicting information on this topic. This leaves people feeling afraid of food and often only eating just a few “safe foods”. Oftentimes these self-imposed food restrictions are unnecessary and lead to malnutrition, loss, low microbiome diversity, poor gut health, and ironically more symptoms!”
This is where Ashley and her team come in. They help those with IBD sort through all the nonsense and get to what really matters most and what works on an individualized basis.
“We are interested in supporting IBD patients, not just while they work with us, but for the long haul! We equip our patients with tools to learn so that they feel confident navigating nutrition even after they leave. We also offer a variety of free and low-cost educational resources on our website and Instagram for those people who just need a next step.”
How to know if you’re truly “healing” your IBD with food
The first question Ashley asks fellow patients she consults with is—is your nutritional approach working? The only way to know is to confirm through colonoscopy and inflammatory lab or stool markers.
“Symptoms alone are not always a great indicator of how our IBD is doing. It is important to monitor your IBD even if you are feeling better to make sure your disease is not progressing.”
Medication is not the “easy way out” and is not a sign of failure
Ashley and her team work with many IBD patients who are on biologics and utilize nutrition as a complementary approach to allow their medications to work better.
“Medications often lower certain nutrients, so one way you can support yourself long term is to check for deficiencies regularly. Some nutrients like zinc and vitamin D we need to regulate inflammation and help support our digestive tract lining. Ensuring they are at appropriate levels can help prevent flares. Vitamin D especially tends to get low with inflammation and is correlated with flare frequency and severity.”
Many patients avoid fiber because they fear it will trigger symptoms. Personally, I remember the first decade of living with Crohn’s, I was told I couldn’t have more than 5 mg of fiber per serving, which I now know is not the case.
“Understanding nutrition can help with expanding your diet. Research shows the importance of fiber for IBD for inflammation reduction, preventing flares and also complications. However, fiber is the most common thing IBD patients avoid. There are many ways you can approach expanding your diet without triggering symptoms and working with an IBD dietitian can help you navigate this better.”
The Roadmap of Nutrition
On average, Crohn’s and Colitis Dietitians helps clients reduce their IBD symptoms by 50-75%. Most report that their other big takeaways are improved energy and feeling more at peace with their food choices.
“We help you achieve this through working with people in a group setting and one-on-one. With one-on-one work we see people for a total of 6 months. It starts off with an intake session where we get to know your goals and your whole story with IBD and outside of IBD. After this session we put together a customized treatment plan that is your roadmap forward.”
The process includes dietary guidance (what to prioritize in the diet) and often targeted supplementation recommendations too. After this session, Ashley and her team see people each month in sessions to monitor progress and troubleshoot anything that comes up.
“We also offer access to us through chat throughout the whole 6 months for any questions that come up. We offer customized meal planning and video modules designed to help you.”
IBD is not your fault. It’s important to remember you didn’t sign up for this and you shouldn’t have to carry the weight of it alone.
“It can be incredibly helpful to have a team around you to support you through flares and the ups and downs of IBD. An IBD focused dietitian can help you navigate what to eat, treat nutrient deficiencies, sort through best options for targeted supplementation and help you reduce IBD symptoms.”
Outsource your stress. It’s overwhelming to juggle all the proverbial IBD balls in the air.
“Having a support team alleviates stress. It’s calming to know you don’t have to think through every decision and worry by yourself. It helps to have someone to lean on and takes the weight off your shoulders.
Don’t base your journey off what works for others. Just because you see someone proclaim their success by treating their IBD with food, doesn’t mean you’ll have the same experience. Before making any rash moves with your treatment plan, it’s imperative you communicate with your care team and get medically guided advice vs. following what you see someone post on Instagram. Same goes for medications—just because one person has had a great response on a biologic, does not mean you’ll have the same response.
Here are what some patients have to say about their experience:
“I’m so glad I started this program. I had to stop biologics due to developing antibodies and have been off biologics for over six months and since starting with the Crohn’s and Colitis Dietitians, I feel better than when I was on them. I only wish I found this program earlier.” -A.T.
“During the 6 months I was with Crohn’s and Colitis Dietitians- my symptoms of diarrhea and urgency reduced significantly, I have more energy and my inflammation decreased from over 100 to 38 (fecal calprotectin). Even my doctor was surprised and curious about what I had been doing with my nutrition!” -S