At 14, Crohn’s Made Her Question Motherhood. At 22, She’s Studying Why.

For women living with Crohn’s disease or ulcerative colitis, the question of whether to have children can carry a weight that goes far beyond the usual conversations about fertility and family planning.

Will my disease be controlled enough to have a healthy pregnancy? What happens if I flare while I’m pregnant? Will my medication affect my baby? What if I’m too sick to care for a child? What if breastfeeding means making another difficult medication decision? And the question that can be hardest to articulate: Will I be able to experience motherhood without IBD taking over the entire experience?

For Grace Hubbel, those questions aren’t simply academic. They are personal.

Diagnosed with Crohn’s disease at 14, Grace is now 22 and studying sociomedical sciences at the State University of New York at Geneseo. Her own experience with IBD and the stories she has heard from other women, led her to pursue an IRB-approved research study examining “The Impact of IBD on Decisions in Maternity and Emotional Wellbeing in Women.”

This week on Lights, Camera, Crohn’s a look at how her personal experience as a young woman with IBD inspired this incredible research and how you can get involved as a citizen scientist. Grace’s goal through her study, “The Impact of IBD on Decisions in Maternity and Emotional Wellbeing in Women” is to explore an area of IBD research that she believes has been overlooked: not simply what happens to a woman’s body during pregnancy, but what it feels like to make decisions about motherhood while living with an unpredictable chronic illness.

A Crohn’s diagnosis at 14

Grace grew up watching her older brother struggle with Crohn’s disease. He was diagnosed when he was starting college and nearly lost his life before his first surgery. When Grace began experiencing symptoms of her own at 14, she wasn’t completely surprised.

Her disease quickly became severe. She lost weight rapidly, her menstrual cycle stopped, and painful sores and ulcers made it difficult to swallow. She remembers feeling exhausted and unlike herself.

“I crawled into my mother’s bed once and told her it felt like I was disappearing with how I was losing pounds by the week,” Grace recalls.

At an age when many teenagers are focused on school, friends and figuring out who they are, Grace was learning a different vocabulary: tests, treatments, infusions, injections, and surgery.

“I was so young, I felt so different from my peers around me,” she says. “I spoke fluent in healthcare, in tests, I was forced to grow up so fast.”

Her Crohn’s journey has included steroids, infusions, injections, tests, a feeding tube, and surgery. At 22, Grace says she is still chasing total mucosal remission and continues to deal with hidden inflammation.

“Will I be able to become a mom someday?”

And almost immediately after her diagnosis, another question entered Grace’s mind.

Would she ever be able to become a mom?

Grace says motherhood was on her mind within months of being diagnosed.

Part of that fear came from watching someone she knew with Crohn’s experience a life-threatening postpartum flare and be unable to have more children. That story stayed with her and illustrates one of the most difficult aspects of IBD whether you’re a parent or not: uncertainty.
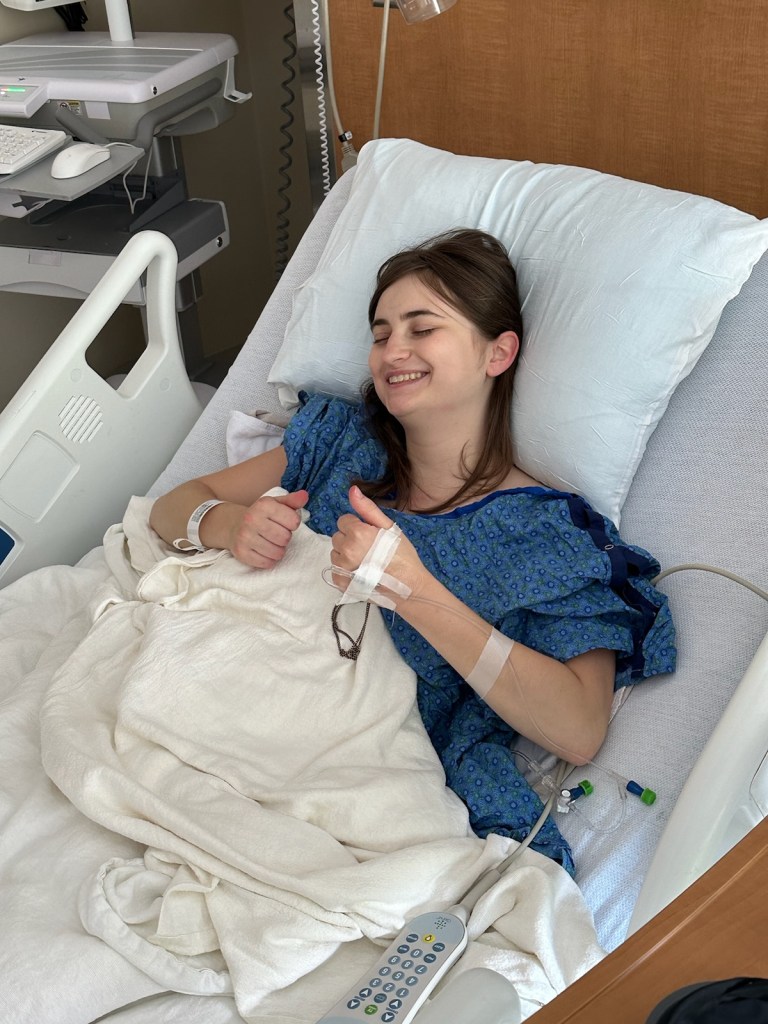
“The monstrous part about IBD is its uncertainty,” Grace says. “It never ceases to amaze me how for some individuals a round of medicine will get their body into remission, and another person will have unrelenting inflammation for years and years.”

For women with IBD, that uncertainty can intersect with some of life’s biggest decisions.

Grace knows this firsthand. Throughout various stages of her disease, she has wondered what a flare would look like during pregnancy or while caring for a young child.

What if severe diarrhea caused her to lose weight and made it difficult to get enough nutrients for a baby? What if medication affected her child’s immune system? What about breastfeeding and medication exposure?

Today, Grace takes Stelara, and she says she thinks about the fact that it can pass through breast milk. She has always dreamed of breastfeeding a baby but wonders how she would weigh that desire against the medical considerations.

And increasingly, another concern has emerged: the emotional experience of pregnancy itself.

“I worry most of all about having to work extra hard as a high-risk pregnancy and that I’d be obsessive about it all,” she says, “living outside of the special moments and experiences because of viewing it all through a clinical lens.”

That sentence captures something that statistics and clinical guidelines can’t always convey.

A pregnancy with IBD isn’t just a series of medical decisions. It can also be an emotional balancing act between wanting to enjoy a deeply meaningful life experience and being unable to completely turn off the part of your brain that is constantly monitoring your disease.

Seeing a gap in IBD research

As Grace learned more about IBD, she found comfort in understanding the disease from both scientific and sociological perspectives. She connected with other patients online and found women with IBD who had navigated motherhood and became role models for her.

That interest eventually led her to major in sociomedical sciences.

When it came time to develop an independent research project, she knew immediately that she wanted to study IBD and women’s health.

That project eventually grew into her current IRB-approved study. Grace noticed that while there is substantial scientific literature examining Crohn’s disease and ulcerative colitis during pregnancy and childbirth, there is far less research examining the qualitative experience of women living through motherhood with IBD.

In other words, researchers have studied many of the physical and medical questions. Grace wants to better understand the why behind women’s decisions, experiences, and emotions.

“This told me something was missing,” she says.

And the missing piece matters.

IBD is commonly diagnosed during reproductive years, meaning many women are forced to make decisions about fertility, pregnancy, breastfeeding, and family size while simultaneously navigating an unpredictable disease.

Could uncertainty itself be affecting women emotionally?

One of the findings that initially caught Grace’s attention was that women with IBD commonly report higher rates of psychological distress than men with IBD.

There are several explanations, but Grace wondered whether another factor deserved more attention.

Could the uncertainty surrounding fertility and motherhood contribute to that emotional burden?

“Could any of it have to do with how uncertain it can be for women to navigate a motherhood journey with an unpredictable illness such as IBD?” she asks.

That question became central to her research.

Rather than focusing solely on conception and pregnancy, Grace wants to understand the entire motherhood journey:

  • What does it mean to parent while living with IBD?
  • How do mothers explain their disease to their children?
  • Does becoming a parent change the way women cope with their illness?
  • How do women make decisions about breastfeeding or having additional children?
  • And perhaps most importantly, how do those decisions make women feel?

“These are the questions I want to explore,” Grace says.

Motherhood doesn’t end at delivery

One of the most compelling aspects of Grace’s research is her focus on what happens after pregnancy.

So much of the conversation around IBD and reproductive health centers on conception and pregnancy. But motherhood is a lifelong experience and IBD doesn’t disappear once a baby is born.

Grace says some of the women she has heard from have described waiting for their doctors to give them the “go-ahead” before trying to conceive.

Others have described delaying or avoiding medical care when they were very sick because they didn’t want to leave their children or frighten them.

But the stories aren’t exclusively difficult.

Grace says she has also heard about positive experiences, including mothers who have noticed their children developing deep empathy toward other people because they grew up with a mother living with IBD.

That is an important reminder: IBD can shape motherhood in challenging ways, but it can also shape families into beautiful ones. As an IBD mom of three kids (ages 9, 7, and 5) I can’t attest to this. Motherhood was the best decision I ever made and my kids are my constant motivation to push through, stay on top of managing my Crohn’s so I’m well for not only myself, but for them, and reminding me all my body is capable of despite my disease.

The decisions women make behind the scenes

One theme Grace has found particularly interesting is the way IBD can influence the timing of family planning. Some women wait for disease stability or medical approval before trying to conceive. Others make decisions about seeking medical care based on the needs of their children. These aren’t necessarily decisions that show up in a medical chart.

They’re the quiet calculations happening in the background of everyday life. And that’s exactly what Grace hopes her research will capture.

The study is designed to explore the experiences and emotional impacts behind these decisions, not simply whether a woman became pregnant or whether she experienced a flare. Because as we know, two women can have similar diagnoses and vastly different emotional experiences.

What Grace wants doctors to talk about earlier

Grace believes the conversation about fertility and family-building should begin much earlier in a woman’s IBD journey. She would like gastroenterologists to routinely ask young women at diagnosis whether they envision having children someday.

“I think it’s so important to get the conversation started and have it routine to discuss it,” she says.

Starting the conversation early can open the door to resources, questions, and appropriate reproductive counseling long before a woman is ready to have a baby. Grace also believes healthcare providers need to be honest about uncertainty.

“We need to be comfortable acknowledging what we don’t know,” she says, particularly when it comes to questions about the long-term effects of medications on children.

She also wants to see stronger communication between gastroenterologists and OB-GYNs.

She has heard women describe being confused about which physician to rely on during pregnancy and postpartum or receiving contradictory recommendations from their doctors.

“Greater communication between OB-GYN physicians, maternal fetal medicine doctors, and gastroenterologists on the topic of IBD and pregnancy is called for,” Grace says.

For patients, that kind of collaboration can mean the difference between feeling like they’re navigating pregnancy alone and feeling like they have a team.

Grace hopes her research changes the conversation

Grace hopes her research will expand how the IBD community thinks about women’s health. The physical side of IBD is important. But emotional wellbeing matters, too.

She points to the connection between psychological health and IBD outcomes, noting that emotional distress can influence disease activity. Her research suggests that the emotional stress of navigating motherhood alongside IBD may be one contributor to the psychological burden reported by women with the disease.

Her long-term goal is to highlight the need for more reproductive counseling and pregnancy programs specifically designed for women with IBD. Because women shouldn’t have to piece together this information on their own. And they shouldn’t have to wait until they’re ready to conceive to start asking questions.

“You will survive some of your biggest fears”

The most powerful part of Grace’s story isn’t the researcher speaking about the gaps in the literature. It’s the 14-year-old girl underneath it all.

If Grace could sit down with herself on the day she was diagnosed, she wouldn’t promise that IBD would become easy. Instead, she would tell her younger self that the disease would shape who she became and that some of that impact would become a source of purpose.

Her experiences would fuel her interest in healthcare and disability advocacy. She would meet healthcare workers who saw through her knowledgeable exterior and recognized the anxiety underneath. She would survive some of the things she feared most. And she would eventually find a partner who would make motherhood feel possible. But she’d also tell herself something many young people with chronic illness need to hear:

You don’t have to control everything.

“I’d tell her to enjoy being a young woman and let go of trying to control so much,” Grace says.

That’s easier said than done when your body has taught you from an early age that anything can change without warning. But that’s also why her message to other young women with IBD is so meaningful.

To the young woman with IBD dreaming about motherhood

Grace doesn’t know exactly what the future holds for her. She still has questions. She still has fears. She still lives with an unpredictable disease. But she isn’t letting uncertainty erase the possibility of motherhood. Her message to other young women with IBD is simple:

“Advocate for yourself and ask questions.”

She encourages women to establish an OB-GYN early and start talking about what pregnancy could look like in the future, even if motherhood is years away. And she wants women to know that they don’t have to abandon the dream simply because IBD may make the path more complicated.

“The reality is, it might be a little more sad and scary to manage,” Grace says. “But from what I’ve learned so far: no women have regretted the choice to pursue their dream, even if it looks different from what they expected.”

For a 22-year-old researcher who has spent much of her life learning to live with Crohn’s disease, Grace is asking a question that deserves far more attention:

What happens when we stop looking at motherhood with IBD solely through a medical lens and start listening to the women living it?

Her research is an important step toward answering it.

Interested in participating in Grace’s research?

Grace is currently seeking women with IBD who are at least 18 years old, English-speaking, and currently mothers living with Crohn’s disease or ulcerative colitis, either biologically or through adoption. A diagnosis before having a child is preferred.

Participants can complete an anonymous survey or contact Grace for a virtual interview. Participation is voluntary, and information provided will be kept confidential.

Join the study here!

Inside IBD Pregnancy with a GI Psychologist: What Patients Need to Know

Finding out you’re pregnant can be one of the most profound moments of one’s life; and, if you’re living with Crohn’s disease or ulcerative colitis, that moment is almost immediately followed by a flood of questions that others don’t have to think about. Will my IBD flare? Is my medication safe? What does this mean for my pregnancy? Can I even do this?

The answer to that last question is yes, absolutely, yes. But it takes a team, a plan, and attention to more than just your GI symptoms. As an IBD mom of three, I’ve been in your shoes and know how it feels to bring a life into this world with so many unknowns.

This week on Lights, Camera, Crohn’s we hear from Licensed Clinical Psychologist, Dr. Antonia Repollet, who specializes in gut-brain health at GI Psychology. Dr. Repollet is a fellow Crohnie and a mother. She works with people navigating exactly this intersection every day. She shares what she wants every person with Inflammatory Bowel Disease (IBD) to know about pregnancy: the medical side, the emotional side, and the parts that often get left out of the conversation entirely.

Your Gut Is Already Under Pressure

Pregnancy is a full-body experience. Hormonal shifts in progesterone, estrogen, and cortisol affect mood and energy, and they directly shape how the gut functions. Progesterone relaxes smooth muscle, slowing the movement of food through the digestive tract (Alqudah et al., 2022). Estrogen influences gut permeability and the composition of the gut microbiome (Chen et al., 2025). Cortisol, the body’s primary stress hormone, can heighten GI sensitivity and drive inflammation (Cherpak, 2019). Together, these hormonal changes can increase bloating, reflux, and constipation even in people without IBD. Add a growing uterus physically displacing digestive organs, and it’s no wonder the gut feels unsettled!

Whether you’re a first-time mom-to-be or someone who has had several children, we know how complicated it can feel to navigate these changes in your body on top of IBD. It’s not unusual to feel a bit overwhelmed.

“For someone with Crohn’s or ulcerative colitis, these changes land on an already-sensitive system, and the hormonal picture matters more than people often realize. Hormones are among the key messengers of the gut-brain axis, the two-way communication highway between the digestive tract and the nervous system,” explain Dr. Repollet. “During pregnancy, when hormone levels are shifting, this axis is working overtime, and stress often amplifies this further. For example, anxiety about your health, your pregnancy, your body, your medications: all of it feeds back into the gut through hormonal and neurological pathways, and the gut sends it right back to the brain. Thus, pregnancy can disrupt this loop.”

Why Remission Before Conception Matters

Here’s something important: research consistently shows that the best predictor of IBD staying stable during pregnancy is whether disease was well-controlled at the time of conception (Abhyankar, 2013). Studies have found that approximately 66% of IBD patients who conceive during active disease experience continuing or worsening symptoms throughout pregnancy (Hashash & Kane, 2015).

Dr. Repollet says, “Remission going in doesn’t guarantee smooth sailing, but it does dramatically improve the odds for both the pregnant person and the developing fetus.”

Looking back, I’m grateful for the timing of my bowel resection surgery when I was engaged, because it put me into surgical remission, and helped prep my body for pregnancy after I got married. Prior to surgery, I had never heard the word “remission” from my gastroenterologist. With IBD pregnancies, this is where the “rule of thirds” comes in. One third of women experience an improvement of IBD symptoms, one third stay the same, and one third see an uptick.

Active disease during pregnancy is associated with increased risks of miscarriage, preterm birth, low birth weight, and other complications (Boyd et al., 2015). This is why the conversation with your gastroenterologist needs to happen before you start trying to conceive, not after a positive pregnancy test.

The Medication Questions

Please don’t stop without talking to your doctors!

“One of the most common things I hear from IBD patients considering pregnancy is some version of: “I thought I should stop my medication just to be safe.” The instinct makes complete sense, because you want to protect your pregnancy. But stopping IBD medication without medical guidance can put you and your fetus at greater risk by triggering a flare,” Dr. Repollet advises.

Many IBD medications, including biologics like infliximab, adalimumab, and certolizumab, are considered safe during pregnancy and are recommended to maintain remission (Mahadevan et al., 2019; Peifer, 2024). Some, like methotrexate, do need to be stopped well before conception, and this applies regardless of which reproductive organs you have (Peifer, 2024). This is important for both partners, as medication safety around conception is a conversation for anyone planning to conceive, regardless of gender. Your GI and obstetrician (OB) should be making these decisions together, with your input.

Build Your Team Before You Need Them

A whole-person approach to pregnancy with IBD means your care team should include more than just your GI and OB. Depending on your history, you may also benefit from a maternal-fetal medicine specialist (an OB with advanced training in high-risk pregnancies), a dietitian who understands IBD and prenatal nutrition, a lactation consultant familiar with chronic illness, and a mental health provider who specializes in the gut-brain connection. According to findings from the Global Consensus on IBD and Pregnancy, all IBD pregnancies are deemed “high risk.”

Dr. Repollet tells me the last one matters more than people realize.

The Part That Doesn’t Get Talked About Enough: Your Mental Health

People with IBD are two to three times more likely to experience anxiety and depression than people without (Neuendorf et al., 2016). Rates of anxiety in IBD hover around 32%, and depression around 25% (Barberio et al., 2021). These numbers don’t go down during pregnancy. If anything, the uncertainty, the body changes, the fear of flares, and the weight of managing a chronic illness while growing a new life can make them go up.

“And here’s what’s easy to overlook: your emotional state is not separate from your physical symptoms. Stress releases hormones that increase inflammation. Anxiety heightens gut sensitivity. When you’re scared that every cramp might be a flare, that fear itself can worsen symptoms. The mind and the gut are in constant conversation,” says Dr. Repollet.

This is why mental health support isn’t a “nice to have” treatment during pregnancy with IBD and should be part of the medical plan.

Evidence-based approaches like Cognitive Behavioral Therapy (CBT) for GI conditions (CBT for GI) (Gracie et al., 2017) and gut-directed hypnotherapy (Keefer et al., 2013) have been shown to reduce GI symptoms, lower flare frequency, and improve quality of life in IBD patients. These approaches are safe during pregnancy, non-pharmacological, and can be genuinely life-changing for anyone who feels like they’re white-knuckling through their pregnancy.

A Story That Might Sound Familiar

“One of my patients (I’ll call her “Alex”) was 12 weeks pregnant and living with Crohn’s. Inflammation was well-controlled, but daily abdominal cramping and pain, diarrhea, and racing thoughts about whether symptoms were affecting the pregnancy had taken over. The response from providers (e.g., “It’s just pregnancy hormones.”) left Alex feeling dismissed and alone.”

With gut-brain therapy, Alex learned to track symptom patterns, practice diaphragmatic breathing, and use clinical hypnosis to interrupt the anticipatory anxiety that was amplifying physical symptoms.

Dr. Repollet says, “Over eight weeks, symptoms decreased, sleep improved, and (maybe most importantly) there was a renewed trust in the body’s signals. Feeling prepared going into delivery and postpartum was something Alex hadn’t expected to feel, but did. This is a reminder that emotional care is physical care. They are not separate things.”

What to Watch For and When to Reach Out

Consider seeking mental health support if you are:

  • Struggling to eat or sleep due to GI symptoms or anxiety
  • Experiencing GI symptoms that feel emotionally overwhelming, are hard to separate from anxiety, or seem to worsen with stress
  • Experiencing distress (whether related to your IBD, your pregnancy, or both) that is interfering with daily life
  • Having fears about flares, delivery, or being a high-risk patient that feel consuming
  • Dealing with resurfacing trauma from prior pregnancy loss, difficult medical experiences, or a complicated diagnosis journey
  • Simply wanting a space to process this enormous thing you are navigating

Please know that you don’t have to be in crisis to deserve support.

The Postpartum Chapter

Pregnancy often gets most of the attention, but postpartum is its own significant transition for people with IBD.

“Hormonal shifts after delivery, sleep disruption, feeding decisions in the context of your medication regimen, and the emotional adjustment to new parenthood can all influence disease activity. Having a plan for the postpartum period, including who on your care team you’ll check in with and how, should be part of a complete prenatal plan,” explains Dr. Repollet.

I remember during all my pregnancies how fearful I was about how I would feel after delivery. By staying on my medication (Humira), it helped keep symptoms at bay not only during my pregnancies, but also after my scheduled c-sections. I required a short burst of steroids after my second child was born, but luckily never experienced a full-blown flare.

It can be easy to place all your focus on your baby but be mindful of how your body is speaking to you through symptoms so you can communicate this directly to your care team, before you’re dealing with an acute flare. Trust that by sharing what you’re going through you’re doing what is not only best for yourself, but what’s best for your family.

You Deserve Coordinated, Whole-Person Care

Pregnancy with Crohn’s or ulcerative colitis is possible. Many people do it every year with the right support, effective communication between providers, and attention to both the physical and emotional layers of what they are carrying.

“At GI Psychology, we specialize in helping people with IBD and other GI conditions navigate exactly these kinds of life transitions. Our clinicians are trained in gut-brain therapies including CBT-GI and gut-directed hypnotherapy, and we work via telehealth across all 50 states + Washington D.C., so support is accessible wherever you are. We also offer an 8-week virtual IBD Psychotherapy Group for adults living with Crohn’s and ulcerative colitis, designed to provide evidence-based tools alongside community with people who truly get it,” says Dr. Repollet.

If you’re planning for pregnancy, currently pregnant, or navigating the postpartum period with IBD, you don’t have to figure it out alone.

Learn More About GI Psychology:

Participate in IBD Pregnancy Research

References

Abhyankar, A., Ham, M., & Moss, A. C. (2013). Meta-analysis: the impact of disease activity at conception on disease activity during pregnancy in patients with inflammatory bowel disease. Alimentary pharmacology & therapeutics, 38(5), 460–466.

Alqudah, M., Al-Shboul, O., Al Dwairi, A., Al-U´Datt, D. G., & Alqudah, A. (2022). Progesterone inhibitory role on gastrointestinal motility. Physiological research, 71(2), 193–198.

Barberio, B., Zamani, M., Black, C. J., Savarino, E. V., & Ford, A. C. (2021). Prevalence of symptoms of anxiety and depression in patients with inflammatory bowel disease: a systematic review and meta-analysis. The lancet. Gastroenterology & hepatology, 6(5), 359–370.

Boyd, H. A., Basit, S., Harpsøe, M. C., Wohlfahrt, J., & Jess, T. (2015). Inflammatory bowel disease and risk of adverse pregnancy outcomes. PloS One, 10(6), e0129567.

Chen, M., Wang, J., Yang, Y., He, Y., & Li, L. (2025). The interplay of estrogen, gut microbiome, and bone immunity in osteoporosis. Cell communication and signaling : CCS, 23(1), 516.

Cherpak C. E. (2019). Mindful Eating: A Review Of How The Stress-Digestion-Mindfulness Triad May Modulate And Improve Gastrointestinal And Digestive Function. Integrative medicine (Encinitas, Calif.), 18(4), 48–53.

Gracie, D. J., Irvine, A. J., Sood, R., Mikocka-Walus, A., Hamlin, P. J., & Ford, A. C. (2017). Effect of psychological therapy on disease activity, psychological comorbidity, and quality of life in inflammatory bowel disease: a systematic review and meta-analysis. The Lancet Gastroenterology & Hepatology, 2(3), 189–199.

Hashash, J. G., & Kane, S. (2015). Pregnancy and inflammatory bowel disease. Gastroenterology & Hepatology, 11(2), 96–102.

Keefer, L., Taft, T. H., Kiebles, J. L., Martinovich, Z., Barrett, T. A., & Palsson, O. S. (2013). Gut-directed hypnotherapy significantly augments clinical remission in quiescent ulcerative colitis. Alimentary Pharmacology & Therapeutics, 38(7), 761–771.

Mahadevan, U., Robinson, C., Bernasko, N., Boland, B., Chambers, C., Dubinsky, M., … & Kane, S. (2019). Inflammatory bowel disease in pregnancy clinical care pathway: A report from the American Gastroenterological Association IBD Parenthood Project Working Group. Gastroenterology, 156(5), 1508–1524.

Neuendorf, R., Harding, A., Stello, N., Hanes, D., & Wahbeh, H. (2016). Depression and anxiety in patients with Inflammatory Bowel Disease: A systematic review. Journal of Psychosomatic Research, 87, 70–80.

Peifer, R. (2024, January 26). IBD and pregnancy: What you need to know. Crohn’s & Colitis Foundation. https://www.crohnscolitisfoundation.org/blog/ibd-and-pregnancy-what-you-need-to-know

When Your Body Doesn’t Follow the Rules: The Overlap Between Endometriosis and IBD No One Talks About

For many women, living with chronic illness means constantly decoding what our bodies are trying to say. When you have inflammatory bowel disease (IBD), whether Crohn’s disease or ulcerative colitis, you get used to tracking symptoms, identifying triggers, and advocating for yourself.

But what happens when something doesn’t quite fit the IBD pattern and the usual narrative?

For a significant number of women, the answer may be endometriosis, a condition that often overlaps with IBD in ways that can delay diagnosis, complicate treatment, and intensify daily life. This week on Lights, Camera, Crohn’s we break down the possible connection, what to watch for, and how to advocate for the care you deserve. I don’t personally have endometriosis with my Crohn’s, so you’ll hear from 10 women who live this reality as they transparently share what it’s like for them and what they’ve learned along the way.

What Is Endometriosis?

Endometriosis occurs when tissue similar to the lining of the uterus grows outside the uterus. This can happen on the ovaries, fallopian tubes, bowel, bladder, and other pelvic structures. This tissue still responds to hormonal cycles, which can lead to:

  • Inflammation
  • Pain
  • Scar tissue (adhesions)
  • Organ involvement (including the intestines)

I ran a poll in my Instagram Stories asking about IBD and endometriosis. Of the 85 votes, 27% of women said they have both, 31% said they think they may have both, and 42% said they don’t have both. Those numbers speak volumes.

What the Stages of Endometriosis mean

Endometriosis isn’t staged the same way cancers are, it’s not about how dangerous it is, but about how much disease is seen during surgery. The most used system is from the American Society for Reproductive Medicine, which divides endo into four stages based on location, depth, size of implants, and scar tissue (adhesions).

Here’s what each stage means:

Stage I — Minimal

  • Small, superficial patches of endometrial-like tissue
  • Little to no scar tissue
  • Often found on the ovaries or pelvic lining

What it feels like:
Symptoms can be mild… or surprisingly intense. Some people with Stage I still have significant pain.

Stage II — Mild

  • More lesions than Stage I
  • Some may be deeper (not just surface-level)
  • Minimal adhesions may start forming

What it feels like:
Pelvic pain, painful periods, sometimes pain with ovulation. Still very variable.

Stage III — Moderate

  • Many lesions, including deep implants
  • Presence of adhesions (organs may start sticking together)
  • Small cysts on ovaries called endometriomas may appear

What it feels like:
More consistent pelvic pain, possible pain with sex, bowel symptoms depending on location.

Stage IV — Severe

  • Extensive deep lesions
  • Thick adhesions (organs can be significantly stuck together)
  • Larger ovarian endometriomas (“chocolate cysts”)
  • May involve bowel, bladder, or other organs

What it feels like:
Chronic, often severe pain; higher likelihood of fertility challenges; symptoms tied to whichever organs are affected.

The most important thing to understand

Stage does NOT equal pain level. Someone with Stage I can be debilitated, while someone with Stage IV might have fewer symptoms. That’s one of the most frustrating parts of endo, it doesn’t behave predictably. That being said, just because you may have Stage 1 should not diminish your experience as a patient or the suffering you are coping with.

Why Endometriosis and IBD Get Confused

The overlap between endometriosis and IBD is more than coincidental, it’s believed to be symptomatically and biologically intertwined.

Both conditions can cause:

  • Abdominal pain and cramping
  • Diarrhea or constipation
  • Bloating
  • Fatigue
  • Nausea
  • Pain with bowel movements

If you already have IBD, it’s easy to assume these symptoms are just part of a flare.

Hormonal Influence

Endometriosis is hormone-driven, meaning symptoms often worsen:

  • Before or during your period
  • Around ovulation

Some women with IBD also report symptom fluctuations tied to their menstrual cycle, which can blur the lines even further.

Inflammation Connection

Both conditions involve chronic inflammation, and emerging research suggests there may be shared immune pathways. Women with IBD may have a higher likelihood of developing endometriosis—and vice versa.

Red Flags That It Might Be More Than IBD

If you’re living with IBD, here are signs that something else, like endometriosis, could be at play:

  • Pain that follows your cycle (gets worse before/during your period)
  • Severe pelvic pain that feels different from your typical IBD pain
  • Pain during or after sex
  • Pain with bowel movements specifically during your period
  • Infertility or difficulty conceiving
  • IBD treatments aren’t improving certain symptoms

One of the biggest clues? When your gut symptoms don’t fully respond to your usual IBD medications.

The Diagnostic Challenge

Diagnosing endometriosis isn’t straightforward.

  • Imaging (like ultrasound or MRI) can help, but may miss smaller lesions
  • The gold standard is laparoscopic surgery, where a specialist can see and biopsy the tissue

For women with IBD, this can feel overwhelming, especially if you’ve already been through scopes, scans, surgeries, and procedures. But getting clarity matters.

How It’s Treated

Treatment depends on severity, symptoms, and your goals (like pain relief vs. fertility).

Hormonal Therapy

  • Birth control pills, patches, or IUDs
  • Medications that suppress estrogen

These aim to reduce or stop the growth of endometrial tissue.

Pain Management

  • NSAIDs (with caution in IBD, especially Crohn’s)
  • Other pain-modulating medications

Surgical Treatment

  • Laparoscopic excision of endometriosis lesions
  • Particularly helpful for more advanced disease

Coordinated Care

If you have both IBD and endometriosis, your care team may include:

  • A gastroenterologist
  • A gynecologist (ideally one who specializes in endometriosis)
  • A colorectal surgeon if bowel involvement exists

This team-based approach can make a huge difference.

Living With Both: Practical Advice

Track Your Symptoms Differently

Don’t just track food and bowel habits. Be mindful of:

  • Your menstrual cycle
  • Pain timing and location
  • Symptom patterns across the month

 Patterns can reveal what labs and scans can’t.

Don’t Dismiss “New” Pain

You know your IBD. If something feels different, it probably is. Trust that instinct.

Be Specific With Your Doctors

Instead of saying “I have more pain,” try:

  • “This pain is worse during my period.”
  • “It feels lower in my pelvis than my usual Crohn’s pain.”
  • “My GI symptoms spike even when my inflammation markers are normal.”

Details help providers connect the dots faster.

Be Careful With Medications

Some common treatments for one condition may complicate the other:

  • NSAIDs can aggravate IBD
  • Hormonal treatments may affect GI symptoms differently for each person

Always loop in both your GI and GYN teams.

Advocate for a Second Opinion

Endometriosis is often underdiagnosed and misunderstood. If you feel dismissed, it’s reasonable to seek a specialist, especially one experienced in excision surgery, not just symptom management.

The Emotional Side No One Talks About

Living with one chronic illness is hard enough. Adding another, especially one that affects fertility, hormones, and daily pain, can feel overwhelming.

There’s often:

  • Frustration from delayed diagnosis
  • Anxiety about symptoms overlapping
  • Exhaustion from managing multiple specialists

If this is your reality, you’re not alone and you’re not imagining it.

The Patient Experience: What women with IBD and endometriosis want you to know

Madison: “I could write a novel about endometriosis and IBD! I’ve had three surgeries for endometriosis, and it’s been found on my bowel in two of the surgeries. I eventually asked my GI if it could have been endo all along (it’s not), but it’s interconnected.

She was diagnosed with ulcerative colitis in 2016 but had symptoms for a few years prior. Madison was diagnosed with endometriosis in August 2020 after unexplained infertility but more importantly, debilitating pain once she stopped birth control in early 2019. Looking back, she says her symptoms probably started at puberty (12 years old) but she didn’t know what was normal. 

“I had surgery in August 2020 to confirm the endometriosis diagnosis and have had 2 additional surgeries since then. I wish I would have known during my first surgery that there’s a difference between an ablation of the endometriosis and an excision of the endometriosis,” she explains. “The best way I’ve had it explained to me is imagine burning weeds in your yard vs pulling them out by the root — if you burn the weeds, they will come back. You need to pull them out by the root. However, not every surgeon is trained in excision and the recovery is definitely longer! I looked into endometriosis advocacy groups like Nancy’s Nook (Facebook) to help learn more about the differences and find excellent surgeons.”

Madison ended up having a hysterectomy in 2023 after they suspected adenomyosis (where endometrial tissue grows within the muscle of the uterus) and the quality of life she has now is significantly improved! She still has endometriosis (there’s no cure and it often regrows) but it’s managed much better now.

“I will probably have a fourth surgery in the next couple years, but I’m hopeful that the medicine and science improves to possibly delay an additional surgery. My endometriosis and my ulcerative colitis symptoms are definitely linked. If I’m in a flare for one, I tend to have symptoms increase for the other. For example, my endometriosis causes really painful bloating and I often look distended. If the distension lasts for a few days, my gut tends to revolt and I start to see an increase in GI symptoms. The last 2 surgeries showed I had endometriosis growing on the bowels (both times it was removed) so my cycles would cause really painful GI symptoms that improved after the surgeries.”

She is more convinced now that the gut/brain/pain feedback loop is real. When Madison’s endo is calm, her ulcerative colitis tends to follow suit. She’s so grateful for Instagram which has connected her to other endometriosis patients that have been willing to share their experiences.

Katherine: “Just saw an endo excision specialist 2 months ago. She wants me to do the surgery, but I’m in my second flare right now in the last year and my IBD specialist won’t sign off on it until I’m in endoscopic remission. Now dealing with fighting CVS in an appeal to increase my Rinvoq back to 45 mg.”

Katherine went on to say that one of the most vital steps in her journey was realizing that her body doesn’t operate in silos, so her doctors shouldn’t either.

“Navigating the overlapping pain of ulcerative colitis and endometriosis requires more than just two separate plans; it requires a unified front. I found that getting my IBD specialist deeply involved in my pelvic health was the catalyst for better care, especially since I noticed my symptoms would constantly peak during my cycle, creating a ‘perfect storm’ for inflammation.”

She says her GI understands the specific complexities of her UC and was able to refer her to an endometriosis specialist who wasn’t just an expert in surgery, but someone who respected the delicacy of the bowel.

“When your GI and endo specialist collaborate, you move away from ‘band-aid solutions’ and toward a strategy that addresses how these conditions trigger one another. Don’t be afraid to ask your gastroenterologist for a referral; a specialist who is already vetted by your IBD team ensures that your care plan is safe, cohesive, and designed for your specific anatomy.”

Katherine is currently in her second UC flare in six months after being in remission for five years. The plan is to start progesterone only birth control once she’s back in remission. Then she plans to get endometriosis excision surgery, and an IUD, which will help with her iron deficiency anemia.

Sabrina: “My doctors have suspected I have endometriosis, but I haven’t done the diagnostic surgery yet because I need to wait until I have my surgery to reconnect my J Pouch.”

Kelly wasdiagnosed with endometriosis stage 4 but most likely had it for years. Then, she received her Crohn’s disease diagnosis in 2005.

“We did several rounds of IVF mainly because back then it wasn’t talked about or taken seriously. I never would have done IVF because my Crohn’s got so bad. We adopted in 2009. I had my colon out in 2010. Then in 2016, I was thinking of a hysterectomy because I was so done with the anemia and pain. I ended up with a small bowel blockage due to my endometriosis and end up (I had a J Pouch—I now have an ileostomy) having an emergency hysterectomy and a 10-hour surgery to unglue all my organs and get rid of the scar tissue on my bowels and the damage from the endo.”  

Kim: “I was diagnosed with Endometriosis first, then Crohn’s, then repeat scopes showed endometriosis on my colon as well. I’ve never been told there is a correlation, but it makes total sense (how women’s bodies store trauma and have far more autoimmune conditions as a result). I wish I would’ve known to advocate for myself and my symptoms as a teenager and young adult.”

Kim says too many times (especially for women) we are told it’s “normal” to have symptoms (cramps, excessive bleeding, fatigue, anemia, etc.) and as a young adult, you don’t know to challenge it.

“Even at 30 years old, my PCP was convinced my rectal bleeding was simply from hemorrhoids and only referred me to GI when I insisted. Then, that GI only performed a colonoscopy because of the referral from PCP as “IBD patients typically present much more ill” than me. We then discovered severe, chronic ulceration and full-blown Crohn’s.”

Kristin: “I was diagnosed with stage 4 endo during a hysterectomy in 2024 after years of terrible symptoms that kept me bedridden during my cycle. However, not all my symptoms were relieved from the surgery. About 15 months later (just last month), I was diagnosed with Crohn’s disease and started on biologics. For years, I was told I had a sensitive stomach, or I should take birth control. I wish I knew what endo was years ago. I also wish I knew how much more likely women with endo are for having an autoimmune disease.

Kristen wants women to know that how you describe your symptoms to doctors is just as important as what you tell them. This will directly impact testing and help in finding a diagnosis. It wasn’t until she told her GI that her symptoms were cyclical but seemed to have no rhythm or reason that the testing approach shifted. Kristen wants women to have the courage to speak up about all your symptoms, even if they seem gross or uncomfortable to talk about.

Allie: “I just wish when I was diagnosed with UC that someone would have told me the likelihood of potentially having endo and then the impact it could have on fertility. I would have gone to a fertility specialist early on and potentially frozen my eggs in early adulthood.

Kate: “I was diagnosed with Crohn’s first 25+ years ago. Then endometriosis 23+ years ago. I have stage 4 endo, meaning it was most recently found fusing my vagina and rectum together. I have had a total hysterectomy, multiple surgeries to remove endometrial tissue throughout my pelvis, and both of my ovaries are now gone. This was discovered after YEARS of constipation (weird for me) and NOTHING worked to resolve it.

Kate is on opioids for chronic pain and her doctors kept telling her the pain medication was the culprit for the constipation, but the reversal medications did nothing. She was hospitalized for nine days for pain and constipation, during which they tried everything. The only fix was to slowly drink colonoscopy prep while getting IV pain meds for the pain it caused.

“I kept asking if it could be a structural or a motility problem, and they kept saying it was the opioids. Colonoscopies have shown my Crohn’s is and has been in remission for years (thanks to Azathioprine!)  After the surgery, where they discovered the actual issue (that it was structural), I’ve had zero constipation issues and have been able to finally start coming out of the depression. We are now looking to find a GI doctor who has a better understanding of endometriosis and Crohn’s.”

Kate says the inflammatory process of both diseases mimic each other, and there is no reason to suffer in pain, nor should patients be told they cannot address their pain using the entire toolkit, including opioids, if they allow the patient to become more functional and lead a more fulfilling life.

“Doctors need better education on how systemic both diseases are, and that if Crohn’s symptoms aren’t responding to treatment, they should be worked up for endo. There also needs to be a better understanding that both diseases can be worse than having cancer, as there are no clear protocols, there is little understanding or support, there is little research, and the idea there could be something worse than cancer doesn’t register with most of the general public.”

Lenette: “I found out I had endometriosis when I had a partial hysterectomy to correct iron deficiency anemia. At first, the pain and symptoms all blurred together. It’s taken time for me to be able to distinguish between the two, but sometimes, I’m still unsure what is what. Tracking symptoms helped me distinguish better because I found some symptoms to be cyclical. However, IBD can worsen around your cycle as well and hormones can affect both conditions.”

Lynette recommends women be extremely specific with doctors about their pain. So many symptoms overlap, and she says it can feel two times as bad: bloating, fatigue, mood, etc. All of this can cause pelvic floor tension, and pelvic floor therapy can be life changing.

“It’s also helpful to find community that have both conditions where you can find someone to talk to or learn more about having both. I have found it to be so frustrating to have both because I seem to experience symptoms so much more dramatically than others do at times. Having two conditions that affect the same area and both cause pain and bloating has been so challenging. What helps one condition might not help the other so it can be very trial and error. It has given me a new sense of awareness of my pain and fatigue since I am constantly monitoring to understand which is occurring or if both are the culprit at that time. It’s so frustrating that my IBD is in remission, yet I still experience a lot of symptoms due to my endometriosis.”

She says it can feel like you rarely get a break from pain.

“I try to listen to my body when I’m experiencing a lot of symptoms. I do a lot of deep breathing, stretching, and walking. I also try to listen to my body regarding food. I try to eat nourishing things but also if I’m craving something, I usually eat what I’m craving. If it increases symptoms, I make a note of that. Sometimes my body is OK with certain foods and sometimes it isn’t. I also try to manage stress levels a lot when I’m experiencing symptoms.”

Jessie: “I was diagnosed with Endo and Crohn’s right around the same time at the age of 15. I think my Endo symptoms showed up at first, but they were all diagnosed at once. At the time, the doctors shared no information on any correlation and treated it like two separate issues. As I aged and both progressed, I still struggled to get any acknowledgement from doctors on the two being related; however, once I was diagnosed stage IV Endo and had my last excision + partial hysterectomy, that surgeon said he could see how my condition could be affecting my Crohn’s in the lower colon and perianal area. I had some endo down by the rectum that they removed and there was just a lot of inflammation.”

Jessie says her inflamed uterus (which was adenomyosis) also may have been contributing to overall inflammation in that area as well. She chose to have an excision and partial hysterectomy before her ostomy was reversed, and her perianal symptoms improved so much by not having a period anymore.

“Every time I would get a period, I would experience pain, inflammation, diarrhea, increased urgency, and pressure around that rectal area and my lower abdomen. While I still have my ovaries, not having a period itself every month almost eliminated all those Crohn’s symptoms that would rage around my cycle.”

The Bottom Line

The truth is, not all pain in women with IBD is “just IBD” and continuing to accept that narrative is where too many stories get stuck. Endometriosis is often hiding in plain sight, especially in bodies already labeled as “complicated.” But your body is not confusing, you’re just being asked to connect dots that the healthcare system doesn’t always put together for you.

So, if something feels off, if your symptoms don’t follow the rules, if your pain keeps showing up despite doing “everything right,” do not ignore it. Track it. Name it. Bring it to your care team repeatedly until someone listens.

Because you deserve care that looks at the whole picture. You deserve doctors who are curious, not dismissive. And most of all, you deserve answers, not assumptions. This isn’t about choosing between diagnoses. It’s about recognizing that sometimes, it’s both, and finally getting the care that reflects that reality.

Learn more here

Life With Crohn’s And Endometriosis: An Overlap Of Painful Symptom | EndoFound

Inflammatory Bowel Disease and Endometriosis: Diagnosis and Clinical Characteristics – PMC

Endometriosis Does Not Worsen IBD and May Be Linked to Milder CD Progression – Gastroenterology Advisor

Inflammatory Bowel Disease and Endometriosis: Diagnosis and Clinical Characteristics – PubMed\

Frontiers | Potential shared pathogenic mechanisms between endometriosis and inflammatory bowel disease indicate a strong initial effect of immune factors

ASSOCIATION OF ENDOMETRIOSIS AND INFLAMMATORY BOWEL DISEASE (IBD), FINDINGS FROM EPIDEMIOLOGICAL EVIDENCE TO GENETIC LINKS – Fertility and Sterility

Endometriosis vs IBD: Symptoms, Overlap, and Evidence