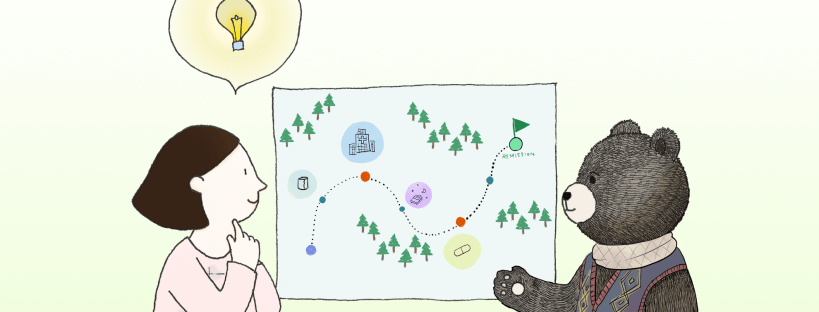
From Memory to Meaning: How Mirae Is Changing the Way We Manage IBD

This is a sponsored blog post; all thoughts and opinions are my own.

Living with Inflammatory Bowel Disease (IBD) means constantly reading the signals your body is sending you. What you eat, how you sleep, your stress level, your energy, and even the seemingly small changes in your routine can influence how you feel. After more than 21 years with Crohn’s disease, I’ve learned that this internal conversation never completely goes away, even during remission.

The challenge is that when symptoms become part of everyday life, gradual changes can be surprisingly difficult to recognize. Whether you’re newly diagnosed or have been living with IBD for decades, knowing your personal baseline can be one of the most valuable tools in managing your disease.

That’s where the Mirae Health app comes in. Rather than relying on memory or trying to piece together months of symptoms and lifestyle patterns before an appointment, Mirae helps patients see their own patterns and recognize when something starts to shift. This week on Lights, Camera, Crohn’s, we hear from Mirae’s founders about the inspiration behind the app and why understanding the connection between our daily lives and how we feel could change the way we approach IBD care.
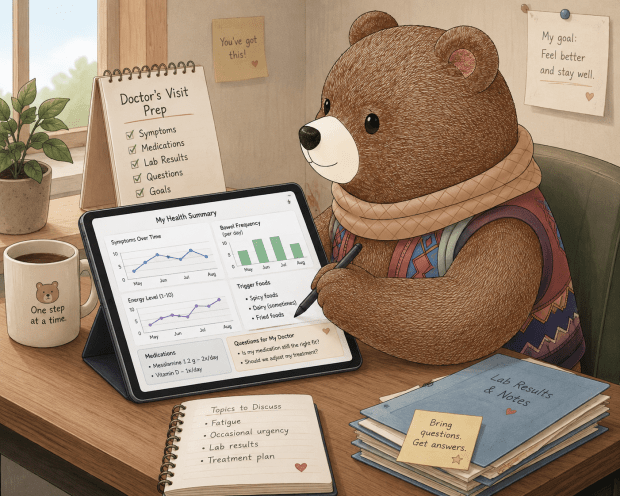
Mirae’s founding designer, Sayoko Yoshida, chose to use a bear because they wanted something that felt:

  • Warm and inviting
  • Steady and dependable
  • Protective
  • Human and personal

The Mirae team specifically didn’t want the app to feel like a cold clinical dashboard or an overly cheerful “health app” mascot. They wanted the bear to represent a reassuring guide, something that helps people living with IBD understand what’s happening and feel supported as they navigate their care.

The inspiration behind Mirae

Mirae’s three founders, James Finucane, David Clifton, and Anuj Patel, have spent their careers using technology to improve access to healthcare. For Anuj, Mirae’s CEO, the mission is also personal. His father was a GI clinician in rural upstate New York, where he saw firsthand how critical and unequal access to specialty care can be, something Anuj recently wrote about on Mirae’s blog.

The team behind Mirae

“It was very clear how unique and how critical having high-quality specialty GI care in a rural market helped patients and how unequal access to care across the US is,” Anuj explains. “It was important that we use technology to help patients that are at the intersection of a chronic, acute and complex condition, of which Crohn’s and ulcerative colitis were the obvious fit.”

Mirae grew from a shared desire to use technology to solve two connected challenges: the burden patients carry to track and remember their disease, and the limited snapshot clinicians often have when making important care decisions.

The “Aha” Moment

The realization wasn’t about one patient story, but where the most valuable information lives. In IBD, important signals are often small and daily: a change in urgency, creeping fatigue, or escalated symptoms when eating certain foods.

I know when my symptoms increase, I can become hypervigilant, quickly jumping to the worst-case scenario. Much of that internal battle happens privately, between me and the bathroom walls or in conversations with my mom and husband.

Yet very little of it makes it into the medical record. Instead, months of experiences get distilled into a few sentences during a clinic visit, filtered through stress and imperfect memory.

“The gap in IBD care is not a lack of good doctors or good treatments. It is that the richest data about the disease is generated by patients outside of a lab, colonoscopy or doctor’s visit and then mostly lost,” says Anuj. “Building something to capture that gently and carry it into the clinic in a useful form felt like the most obvious unsolved problem in the field.”

Anuj Patel, co-founder and CEO of Mirae Health

The Missing Puzzle Piece in Patient Management

As Mirae’s creators examined the gaps in IBD care, they saw one major problem: there was no single place connecting the pieces.

“People track symptoms in a Notes app, photos of meals on their phone, questions on scraps of paper, and half of it in their head. Most existing tools were built like diaries. They demand daily discipline, which is exactly what you do not have during a flare, so people abandon them when things get hard, when the data matters most. Most importantly, nothing connected the tracking to actual care,” says Anuj.

You can track symptoms for a year, but if your gastroenterologist never sees that information, it’s pointless. And when living with a chronic illness already feels like a full-time job, adding more work to disease management is the last thing those with IBD need.

Mirae aims to change that.

“We wanted to make day-to-day management delightful and to use the AI models developed by our team to better understand disease progression and connect that information to clinicians that can make more informed decisions on a patient’s care.”

Answering the Call as Patients Feel Overwhelmed and Unheard

Feeling unheard usually isn’t about clinicians not caring. It’s about trying to fit months of lived experience into a 15-minute appointment, with the patient expected to remember and explain it all on the spot. That’s an unfair expectation of someone who is unwell.

“Mirae is designed to carry that burden instead. The app does the organizing, the remembering, and the summarizing, so the patient does not have to perform their own case in the room,” says Anuj. “We kept the language plain, the daily effort small, and made forgetting or skipping days completely fine. The goal is that when you walk into a doctor’s visit, your patient experience is clearly summarized for a clinician, allowing the visit to be more humane and genuine, while helping clinicians make more informed treatment decisions.”

At home, Mirae is designed to make living with IBD feel a little lighter. You can think of it as a quiet companion while navigating an often-isolating disease.
“In the clinic, we want people to feel prepared and taken seriously. There is a real difference between walking in trying to remember everything and walking in with a clear summary of the last three months in your hand. One feels like being tested. The other feels like being a partner in your own care,” says Anuj.

A Step Toward Personalized Medicine and Treatment Options

Personalized medicine in IBD starts with recognizing that Crohn’s disease and ulcerative colitis are not one-size-fits-all. Mirae’s technology looks for patterns that can help identify patient subgroups and better understand how individuals respond to treatment.

“Knowing how patients in each subgroup respond to treatment or how symptoms manifest can help a care team recognize earlier when someone may need attention, rather than waiting for the next scheduled visit,” explains Anuj. “It can also make treatment discussions more grounded, starting with months of real-world data and experience that our tools can translate into clinical insight, rather than a few minutes of recollection.”

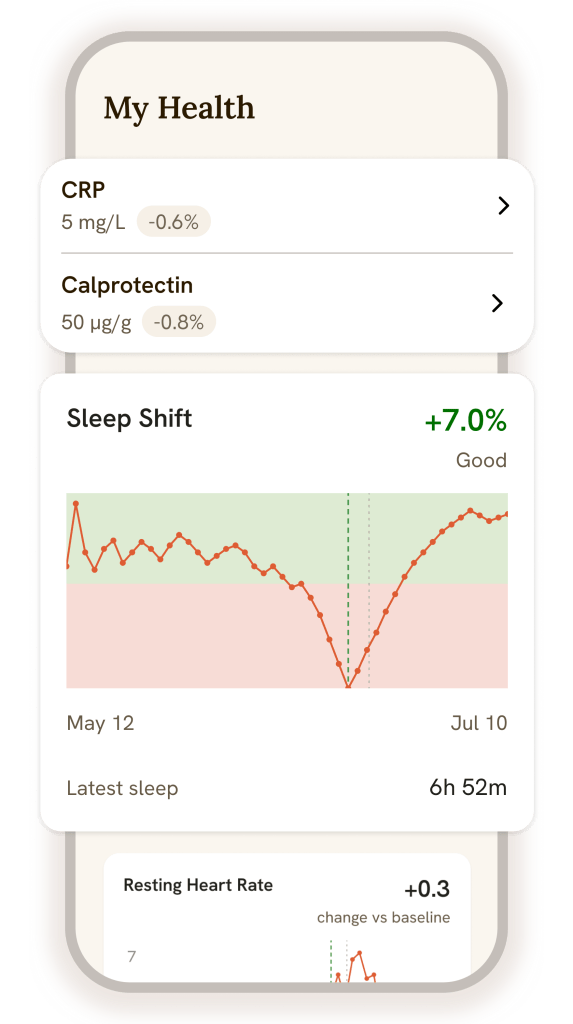
Mirae builds that picture from what patients choose to share over time: symptoms such as pain, urgency, bowel habits, fatigue, and energy; medications and how they’re tolerating them; lifestyle factors like sleep, food and activity; and free-form notes and questions captured in the moment.

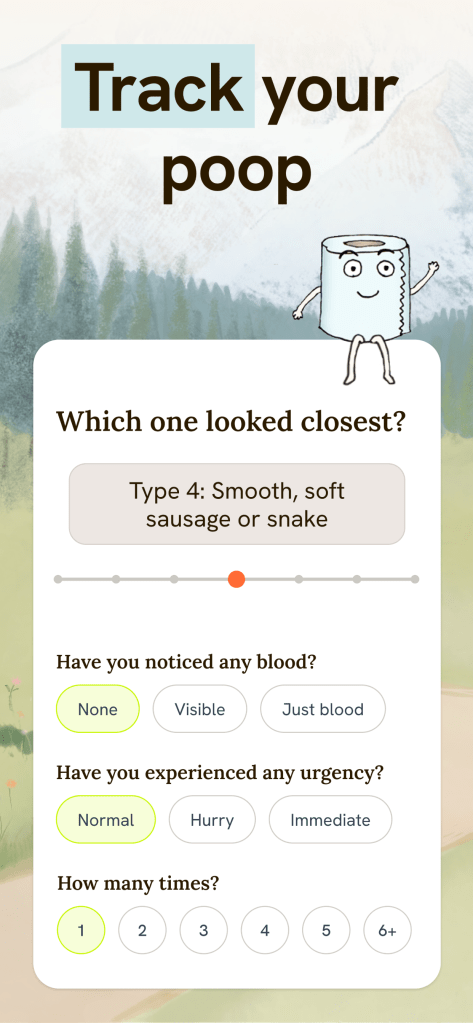
The app looks for what has changed and what you’ve flagged. Mirae suggests; you decide. The goal is to make sure the things that matter most to you are at the center of the conversation. Mirae supports clinical judgment; it doesn’t replace it.

The App Is Free—How?

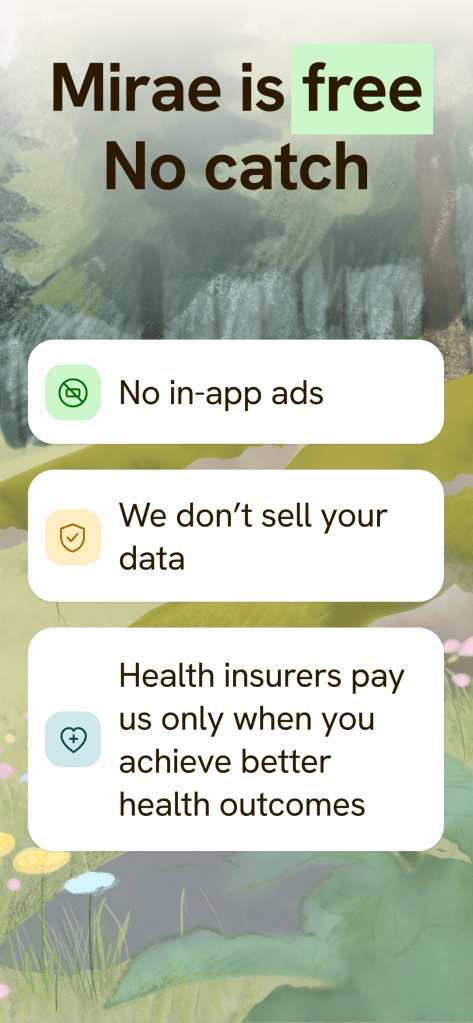
Living with IBD is expensive. Between medications, procedures, time off work, and everything in between, patients already carry a significant financial burden. Mirae’s creators didn’t want to add a subscription fee or rely on ads that could compromise the trust they’re building with patients.

“At a high level, our model works with the healthcare system for payment when patients enter remission sooner. Health systems and care programs benefit when patients arrive prepared, problems are caught earlier, and care between visits is more visible. All of this can help patients get on the right medication sooner while reducing future medical costs, such as surgery or ER visits,” says Anuj.
Making Patients Active Participants in Their Care

The biggest barrier to participating in our own care isn’t motivation, it’s preparation and organization. Too often, we leave appointments remembering the question we forgot to ask or downplaying what daily life with IBD feels like because suffering in silence has become our normal.

“Throughout the weeks between visits, the app makes it easy to capture questions and concerns as they come up, instead of hoping to remember them later. Before an appointment, it helps pull everything together into pre-visit notes: what has changed, what’s worrying you, what you want to ask, and what you want out of the visit,” explains Anuj.

When you arrive with that information in hand, the dynamic shifts. You’re no longer a passive recipient. You have an agenda backed by your own experience. That’s active participation in your care.

The Power of Pre-Visit Notes

One of my favorite Mirae features is the pre-visit process. You can capture observations about your health, answer targeted questions, and, most importantly, identify your biggest concerns going into the appointment.

Mirae then turns that information into a plain-language summary: what has changed, what has stayed stable, what’s worrying you, and the questions you want to address.
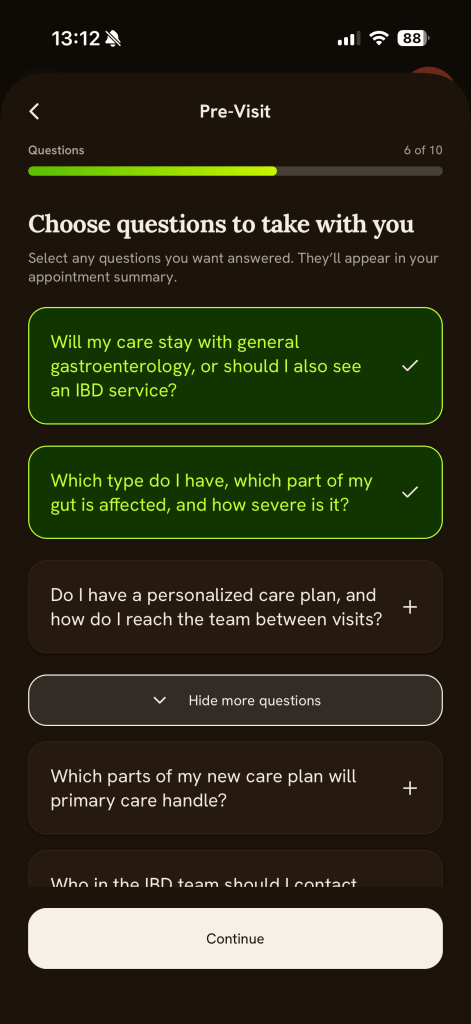
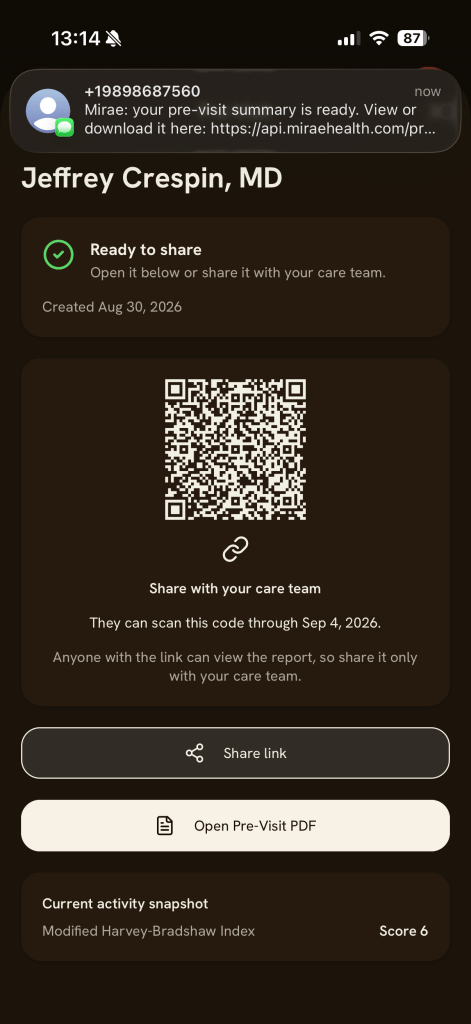
“You can edit anything, remove what doesn’t matter to you, and rank what you most want to discuss. You stay in control of what is shared. When you’re done, you have a short, clear document you can bring into the room or share ahead of the visit,” says Anuj.

An educated patient is an empowered patient. Taking a few minutes to prepare can help both you and your provider make the most of limited appointment time, something especially valuable when we’re juggling multiple specialists.

“The core principle is to change from your own baseline. A symptom level that is normal for one person may be a red flag for another, so relevance is always personal,” says Anuj. “The app looks at what is new since the last visit, what has been trending in either direction, or what has been persistent. Mirae also gives weight to things you have marked as important, medication changes and how they have gone, and anything that has come up repeatedly in your notes. Repetition is a strong signal that something deserves airtime.”

Input from Medical Providers and IBD Patients

Mirae was shaped with input from IBD clinicians, including advisors at Oxford and across the United States.

A consistent theme was where the appointment begins. Too often, the first minutes are spent reconstructing months of symptoms from memory. With organized pre-visit notes, that work is done, allowing more time for meaningful discussion, decisions, and care planning.

“Clinicians have also been clear with us about what they do not want: another screen, more unfiltered data, or anything that adds time. That feedback pushed us to keep the clinician-facing side short and structured. As the pilot progresses, we will let the results speak rather than getting ahead of them,” explains Anuj.

Dr. Simon Travis, Professor of Clinical Gastroenterology at the University of Oxford, sees Mirae as ‘stepping stones across a river, sometimes widely apart.’

He says, “Mirae acts as a bridge. It provides depth, credible advice, links to the evidence, informed comment, and guidance. It complements specialist advice by addressing complex factors such as fatigue or diet in detail, way beyond what is possible to cover during a consultation.”

Dr. Alissa Walsh, a Gastroenterologist at the Oxford University Hospitals NHS Trust and Nuffield Health, The Manor Hospital, Oxford, agreed to support Mirae because she believes people living with IBD deserve to be active partners in their own care, not passive recipients to it.

“Too often patients feel they’re navigating this condition alone, without the information or confidence to ask the right questions,” she says. “Mirae’s work has the potential to change that — empowering patients at every stage of their journey and, ultimately, improving the quality of care they receive.”

As an IBD patient advocate, I’m one of many who have helped to provide feedback and guidance through the app development process. Having patient and provider input is paramount to making sure the app works for us in real time. Multiple members of the Mirae team also have IBD themselves.

“It is hard to advocate for yourself on subjective terms such as “I feel like things have been worse lately.” It is much easier when you can say things have been different for six weeks, here is the pattern, and here is what I would like us to consider,” says Anuj. “When patients see their experience taken seriously, written down, reflected back, and brought into the clinical conversation, it reinforces that their observations matter.”

What Sets Mirae Apart from Other IBD Apps?

Most health apps are islands: you track diligently, but the information rarely goes anywhere. Mirae aims to close that gap in three ways:

  • Connected to clinical care. Mirae is designed to work with a patient’s existing care team. The information gathered is intended to inform care rather than sit in a silo. Its first deployment is within a large academic medical center.
  • Built specifically for IBD. This isn’t a general wellness app with an IBD mode. Mirae was incubated at Oxford’s Computational Health Informatics Lab and shaped by IBD specialists and patients.
  • Designed for both patients and clinicians. Rather than making patients pay for premium features or clinicians pay costly software fees, Mirae is built to serve both sides of the care relationship.

The Goal Five Years from Now

Looking ahead, Mirae’s creators hope the platform will build something that doesn’t currently exist at scale: a rich repository of patient-reported symptoms connected to clinical data that could improve treatment recommendations and eventually inform drug discovery. Longer term, they envision expanding beyond IBD to other autoimmune conditions, where many of the same challenges exist.

“The goal for us is in five years, is that “Maya”, a newly diagnosed Crohn’s patient, is able to use our platform to have a trusted companion that helps her understand her condition and, alongside her gastroenterologist, precisely identify the specific type of Crohn’s she has, find the best therapy for that type, and get on her way to remission and stay there.”

For Mirae’s founders, success means making that experience the norm, so Crohn’s becomes one part of Maya’s identity, not something that consumes her life.

Final Thoughts

Mirae’s goal is to end the era of memory-based appointments where patients carry months of their lives in their heads, then try to summarize it all under pressure. For gastroenterologists, it’s a similar challenge: extracting that information while balancing an enormous amount of clinical knowledge.

Mirae is designed to fit into patients’ lives, especially during the hard weeks, helping turn real observations into a clearer picture of their health and a more personalized care plan.

“We hope Mirae shifts some weight off patients’ shoulders. Managing IBD will never be effortless, but the administrative and cognitive load, the tracking, remembering, and preparing is something technology can genuinely carry. If patients spend less energy managing their disease and more living their lives, we have done our job.”

Download Mirae for FREE! Learn more about Mirae here.

Apple Store

Android

Eighteen Years of Humira: The Treatment That Helped Me Build a Life, Not Just Manage a Disease

Eighteen years ago, when I was 24 years old, I gave myself my very first Humira injections following a hospitalization for an abscess the size of a tennis ball in my small intestine. The loading dose involved four painful injections, in my GI office. While much of my patient journey tends to be a blur, the day I started Humira is crystal clear in my memory. I remember how I was sitting, what it felt like, the emotions, the tears, the worry about starting a biologic medication, and the desperation to be well.

I don’t have any photos of the day I started on Humira, but this was the month after my loading dose, while still on 60 mg of prednisone.

At the time, I wasn’t thinking about anniversaries or milestones. I wasn’t wondering if I’d still be taking this medication nearly two decades later. I was simply hoping it would work. This week on Lights, Camera, Crohn’s I reflect on what I’ve learned and what I wish I knew all those years ago.

Would life ever be the same?

When you live with Crohn’s disease or ulcerative colitis, hope can sometimes feel like the most powerful prescription of all.

Back then, my disease had already taken so much from me. I had endured three years of on and off flares, hospitalizations, procedures, uncertainty, and the emotional weight that comes with wondering if you’ll ever feel like yourself again. I went from being a perfectly healthy person to being diagnosed with Crohn’s at age 21, put on 22 pills a day, and not knowing what the future would hold.

Humira didn’t cure my Crohn’s disease. There is still no cure, of course. But it gave me something I desperately needed: stability. Over the past 18 years, this injection has quietly stood beside me through nearly every major chapter of my adult life.

It helped me continue my career as a television journalist and keep my IBD private from the public, thanks to the medication being a self-injection. It was there as I found my voice as a patient advocate and launched Lights, Camera, Crohn’s. It was there when I fell in love, got married, and became a mom to three children. It’s been there through pregnancies, postpartum life, sleepless nights, school drop-offs, family vacations, soccer/baseball/basketball games, dance recitals, and countless ordinary moments that aren’t ordinary when you’re living with a chronic illness.

Because chronic illness has a way of making the ordinary feel extraordinary.

My youngest child was ironically born on the anniversary of when I started Humira (July 14th)!

Not all sunshine and rainbows

There have certainly been bumps along the way. People are often surprised to hear that I still had multiple bowel obstructions and hospitalizations prior to my bowel resection surgery in 2015, despite being on Humira. More recently, I experienced firsthand how disruptive a forced switch to a biosimilar in 2024 was before successfully appealing to return to Humira. And like anyone living with inflammatory bowel disease, I still have difficult days, anxious moments, unexpected symptoms, and reminders that remission doesn’t always mean life is symptom-free.

But through it all, Humira has remained the foundation of my treatment and a crutch in my life. I recognize how fortunate I am to still be on the same therapy all this time.

No two journeys look the same

One of the greatest lessons patient advocacy has taught me is that no two IBD journeys look alike.

I know many people who have cycled through medication after medication searching for relief. Reminder: The medications are failing you; you aren’t failing anything. Others have exhausted every available therapy, no fault of their own. Some are preparing to start clinical trials because approved treatments have stopped working. Many have endured multiple surgeries, ostomies, prolonged hospital stays, or years of uncontrolled inflammation despite doing everything right.

Their stories matter just as much as mine.

When I share that one medication has managed my disease for 18 years, I don’t do so to suggest this is typical or attainable for everyone. I share it because it represents what every person living with IBD deserves: a treatment that allows them to live life fully. When I started Humira 18 years ago, I had no idea if it would help control and manage my Crohn’s.

I never take that for granted. I don’t know if a year from now I’ll still be in the same boat or if this is a medication I will be on for the rest of my life. I’ve gotten to the point where it’s difficult to imagine life without it, which can feel a bit daunting.

Science changes lives

Every injection is a reminder that science changes lives.

Years ago, biologic medications transformed what was possible for people like me. Back in 2008, there were only two options for IBD patients (Remicade or Humira), now the landscape for treatment options is so vast. Before these therapies existed, many patients faced repeated surgeries, lengthy hospitalizations, and significantly fewer treatment options. Steroids were the go-to. Today, the landscape continues to evolve with new biologics, biosimilars, small molecules, and research that offers hope to the next generation of patients.

I’ve had a front-row seat to that evolution, not only as a patient but as an advocate and journalist interviewing physicians, researchers, and fellow patients around the world. I’ve learned that medicine isn’t just about controlling inflammation.

It’s about allowing someone to chase a career.

To become a parent.

To celebrate birthdays.

To travel.

To make memories.

To simply say yes to life more often than no.

Final thoughts

For me, Humira became more than a medication. It became a bridge between the life Crohn’s disease tried to take away and the life I was determined to build.

If you’re reading this and your current treatment isn’t working, please don’t lose hope.

I’ve met far too many people who found the right therapy after believing they’d run out of options. Research continues to move forward. New medications continue to emerge. Physicians are learning more every year about how to personalize treatment and truly target our disease. Your next chapter may look very different from the one you’re living in today.

And if you’ve found a treatment that works, whether it’s been six months, six years, or eighteen years, I hope you pause to appreciate what an incredible gift that is. Not because the journey is easy. But feeling well enough to live your life and discover a new normal is something worth celebrating.

Today, I’m incredibly grateful.

Grateful to the physicians who believed in biologic therapy long before it became commonplace. Grateful to researchers who dedicate their careers to continuing to advance IBD care. Grateful to my family for standing beside me through every injection and every flare. And grateful for a medication that has helped me experience so many beautiful moments I once feared Crohn’s disease would steal.

Eighteen years later, I’m still here. Still advocating. Still telling stories. Still raising my family. Still chasing dreams. Still injecting every other week.

And I am still profoundly thankful that this self-injection that I’ve given myself 480 times, has helped me live a life that has been so much bigger than my diagnosis.

Hydration and IBD: Why Summer Can Be More Complicated Than It Looks

As temperatures rise, so can the challenges of living with Crohn’s disease and ulcerative colitis. For people with inflammatory bowel disease (IBD), summer heat (and heat in general) isn’t just uncomfortable, it can amplify symptoms, increase dehydration risk, worsen fatigue, and make everyday activities feel far more difficult.

And while everyone is told to “drink more water” during the summer, hydration with IBD is often much more complicated than that. Living in St. Louis, I’m no stranger to extreme heat and humidity!

Between diarrhea, ostomies, inflammation, medication side effects, and nutrient absorption issues, those of us with IBD are already operating at a hydration deficit before stepping outside into 90-degree-plus weather. This week on Lights, Camera, Crohn’s a look at what patients need to know about staying safe, hydrated, and feeling their best during the hottest months of the year.

Why People With IBD Are More Vulnerable to Dehydration

Dehydration happens when your body loses more fluids than it takes in. While that can happen to anyone in the heat, people with IBD face unique risks.

Some of the biggest contributors include:

  • Frequent diarrhea
  • Active inflammation
  • Vomiting
  • Excessive sweating
  • Reduced appetite
  • Short bowel syndrome
  • Ileostomies or J-pouches
  • Certain medications
  • Avoiding fluids due to bathroom anxiety

For patients with Crohn’s disease affecting the small intestine, the body may also struggle to absorb fluids and electrolytes efficiently. Meanwhile, people living with an ostomy can lose significant amounts of sodium and fluids throughout the day, especially in extreme heat. The result? We can become dehydrated faster than we realize.

Signs of Dehydration Can Look Different in IBD

Many symptoms of dehydration overlap with symptoms those with IBD already experience regularly, which can make it harder to recognize when something is wrong.

Common warning signs include:

  • Dizziness or lightheadedness
  • Fatigue or weakness
  • Headaches
  • Muscle cramps
  • Dry mouth
  • Rapid heartbeat
  • Brain fog
  • Dark urine
  • Nausea
  • Increased GI symptoms

For some, dehydration can trigger a vicious cycle: diarrhea leads to fluid loss, dehydration worsens fatigue and weakness, and patients feel too sick to adequately rehydrate.

Why Water Alone May Not Be Enough

One of the biggest misconceptions about hydration is that drinking plain water is always sufficient.

In reality, many IBD patients lose electrolytes (especially sodium and potassium) along with fluids. Drinking large amounts of water without replacing electrolytes can sometimes leave us feeling even worse.

Electrolytes help the body:

  • regulate fluid balance
  • support muscle function
  • maintain blood pressure
  • keep nerves functioning properly

That’s why your gastroenterologist may recommend oral rehydration solutions or electrolyte drinks during flares, illness, travel, heat exposure, or high-output ostomy periods.

Be mindful that some sports drinks contain large amounts of sugar or artificial sweeteners that can aggravate symptoms. I’ve personally had luck with DripDrop and Liquid IV.

Summer Activities Can Add Another Layer of Stress

Summer doesn’t just bring heat; it brings logistical anxiety. Long car rides and flights for fun travel. Outdoor festivals. Pool days. Sporting events. Theme parks. Beach vacations. Going to parks with the kids that don’t have bathrooms. The list goes on and on. I know I feel extremely anxious every time I get on my in-law’s boat and just pray, I don’t run into any bathroom issues!

We often become hyper-aware of where bathrooms are located, whether they’ll have access to safe foods, and how quickly heat exhaustion could escalate symptoms. And unlike others, people with chronic illness often can’t simply “push through” dehydration or fatigue.

Medications Can Complicate Heat Tolerance

Certain medications commonly used in IBD management may affect how patients tolerate heat. Steroids can increase sweating and cause fluid shifts within your body, some medications can cause nausea (Zofran to the rescue!), and fatigue from chronic inflammation can worsen when temperatures rise (especially if you’re anemic)!

Tips for Staying Hydrated With IBD This Summer

While every patient is different, experts often recommend:

Hydrating Before You Feel Thirsty. Thirst can be a late sign of dehydration. Consistent hydration throughout the day is key. I make a point of making a water bottle for myself before I even have breakfast or my coffee each morning. As an IBD mom, we can get so busy taking care of everyone else that we can put eating and drinking on the backburner for ourselves.

Focus on Electrolytes During High-Risk Situations

Especially:

  • outdoor events
  • travel days
  • exercise
  • active flares
  • ostomy output increases
  • stomach illnesses

Carry “Safe” Hydration Options: Many people find certain drinks are easier to tolerate than others. Trial and error matters. What may help someone else, may not sit well with you.

Eat Hydrating Foods: Foods like watermelon, lettuce, celery, zucchini, bell peppers, cucumbers, broth-based soups, smoothies, and fruits can contribute to fluid intake. If you’re currently flaring or have active stricturing disease, talk with a registered dietitian about how to navigate this (ex. Cooking the veggies so they’re tender or chewing to applesauce consistency).

Be Careful with Alcohol and Excess Caffeine: Both can worsen dehydration for some people.

Watch for Heat Exhaustion: If symptoms escalate to severe dizziness, fainting, confusion, rapid heartbeat, or inability to keep fluids down, medical attention may be necessary. Be vigilant and proactive as best you can.

The Emotional Side of Summer With Chronic Illness

There’s also a mental load that comes with navigating summer while living with IBD.

Many of us want to participate fully in vacations, outings, and family activities, but may quietly spend the entire day navigating bathroom access, our energy levels, finding safe foods, and staying on medication schedules. That invisible planning can be exhausting.

And for parents with IBD, summer can feel even more physically demanding. I’m gearing up for that with my three kids! The combination of heat, disrupted routines, increased outdoor activities, and caring for children often leaves little room for rest and recovery. Now that my kids are 9, 7, and almost 5, I know that everyday doesn’t need to be an adventure and that low-key days at home can be just as fun for everyone, too. There’s all this hype about bringing back the 90’s summer. Listen to your body and if it means staying home and having the kids ride their bikes, run through the sprinkler, and have popsicles versus going to parks, pools, and amusement parks—that’s ok. Give yourself grace, your body will thank you!

The Bottom Line

Hydration isn’t just a wellness trend for people with IBD, it’s a critical part of symptom management and overall health and something to discuss with your care team.

As summer temperatures climb, patients may need to be more proactive about fluids, electrolytes, rest, and recognizing the early signs of dehydration. As always, listen to how your body speaks to you through symptoms and do your best to address those needs before they become an acute issue.

Because while summer is often portrayed as carefree, many people living with Crohn’s disease and ulcerative colitis are dealing with an entirely different reality behind the scenes: one that requires constant awareness, preparation, and self-advocacy just to feel well enough to participate.

News You Can Use

Electrolytes and Hydration for IBD: What You Need to Know — Stacey Collins Nutrition

The Connection Between Ulcerative Colitis and Dehydration

Inflammatory bowel disease (IBD): Staying hydrated – AGA GI Patient Center

Dehydration: How to Avoid It If You Have IBD

4 Ways To Avoid Dehydration and Balance Electrolytes With Crohn’s and Colitis | MyCrohnsAndColitisTeam

Traveling with IBD: Real Talk, Hard Truths, and the Courage to Keep Exploring

Traveling with inflammatory bowel disease (IBD) is rarely as simple as packing a suitcase and showing up. It’s logistics, emotions, planning, and flexibility. It takes a bit of hypervigilance. This layered on top of a disease that doesn’t take vacation days. But it is possible. And for many of us, it becomes one of the most empowering reminders that life with IBD can still be adventurous, and rich with new experiences.

This week on Lights, Camera, Crohn’s you’ll hear from two incredible IBD advocates, Kelly Dwyer and Rachel Verbanac. They both open up about their diagnoses, their anxieties, their coping strategies, and their go-to travel essentials. Their honesty and wisdom offer a roadmap for anyone who wants to explore the world without letting IBD call all the shots.

Meet Kelly: 21 Years of Symptoms, 7 Years Diagnosed

Kelly may have been diagnosed with Crohn’s disease in 2018, but she’d been living with severe perianal fistulizing ileal Crohn’s since the early 2000s.

“Before diagnosis, I avoided significant travel whenever possible because I was so ill. And when I did travel, I tried so hard to plan for every single scenario that it became stressful for me and everyone around me.”

Now in deep remission thanks to medication, Kelly still plans intentionally, but the difference is that the planning empowers her instead of holding her back.

She structures trips around:

  • Her injection schedule
  • The time of day she flies or drives
  • What foods she eats before travel
  • How to pace her energy
  • And what she needs to stay healthy while surrounded by crowds

“I wear a mask, use sanitizer constantly, wash my hands as much as I can… it all helps me feel like I’m doing what I can to set myself up for success.”

Kelly on Travel Anxiety: The Trauma Stays with You

Despite years of remission, Kelly still carries fear rooted in lived experience.

“I constantly worry about not making it to a bathroom. Even though it has not happened in years, that trauma stays with you.”

Kelly also experiences nausea, anxiety and a whole lot of gas and burbling guts when she travels.

“Finding the right medication cocktail that keeps things calm and in order in my guts (and brain!) took a lot of trial and error, but was worth it for me to find a combination to give me confidence that I’ll feel like I’ve done everything I can to get the trip off on the right foot. I would recommend you ask your doctor or GI about Zofran, anti-anxiety medications in small doses, Gas-x, antacids, and other OTC medications that might help you to make sure they’re safe for you to take.”

She’s built a system that helps her feel confident when she’s traveling:

  • A “Can’t Wait” restroom access card
  • Depends or heavy-duty panty liners on days she’s unsure
  • Change of clothes and wipes in her purse, not her carry-on
  • Imodium and emergency meds ready to go
  • Small meals before and during travel days
  • Medication for nausea, anxiety, gas, and gut discomfort

“I had to learn to relax into the chaos of travel and not panic when plans change. Travel is unpredictable—but so is Crohn’s.”

The Power of Protection: Insurance (Both Emotional and Literal)

Kelly is adamant that travel insurance is non-negotiable.

“I have used travel insurance many times for flare-related cancellations. It can be heartbreaking to miss something important, but it’s not your fault. This is your reality, and you’re doing your best.”

She also communicates openly with travel companions, so expectations are clear and compassionate from the start.

“Find as much peace as possible. Asking for everyone’s understanding and compassion, is so important. I remind myself that it’s not my fault that I am unwell. It’s not anything I did to cause the flare. This is simply my reality, and I am trying my very best, even if it doesn’t always work out the way I’d hoped.”

Kelly’s Must-Have Travel Kit

Here’s what she never leaves home without:

Kelly’s biggest piece of advice?

“Treat yourself with compassion, always. Build in extra time everywhere. Your comfort is worth it. Having a few extra hours at the airport to sit and read a magazine is much preferable to rushing through security lines and not being able to use the bathroom before getting on the plane because you’re late.”

Meet Rachel: A Travel-Lover Who Refused to Stop Exploring

Rachel was diagnosed with Crohn’s disease in 2021, right as she was going back to nursing school. Before that, she spent months living a nomadic lifestyle in New Zealand and expected to spend her twenties exploring the world. Her diagnosis meant rethinking what travel could look like. Requiring infusions changed everything.

“Hiking the Appalachian Trail used to be a dream, but with the need for insurance, pharmacy authorizations, infusion clinics, and access to university health systems… that lifestyle just wasn’t realistic anymore.”

But Rachel didn’t stop traveling. She adapted.

How Rachel Travels Now

Rachel describes herself as someone who “packs her anxieties,” but in a productive way.

Her prep includes:

  • Bringing a med kit stocked with small doses of essential meds
  • Monitoring hydration closely on travel days
  • Planning meals and bowel habits ahead of time
  • Understanding bathroom access in each country
  • Carrying small local currency bills for paid restrooms
  • Bringing a letter from her provider outlining her diagnosis and meds

“After many international trips, I’ve proven to myself that how I feel at home reflects how I feel on the road.”

Rachel also buys comprehensive travel insurance that covers pre-existing conditions, often from TinLeg, and encourages others to read the fine print carefully, especially regarding upfront payment rules.

“I feel much more secure knowing all medical bills will be paid for should I need anything abroad. Beyond health insurance, I have used the insurance for trip interruption and costs of delays. I also have my provider write me a letter stating my disease, common side effects, and my current medications. This letter can be useful when seeking care at a new clinic or if TSA should ever give you a difficult time (I have never experienced this). I like having the physical letter in the med kit.”

Bathroom Access: A Cultural Learning Curve

When traveling with others, Rachel gives them a heads up that access to bathrooms is a priority for her. Especially when traveling in Europe.

“Europe often requires a purchase to use a restroom. You cannot just run into a McDonald’s.”

Her strategy?

And she always tried to keep everything in perspective, even when the unexpected happens.

“Accidents are embarrassing, but you will most likely never see these people again. It is okay. You are okay.”

Travel Anxiety: You’re Not Alone

Rachel acknowledges the fears that come with IBD, but her message is clear:

Do not let IBD keep you from seeing the world.
Start small and your confidence will grow.

She now travels to Mexico annually and cannot imagine winters without it.

Nurse-Approved Safety Tips from Rachel

Some of her favorite reminders:

  • Even healthy travelers get GI bugs—be cautious with food and water. Taking general precautions like only drinking bottled water in areas where the water might not be safe to drink, sanitizing your hands often, and avoiding touching your eyes and mouth are still the best ways to prevent infections.
  • Avoid buffet sushi
  • Choose made-to-order stations
  • Read resort and food reviews. She checks out Google reviews, TripAdvisor, and Hotels.com to see what people have to say before she books a trip.
  • Wear an N95 on flights to avoid illness and see if your travel companions will do the same to help keep germs at bay.
  • Advocate for yourself with travel companions
  • Read Google reviews quickly if you’re unsure of a restaurant, locals and travelers will share if they got sick eating there. Look for highly frequented places.

As a nurse, Rachel has these words of wisdom for our community, “Don’t let IBD keep you from seeing places and experiencing new cultures. Often as patients we have anxiety and unknown destinations can seem overwhelming and scary. Start small and your confidence will grow, promise.”

Rachel’s Travel Med Kit

She carries:

  • Doctor’s letter
  • Hand sanitizer
  • Tylenol
  • Imodium
  • Pepto
  • Tums
  • Fiber
  • Gas-X
  • Benadryl
  • Dramamine (also helpful for intense nausea)
  • Zofran
  • Liquid I.V.
  • Band-Aids that are a few sizes
  • Contact solution or small vial of artificial tears (I wear contact lenses) 
  • A few doses of Dayquil and Zyrtec—when changing the container medication comes in, be sure to write the dose (mg or ml or the number of pills) and how often you take it.
  • A tube of triple antibiotic ointment and hydrocortisone ointment (for scrapes and bug bites)

Final Thoughts: You Deserve to Experience the World

Traveling with IBD takes more planning, more flexibility, and more courage than most people will ever understand. But as Kelly and Rachel show, it’s possible and it can even become empowering.

As someone who was diagnosed with Crohn’s more than 20 years ago traveling can still make me feel a bit uneasy. I always keep pain medication, Zofran, and Dramamine in my carry on. If you have to pack your biologic medication, keep that on you as well. It’s important to check how long your injection can be out of the fridge. Nowadays, Humira for example, can be unrefrigerated for up to 14 days. If you have to do your injection while away from home, make sure to have alcohol swabs and an ice pack (if you are used to using one).

I never drink caffeine prior to flights or long road trips, and I eat very light until I am at my destination. I try to dress as comfortably as possible, and do not restrict my belly in any way. The moment I get to my hotel room I take off my travel clothes and shower. If you are traveling and feeling symptomatic, it can be helpful to alert your care team at home and also do research beforehand about local hospitals so you have a game plan in place should you be facing an acute flare that may require a trip to the emergency room.

Whether you are taking a weekend road trip or boarding a long-haul flight, remember:

You’re allowed to take up space.
You’re allowed to prioritize your needs.
You’re allowed to choose comfort over speed.
You’re allowed to protect your energy.

And most importantly:

You deserve to make memories that reach far beyond the walls of your disease.

Additional resources

Traveling with IBD | Crohn’s & Colitis Foundation

Crohn’s Disease: Plan Ahead to Make Travel Easier

Travel Tips When You Have Ulcerative Colitis

Tips for Long Travel Days When You Have Crohn’s Disease

Snacks for Crohn’s Disease: 10 Easy Grab-and-Go Ideas

I’m a Frequent Traveler With Crohn’s Disease—Here Are My Packing List Non-Negotiables | Condé Nast Traveler

21 Tips for Traveling with IBD – Romanwell

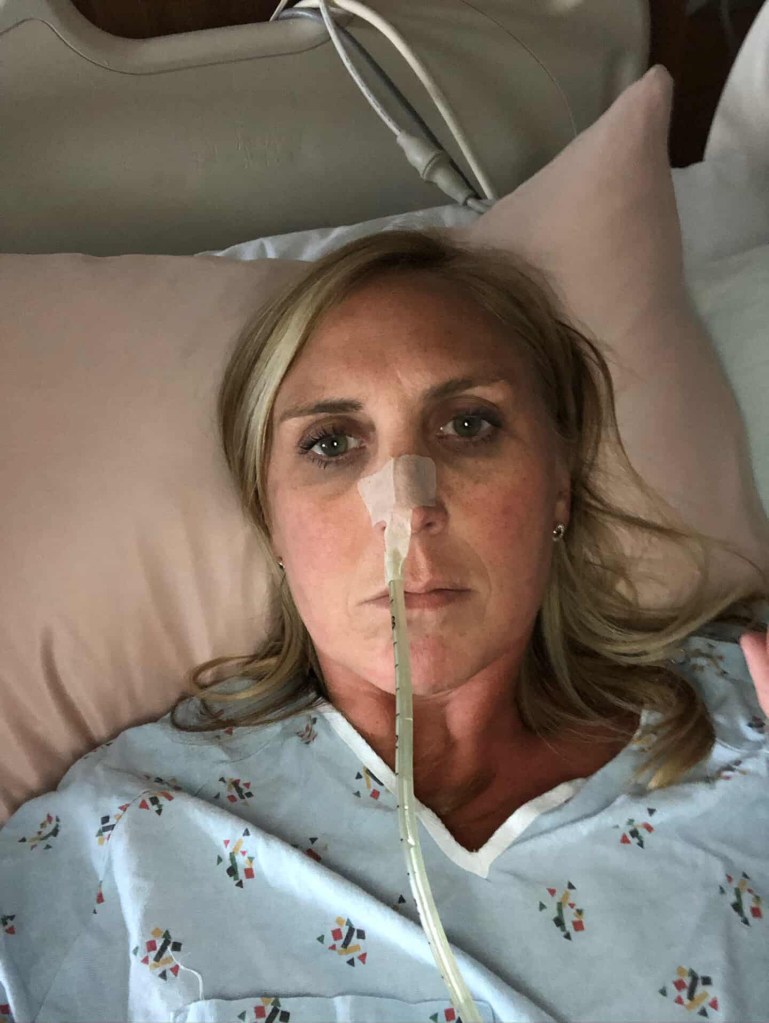
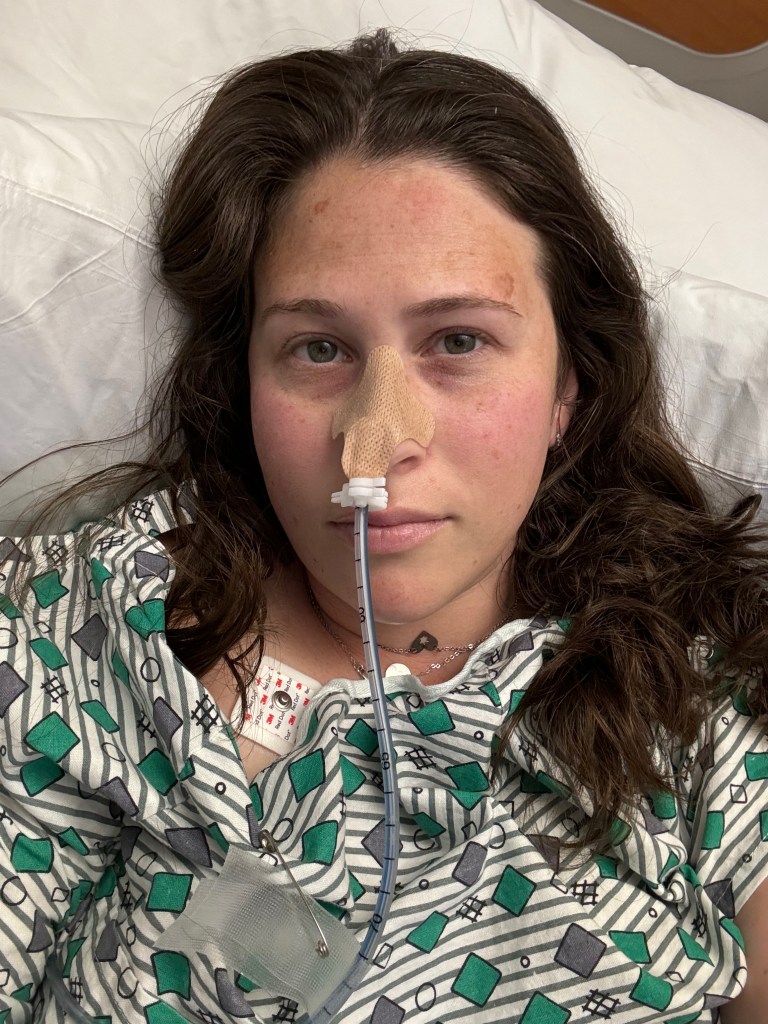
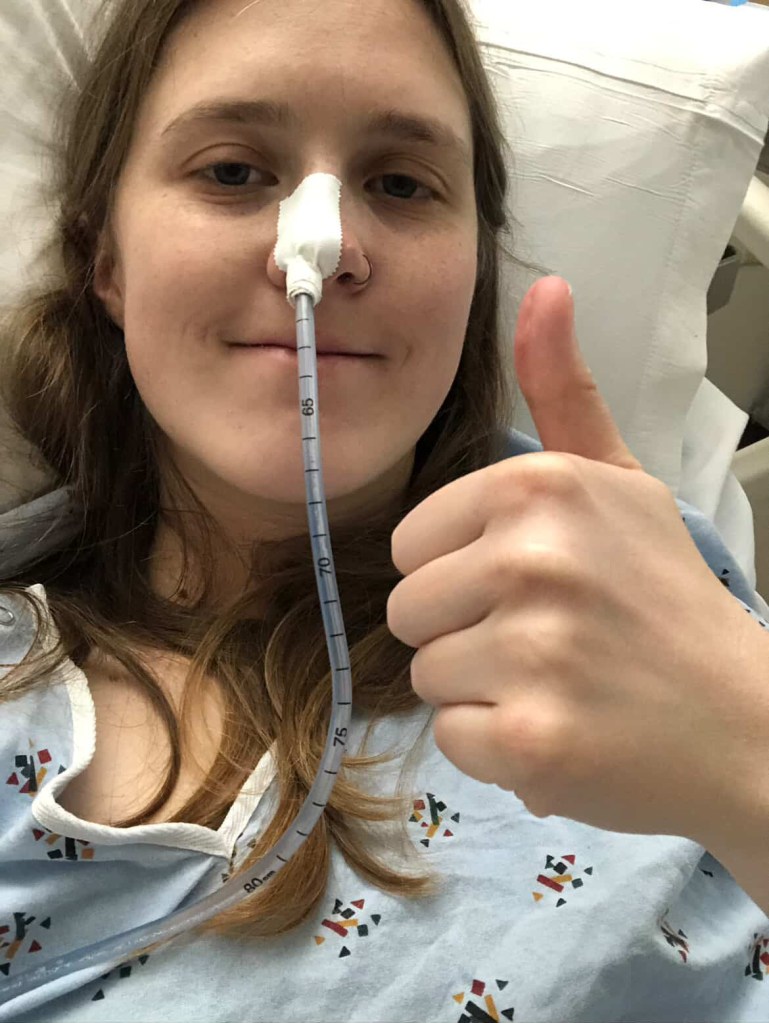
Navigating NG Tubes: Practical Tips and Emotional Support for Patients and Caregivers

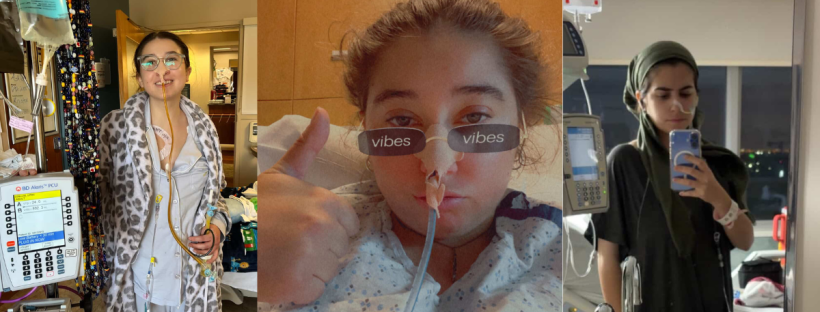
When you live with Inflammatory Bowel disease, there’s no telling if or when you’re going to need an NG tube (nasogastric tube) to help stabilize your symptoms, deliver nutrition, and help your body heal. In my 20-plus years living with Crohn’s disease, and despite many hospitalizations for bowel obstructions, I have never needed one (yet). Recently, a fellow IBD mama on Instagram shared about getting one as she’s hospitalized right now (with a new/additional diagnosis-Gastroparesis), and her experience inspired this article.

This week on Lights, Camera, Crohn’s, a guide that breaks down what to expect, what helps, and how we can best cope from fellow patients and caregivers who have lived through it. Whether you are facing your first tube placement or supporting someone who is, the fear of the unknown can often feel bigger than the procedure itself.

Understanding the Process (and Why It’s So Intense)

NG tube placement can feel overwhelming because it involves an extremely sensitive area: your nose, throat, and gag reflex. It is quick, but not exactly pleasant. Knowing what is coming can dramatically reduce anxiety.

An NG tube is typically used for:

  • Bowel rest and decompression during IBD flares
  • Relieving bowel obstructions
  • Nutrition support
  • Medication delivery

And while the experience varies widely, preparation and honest communication with your care team make a huge difference.

Before Placement: Preparing Your Mind and Body

  • Ask for numbing options: Most hospitals can use lidocaine spray or gel in your nostril to make the initial insertion more tolerable. It is worth requesting.
  • Practice slow breathing: Focusing on deep, steady inhales through your nose helps decrease the gag reflex and keeps your body relaxed.
  • Sit upright with your chin slightly tucked: This position straightens the path the tube travels and can make the process smoother.
  • Have emotional support: Whether it is a partner, parent, friend, or even someone on speakerphone, having a familiar voice can ease anxiety.

During Placement: Strategies That Actually Help

  • Swallow as the tube advances: If the nurse allows, sipping water and swallowing as the tube moves downward helps guide it into the esophagus rather than the airway.
  • Anchor your eyes on one spot: A visual point of focus reduces the instinct to pull back or panic.
  • Choose a mantra: Something like “This is temporary” or “Every swallow gets me closer” can center your mind.
  • Ask your nurse to narrate the steps: Knowing what is happening and when it will be over prevents surprises and makes the process feel more controlled.

What Patients and Caregivers Have to Say

Hindy: “I would say to request the thinnest tube possible. It is really awful.”

Ashley: “It’s a horrible experience. I’m glad I didn’t know what to expect before getting one placed, because I don’t think I would’ve been able to handle it. I don’t think there’s anything that could have prepared me for it.”

Amy has IBD and her four-month-old daughter does not, but she has had an NG tube for two months, due to issues with strength, stamina, and desire to eat after being born prematurely.

“She was diagnosed with Failure to Thrive, and her NG tube has been lifesaving! I can guarantee she gets the nutrients she needs to grow and thrive. She tolerates the NG tube very well. She has pulled it out multiple times, but thankfully we live close to the GI clinic and a great Children’s hospital.”

Amy has found there are certain strategies to limit the number of times she pulls the NG tube out, such as taping it closer to her nose. She says it can be stressful at times, but luckily with her medical background she knows how to clean the tube 8 times a day. Even though her daughter has handled the NG tube like a champ, Amy and her husband have decided to transition to a G-tube, since their baby girl will need nutritional support for a little bit longer, which Amy thinks will aide in comfort and speech development.

Alexis: “Get a little white board so that you can write what you want to say as talking is so uncomfortable.”

Karen: “Taking anti-anxiety + pain medication to help with the uncomfortable pain and anxiety that NG’s cause. I refuse NG tubes now without serious meds, the trauma, pain, and discomfort they cause must be treated and I think providers really underestimate how traumatizing it is to have one, especially if it’s put in while you’re awake.

Amanda: “Ask for some nebulized lidocaine before insertion.”

Abbie: “Ask for throat numbing spray!!! I was given it my first time and then every other time I’ve had to ask, but I’m so appreciative the first nurse I had gave me some so I knew to ask for it in the future.”

Sarah: “I didn’t even know what an NG tube was until it was already inserted. I suppose the shock of how quickly the insertion went shielded me from the pain and discomfort. Numbing spray was the only way I could cope with the tube irritating my throat. Mine was in for three days while I had a bowel obstruction and the day it came out felt like FREEDOM.”

Becca: “They are the f***ing worst. You can quote me.”

Melissa: “I had one they put in while I was awake and after SIX tries, I was adamant on getting something to relax me. They put a little something in my IV and then it went down without an issue. I also had a smaller one, more child-sized than adult.”

Dana: “I wish I had something positive to say about NG tubes, frankly I didn’t cope at all until they gave me Ativan and eventually a muscle relaxer. Sometimes they can give you a numbing throat spray to help with irritation. After the first few days, it gets little more tolerable as your body gets used to it.”

Jennifer: “OMG. 26 years with Crohn’s and nothing traumatizes me more than the mention of an NG tube. I was about 95 pounds the first time I got one. I’m almost 5 feet tall, and after two tries of me not being able to breathe they realized I needed a child-size tube.”

Mayara: “When I had my NG tube, I used to suck on ice chips/cubes to help ease my sore throat.”

Claire says she’s been through the wringer with NG tubes. There was a point where she had 10 in one year!

She says, “Regardless of how awful NG tubes are and the damage (long or short term) they can do, they have saved my life repeatedly. I am no stranger to bowel obstructions. Developing strictures seemed to be a favorite past time for my small intestines. The NG tube is supposed to decompress the obstruction and stop or at least reduce the amount of vomiting (also helps to prevent aspiration). I will never forget how nervous I was before my first NG placement and even now as an NG vet, I still get very nervous. I always ask the doctor for IV Ativan or IV Valium beforehand.

Claire also says even if a doctor does not want to give a benzo after an opiate that they will usually give her a dose right before placement.

“Don’t be afraid to ask for what you need. I also won’t sugarcoat it; you will most likely gag and vomit during the placement. Ask for an emesis bag or basin. It sounds counterintuitive, but if the nurse doing the placement is experienced, they will be able to utilize you gagging/vomiting to get the tube in faster. Nosebleeds are also very common.”

After NG Placement: Getting Comfortable

  • Secure the tube well: Do not be shy about asking for gentler tape, extra adhesive, or adjustments. A well-secured tube is less irritating and less likely to tug.
  • Soothe nasal irritation: Saline spray, warm compresses, or a tiny amount of water-based lubricant around the nostril can reduce soreness in the first day.
  • Experiment with sleeping positions: Many find sleeping slightly elevated or on their back with a supportive neck pillow helps keep the tube comfortable.
  • Be comfortable: Wear loose tops, zip-up hoodies, or scarves if you want to conceal the tube and prevent snagging on straps or bags. Obviously, many people are choose to stay in their hospital gown.
  • Protect it in the shower: A bit of cling wrap or a small waterproof dressing keeps the tape from falling off.
  • Move with intention: Sharp head turns or bending forward quickly can tug the tube and cause discomfort. Slow and steady helps.

Support for Caregivers: What Helps Most

As a caregiver, it can be easy to feel helpless on the sidelines as you watch your child or a loved one or friend go through this. Here is how you can help ease that burden:

  • Watch for tension or kinks: If the tube starts pulling, the patient may feel nausea or pressure.
  • Track symptoms: Be mindful of any changes you may notice with coughing, reflux, or fullness. This can mean the tube has shifted.
  • Learn how to flush the tube: If this is a long-term situation, educate yourself so you can help prevent blockage and avoid urgent care visits.
  • Offer emotional space, not pressure: Let your loved one set the tone. Everyone is different. Some want distraction, others want quiet, some want humor. Follow their lead. You know them best, trust that instinct and know that even if they may seem frustrated or short, that anger is not geared towards you, but rather the difficult circumstance and situation they are enduring.

The Emotional Side: What We Don’t Talk About Enough

Having an NG tube can stir up fear, embarrassment, frustration, sadness, or anger. All these feelings are normal.

Many patients say:

  • They feel “less like themselves.”
  • They are worried about how they look.
  • They are afraid to sleep.
  • They are overwhelmed by the sensation of the tube at first.

These feelings tend to ease within 24–48 hours as the body adjusts. Give yourself grace. This is a medical tool, not a reflection of strength, identity, or dignity. It is ok to feel all the feelings.

Celebrate the small wins

Take this one like you do with all things IBD. Give yourself credit where credit is due! It is not easy and it is important to celebrate all the wins, no matter how “small” they may seem. You are making strides and growing through this journey, whether you realize it or not. What you are experiencing matters and your resiliency deserves celebrating!

  • The first time you swallow without noticing the tube
  • Sleeping through the night
  • Getting out of bed more comfortably
  • Tolerating feeds or feeling abdominal relief

When to Call Your Care Team

You may wonder what is “normal” and what deserves pushing the nurses light or alerting your care team. You should reach out immediately if any of the following happen:

  • You have trouble breathing or persistent coughing
  • The tube appears to be slipping out
  • There’s significant nasal bleeding
  • You feel intense nausea or vomiting
  • The tube becomes clogged and flushing does not help

You should never hesitate to call. NG tubes are temporary but important, your team expects questions. Classic example of better safe than sorry. You are not a burden to anyone.

Final Thoughts

An NG tube can feel intimidating, and while extremely unpleasant, they can help give you some relief while allowing your doctor to keep finding answers for you. With preparation, the right coping strategies, and the support of a caregiver or medical team, you can make the experience more manageable. Always remember you are never alone in your fears and setbacks and that your ability to cope and your voice matters.

Additional Resources:

Tricks of the Trade: Making NG Tube Placement Less Horrendous // ACEP

The Role of Enteral Nutrition in Patients with Inflammatory Bowel Disease: Current Aspects – PMC

NG Tubes for IBD: Video and Tips for Swallowing

Nutritional Support Therapy | Crohn’s & Colitis Foundation

Tube Feeding | My Experience with a Nasogastric Tube for Crohn’s Disease | Let’s Talk IBD

A Quasi-Experimental Study on the Impact of a Nasogastric Tube Placement Educational Program on Pediatric Nurses’ Knowledge and Practices – Shimmaa Mansour Moustafa Mohammed, Gihan Mohamed, Raghad Almushawah, 2025

When Science Meets Story: The Patient Voice in the Global Consensus on IBD and Pregnancy

It is an exciting and transformative time for the IBD community when it comes to family planning and pregnancy. For years, patients and providers faced uncertainty and conflicting guidance about everything from fertility to medication safety. Now, with the publication of the Global Consensus on IBD and Pregnancy, we finally have a unified, evidence-based roadmap created by leading experts worldwide.

This groundbreaking research, jointly published across multiple top journals, is more than just a collection of data—it’s a lifeline for patients, caregivers, and clinicians seeking clarity and confidence. And for the first time, that guidance comes to life through a series of 12 videos now available online. As the sole U.S. Patient Ambassador and Group Lead for patient advocates worldwide, I was honored to contribute not only to this historic project, but also to share my own journey in the video series—bringing the patient perspective directly into the global conversation.

Grateful for Dr. Uma Mahadevan and the entire team for their incredible work on the Global Consensus.

Check out the video series

Following the release of the research from the 2025 Global Consensus Conference on IBD, a series of 12 videos were also published on the PIANO (Pregnancy in IBD and Neonatal Outcomes website), featuring experts speaking on best practices, emerging data, and consensus statements.

Among those 12, my Patient Perspective video is unique. It’s the only video in the lineup where you hear firsthand experience from an IBD mom. During my unscripted 18-minute video, I share openly about the tough decisions I faced personally, the hopes and worries I encountered while bringing babies into this world, and what I want fellow patients and doctors to know. As an IBD mom of three kids (now ages 8, 6, and 4) who were all exposed in utero to Humira, I have a unique perspective to share.

I know what it’s like when you’re 32 weeks pregnant and have to do a biologic injection while you see your baby’s foot kicking at your belly. I know how stressful it is when you don’t know if you’re going to flare while pregnant or shortly thereafter. I know how complicated and overwhelming it can feel when you’re juggling a chronic illness along with pregnancy and motherhood.

Having a patient video placed alongside expert commentaries is a statement: our lived experience is essential to understanding how guidelines work in the real world. I hope my words leave you feeling seen and empowered.

The 12 published videos cover the following topics:

  • Adverse Outcomes of Pregnancy in IBD
  • Fertility and IBD
  • Fetal and Neonatal Adverse Events in IBD
  • IBD Medications During Pregnancy
  • IBD Medications During Breastfeeding
  • Immunizations for Infants of Mothers with IBD
  • IBD Medication During Breastfeeding
  • Key Findings and Recommendations
  • Management of IBD During Pregnancy
  • Maternal Factors in IBD
  • Preconception Counseling and Contraception for Patients with IBD
  • The Patient Perspective

Why These Videos Matter

Each video is a piece of a bigger puzzle. Together they tell a story about where we are now, where we need to go, and how patients can be—and must be—central to that journey.

Bridging gaps between patient, clinician, and researcher. These videos are designed not just for patients, but for caregivers, physicians, policy makers, and anyone interested in improving IBD care. Seeing things through the patient lens can spark better communication, more empathic care, and guidelines that address what matters most.

Empowerment through shared experience. Whether it’s coping with symptoms, navigating treatment decisions, or facing uncertainty, this research will make you feel more confident in every decision you make along the way. Rather than feeling like there’s an overwhelming amount of gray area, you can see the roadmap of decision-making created from the Consensus that will help you each step of the way.

How to Watch & What To Do Next

  1. Watch the videos: Listen firsthand and educate yourself. An educated patient is an empowered patient. It’s one thing to read a published medical study, it’s especially helpful to see these videos and watch the research come to life.
  2. Join the conversation: Use these videos as conversation starters, take what you learned into clinic visits, have conversations with your partner/family/friends, or on social media. When you’re talking about family planning, make sure your GI and Maternal Fetal Medicine doctors are aware of the Global Consensus on IBD and Pregnancy to ensure they are up-to-date on the very latest research.
  3. Join the PIANO study. This is a great way to become a citizen scientist and use your journey to motherhood as a way to pave the way for others. I participated in PIANO with my youngest child, and he will continue to be “followed” until age 18. It does my heart good to know we’re helping bridge the gaps in understanding so women with IBD now and in the future can feel more comfortable about staying on medication in pregnancy and during breastfeeding.

Too often, patient voices are an afterthought or an add-on. Being featured as an integral voice, not a sidebar, is a powerful shift. The fact the Global Consensus Conference team made such a point to incorporate patients like myself who are IBD moms, from around the world, goes to show just how inclusive and comprehensive this research is.

Final Thoughts

Living with IBD means navigating uncertainty, physical challenges, and emotional strength, but it also means being part of a community that continues to push boundaries in care. These videos highlight not only the science and data, but the lived realities that bring those numbers to life. Patient voices don’t just complement medical expertise, they help shape the future of care. By placing my perspective alongside global experts, the Consensus reminds us that guidelines are most powerful when they reflect both evidence and experience.

As an IBD mom, I think about what this progress means for my three children and for the next generation of families impacted by this disease. I volunteer my time and energy for these projects because they are at the heart of my patient advocacy and genuinely matter so much to me. The inclusion of patient voices today paves the way for a future where no one feels alone in their decisions about pregnancy and IBD. Together—patients, clinicians, and researchers are building a roadmap that will make the journey clearer, safer, and more hopeful for those who come after us.

Managing ADHD Medications with Crohn’s and Colitis: What Patients Want You to Know

Living with Inflammatory Bowel Disease (IBD) often means juggling more than one health condition. For some, that includes managing Attention-Deficit/Hyperactivity Disorder (ADHD). Both conditions can significantly impact daily life, and when it comes to treatment, it’s important to understand how ADHD medications may interact with IBD and its therapies. This week on Lights, Camera, Crohn’s we hear from more than 25 people who are juggling both and share their impactful advice.

The Overlap Between ADHD and IBD

While ADHD and IBD are separate conditions, research shows that people with chronic illnesses, especially those that begin in childhood or young adulthood may experience higher rates of ADHD or ADHD-like symptoms. Brain fog, fatigue, and difficulty concentrating are also common in IBD, which can make it challenging to distinguish what’s driving certain symptoms.

For those diagnosed with both conditions, ADHD medications can be life-changing, improving focus, energy, and daily functioning. But because IBD involves a sensitive gastrointestinal (GI) system, it’s important to weigh the potential effects ADHD medications can have on digestion and disease activity.

Common ADHD Medications and GI Considerations

Stimulant Medications (Adderall, Ritalin, Vyvanse, Concerta)

  • Appetite suppression: Stimulants often decrease appetite, which may be concerning for IBD patients who already struggle to maintain weight or adequate nutrition.
  • GI side effects: Nausea, abdominal pain, and diarrhea can occur, sometimes making it difficult to know whether a flare or medication side effect is to blame.
  • Sleep disruption: Poor sleep can worsen IBD symptoms and overall inflammation. Timing doses earlier in the day can help.

Non-Stimulant Medications (Strattera, Qelbree, Intuniv, Kapvay)

  • Slower onset: These may be less likely to cause GI upset but can take weeks to become effective.
  • Potential side effects: Constipation, abdominal pain, and fatigue are possible, which can overlap with IBD symptoms.

Impact on Gut Motility

Both stimulant and non-stimulant ADHD medications can influence gut motility (how fast or slow food moves through the digestive tract). For those with Crohn’s or ulcerative colitis, this may complicate symptom management, particularly if diarrhea or constipation is already a challenge.

Key Considerations for Patients with IBD

  1. Collaborative Care is Essential
    Make sure your gastroenterologist and psychiatrist (or prescribing physician) are aware of all your medications. This helps prevent drug interactions, especially if you’re on biologics, immunosuppressants, or steroids.
  2. Monitor Nutritional Status
    If stimulants suppress appetite, work with a dietitian to find calorie-dense, IBD-friendly foods and snacks that can help you maintain strength and body weight.
  3. Track Symptoms Carefully
    Keep a journal noting when you take your ADHD medication, what you eat, and how your GI symptoms present. This can help differentiate between medication side effects and IBD flare activity.
  4. Adjusting Doses and Timing
    Sometimes, smaller, or extended-release doses can reduce side effects. Timing medication with meals or adjusting when you take it can also ease GI discomfort.
  5. Mental Health Matters
    ADHD itself can heighten stress and anxiety, which are known triggers for IBD flares. Finding a treatment balance that supports both brain and gut health is critical for overall well-being.

An IBD mom and therapist shares her advice

Sammi is an IBD mom who works as a therapist. In her experience, both personally and professionally, she has valuable input to share about taking ADHD medications when you have Crohn’s or UC. Sammi took a low dose of Adderall (5 mg, sometimes 10 mg) in graduate school for her anxiety and ADHD.

“My appetite was extremely impacted I’m sad to say. I did not feel hungry until my stomach was physically giving me intense hunger cues. I was only a couple of months into Humira at that point so I too, was struggling with maintaining my weight and didn’t want that to be impacted.”

Here are a few things Sammi did to make it manageable:

1. ALWAYS eat before you take ADHD medications. Eat a big breakfast, if possible, protein and carbs (if you can tolerate generally, of course). As a therapist, many of my clients struggle with taking meds early enough at times. And inferring a good meal ahead of time can feel like a barrier so I just want to hold space for that. However, it is so imperative to be really fueled and in a good place stomach wise / eating wise before taking for the day.

2. Plan your meals out as much as possible. Since hunger cues were lessened for me, I was in the mood for nothing. So  it would be hard to decide what I was going to eat, and then I would not have to decide when I was feeling fatigued and overwhelmed.

3. Snacks are clutch. I say snacks because sometimes that’s just the easiest thing to eat, especially when you don’t want to think about food or you’re not actively thinking about food because your appetite is suppressed. I have Crohn’s disease and one of my biggest triggers is my stomach getting too empty whether it’s because I’ve waited too long to eat or I haven’t eaten enough that day. It will give me such a bad stomachache so that was happening to me pretty frequently when I first started taking the Adderall.

4. Take your ADHD medicines early in the day. This is my BIGGEST piece of advice and clinical recommendation for anyone who is considering taking ADHD medication. Take it early in the day so your sleep isn’t impacted. As we know with IBD- sleep can already be difficult this is so important!

More from the patient community

“My advice is to take it early in the morning so that you can eat more in the afternoon and evening. I don’t have a problem with dropping weight; I had the problem of retaining! Transparently, now I’m on GLP-1 (GI approved) medication, and I’ve lost 38 pounds. Best I’ve ever felt! But, when I take my Adderall too late in the day, I don’t eat and that’s not good either. I take my ADHD meds twice a day, as prescribed. Once at 7 am and once around noon.”

“I have IBD, and I currently take Adderall for my ADHD. I have been on it for a few months, and in my experience, my biggest issue is that it suppresses your appetite for quite some time. I’ve been struggling to gain weight for awhile due to my IBD, so taking something that makes it hard for me to eat all day has been a big challenge. I am thinking about asking my doctor to switch me to a new treatment plan to hopefully find something that doesn’t suppress my appetite!”

“I feel like it never affected me very much with eating and I don’t think there was any interactions between anything with ADHD meds and my UC!”

“I’ve heard fellow moms with kids on these medications recommend eating a big breakfast before ADHD meds kick in, having a snacky lunch, and a late dinner after they wane.”

“There are non-stimulant ADHD meds. Stimulants are the ones that suppress appetite. You can ask your doctor about these and ask to start on the very lowest possible effective dose, if stimulants are required.”

“I don’t take ADHD medications now, but in college I did. I did not find it impacted anything with my Crohn’s. Depending on the ADHD med, it could impact appetite but didn’t interfere with how I manage my IBD.”

“I’m on mental health meds for anxiety and depression, along with ADHD meds, and I do think I’ve had a slight decrease in appetite. I also naturally have a lower appetite than most. A family friend of mine has been on Ritalin for longer than me, and I think he has struggled more in that aspect than I have though.”

“I have a j-pouch with a post-pouch diagnosis of Crohn’s, and I take Vyvanse for ADHD. I take 30 mg a day, I don’t feel like it impacts my appetite at all.”

“I take stimulants for my ADHD, and I don’t have any decrease in appetite. It just depends on the person.”

“The best advice is eating a big breakfast, having snacks for lunch, and then eating a big dinner. I have also reached out to my Crohn’s dietitian  to have more creative ideas for small meal ideas! The issue with choosing what medicines is that they all aren’t covered immediately—I’m starting on Adderall, which is one of the suppressants—my doctor doesn’t plan to keep me on that long term, but due to insurance, I have to start there. I have also have to find out what exactly is covered and is not covered (as IBD patients we’ve been there before, right!?)”

“I have Crohn’s and just started to take Vyvanse about two months ago. Even on a low dose, while also being on a high dose of prednisone, I’ve had little appetite. It has helped me to eat something small as soon as I’m able in the morning, before taking the medicine. It helps me have more of an appetite throughout the day, though I have smaller meals now.”

“I have Crohn’s and ADHD. I take an extended release 10 mg Adderall and find that my appetite is fine, a little less, but not dramatically so. I hadn’t really thought about it until my GI went through my meds. I have found that if I take 20 mg (we played around with the dose to find which works best), I do experience a loss of appetite. I think if you can find the therapeutic dose, it should be ok! I’m just a case study of one, but I would also add that ADHD meds have the benefit of supporting healthier time management skills, so I’m more inclined to stop and eat, which my scattered self sometimes didn’t do.”

“I don’t take my ADHD meds every day, but I take Vyvanse and when I do take it, I notice appetite suppression, but it’s nothing severe. I don’t have a j-pouch or struggle with being underweight. When I take them, I usually notice mid-day appetite suppression the most. I tend to eat breakfast before it’s fully kicked in and the effects have waned by dinner time.”

“I have been on Vyvanse, and it has been the best on my stomach and ADHD. I was diagnosed early this year. I tried Adderall, and it made me anxious and over stimulated. Concerta had me nauseated all day, everyday…Vyvanse is the way to go!”

“I have been on Ritalin for the last 2.5 years (finally) and even started an anxiety med that also helps with my chronic pain.”

“I’m on 10 mg of Focalin for ADHD and on Imuran (max dose), Entyvio infusions, and other meds for anxiety and depression. I never had a big appetite regularly, so I haven’t noticed a big difference. The benefit for me has been that I am calmer now and don’t get that ADHD stress. I’m 45 and was just diagnosed with ADHD last November. I’ve had Crohn’s since age 14 with many surgeries between then and 2022.”

“I have IBD and take ADHD meds. I never had the lack of appetite side effect, so I might be an outlier. I usually eat breakfast before taking my pills. Sometimes I need to set timers to eat though if I’m hyperfocusing.”

“I recommend keeping snacks in view. If you don’t feel like eating, drink a protein shake. My Crohn’s symptoms improved a bit with ADHD meds, too.”

“I can’t speak to the loss of appetite, but I was diagnosed with ADHD a few months ago. I tried Adderall for three days, but each day it upset my gut. I had way more bowel movements than normal, even though I was not flaring, and my gut was sore after each one. So, I stopped taking the Adderall and everything went back to normal. I’ve just been self-medicating with caffeine ever since.”

“It helps to eat when you take your ADHD meds and then eat smaller meals throughout the day. It’ll make you not thirsty, so make sure you’re mindful about hydrating. I recommend taking little breaks from it, during weekends and things.”

“I just started my ADHD medications again post-baby and have noticed a huge drop in appetite. I tried a few different meds before settling on extended-release Ritalin. I will say immediate release Adderall severely exacerbated my Crohn’s and gave me horrible stomach cramps. The stomach cramp thing is common with that one, even if you don’t have IBD.”

“I stopped my ADHD medication. It absolutely  destroyed my belly. They are a stimulant and make you go to the bathroom more an also affect blood flow to the colon. It’s been awful.”

“Personally, it’s never been enough to make me lose weight. But I do tend to front load—eat my biggest meal in the morning. Also, the come down from stimulants will have you ravenous by the end of the day.”

Finding the Right Balance

Every person’s IBD and ADHD journey looks different. What works well for one person may not for another. The key is to be proactive, keep your healthcare team in the loop, and advocate for adjustments when needed.

Managing IBD is already a full-time job. Adding ADHD into the mix can feel overwhelming, but with the right treatment plan, many people find that their ADHD medications not only improve focus but also help them feel more in control of their health overall.

Additional Resources

Risk of Anxiety, Depression, and Attention-Deficit/Hyperactivity Disorder in Pediatric Patients With Inflammatory Bowel Disease: A Population-Based Cohort Study – PubMed

Association between attention-deficit/hyperactivity disorders and intestinal disorders: A systematic review and Meta-analysis | Scientific Reports

Gut dysbiosis as a driver of neuroinflammation in attention-deficit/hyperactivity disorder: A review of current evidence – ScienceDirect

Is There a Link Between Adderall and Ulcerative Colitis or Crohn’s Flares? | MyCrohnsAndColitisTeam

ADHD and Bowel Issues: Finding ReliefWhen ADHD Meets IBD: A Complicated Relationship – Girls With Guts

Colonoscopy Prep Hacks You’ll Actually Want to Try: Tips from the IBD Community

Whether you’ve experienced one colonoscopy or 20, you know the process is far from enjoyable. This past week while scrolling through Instagram I came across a story an IBD caregiver posted as her young daughter prepped for her scope. During the video she explained how her husband rolls dice, and whatever number it lands on is how many sips their daughter has to take of prep. I was amazed at this brilliant trick to ease the struggle of getting the prep down, and it inspired me to dig a little deeper and ask the IBD community what their “tips and tricks” are.

This week on Lights, Camera, Crohn’s read firsthand advice from caregivers and patients of all ages. My hope is that you find comfort and maybe even a new idea or two to make your next prep a little less stressful.

Firsthand advice for pediatric IBD caregivers

Mara’s daughter has IBD and has already been through eight colonoscopies in just five years. She says the dice game was a huge success for their family the first time around:

“She was at the perfect age for a little competition as motivation with a reward at the end for the winner…of course she always won. It was honestly so easy to prep her I was shocked.”

However, being NPO (derived from the Latin saying ‘nil per os’ or nothing by mouth/no food or drink) after midnight was NOT easy.

“There were lots of tears and anger directed at us. We bought her a special blanket and stuffed animal, which helped diffuse some of that anger.”

As many caregivers know, every prep is different. Mara recalls their second scope being much more difficult, requiring hospitalization and an NG tube after her daughter couldn’t keep the prep down. Now, they focus on giving their daughter as much autonomy as possible, letting her choose flavors, snacks, and activities.

“On prep days or days, she must be NPO, dad and I also follow that diet. It gives her a sense of belonging and that we are struggling right alongside her. We’ve done it for all eight scopes, and we will continue to do it if she needs us to.”

Over time, Mara says they let their daughter lead as much as they can. They give her a “yes” day.

“Whatever she wants (within reason) to eat or drink. Gummy bears, sure. Popsicles, sure. Want to try to mix three different Gatorades? Why not? She wants to watch TV while she preps or play hockey, absolutely.”

Emily’s Family
Emily has three daughters with IBD (now ages 9, 12, and 15) who’ve been doing preps for over a decade. Their youngest had to prep for a scope when she was only 21 months old. Their top tips include:

  • Only prepare 8oz of the drinking mixture at a time. With MiraLAX prep, we let them pick a new flavor to mix each 8oz.
  • Think outside the box with the liquids for MiraLAX! One preferred water once! (With other electrolyte drinks that day.) One daughter does her whole prep with tea and chicken broth. (Add MiraLAX after the liquid is warmed.)
  • Use distraction!! This is our biggest piece of advice. We surprise the girls with a new activity the day of prep. They know there will be something fun to do – just not what it is. We have gotten Lego sets, multi-step craft projects, etc. We pick something that we can partition up and give them one part at a time in celebration for ounces drunk!
  • Keep them active. We have found that the girls tolerate the large amounts of liquids better if they get up and get moving! In the warmer months, they go walk laps around the driveway between cups of the prep.
  • Pick the “fun” liquids together ahead of prep day. Since they normally cannot have juice or soda, they pick out a few drinks that they are excited to have. This helps them to drink more, once the MiraLAX prep is complete.
  •  I set timers for myself for the day of prep for every 10 mins or so. Just to check in on their drinking. It’s easy to lose track of time and accidentally go 30 mins (or more!) without drinking.
  • Pack a bag of supplies for the scope day. We always take extra clothes and baby wipes for any accidents. Games/books/crafts are great to keep the girls distracted during the wait before their procedure time. We take some water/light snacks for afterwards. (Check with your providers to see what/when your child can eat afterwards.) Chapstick is always requested by mine now too.
  • Remember that you can speak up and (nicely!) ask for what your child needs to make them comfortable. For example, at our hospital, the kids usually get their IV’s after they are sedated with some gases through their breathing mask. This is great to avoid needle anxiety for many kids. However, mine have taken a dislike to the masks and the smell of the gas. Since they get regular med infusions, they prefer to get their IV’s back in the holding area and then use the IV for their sedation to sleep. While not the normal procedure, the anesthesiologists and nurses have kindly worked with us to do it the way my kids prefer.

Cindy’s Perspective
Cindy, mom to a teenage daughter with Crohn’s disease, says scheduling scopes early in the day is key. Even if you have a teen who likes to sleep in, sleeping in is worth nothing if you already feel like crud due to the prep. She emphasizes advocating during IV placement and following your gut as a caregiver:

“A parent’s intuition of how much is too much comes into play, and you’ve got to listen to that voice. Tell the nurse you (parent and child) did your best to complete as much of the prep as possible. If you can’t finish it to a T, they can still make it work. They know they are working with a child. If they are having trouble placing an IV, advocate for your kid. Give them two tries and then request another person to try. We’re still traumatized from watching them work for 10 minutes to get an IV into my dehydrated and scared 9-year-old, and I think that trauma will live with us both forever.”

She also believes in being honest with your child without over-preparing. Start the conversations when it’s time, but don’t talk about it for days or even hours beforehand.

“This is not going to be fun, and it won’t feel good. But I know you can do it and we are going to do it together because I will be beside you every step of the way. Here are the steps we will take and outline them in age-appropriate detail. Let’s think about how amazing this is going to be once it’s done! This is our focus for the next 24 hours… that moment when it’s done… that will be the best! As soon as you are done at XYZ time tomorrow, we can celebrate and go back to normal life, and you can eat whatever you want.”

Additional feedback for pediatric patients

“For pediatric prep, popsicles are necessary. Blue popsicles allow kids to “poop blue,” which many like. The Gatorade with the MiraLAX is the easiest for them to get down. We tried magnesium citrate once and it was a disaster. Gatorade is where it’s at. Also, we make it a party. Popsicle party. Jokes and TV while pooping. Anything to keep the mood light.”

“Turn the ordeal into a scavenger hunt by completing parts of the prep with small stickers to earn up to something whether it be completing a picture or something to distract when prep is working.”

“My daughter’s first prep at home didn’t go well, but prep while in-patient thru NG tube really worked.”

“If the hospital or your GI team has a Child Life specialist, they can send prep books to families ahead of time so they can help prepare kids for what to expect the day of the procedure.”

“Bribes! Lots of bribes! New toys or games. Legos keep little ones busy. Family doesn’t eat in front of them. Lots of snuggles. Clear your schedule to spend time with them. For young kids, put all food out of reach or lock the pantry so a hungry little one doesn’t get into something they can’t have and make you have to cancel the procedure, which is always my fear!”

“I have a prep approved Starbucks order—Mango Dragonfruit refresher, Venti, no ice, no Dragonfruit fruit inclusions, peach juice blend, in my personal cup … I like to line up cups so I can visually see how much is left and removing one feels like an accomplishment. A seasonal suggestion is using an advent calendar and dividing prep by 24 and opening one door after each one…just make sure the prizes are not food!”

“Arts and craft activities and projects can be a good distraction. Recently gave a sensory art bin to a VEO-IBD patient through their first scope as a kid it helped me to have new things to do.”

“My mom fasted with me when I was doing the prep as a kid! My tips now as a mom myself are to make Jello without Red 40. Ramen seasoning dissolved in water tasted way better than broth to me as a kid…I know that’s not good for you. I would make it a fun and relaxing day, so your kiddo is distracted. I would recommend not watching TV or YouTube because there are so many advertisements for food everywhere and it didn’t help distract me much. I advise having a movie marathon instead!”

“We didn’t eat out much when I was a kid, so eating out with my parents only was a big treat for me to look forward to after starving the day before! Back in the day, GIs used to do a combination of drinkable prep and suppositories for pediatric patients, and I’m glad my mom did the suppositories for me because it was not something else you had to drink. Ask pediatric GIs about low consumption prep so your child doesn’t throw up.”

“When I was a pediatric patient, my mom took me to the store to pick out different drinks for the mix, Jello flavors, etc.… which would make it fun picking it out myself and this also gave me a sense of control in a very out my control situation. My mom always fasted with me, which I appreciated not feeling alone in it. I was also able to pick the restaurant to go to after for something to look forward to!”

“Have your child drink their prep in a fun container., a Disney theme with a silly straw. For adults, use a wine glass or fun mug. Cheers!”

“My 12-year-old just had their first colonoscopy. As a Crohn’s patient myself, I have done one every other year for 25 years and it was hard to watch him go through it. He was tougher than me. The hardest part was him not eating! He had to do a full two days of clears only—per our doctor’s recommendation. That’s my hack as an adult, too. I start taking a Dulcolax dose and not eating a day or two earlier than recommended. You only have to drink the drink until it’s clear in the toilet. The milder/longer prep is easier on me and saves me drinking half the magnesium citrate drink.”

“My daughter couldn’t get any of the prep down at age 16 and by this summer, at age 19, she felt ready. This time we tried over the counter prep of MiraLAX and Dulcolax. The doctor said if she did it this way, she would need to fast for 48 hours instead of 24. She was fine with that. She started taking a couple of Dulcolax tablets at 5 pm the night before. Then, we put half a bottle of MiraLAX into Sprite. She drank a cup every 10 minutes until it was gone. We did the same thing a few hours later. She was clear before going to bed at night. It was easy and stress-free for her.”

“My parents would set me up with my iPad for movies, a desk chair, and a blanket in the bathroom so I could go back and forth from the toilet easier.”

“Make MiraLAX with white grape juice instead of Gatorade! Drink with a fun straw so you can put it on the back of your tongue and taste less. Put on headphones with loud music to distract your sense from the taste so you can drink the prep faster.”

“I confirmed with my child’s GI that colorless cotton candy is a clear liquid! Obviously in moderation, but this could be super helpful for kids and adults who need a different texture than liquid or gelatin.”

Prep Hacks for Adult Patients

Our IBD family had plenty of creative hacks for adults, too:

“The MiraLAX + Dulcolax prep hands down!! I’ve tried them all, and it’s tasteless and easiest.”

“Lemonheads or lemon jolly ranchers RIGHT after you get done drinking a dose!”

“Gummy bears and lifesavers! I love having stuff to chew. I also had pickle juice shooters, which gave me some salty/sour taste to balance all the sweet stuff. I also keep my schedule open for the remainder of the day and allow myself to relax.”

“I put my Suprep in the fridge (even though it says not to) and it makes it SUBSTANTIALLY easier to drink (and doesn’t seem to make it less effective in any way). I also buy myself a new book to read or save a special TV show episode, so I have something to look forward to when I’m drinking prep at 2 in the morning. Colonoscopies are miserable and until they figure out how to make them a nicer experience, it’s great to team together to gather the best tips.”

“Clear Gummy Bears!! This keeps it fun for all ages! Here’s a recipe!

“Drinking chicken broth throughout the day. This gives energy and takes away the bad taste of the prep drink. As a kid, my sister used to make a colonoscopy prep kit. Every 8 oz. I drank; there would be a little gift or activity to do. For example, after the first 8 oz., I got a nice bottle to drink the rest from. The next thing was a Lego kit or a paint by number.”

“I begin my prep four hours ahead of their suggested time, so I can sleep through the entire night. Getting up in the middle of the night, especially for children to complete round two of the prep is just borderline inhumane. What a nightmare. The catch is waking up and hydrating with enough water before the anesthesia cut-off which requires not to drink anything 2 hours before the procedure.”

“Wet wipes and diaper cream are super helpful!”

“A lot more MiraLAX than the prescription prep. And gummy bears (except red ones) are a gamechanger. They let you feel like you’re eating, but they liquify in your gut.”

“Rotate flavors and get some protein through broths. Have broth, then 2 hours later do Jello or change the texture and taste, then 2 hours later do broth and rotate.”

“Strain chicken noodle soup to just have the clear broth, it has more sodium.”

“Avoid eating vegetables/fruits/seeds three days before. Taking preps that you can take with a glass of water and then drink two liters of tea or water.”

“My son, Andrew, has autism and Crohn’s disease. When he has to do colonoscopy prep, he likes to listen to Disney music and use a timer. Andrew is almost 30 years old and has been having to do colonoscopies since he was 17. This past year, for the first time, he did the pill prep and loved it. He used a timer to tell him when to take the next pill. Andrew told me he will never go back to liquid prep. Pill prep was so much easier for him, especially with his sensory issues.”

“Take notes on all preps you’ve been assigned and take notes and photos of what it felt like. I found one that was less painful for me, and I always request it. I also alternate sips out of a straw with apple juice. I drink the prep in my kitchen, near a bathroom, and watch TikTok’s while drinking to distract myself.”

“I only eat soft foods 2-3 days before, make sure to hydrate, and follow the instructions they give about not eating things like seeds or nuts a week before.”

“Have a bidet and diaper cream ready.”

“Desitin, Gatorade that is the Frost Glacier Cherry flavor (not red) frozen or really cold to help me stay hydrated.”

“Make freezer pops out of the Gatorade prep mix.”

“For me—finding fun drinks, whether a tea at Starbucks or stocking up at the grocery store, really makes it feel less horrible. I started this as a teenager. I make a list of movies or shows I want to binge. If you’re comfortable with it, have a friend there to distract you—at 15 years old, my boyfriend stayed with me all day for my surgery prep which was the same as a colonoscopy and we watched movies and he distracted me/made me laugh and at times I forgot what was going on!.”

“Savory liquids to balance out the sweet!”

“Mix the prep with Crystal Light Lemonade—instead of the lemon mix the pharmacy provides. Drink the prep through a straw and suck on hard candy (e.g., Werther’s Originals) in between doses to get rid of the taste and have something to look forward to.”

“Take SUTAB (pill prep) and Zofran and then fall asleep. Your bowels will wake you up and you’ll avoid the nausea but start the pooping process. I do the same for the morning dose! If you vomit, at this point it’s fine, just hopefully after the nap and pills are digested!”

“Gummy bears/worms!”

“Pill prep has been a gamechanger for me!”

“Extending the clear liquid diet an extra half day or full day helps a ton with prep.”

“You have to have a movie downloaded on a device that you can have in the bathroom and a pillow for the toilet seat for your back. I’m a fan of disposable diapers because after the first several poopy poops, you get to the drizzle stage and then it’s annoying to have to get up every two seconds towards the end. They also come in handy when you’re sleeping and when you’re traveling to the procedure.

“Before I have a colonoscopy I write down positive affirmations and thoughts and there is like a Table of Contents that’s like “When you’re sad” or “When you need a good laugh” and it really helps me though the ups and downs, although it may sound silly. I choose what to drink and I always have my good luck drink which is blue Gatorade.”

“Use nuun electrolyte drink instead of Gatorade!”

“My personal hacks are to follow what you know works for you. I followed the timings of when to take what from the last instructions and it wasn’t the cleanest prep. I should have listened to my gut and started doing that earlier. I resort to drinking Ensure Plus instead of just relying on broth and soft foods to keep me feeling full. It’s helped me SO much. I know not everyone can tolerate it or like it, but when I was on a liquid diet about a year ago for two months, I only had Ensure Plus. I got used to it. It’s now a lifesaver, especially if I’m traveling or on the road and not sure what food I will have access to. It helps to start the diet a bit earlier, so mash and fish instead of just toast and pasta.”

“I mix apple juice with my Suprep! I also always buy bone broth or stock because the protein per cup is higher. I like the Zoup brand because there’s 3 or 4 gram of protein per cup. I also get the College Inn brand bone broth which has up to 10 grams of protein per cup.”

“Gummy bears!! Just not the red or purple ones. Just being able to chew something helps! Progresso Chicken Soup. Use a metal strainer to strain out all the solids and then sip the broth. It’s thicker and has more flavor than regular stock and it’s just more satisfying.”

“Remind yourself “this is only temporary.” Having loved ones supporting also helps to distract a little, which makes it easier to get through. Focusing solely on drinking cup after cup can seem very overwhelming.”

“Start a low residue diet a few days early even before your doc says to. Mix prep with Sprite. Have hard candies or gum to chew on while doing prep. Use a measuring cup or something to lines to indicate how much to drink.”

“I really love the Trader Joes less sugar lemonade mix with water for my prep. I chugged and it was so delicious! Also, ice pops like the good pop brand were yummy.”

“Gummy bears! Making ice cubes out of juice and chewing on the ice.”

“Make sure it’s cold! Drink with a straw, chew Juicy Fruit gym in between drinks, this helps cut the saltiness. Do two-step prep if your practitioner allows it (half the night before and the other half in the morning). Ask if you can use one of the lower volume prep or the MiraLAX and Gatorade prep.”

“For the MiraLAX prep I use two different flavors so I can alternate when I get sick of one.”

“Mix the prep early and put it in the fridge. Have music and TV on to help distract yourself.”

“While most people say to drink it cold, I prefer my prep at room temperature so I can chug it faster.”

“Always lots of ice and drinking thru a straw. Big gulps. Have a station in the bathroom with a laptop streaming Netflix. I also got a Bidet before my last one!”

“Gummy bears! I buy the Haribo ones and don’t eat the red ones. My favorite prep hack thus far. It’s great getting to chew something when everything else is liquid.”

“Lots of mint tea when the cold chills kick in a few hours before you have to go in for the procedure.”

“Use a Pedialyte jug and ensure it is very cold and drink the prep with a straw. The slower you drink, the worse it is. I always chug it super-fast through a straw and it gives me 10-15 minutes between each cup. Have lots of other drinks that you don’t normally consume to make it fun and have lots of juice, Jello, soda, and popsicles on hand!”

“I’ve turned prep days into self-care days. I binge shows, nap, relax, and try to take care of myself.”

“I like to alternate between sweet/cold beverages and salty/warm soups when I am trying to stay hydrated before starting prep. Sprite/popsicles/lemon ice and then chicken broth.”

“I chase my prep by sucking on approved colored Lifesavers. They truly are a lifesaver for me. I could never do it without them.”

“I recommend the pill prep instead of liquid prep if you’re neurodivergent or have issues with taste and textures. Maybe keep a backup on MiraLAX and Gatorade or juice in case you can’t tolerate the liquid prep. If you know you get nauseated, take prescription anti-nausea medication like Zofran before you begin the prep. I like Squatty Potty and having wipes to dab and pat my skin. A Peri Bottle can be useful. If you’re prone to hemorrhoids or know you have vascular issues like pelvic congestion syndrome, apply hemorrhoid cream in advance. Keep Zinc Oxide handy if it starts to burn or feel raw. Get into comfortable clothes that’s easy to get in and out of in the bathroom. I personally use a heating pad and Bentyl for intestine cramping. I usually make sure I’m scheduled first thing in the morning, and I ask for extra IV fluids.”

The Takeaway

Colonoscopy prep is a universal challenge in the IBD community, whether you’re a child facing your first scope or an adult whose been through dozens. But as the stories above reveal, there are countless ways to make it less daunting through creativity, distraction, teamwork, and sometimes sheer humor.

I personally start a full liquid diet 4-5 days before my scope to ease the actual prep. I make sure I have Zofran on hand to manage my nausea (I always vomit, regardless), and I prefer the SUTAB pill prep. I’ve done multiple preps since being diagnosed with Crohn’s disease in 2005, and my last three preps, SUTAB pills have been the “most tolerable.” While MiraLAX/Dulcolax is popular, I never enjoyed having to drink such a large volume of liquid. Having gummy bears on hand is also a necessity for me! My husband always takes the day off work, and we go out to breakfast and spend the day together afterwards as a reward for all I went through.

If you’re gearing up for a prep, remember you’re not alone. Thousands of IBD patients and caregivers are walking this same path and learning tricks along the way. Find what works for you (or your child), advocate for needs, and give yourself grace. And once it’s done? Celebrate that victory meal and the relief of getting through another milestone in your IBD journey.

A Rare Case, A Powerful Message: One IBD Mom’s Battle with Vitamin K Deficiency During Pregnancy

When you live with Inflammatory Bowel Disease (IBD), you become an expert in knowing life can throw you curveballs at any given moment. Those curveballs are especially worrisome and scary during pregnancy and after you become a mom.

For one IBD mom who wishes to remain anonymous, that curveball came in the form of a rare and dangerous vitamin K deficiency that caused life-threatening complications for both her and her newborn son after delivery. Now, two years later, a published medical case study based on their experience is helping raise awareness of this rare issue, offering hope that future pregnancies in the IBD community might benefit from earlier detection and intervention.

Diagnosed Young, Navigating the Unknown

This mom was diagnosed with Crohn’s disease at age 13, and now at 34, she’s lived with IBD for more than 20 years. Her journey has included numerous medications, including a long stretch on Humira, which she remained on during her pregnancy, and four partial small bowel resections. She’s also undergone several exams under anesthesia due to complications like abscesses and fistulas.

Thankfully, during her pregnancy, her Crohn’s was well-controlled with no active disease, making the post-delivery complications much more shocking.

A Sudden Turn After Delivery

After giving birth to her son (we’ll call him “B”), what should have been a joyful moment quickly turned traumatic.

She spent 16 days in the hospital, including three in the ICU, while her newborn faced a 23-day NICU stay. The cause? A severe, undiagnosed vitamin K deficiency, which led to hemorrhaging in both mom and baby. The medical team was blindsided—none of them expected this.

Understanding Vitamin K Deficiency & IBD

Let’s get one important thing straight first. This situation is not about skipping the vitamin K shot that newborns typically receive. The mom explains:

“It’s imperative that newborns receive a vitamin K shot after they are born to prevent vitamin K deficiency bleeding. The American Academy of Pediatrics recommends that all newborns receive a single dose of vitamin K, because babies are naturally born with very little in their bodies. In our case, my son did get the shot—but because I was unknowingly severely deficient in vitamin K during pregnancy, his vitamin K levels in utero were dangerously low, leading to a brain hemorrhage before he was even born. The bleeding he experienced was similar to what some babies experience when they don’t receive the shot, but in our case, it happened earlier—and was not caused by withholding care. In fact, he needed far more vitamin K after birth to restore safe blood clotting levels.”

This vital distinction can prevent confusion and reinforce just how important that standard vitamin K shot is for all newborns.

What She Wants Other IBD Moms to Know

“Knowing what I know now,” she says, “I want fellow IBD women to understand a few key things about vitamin K deficiency during pregnancy:”

This is rare. Most pregnant people with IBD will never encounter this issue. “I hope that offers peace of mind. But as we all know, knowledge is power—especially when you live with IBD.”

If you’ve had bowel resections or are deficient in other fat-soluble vitamins (like A, D, or E), consider bringing this case study to your GI and OB/Maternal Fetal Medicine (MFM) doctors. Ask about checking vitamin K levels, as well as PT/INR and PTT, which monitor blood clotting.

You can develop a deficiency during pregnancy even if you’ve never had one before. “Outside of pregnancy, I had no clotting issues. But between my history of resections and my baby’s increasing demand for nutrients, my levels dropped—and no one knew.”

Looking Back: What She Wishes Had Been Done

“If we had been monitoring my vitamin K levels, PT/INR, and PTT throughout my pregnancy, we likely would have seen early warning signs,” she says. “These aren’t standard tests, but I hope someday they will be for IBD moms with similar risk factors.”

A Silver Lining in the Study

Despite the trauma, having their experience turned into a published medical case study brought a sense of closure.

“When they told us they wanted to publish it, I felt incredibly validated. This wasn’t just something we lived through—it’s now out in the world to potentially save lives. That’s the best-case scenario for us.”

The comprehensive care team—consisting of her OB, MFM, GI, hematologist, and PCP—remained closely connected throughout the experience. After both mother and baby were stabilized, Ohio State’s hematology team and Nationwide Children’s Hospital worked together to identify the deficiency as the root cause for both patients.

“They didn’t miss anything—they acted on the knowledge they had at the time, and when things went south, they sprang into action. I’ll always be grateful for that.”

“B” Today: A Story of Resilience

Despite a traumatic start, B is now a thriving, happy, and a miraculously healthy two-year-old.

“We were so worried about long-term impacts due to the hemorrhage in his brain, but he is now meeting and exceeding all his developmental milestones. He doesn’t need any additional support. It’s truly a miracle.”

His early care included close monitoring from neurology and the Early Development Clinic at Nationwide Children’s Hospital, along with early intervention specialists. Today, all those appointments are in the rearview mirror.

What About Future Pregnancies?

The reality is that this situation may recur if she decides to grow her family.

“My doctors believe I’d face similar risks, so we would monitor everything very closely: vitamin K levels, PT/INR, PTT and I’d likely receive IV vitamin K infusions throughout pregnancy to stay ahead of any deficiencies.”

Lifting the Tide for Others

After two decades of managing Crohn’s, she knows how isolating chronic illness can be.

“It’s hard. It’s lonely. It’s easy to feel invisible. But finding others who share their stories and who get it has been a game-changer for me. That’s why I’m sharing this now. Even if this specific challenge never affects you (and I truly hope it doesn’t), I hope you feel a sense of solidarity. A rising tide lifts all ships and if sharing our story lifts someone else’s experience just a little, it’s worth every word.”

If you’d like to contact this IBD Mom don’t hesitate to reach out to me, and I will connect you. It’s stories like this that help to pave the way for future families.

Magnesium Deficiency in IBD Patients and the Role of Natural Support

When you’re living with a chronic illness like Crohn’s disease or ulcerative colitis, it’s easy to become hyper-aware of every medication, every symptom, and every nutrient—or lack thereof. One essential mineral that often flies under the radar is magnesium.

Magnesium supports nerve function, hormone balance and how we respond to stress, so when levels drop, the nervous system can become overly reactive. For those with Inflammatory Bowel Disease (IBD), these symptoms can be even more noticeable because our bodies often struggles to absorb and retain magnesium properly.

According to Hollie King, Founder of Sweet Bee Organics, this humble mineral could be one of the most powerful tools in the IBD toolkit. This week on Lights, Camera, Crohn’s Hollie explains why magnesium matters so much for people in our community.

While I was working on this article, I did an Instagram poll asking the IBD community if they take a magnesium supplement. Of the 245 people who responded, 34% said “yes”, 29% said “no”, and 37% replied “should I be?”

The power of Magnesium

“Magnesium is one of those quiet powerhouses in the body,” Hollie explains. “It’s often overlooked, but absolutely essential. It plays a role in over 300 biochemical reactions, helping muscles relax, supporting proper nerve function, balancing hormones, and aiding energy production.”

When magnesium levels drop, your body knows it—but it doesn’t always scream it out loud. Instead, it whispers. Symptoms like anxiety, poor sleep, muscle cramps, low energy, and even restless legs may emerge. But there are subtler signs too: eye twitching, heart palpitations, tingling sensations, and a hypersensitivity to noise or stress.

For those with IBD, particularly Crohn’s disease, magnesium deficiency can be even more pronounced. “When the gut is inflamed or damaged, it struggles to absorb nutrients properly,” Hollie shares. “And magnesium is one of the first to drop.”

The Magnesium–IBD Connection

Recent research, like the article “Magnesium—A Potential Key Player in Inflammatory Bowel Diseases? published in the Journal of Inflammation Research, highlights the strong link between magnesium deficiency and IBD. But knowing you’re deficient and being able to do something about it are two very different things, especially if your gut can’t absorb it well.

That’s where Sweet Bee Organics comes in. Rather than relying on supplements taken by mouth, Hollie and her team focus on transdermal support—a method that completely bypasses the digestive system.

“Our Sweet Sleep Magnesium Butter delivers highly absorbable magnesium chloride directly through the skin,” Hollie says. “You simply massage it into your chest, feet, lower back, or even your tummy before bed. It’s not just about topping up magnesium—it’s about calming the nervous system, supporting sleep, and helping the body reset.”

The Sweet Sleep Magnesium Butter isn’t just effective—it’s a best-seller across the U.S. and U.K. for a reason. “We’re obsessed with packing as much magnesium as possible into our balm,” says Hollie. “It’s not easy, but we’re committed to delivering a product that works—and works quickly.”

For people with Crohn’s or ulcerative colitis, the benefits of restoring magnesium levels can be profound. Balanced magnesium supports better digestion, improves sleep, reduces muscle tension, steadies mood swings, and even eases PMS symptoms. You sleep better. You feel calmer. Your energy becomes more stable, and your muscles feel less tight or twitchy.For IBD patients in particular, it can help calm inflammation and improve nutrient absorption—essential steps in managing the day-to-day symptoms of the disease.

“It’s not a magic fix, but it’s one of those foundational nutrients that helps everything else work better. The biggest thing people notice? They just feel more like themselves again,” Hollie explains.

Hollie’s Health Journey

This mission is deeply personal for Hollie, who was diagnosed with aggressive cervical cancer and had to completely reimagine how she cared for her body. “Magnesium became an important part of my healing journey. It wasn’t just about sleep or stress—it was about helping my body heal, rebuild, and feel safe again.”

Screenshot

Hollie happens to be my husband’s first cousin—and witnessing her health transformation and all she’s accomplished since her cancer diagnosis has been awe-inspiring. We’re not only family, but friends and I admire her and the genuine work she’s doing. We’ve wanted to collaborate for awhile and when Hollie saw the recent published medical study regarding magnesium and IBD we knew this was the perfect opportunity.

Hollie and I took our kids trick or treating this past Halloween when she was back in the States

Her empathy extends to the IBD community. “For anyone living with IBD, I truly see you. I know how exhausting it can be to manage symptoms, juggle treatments, and wonder if your body is even absorbing what it needs. That’s why I created Sweet Bee. Magnesium might seem like a small thing, but sometimes the smallest shifts are the ones that change everything.”

How is Magnesium Measured—and Why the Standard Test Might Miss the Mark

Many of us assume a blood test will tell the full story, but Hollie points out that traditional serum magnesium tests only measure about 1% of the magnesium in your body.

At my clinic visit with my GI last week, my doctor included magnesium in my lab work and the results were within range, but he also told me there would be no harm in using the transdermal magnesium discussed in this article.

For people with IBD, especially those experiencing persistent symptoms, your GI may suggest testing beyond the standard serum magnesium draw or even recommend supplementation based on symptoms alone. This may be something you want to bring up during your next clinic visit or over the Patient Portal.

How to Naturally Raise Your Magnesium

While supplements are helpful, diet is still key. Magnesium-rich foods include:

  • Pumpkin and chia seeds
  • Almonds, cashews, and peanuts
  • Beans and legumes
  • Spinach, broccoli, and potatoes with skin
  • Whole grains like oats and brown rice
  • Avocados, bananas, raisins
  • Milk, yogurt, and soy milk
  • Salmon, halibut, chicken, beef
  • Fortified cereals

That said, people with IBD often can’t rely solely on food due to absorption challenges. This is where topical support like Sweet Bee’s magnesium products truly shine.

Can You Take Magnesium with Crohn’s or Colitis?

Yes, but with care. Magnesium—especially in forms like citrate—can cause loose stools, which is problematic for IBD patients. That’s why topical magnesium is often a safer, more effective choice.

Always consult with your gastroenterologist before starting new supplements, especially if you’re in an active IBD flare, dealing with kidney disease or if you’re concerned about the medication(s) you are on.

Final Thoughts

In the landscape of IBD care, it’s easy to feel overwhelmed. But as Hollie reminds us, simple, natural tools—when thoughtfully applied—can offer real relief. Whether you’re struggling to sleep, feel calm, or just want to feel like yourself again, magnesium might be what your body’s been craving.

“You deserve to feel strong, rested, and well in your body. Replenishing magnesium levels in a gentle, non-irritating way can make a real difference in how you feel, both physically and emotionally,” Hollie says. “And we’re here to support that every step of the way.”

Learn More About Sweet Bee Organics

To explore Sweet Sleep Magnesium Butter and other clean wellness products created with love and integrity, click here. Use code NATALIE15 for 15% off sitewide.

Sweet Sleep was recently spotlighted on The View Co-Host’s Favorite Things for Mother’s Day. Check out the segment here.

Additional resources:

Can You Take Magnesium With Crohn’s or Colitis? | MyCrohnsAndColitisTeam

IBD and Magnesium | InflammatoryBowelDisease.net

Magnesium for ulcerative colitis: Benefits and more

Does Magnesium Provide a Protective Effect in Crohn’s Disease Remission? A Systematic Review of the Literature

Malnutrition in Ulcerative Colitis: 6 Common Vitamin and Mineral Deficiencies

What can magnesium do for you and how much do you need? – Harvard Health

Disclaimer: This article was not sponsored, but the content is for informational purposes only and does not replace professional medical advice. Always consult your healthcare provider before starting any new supplement.