From Puberty to Menopause: How IBD Care Evolves for Women Across a Lifespan

As the years go by living with IBD, our health needs change and our IBD care should evolve with us. Women’s health in IBD is about so much more than pregnancy. Symptoms around menstruation, questions about contraception, puberty, sexual health, fertility, menopause, bone health, and cardiovascular health are all legitimate parts of your IBD care. Cedars-Sinai Hospital in Los Angeles, California recently held their second annual Women’s Health in IBD Conference.

Dr. Puja Khanna, MD, spearheads the conference and wanted to share more about the key takeaways and where she sees personalized medicine moving in regard to women’s health now and into the future. This week on Lights, Camera, Crohn’s, Dr. Khanna shares incredible guidance that will leave you feeling empowered as you navigate all the joys of being a female living with IBD.

Personalized IBD care for women

We have become very sophisticated at phenotyping IBD—Crohn’s versus ulcerative colitis, disease location, behavior, biomarkers, and prior medication exposure. But we have been much less sophisticated about incorporating a woman’s life stage into that same personalized approach.

“A 14-year-old navigating puberty, a 28-year-old choosing contraception, a 35-year-old planning pregnancy and a 52-year-old entering menopause may have exactly the same Crohn’s phenotype on paper, but they do not necessarily have the same health priorities or the same risks.”

Dr. Khanna thinks the future of precision medicine in IBD needs to include not only what kind of IBD a patient has, but also where a woman is in her life, and what she needs at that specific life stage.

Navigating hormonal shifts

Hormones can intersect with IBD throughout a woman’s entire life—from puberty and menstruation, through contraception and pregnancy, and into perimenopause and menopause.

“I want women to understand that changes in symptoms do not always mean their IBD is becoming more active. Hormonal shifts can affect bowel habits, fatigue, pain, sleep, and mood, and sometimes those symptoms can look like an IBD flare,” Dr. Khanna explains. “The good news is that we increasingly have tools such as fecal calprotectin, blood markers and intestinal ultrasound that can help us distinguish symptoms from true intestinal inflammation rather than simply guessing.”

Recognizing that your GI team is a safe space

As a woman who has lived with Crohn’s disease for over 21 years, I know from my own personal experience how important it is to feel comfortable bringing these issues up to your GI team. Women’s health and IBD are all part of the comprehensive care you should be receiving. Questions about periods, contraception, sexual health, fertility, menopause, bone health, and even cardiovascular health are all part of comprehensive IBD care.

“I want women to feel empowered. Their health needs are going to change throughout their lives, and their IBD care should change with them. The goal is not simply to control inflammation—it is to help women with IBD stay healthy and thrive through every stage of life,” says Dr. Khanna.

The intersection of each chapter in a woman’s life with IBD

While pregnancy remains incredibly important, it’s important to remember that the child-bearing years are just one chapter in a woman’s life with IBD. It’s becoming increasingly understood that each touchpoint in a woman’s development and aging intersects with IBD in different ways.

Dr. Khanna says, “Research is beginning to reflect that broader view. Recent reviews are specifically looking at IBD from puberty through menopause rather than treating women’s health as synonymous with pregnancy. The next step is translating that into routine clinical care, where we proactively ask women about these issues rather than waiting for them to bring them up.”

Gaining a better understanding of hormones and their impact on IBD

Hormones used to be thought of as almost an on-off switch—more estrogen or less estrogen and perhaps more or less inflammation. We now appreciate that it is far more complicated.

“Estrogen and progesterone interact with receptors on intestinal epithelial and immune cells and may influence intestinal permeability, immune signaling, gastrointestinal motility and even the gut microbiome,” says Dr. Khanna. “At the same time, the microbiome can influence estrogen metabolism through what is sometimes called the “estrobolome.” Genetics, medications, diet, and underlying inflammation are interacting with all these pathways.”

The important caveat is that much of the mechanistic science is ahead of the clinical evidence.

“We understand the biologic plausibility much better than we did a decade ago, but we cannot yet predict an individual woman’s IBD course based on hormone levels.”

Puberty and IBD

Dr. Khanna recommends parents watch out for the overall trajectory rather than any single symptom. Ask yourself:

Is she growing appropriately?

Is she gaining weight?

Is puberty progressing normally?

Are menstrual periods developing normally?

Is she unusually fatigued or becoming iron deficient?

Has her appetite changed?

“Growth failure or delayed puberty can be a manifestation of inadequately controlled IBD, particularly Crohn’s disease. Chronic inflammation, inadequate nutrition, and corticosteroid exposure can all interfere with growth, pubertal development, and the accumulation of bone mass during a period when young women should be building the foundation for their future bone health,” says. Dr. Khanna.

We should not automatically dismiss significant weight loss, delayed puberty, persistent fatigue, or major menstrual abnormalities as simply being part of adolescence.

Dr. Khanna says, “We do not have compelling evidence that puberty itself simply “switches on” IBD activity. In fact, one of the clearest relationships goes in the other direction: uncontrolled inflammation and poor nutrition can delay growth and puberty.”

It’s important to note—sex hormones interact with the immune system, intestinal barrier, and microbiome, so puberty is occurring during a period of tremendous biologic change. What ultimately happens to an individual patient is probably determined by the interaction of hormones with genetics, immune regulation, nutrition, microbiome composition, medications, and the underlying behavior of her IBD.

Symptoms peaking during your period?

This is such an important distinction because more symptoms do not necessarily mean more inflammation. Read that again.

“More than half of women in a large IBD cohort reported worsening symptoms during menstruation, and other studies have shown increases in diarrhea, abdominal discomfort and bowel frequency around the menstrual cycle,” says Dr. Khanna. “Hormonal fluctuations and prostaglandins can change intestinal motility and visceral sensitivity even when the IBD itself remains controlled.”

Dr. Khanna asks her patients about the pattern. If the symptoms predictably occur around every menstrual cycle, resolve as the period ends, and the patient otherwise feels well, that makes a hormonal contribution more likely. If symptoms are progressively worsening, persisting beyond the menstrual window or accompanied by features such as rectal bleeding, nocturnal diarrhea, weight loss, or persistent systemic symptoms, she becomes more concerned about inflammatory activity.

“A predictable, short-lived pattern that happens at approximately the same point in every cycle and then returns to baseline is reassuring, particularly in someone whose IBD has otherwise been objectively well controlled,” she explains.

Dr. Khanna says she would want a patient to contact her when something is different from the usual pattern:

  • Symptoms are becoming progressively more severe
  • Symptoms continue well beyond the menstrual period
  • Development of new rectal bleeding
  • Persistent nighttime symptoms,
  • Fever
  • Weight loss
  • Dehydration
  • Significant anemia or fatigue
  •  Not returning to baseline

“One of the messages I want women to hear is: you do not have to decide on your own whether this is hormones or IBD. That is exactly where objective monitoring can help,” says Dr. Khanna.

Diagnostic tools that help make the distinction between hormonal symptoms and inflammation

Fecal calprotectin is particularly useful because it gives a relatively noninvasive measure of intestinal inflammation. Your GI can also look at blood markers such as CRP, although CRP is not equally sensitive in every patient.

“Intestinal ultrasound is another exciting tool because it allows us to look directly for features of bowel inflammation—such as increased bowel-wall thickness and vascularity—without radiation and often right in the clinic. Depending on the situation, cross-sectional imaging or endoscopy may also be appropriate,” says. Dr. Khanna.

The larger point is that modern IBD care increasingly allows doctors to separate symptom burden from inflammatory burden. That distinction is extremely important for women whose symptoms fluctuate with hormonal transitions.

Hormonal contraception and IBD activity

Overall, Dr. Khanna says there is not convincing evidence that hormonal contraception consistently causes established IBD to flare. Older cohort data and European guidelines have generally been reassuring, although a 2025 systematic review emphasized that the available studies are heterogeneous and the certainty of the evidence remains low.

“For me, the bigger issue with estrogen-containing contraception is often not disease activity but blood-clot risk. IBD itself increases the risk of venous thromboembolism, particularly during active disease, hospitalization, surgery, or corticosteroid exposure. The CDC therefore recommends individualized assessment before using combined estrogen-containing contraception in women with IBD who have additional thrombotic risk factors,” explains Dr. Khanna.

Long-acting options such as an IUD or implant can be excellent choices for many women.

“We also must think about bone health when considering depot medroxyprogesterone and about absorption of oral contraception in women with significant small-bowel disease or extensive resections. The contraceptive conversation should really be individualized.”

Emerging data on perimenopause and IBD

During perimenopause, estrogen and progesterone do not simply decline in a straight line—they can fluctuate considerably.

Dr Khanna says, “Those hormonal changes may affect intestinal motility, visceral sensitivity, immune regulation, intestinal barrier function, and the microbiome. That creates the potential for changes in GI symptoms even when inflammatory disease activity has not changed.”

But we need to be very clear about the limitations of the evidence. A recent systematic review found only 15 studies addressing menopause and IBD, and most women did not report a major change in their IBD after menopause, although a subset did worsen. We need much more prospective research during the actual perimenopausal transition.

The overlap between perimenopause and IBD symptoms

There is tremendous overlap, which is exactly why this can be challenging.

“Fatigue can come from active inflammation, anemia, poor sleep, or menopause. Joint pain can be an extraintestinal manifestation of IBD, but musculoskeletal symptoms also become common during the menopausal transition. Bowel habits can change because of IBD, but hormones can also influence motility and visceral sensitivity.”

Dr. Khanna says instead of attributing everything to either IBD or menopause, she prefers to ask two questions simultaneously: Could her IBD be active, and could menopause be contributing to how she feels?

“We can then use her clinical pattern together with CBC, iron studies when appropriate, CRP, fecal calprotectin and sometimes intestinal ultrasound or endoscopy to determine whether inflammation is actually present.”

Just like disease journey, menopause is experienced uniquely, too

Biologically, two women are not experiencing the same transition. They may have different IBD phenotypes, different levels of baseline inflammation, different prior surgeries, different medications, different microbiomes, different genetic susceptibility and different responses to estrogen and progesterone signaling. One woman may also have overlapping IBS, pelvic-floor dysfunction, or musculoskeletal symptoms that another woman does not.

Even the hormonal transition itself varies enormously between women.

“That heterogeneity is one of the reasons I do not think we will ever have a simple statement that “menopause makes IBD better” or “menopause makes IBD worse.” The 2025 systematic review reflects that variability: most women had no major change, while subsets reported worsening or improvement,” Dr. Khanna says.

Hormone Replacement Therapy and IBD—Yay or nay?

The available evidence is reassuring, but it remains limited.

“An older study suggested less IBD activity among postmenopausal women using hormone therapy, and a more recent multicenter retrospective study also found improvement in physician-assessed disease activity after HRT. The newest systematic review concluded that hormone therapy may reduce flare severity but emphasized how limited the evidence remains.”

Dr. Khanna says she would not prescribe hormone therapy as a treatment for IBD, because we do not have evidence to support that. But having IBD by itself should not automatically exclude a woman from receiving appropriate treatment for bothersome menopausal symptoms.

This is a shared decision involving the patient, her women’s health provider and, when appropriate, her gastroenterologist. Remember it’s a team approach—keep your providers in the loop and don’t silo your “women’s health issues” to one provider, make sure your gastroenterologist knows what you’re experiencing, too.

Considerations for Estrogen-containing therapy, progesterone, or menopausal treatments

Women with IBD already have an elevated risk of venous thromboembolism (blood clots), particularly when their disease is active. Oral estrogen can also increase thrombotic risk. For women with increased VTE risk, data from the broader menopause literature suggest that transdermal estradiol has a more favorable thrombotic profile than oral estrogen.

“We also consider whether the woman has a uterus, because systemic estrogen generally requires an appropriate progestogen to protect the endometrium, as well as her age, time since menopause, cardiovascular history, smoking, prior thrombosis, breast-cancer risk, migraine history, bone health and current IBD activity,” explains Dr. Khanna.

So, it should not be “IBD equals no hormones.” It should be a thoughtful, individualized risk-benefit assessment.

Being Proactive with Bone Health

IBD can affect bone health through chronic inflammation, malnutrition, low body weight, and corticosteroid exposure, and then menopause adds the accelerated bone loss associated with declining estrogen.

Current AGA guidance recommends considering bone-density testing in people with IBD who have risk factors including low BMI, more than three cumulative months of corticosteroid exposure, smoking, hypogonadism, or postmenopausal status. Even in the absence of additional risk factors, bone densitometry should be considered in postmenopausal women with IBD.

I personally have had a “bone health doctor” for the past four years. It blows my mind how many people with IBD I speak to who never had a baseline bone scan. My first bone scan was at age 26. Bring this up to your GI, it’s important to be proactive rather than reactive. Now, at 43, given my history of Crohn’s, anemia, past steroid exposure,  and my age, I get a bone scan every two years.
“I also think about vitamin D status, adequate calcium intake—preferably through diet when possible—regular weight-bearing and resistance exercise, adequate protein, minimizing unnecessary steroid exposure, avoiding smoking, fall prevention and treating osteopenia or osteoporosis when indicated,” says Dr. Khanna.

For women with IBD, bone health should become part of the menopause conversation before the first fracture occurs.

Working together across specialties

One of the biggest gaps in medicine has been that women with IBD have often had to navigate their gastroenterological health and their women’s health in parallel rather than together.

That is beginning to change.

“We are learning that hormonal transitions can influence symptoms, immunity, the intestinal barrier, the microbiome, bone health, cardiovascular risk and quality of life—but we also have to be careful not to attribute every change a woman experiences to hormones.”

Dr. Khanna says the opportunity now is to build a model of care where gastroenterology and women’s health truly intersect across the lifespan.

“That means asking better questions, using objective measures of inflammation when symptoms are ambiguous, collaborating across specialties and making sure women have the information they need to advocate for themselves. For me, that is really the future of women’s health in IBD.”

One final piece of advice

I asked Dr. Khanna if she could give women with IBD one piece of advice about navigating their disease through puberty, menstruation, pregnancy, perimenopause, and menopause, what she would want them to know.

“I would tell them: Do not assume that every symptom is your IBD but also do not assume that everything is “just hormones.” Ask the question and let us help you figure it out.”

When it comes to future IBD and Women’s Health Conferences through Cedars-Sinai, Dr. Khanna would love to expand the reach of the program well beyond the women who can physically attend a conference in Los Angeles.

“We are exploring virtual collaborations and opportunities to connect with colleagues and patients in other communities so that education around women’s health and IBD can become more accessible. I would like to see women’s health become an integrated part of excellent IBD care everywhere—not a niche topic or something we discuss only when a woman becomes pregnant.”

What If You Never Had to Forget What Your Doctor Said Again? Babble Puts Patients in Control

This is a sponsored blog post. All thoughts and opinions are my own.

You’re in the doctor’s office with a thousand thoughts flying through your mind as your provider asks questions and shares intel that you’re trying to remember but can’t keep up. You nod and appear to be fully engaged and listening, but you walk out feeling a bit confused and unclear of next steps. We’ve all been there. That’s where a new app called “Babble” comes to save the day. To advocate for yourself, you first need to understand your own health story. This week on Lights, Camera, Crohn’s we hear firsthand from the co-founder of Babble and why she felt the need to create this cutting-edge tool for patients and caregivers.

How Babble was born

Jessica Bieligk, co-Founder of Babble, can pinpoint two experiences that really drove her to try and create a healthcare solution. She was volunteering to drive some of her older neighbors to their doctor’s appointments and through that she witnessed how challenging it was to capture what the doctor said and then effectively communicate it back to adult children or caregivers in the room.

“In parallel, I was managing healthcare for myself and my three young children. I was constantly scribbling questions on pieces of paper, trying to take notes on my phone, forgetting what a doctor had told me months earlier, or calling my husband after an appointment and trying to recreate a conversation from memory,” Jessica says.

The combination of the two made her realize that there was an opportunity to make this easier for patients and their families. We didn’t have to carry as much of the mental burden – patient-owned technology should be able to help us.

What does “Babble remembers, so you don’t have to” really mean in practice?

We can all relate to how it feels when you’re sitting in an appointment telling yourself I need to remember this. Jessica wants people utilizing Babble to be engaged listeners who are asking questions and being present without the added, unnecessary pressure.

“Babble can capture the conversation and turn it into a clear summary with the important takeaways and next steps,” she explains. “That summary becomes part of your health story, so three months later you’re not trying to remember, What did my GI say about that medication? When was I supposed to follow up? Why did we decide to change treatment?”

Babble remembers, so your brain doesn’t have to be the medical record.

Breaking down the process

Babble app developers have broken the experience on Babble to three simple steps.

Prepare → Capture → Share.

Before the visit, you can create the appointment and add the questions or concerns you want to discuss. Babble even provides some suggested questions based on your initial input. That alone can make an appointment more productive because you’re not trying to remember everything once the doctor walks into the room – there’s a simple “cheat sheet” from the app.

During the visit, with permission, you use Babble to capture the conversation. Instead of frantically taking notes, you can focus on the discussion, make sure you ask the questions that matter to you and truly engage with the doctor to feel confident in your care.

Afterward, Babble turns that conversation into a clear, easy-to-understand summary with the important information and next steps. It becomes a chapter in your health story and you’re able to easily share it with someone in your care circle who you want in the loop.

“This capsule approach hopefully ensures your questions are answered and you’re able to have a simple way to refer to what you discussed with the doctor. The goal is that the content of the appointment doesn’t disappear the moment you leave the exam room and that you’re able to keep others informed, even if they can’t be in the appointment directly,” says Jessica.

What sets Babble apart

Notes on your phone are only as good as what you manage to type while you’re also trying to listen, process information and ask questions. We’ve heard from patients with chronic illness that sometimes they feel like they have to choose between listening to the doctor and documenting what the doctor says.

Patient portals solve a different problem. They’re incredibly useful, but they’re generally organized around a provider or health system. Your GI might be in one system, your dermatologist in another, and another specialist somewhere else.

“Babble is organized around you – the patient- and is a simple experience that lets you keep your health story in a single place. It’s your record of what you discussed, what you understood and what you’re supposed to do next — across doctors, specialists and health systems,” Jessica shares.

There are an abundance of AI note-taking tools out on the market right now. Those are great and can work well for many people. Babble is a secure, healthcare focused and intentionally designed experience where all your health information is owned by you, in one place and easy to access when you need it.

Leveraging the conversations between providers and patients

Babble leverages AI to transcribe the audio from the conversation with the doctor and then create a simple summary of key themes and takeaways.

Babble can take that conversation and create a clear, structured summary that helps you understand what was discussed and what happens next. And because you retain those summaries, the value compounds over time. You’re not just creating notes from individual appointments. You’re beginning to build a health story.

Doing the “homework” before the appointment

Preparation is an important part of Babble and an important part of care, especially when there are multiple stakeholders involved.

Before an appointment, you can put the questions and concerns that have been floating around in your head, or questions your family members have asked you, into one place. Instead of remembering something important in the parking lot afterward, you go into the appointment knowing what you want to cover.

“One of the things we’ve heard in testing is that people love the idea of Babble becoming the place where their pre-appointment thoughts live. And we’ve created an experience where you can create a starting point and add and adjust as you get closer to the appointment and may have new questions or concerns,” says Jessica.

Ultimately, using Babble should help you get more of the limited time you have with your doctors. You can be more efficient and effective in communicating your concerns up front and then have clarity following each appointment.

“While we’ve built Babble for patients, so many of the physicians we’ve met with through our research are excited about how it can help them deliver better care for their patients,” Jessica adds.

Sharing your health story with loved ones

Sharing is core to what Babble is building, and Jessica says it’s one of her most used aspects of the app – it’s become indispensable in keeping her and her husband on the same page with their children’s care.

The experience is simple, once a user receives the visit summary, they can select to share that summary with a person of their choosing. That might be a spouse, an adult child, a sibling or another caregiver. The designated individual will receive an email with the summary so they can get up to speed in just a minute.

Jessica and her family. As a busy mom, Babble has helped her keep track of all her family’s healthcare needs.

“Longer term, we hope to build in functionality so that users are able to collaborate across a care story (i.e. adult children coordinating a parent’s care) but we’re starting simple with the email,” says Jessica. “We’ve heard this need across generations: college students trying to explain an appointment to parents hundreds of miles away, adults coordinating care for aging parents, and parents trying to make sure both spouses understand what the pediatrician said.”

Instead of playing a game of telephone, everyone can work from the same information.

Addressing the hesitation around AI in healthcare

Hesitation is healthy. Healthcare information is incredibly personal, and Babble has been built in that reality. Babble is inspired by HIPAA-requirements and data security, and privacy have been priorities from the beginning.

“First, the patient is at the center of the product. Your information belongs to you, and you decide whom you share it with,” explains Jessica. “We don’t retain the audio recording after it has been processed, and your summaries are private to you unless you choose to share them.”

It’s also important to be clear about what Babble’s AI is, and isn’t, doing.

“Babble isn’t your doctor. It isn’t diagnosing you, prescribing treatment or replacing medical advice. We’re using AI to help you better capture, organize and understand the information from your actual healthcare conversations. It’s the communications superpower,” says Jessica.

The use of AI here is supporting the patient, not replacing the provider and users are reminded throughout the app experience that they should always confirm with their provider if they are confused by any of the notes.

A helpful tool for those with multiple specialists

The past few months, Jessica has collaborated with me and tapped into the Lights, Camera, Crohn’s community for product development and feedback from fellow patient advocates to better understand how Babble can support those us of navigating chronic illness. I personally have been appreciative of how genuinely invested Jessica has been in capturing what matters from the patient perspective.

“Patients have told us they’re exhausted by having to “start over” and reconstruct their history every time they see someone new,” says Jessica. “Babble gives the patient continuity even when the healthcare system doesn’t. Over time, your individual appointment summaries become a longitudinal health story that stays with you.”

We may have a gastroenterologist, primary care physician, dietitian, surgeon, dermatologist or other specialists involved in our care. Those providers may not share the same system, and each appointment is only one chapter. Babble helps take some of the pressure of coordinating care across specialists off our shoulders.

Screenshot

“Over the last year, we’ve relied on the feedback and reactions from parents, older adults, caregivers, college students and people managing complex or chronic conditions…and doctors, too. Despite very different circumstances, we keep hearing versions of the same things: “I remember the big picture but lose the details,” “My records are everywhere,” “I end up getting calls after hours from family members,” and “I don’t want to spend the appointment taking notes,” says Jessica.

Helping Caregivers stay in the know

Caregiving was one of the original inspirations for Babble. So much caregiving is really information and communication management: What did the doctor say? Did the medication change? When is the follow-up? What symptoms are we supposed to watch? Did anyone tell my sister?

And often the person managing all of this wasn’t even at the appointment.

“One caregiver we interviewed described receiving secondhand information from a sibling who accompanied the parent to appointments. Another talked about the anxiety of managing a parent’s medication instructions after missing the appointment because of work,” Jessica recalls. “I want Babble to reduce that burden. The person who attends the appointment can capture it, and the people helping with care can receive a clear summary, with the patient’s permission, rather than trying to reconstruct what happened.”

Looking into the future

On day one, Babble helps you have a better appointment. Six months later, it starts helping you understand your holistic health story. A year later, imagine being able to look back and clearly understand: Here’s what I was experiencing. Here’s what we discussed. Here’s what we tried. Here’s what changed. Here’s what my different specialists told me.

Instead of healthcare, feeling like a series of disconnected encounters, you have continuity and an integrated look across the providers and conditions you’re managing.

“That’s why our invitation to patients is: Start writing your health story with Babble,” says Jessica.

Subscribing to Babble

Babble is a subscription product because the creators made a deliberate decision to build a business where the patient is the customer.

“We don’t want the business model to depend on selling patient data or monetizing people’s health information. We want to build and continually improve a product that works for the patient,” says Jessica.

Everyone will be able to record their first visit free, so you can experience Babble before deciding whether it’s valuable enough to keep using. Then users can opt into a $4.99/month subscription that gives you access to tracking unlimited appointments (for you and as many others as you’d like to manage).

For the Lights, Camera, Crohn’s Community, for anyone that signs up in the month of October, the first month is FREE!

Final thoughts

Healthcare can feel overwhelming enough without having to remember every question, every medication change, every recommendation and every next step once you walk out of the exam room.

For people living with chronic illness and caregivers and loved ones helping them navigate it, that mental load can add up quickly. We shouldn’t have to rely on memory, scattered notes or a game of telephone to understand our own healthcare.

That’s what makes the idea behind Babble so compelling. It’s not about replacing your doctor or turning AI into your healthcare provider. It’s about using technology to help you listen, understand, remember and stay connected so you can spend less time trying to document your care and more time participating in it.

Because your health story shouldn’t live in a dozen patient portals, a stack of notes or someone’s memory.

It belongs to you.

And when you can walk out of an appointment knowing what happened, what comes next and how to explain it to the people who support you, that’s more than better notetaking. It’s a little more clarity, a little more confidence and, ultimately, a little more control over your healthcare journey.

Short Bowel Syndrome: The Complication Many IBD Patients May Not See Coming

For someone living with Crohn’s disease, surgery can feel like a necessary reset button. The diseased portion of your intestine is removed, you recover, and you hope your body and your life will settle into a new normal.

But what happens when too much intestine is removed, or the remaining intestine can no longer absorb what your body needs?

That’s where short bowel syndrome (SBS) comes in.

SBS occurs when the small intestine is too short or isn’t functioning well enough to adequately absorb the fluids, electrolytes, nutrients, and calories the body needs. For people with Crohn’s disease who have undergone multiple intestinal surgeries, SBS is a potential complication that deserves more attention.

When 18 inches of my small intestine were removed in 2015, SBS was never mentioned as something I might need to think about if future surgeries became necessary. And that got me wondering: How many other people living with IBD aren’t aware of this?

This week on Lights, Camera, Crohn’s, we’re taking a closer look at SBS: what it means for people with IBD, how it can affect quality of life, what treatment options are available, and what patients and caregivers should know so they can recognize the signs and advocate for the care they need.

What exactly is short bowel syndrome?

The small intestine plays a huge role in keeping us nourished and hydrated. It absorbs nutrients from the foods and liquids we consume and helps our bodies get the building blocks they need to function. When someone has SBS, there isn’t enough functional small intestine to adequately perform that job.

SBS can develop after surgical removal of the small intestine because of conditions including Crohn’s disease, other forms of IBD, cancer, blood clots, or traumatic injury. It can also occur in people who are born with a shortened or incompletely developed small intestine.

According to the Short Bowel Foundation, SBS is a rare condition affecting 20,000 people in the United States.

Much like IBD, A person with SBS may look completely healthy on the outside while dealing with fatigue, abdominal symptoms, frequent bathroom trips, diarrhea, difficulty maintaining weight and ongoing challenges with hydration and nutrition.

Dr. Sukanya Subramanian, MD, Medstar Georgetown University Hospital, is a small bowel adult transplant gastroenterologist and specializes in intestinal rehab. She says diagnosing SBS can be a challenge.

“For example, Crohn’s disease is much more recognizable with endoscopic, microscopic, and laboratory criteria. There isn’t an absolute unequivocal test that tells you that you do or don’t have short bowel syndrome. Sometimes people are in the ambiguous zone, and we have to estimate length of bowel, do testing of absorptive capacity, evaluate transit times of food through the remaining intestine and consider this in the context of symptoms and lab data to make inferences about the diagnosis.”

Short bowel doesn’t automatically mean short bowel syndrome

There isn’t a simple blood test, scan or single diagnostic test that says, You have SBS.

Short bowel is described as having fewer than approximately 180–200 centimeters of small intestine, but the number alone doesn’t tell the whole story.

Think about it this way: two people could have the same amount of intestine remaining but have very different experiences.

The amount of bowel someone started with can vary. A smaller person may naturally have less intestine than a much taller person. And someone may technically have more than 200 centimeters of intestine remaining but still experience significant problems if their bowel isn’t functioning properly.

That’s why length isn’t the only consideration. Function matters.

Healthcare providers need to consider whether the remaining intestine can absorb enough fluid, electrolytes, and nutrients to maintain adequate hydration and nutrition.

SBS should be on the radar for someone with a history of intestinal surgery who is experiencing ongoing loose stools, difficulty maintaining weight or challenges staying adequately hydrated.

Why Crohn’s patients should know about SBS

Life with Crohn’s is unpredictable and ongoing inflammation, strictures, fistulas, obstructions, and other complications can lead to surgery. While removing diseased bowel can be lifesaving and dramatically improves someone’s quality of life, every intestinal surgery can change the anatomy and function of the digestive system. For example, if someone has their ileum removed, they become vulnerable to fat malabsorption, meaning that bile salts can’t be recycled to the liver.

For patients who have had multiple resections, it’s important to understand that there can be consequences beyond the recovery period.

The question isn’t simply, “How much intestine do I have left?” It’s, “How well is the intestine I have left working?”

Dr. Subramanian says, “Length of remnant bowel is not the sole determining factor in the diagnosis of SBS. The quality of the remaining bowel is very important. Intestinal ischemia, active Crohn’s disease, Crohn’s fibrosis, and intestinal dysmotility are co-existing conditions that can impact the capacity of the bowel.”

This is a conversation worth having with your gastroenterologist, particularly if you’re experiencing persistent diarrhea, dehydration, nutritional deficiencies, or difficulty maintaining your weight after intestinal surgery.

Treatment starts with nutrition and hydration

When someone is first diagnosed with SBS, the immediate priority is getting the patient out of crisis and stabilized.

That can sometimes mean an escalation of care to make sure the person receives the fluids, electrolytes, and nutrition they need. Once someone is stable, the goal is to gradually optimize their intestinal absorption, and when possible, dial back the level of parenteral or intravenous support required.

“Dietary modifications are crucial to achieving enteral autonomy and far too often are treated as an afterthought during a clinical visit, explains Dr. Subramanian. “The dietary recommendation for each patient depends on their anatomy, mainly whether there is a colon present and if it is in continuity with the rest of the bowel. It is important that each patient with SBS work with their local care team to identify and address their unique needs.”

Some people can meet their nutritional needs by eating and drinking by mouth. Others may require nutritional support through a vein, known as parenteral nutrition.

Someone with SBS may assume that drinking more plain water is the obvious solution to frequent diarrhea or dehydration. But depending on the individual, simply increasing water intake may actually make symptoms worse.

That’s why some patients may need oral rehydration solutions specifically designed to help the body absorb fluids and electrolytes more effectively.

There is no “perfect SBS diet”

Nutrition counseling for SBS should be individualized and physician and patient priorities should be aligned.

A healthcare provider may consider:

  • What foods is the person eating now?
  • What foods do they tolerate?
  • What foods are important to them? Are there cultural considerations?
  • What are their nutritional needs?
  • What are their symptoms?
  • What changes are realistic?
  • What are the patient’s non-negotiables?

A treatment plan that completely ignores quality of life may look perfect on paper but may be challenging for a person to sustain. The goal should be to find an approach that supports nutrition and hydration while still honoring the person dealing with the diagnosis and setting them up for success.

Medications can help manage symptoms

Nutrition and hydration are the foundation of SBS care, but medications may also play an important role.

Antidiarrheal or antimotility medications can slow the movement of food through the intestine, which may help manage the diarrhea that frequently accompanies SBS.

Acid-reducing medications may also be used to decrease stomach acid that can contribute to damage of the intestinal lining and affect absorption.

And there is another important medication to know about: teduglutide, a GLP-2 analog.

Teduglutide is currently the only FDA-approved medication specifically for SBS. Unlike medications that primarily address symptoms, it is considered a disease-modifying treatment. It works by promoting structural and functional changes in the intestine, slowing intestinal transit, and improving nutrients and fluid absorption.

“Teduglutide has changed the paradigm of treatment of SBS because it is disease modifying; it structurally changes the bowel,” says Dr. Subramanian. “It doesn’t just slow transit; it enhances the capacity of the intestine to absorb. Patients have to be able to eat though in order for this treatment to be effective.”

Living with SBS can feel isolating

One of the most difficult parts of any invisible illness is explaining something that other people can’t see. People living with SBS and their caregivers and family members can benefit from connecting with others who understand the realities of the condition. SBS is not as dismal of a prognosis as it used to be. Support groups, advocacy organizations, and educational resources can help patients feel less alone and better equipped to advocate for their care.

If you or someone you love is living with short bowel syndrome, education and support can make a meaningful difference. The Med-IQ Short Bowel Syndrome Patient and Caregiver Education Resource Hub offers educational materials, links to patient advocacy and caregiver resources, and a clinical directory to help people find SBS care.

Thanks @mediqcme. Supported by an educational grant from Takeda Pharmaceuticals, U.S.A., Inc. 

Join me LIVE on Instagram TONIGHT (Monday, September 21) at 7 PM CT for an in-depth conversation with Dr. Subramanian about SBS—what it means for patients, the latest strides in care, and what patients and caregivers need to know. We’ll break down the questions you may have, the treatment landscape, and how people living with SBS can better advocate for themselves.

Med-IQ is conducting a survey about SBS and they are giving away FIVE, $100 VISA gift cards. You can participate in the survey and enter to win here: https://survey.alchemer.com/s3/8986041/Natalie-Hayden

At 14, Crohn’s Made Her Question Motherhood. At 22, She’s Studying Why.

For women living with Crohn’s disease or ulcerative colitis, the question of whether to have children can carry a weight that goes far beyond the usual conversations about fertility and family planning.

Will my disease be controlled enough to have a healthy pregnancy? What happens if I flare while I’m pregnant? Will my medication affect my baby? What if I’m too sick to care for a child? What if breastfeeding means making another difficult medication decision? And the question that can be hardest to articulate: Will I be able to experience motherhood without IBD taking over the entire experience?

For Grace Hubbel, those questions aren’t simply academic. They are personal.

Diagnosed with Crohn’s disease at 14, Grace is now 22 and studying sociomedical sciences at the State University of New York at Geneseo. Her own experience with IBD and the stories she has heard from other women, led her to pursue an IRB-approved research study examining “The Impact of IBD on Decisions in Maternity and Emotional Wellbeing in Women.”

This week on Lights, Camera, Crohn’s a look at how her personal experience as a young woman with IBD inspired this incredible research and how you can get involved as a citizen scientist. Grace’s goal through her study, “The Impact of IBD on Decisions in Maternity and Emotional Wellbeing in Women” is to explore an area of IBD research that she believes has been overlooked: not simply what happens to a woman’s body during pregnancy, but what it feels like to make decisions about motherhood while living with an unpredictable chronic illness.

A Crohn’s diagnosis at 14

Grace grew up watching her older brother struggle with Crohn’s disease. He was diagnosed when he was starting college and nearly lost his life before his first surgery. When Grace began experiencing symptoms of her own at 14, she wasn’t completely surprised.

Her disease quickly became severe. She lost weight rapidly, her menstrual cycle stopped, and painful sores and ulcers made it difficult to swallow. She remembers feeling exhausted and unlike herself.

“I crawled into my mother’s bed once and told her it felt like I was disappearing with how I was losing pounds by the week,” Grace recalls.

At an age when many teenagers are focused on school, friends and figuring out who they are, Grace was learning a different vocabulary: tests, treatments, infusions, injections, and surgery.

“I was so young, I felt so different from my peers around me,” she says. “I spoke fluent in healthcare, in tests, I was forced to grow up so fast.”
Her Crohn’s journey has included steroids, infusions, injections, tests, a feeding tube, and surgery. At 22, Grace says she is still chasing total mucosal remission and continues to deal with hidden inflammation.

“Will I be able to become a mom someday?”

And almost immediately after her diagnosis, another question entered Grace’s mind.

Would she ever be able to become a mom?

Grace says motherhood was on her mind within months of being diagnosed.

Part of that fear came from watching someone she knew with Crohn’s experience a life-threatening postpartum flare and be unable to have more children. That story stayed with her and illustrates one of the most difficult aspects of IBD whether you’re a parent or not: uncertainty.

“The monstrous part about IBD is its uncertainty,” Grace says. “It never ceases to amaze me how for some individuals a round of medicine will get their body into remission, and another person will have unrelenting inflammation for years and years.”
For women with IBD, that uncertainty can intersect with some of life’s biggest decisions.

Grace knows this firsthand. Throughout various stages of her disease, she has wondered what a flare would look like during pregnancy or while caring for a young child.

What if severe diarrhea caused her to lose weight and made it difficult to get enough nutrients for a baby? What if medication affected her child’s immune system? What about breastfeeding and medication exposure?

Today, Grace takes Stelara, and she says she thinks about the fact that it can pass through breast milk. She has always dreamed of breastfeeding a baby but wonders how she would weigh that desire against the medical considerations.

And increasingly, another concern has emerged: the emotional experience of pregnancy itself.

“I worry most of all about having to work extra hard as a high-risk pregnancy and that I’d be obsessive about it all,” she says, “living outside of the special moments and experiences because of viewing it all through a clinical lens.”
That sentence captures something that statistics and clinical guidelines can’t always convey.

A pregnancy with IBD isn’t just a series of medical decisions. It can also be an emotional balancing act between wanting to enjoy a deeply meaningful life experience and being unable to completely turn off the part of your brain that is constantly monitoring your disease.

Seeing a gap in IBD research

As Grace learned more about IBD, she found comfort in understanding the disease from both scientific and sociological perspectives. She connected with other patients online and found women with IBD who had navigated motherhood and became role models for her.

That interest eventually led her to major in sociomedical sciences.

When it came time to develop an independent research project, she knew immediately that she wanted to study IBD and women’s health.

That project eventually grew into her current IRB-approved study. Grace noticed that while there is substantial scientific literature examining Crohn’s disease and ulcerative colitis during pregnancy and childbirth, there is far less research examining the qualitative experience of women living through motherhood with IBD.

In other words, researchers have studied many of the physical and medical questions. Grace wants to better understand the why behind women’s decisions, experiences, and emotions.

“This told me something was missing,” she says.

And the missing piece matters.

IBD is commonly diagnosed during reproductive years, meaning many women are forced to make decisions about fertility, pregnancy, breastfeeding, and family size while simultaneously navigating an unpredictable disease.

Could uncertainty itself be affecting women emotionally?

One of the findings that initially caught Grace’s attention was that women with IBD commonly report higher rates of psychological distress than men with IBD.

There are several explanations, but Grace wondered whether another factor deserved more attention.

Could the uncertainty surrounding fertility and motherhood contribute to that emotional burden?

“Could any of it have to do with how uncertain it can be for women to navigate a motherhood journey with an unpredictable illness such as IBD?” she asks.

That question became central to her research.

Rather than focusing solely on conception and pregnancy, Grace wants to understand the entire motherhood journey:

  • What does it mean to parent while living with IBD?
  • How do mothers explain their disease to their children?
  • Does becoming a parent change the way women cope with their illness?
  • How do women make decisions about breastfeeding or having additional children?
  • And perhaps most importantly, how do those decisions make women feel?

“These are the questions I want to explore,” Grace says.

Motherhood doesn’t end at delivery

One of the most compelling aspects of Grace’s research is her focus on what happens after pregnancy.

So much of the conversation around IBD and reproductive health centers on conception and pregnancy. But motherhood is a lifelong experience and IBD doesn’t disappear once a baby is born.

Grace says some of the women she has heard from have described waiting for their doctors to give them the “go-ahead” before trying to conceive.

Others have described delaying or avoiding medical care when they were very sick because they didn’t want to leave their children or frighten them.

But the stories aren’t exclusively difficult.

Grace says she has also heard about positive experiences, including mothers who have noticed their children developing deep empathy toward other people because they grew up with a mother living with IBD.

That is an important reminder: IBD can shape motherhood in challenging ways, but it can also shape families into beautiful ones. As an IBD mom of three kids (ages 9, 7, and 5) I can’t attest to this. Motherhood was the best decision I ever made and my kids are my constant motivation to push through, stay on top of managing my Crohn’s so I’m well for not only myself, but for them, and reminding me all my body is capable of despite my disease.

The decisions women make behind the scenes

One theme Grace has found particularly interesting is the way IBD can influence the timing of family planning. Some women wait for disease stability or medical approval before trying to conceive. Others make decisions about seeking medical care based on the needs of their children. These aren’t necessarily decisions that show up in a medical chart.

They’re the quiet calculations happening in the background of everyday life. And that’s exactly what Grace hopes her research will capture.

The study is designed to explore the experiences and emotional impacts behind these decisions, not simply whether a woman became pregnant or whether she experienced a flare. Because as we know, two women can have similar diagnoses and vastly different emotional experiences.

What Grace wants doctors to talk about earlier

Grace believes the conversation about fertility and family-building should begin much earlier in a woman’s IBD journey. She would like gastroenterologists to routinely ask young women at diagnosis whether they envision having children someday.

“I think it’s so important to get the conversation started and have it routine to discuss it,” she says.

Starting the conversation early can open the door to resources, questions, and appropriate reproductive counseling long before a woman is ready to have a baby. Grace also believes healthcare providers need to be honest about uncertainty.

“We need to be comfortable acknowledging what we don’t know,” she says, particularly when it comes to questions about the long-term effects of medications on children.

She also wants to see stronger communication between gastroenterologists and OB-GYNs.

She has heard women describe being confused about which physician to rely on during pregnancy and postpartum or receiving contradictory recommendations from their doctors.

“Greater communication between OB-GYN physicians, maternal fetal medicine doctors, and gastroenterologists on the topic of IBD and pregnancy is called for,” Grace says.

For patients, that kind of collaboration can mean the difference between feeling like they’re navigating pregnancy alone and feeling like they have a team.

Grace hopes her research changes the conversation

Grace hopes her research will expand how the IBD community thinks about women’s health. The physical side of IBD is important. But emotional wellbeing matters, too.

She points to the connection between psychological health and IBD outcomes, noting that emotional distress can influence disease activity. Her research suggests that the emotional stress of navigating motherhood alongside IBD may be one contributor to the psychological burden reported by women with the disease.

Her long-term goal is to highlight the need for more reproductive counseling and pregnancy programs specifically designed for women with IBD. Because women shouldn’t have to piece together this information on their own. And they shouldn’t have to wait until they’re ready to conceive to start asking questions.

“You will survive some of your biggest fears”

The most powerful part of Grace’s story isn’t the researcher speaking about the gaps in the literature. It’s the 14-year-old girl underneath it all.

If Grace could sit down with herself on the day she was diagnosed, she wouldn’t promise that IBD would become easy. Instead, she would tell her younger self that the disease would shape who she became and that some of that impact would become a source of purpose.

Her experiences would fuel her interest in healthcare and disability advocacy. She would meet healthcare workers who saw through her knowledgeable exterior and recognized the anxiety underneath. She would survive some of the things she feared most. And she would eventually find a partner who would make motherhood feel possible. But she’d also tell herself something many young people with chronic illness need to hear:

You don’t have to control everything.

“I’d tell her to enjoy being a young woman and let go of trying to control so much,” Grace says.

That’s easier said than done when your body has taught you from an early age that anything can change without warning. But that’s also why her message to other young women with IBD is so meaningful.

To the young woman with IBD dreaming about motherhood

Grace doesn’t know exactly what the future holds for her. She still has questions. She still has fears. She still lives with an unpredictable disease. But she isn’t letting uncertainty erase the possibility of motherhood. Her message to other young women with IBD is simple:

“Advocate for yourself and ask questions.”

She encourages women to establish an OB-GYN early and start talking about what pregnancy could look like in the future, even if motherhood is years away. And she wants women to know that they don’t have to abandon the dream simply because IBD may make the path more complicated.

“The reality is, it might be a little more sad and scary to manage,” Grace says. “But from what I’ve learned so far: no women have regretted the choice to pursue their dream, even if it looks different from what they expected.”

For a 22-year-old researcher who has spent much of her life learning to live with Crohn’s disease, Grace is asking a question that deserves far more attention:

What happens when we stop looking at motherhood with IBD solely through a medical lens and start listening to the women living it?

Her research is an important step toward answering it.

Interested in participating in Grace’s research?

Grace is currently seeking women with IBD who are at least 18 years old, English-speaking, and currently mothers living with Crohn’s disease or ulcerative colitis, either biologically or through adoption. A diagnosis before having a child is preferred.

Participants can complete an anonymous survey or contact Grace for a virtual interview. Participation is voluntary, and information provided will be kept confidential.

Join the study here!

From Memory to Meaning: How Mirae Is Changing the Way We Manage IBD

This is a sponsored blog post; all thoughts and opinions are my own.

Living with Inflammatory Bowel Disease (IBD) means constantly reading the signals your body is sending you. What you eat, how you sleep, your stress level, your energy, and even the seemingly small changes in your routine can influence how you feel. After more than 21 years with Crohn’s disease, I’ve learned that this internal conversation never completely goes away, even during remission.

The challenge is that when symptoms become part of everyday life, gradual changes can be surprisingly difficult to recognize. Whether you’re newly diagnosed or have been living with IBD for decades, knowing your personal baseline can be one of the most valuable tools in managing your disease.

That’s where the Mirae Health app comes in. Rather than relying on memory or trying to piece together months of symptoms and lifestyle patterns before an appointment, Mirae helps patients see their own patterns and recognize when something starts to shift. This week on Lights, Camera, Crohn’s, we hear from Mirae’s founders about the inspiration behind the app and why understanding the connection between our daily lives and how we feel could change the way we approach IBD care.

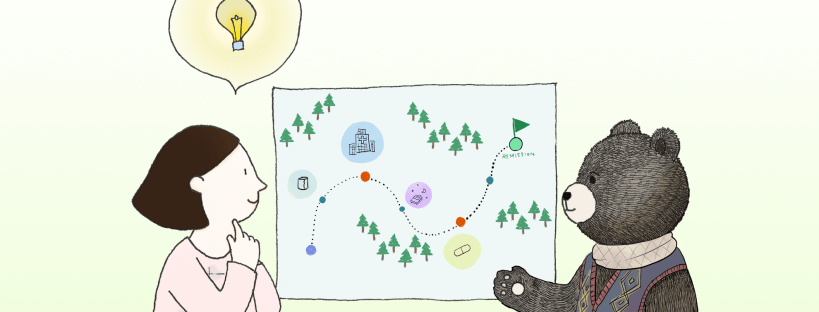
Mirae’s founding designer, Sayoko Yoshida, chose to use a bear because they wanted something that felt:

  • Warm and inviting
  • Steady and dependable
  • Protective
  • Human and personal

The Mirae team specifically didn’t want the app to feel like a cold clinical dashboard or an overly cheerful “health app” mascot. They wanted the bear to represent a reassuring guide, something that helps people living with IBD understand what’s happening and feel supported as they navigate their care.

The inspiration behind Mirae

Mirae’s three founders, James Finucane, David Clifton, and Anuj Patel, have spent their careers using technology to improve access to healthcare. For Anuj, Mirae’s CEO, the mission is also personal. His father was a GI clinician in rural upstate New York, where he saw firsthand how critical and unequal access to specialty care can be, something Anuj recently wrote about on Mirae’s blog.

The team behind Mirae

“It was very clear how unique and how critical having high-quality specialty GI care in a rural market helped patients and how unequal access to care across the US is,” Anuj explains. “It was important that we use technology to help patients that are at the intersection of a chronic, acute and complex condition, of which Crohn’s and ulcerative colitis were the obvious fit.”

Mirae grew from a shared desire to use technology to solve two connected challenges: the burden patients carry to track and remember their disease, and the limited snapshot clinicians often have when making important care decisions.

The “Aha” Moment

The realization wasn’t about one patient story, but where the most valuable information lives. In IBD, important signals are often small and daily: a change in urgency, creeping fatigue, or escalated symptoms when eating certain foods.

I know when my symptoms increase, I can become hypervigilant, quickly jumping to the worst-case scenario. Much of that internal battle happens privately, between me and the bathroom walls or in conversations with my mom and husband.

Yet very little of it makes it into the medical record. Instead, months of experiences get distilled into a few sentences during a clinic visit, filtered through stress and imperfect memory.

“The gap in IBD care is not a lack of good doctors or good treatments. It is that the richest data about the disease is generated by patients outside of a lab, colonoscopy or doctor’s visit and then mostly lost,” says Anuj. “Building something to capture that gently and carry it into the clinic in a useful form felt like the most obvious unsolved problem in the field.”

Anuj Patel, co-founder and CEO of Mirae Health

The Missing Puzzle Piece in Patient Management

As Mirae’s creators examined the gaps in IBD care, they saw one major problem: there was no single place connecting the pieces.

“People track symptoms in a Notes app, photos of meals on their phone, questions on scraps of paper, and half of it in their head. Most existing tools were built like diaries. They demand daily discipline, which is exactly what you do not have during a flare, so people abandon them when things get hard, when the data matters most. Most importantly, nothing connected the tracking to actual care,” says Anuj.

You can track symptoms for a year, but if your gastroenterologist never sees that information, it’s pointless. And when living with a chronic illness already feels like a full-time job, adding more work to disease management is the last thing those with IBD need.

Mirae aims to change that.

“We wanted to make day-to-day management delightful and to use the AI models developed by our team to better understand disease progression and connect that information to clinicians that can make more informed decisions on a patient’s care.”

Answering the Call as Patients Feel Overwhelmed and Unheard

Feeling unheard usually isn’t about clinicians not caring. It’s about trying to fit months of lived experience into a 15-minute appointment, with the patient expected to remember and explain it all on the spot. That’s an unfair expectation of someone who is unwell.

“Mirae is designed to carry that burden instead. The app does the organizing, the remembering, and the summarizing, so the patient does not have to perform their own case in the room,” says Anuj. “We kept the language plain, the daily effort small, and made forgetting or skipping days completely fine. The goal is that when you walk into a doctor’s visit, your patient experience is clearly summarized for a clinician, allowing the visit to be more humane and genuine, while helping clinicians make more informed treatment decisions.”

At home, Mirae is designed to make living with IBD feel a little lighter. You can think of it as a quiet companion while navigating an often-isolating disease.

“In the clinic, we want people to feel prepared and taken seriously. There is a real difference between walking in trying to remember everything and walking in with a clear summary of the last three months in your hand. One feels like being tested. The other feels like being a partner in your own care,” says Anuj.

A Step Toward Personalized Medicine and Treatment Options

Personalized medicine in IBD starts with recognizing that Crohn’s disease and ulcerative colitis are not one-size-fits-all. Mirae’s technology looks for patterns that can help identify patient subgroups and better understand how individuals respond to treatment.

“Knowing how patients in each subgroup respond to treatment or how symptoms manifest can help a care team recognize earlier when someone may need attention, rather than waiting for the next scheduled visit,” explains Anuj. “It can also make treatment discussions more grounded, starting with months of real-world data and experience that our tools can translate into clinical insight, rather than a few minutes of recollection.”

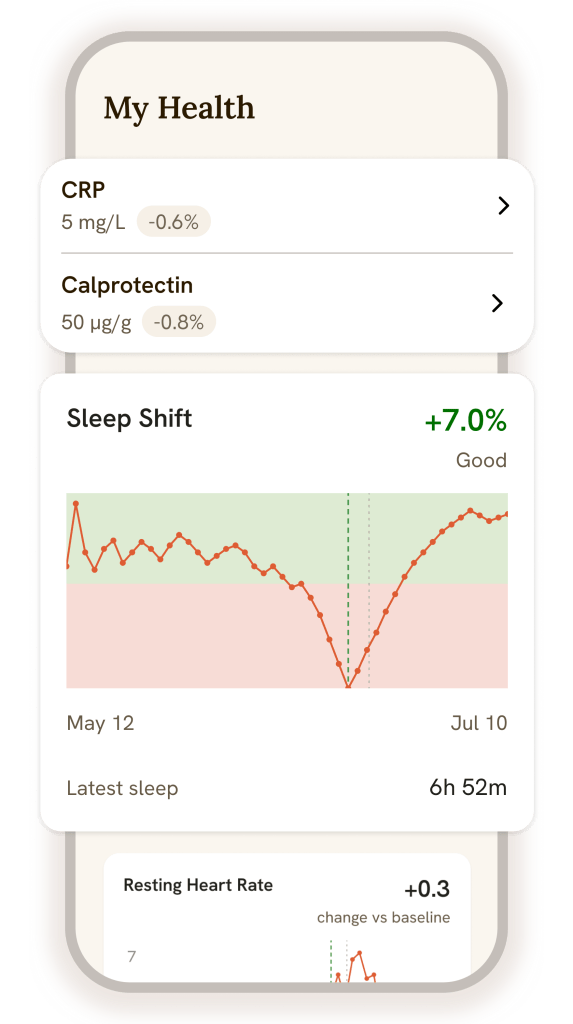
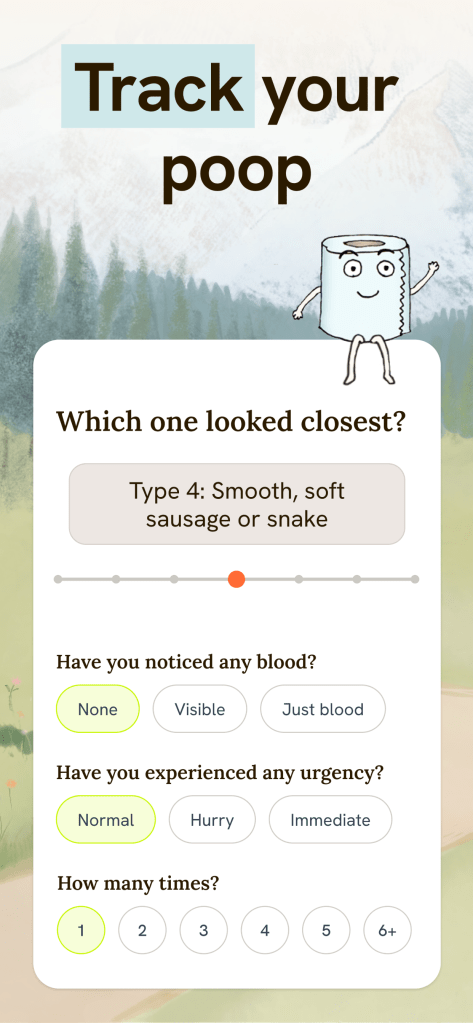
Mirae builds that picture from what patients choose to share over time: symptoms such as pain, urgency, bowel habits, fatigue, and energy; medications and how they’re tolerating them; lifestyle factors like sleep, food and activity; and free-form notes and questions captured in the moment.

The app looks for what has changed and what you’ve flagged. Mirae suggests; you decide. The goal is to make sure the things that matter most to you are at the center of the conversation. Mirae supports clinical judgment; it doesn’t replace it.

The App Is Free—How?

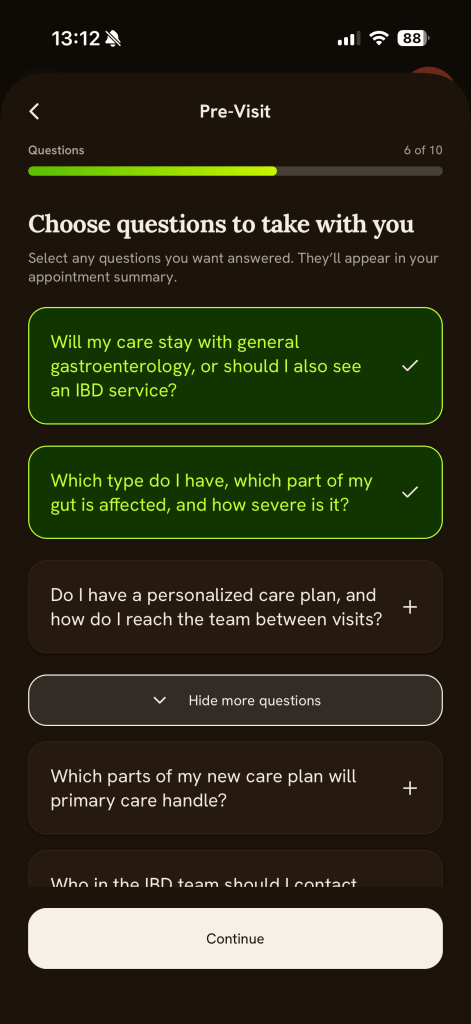
Living with IBD is expensive. Between medications, procedures, time off work, and everything in between, patients already carry a significant financial burden. Mirae’s creators didn’t want to add a subscription fee or rely on ads that could compromise the trust they’re building with patients.

“At a high level, our model works with the healthcare system for payment when patients enter remission sooner. Health systems and care programs benefit when patients arrive prepared, problems are caught earlier, and care between visits is more visible. All of this can help patients get on the right medication sooner while reducing future medical costs, such as surgery or ER visits,” says Anuj.

Making Patients Active Participants in Their Care

The biggest barrier to participating in our own care isn’t motivation, it’s preparation and organization. Too often, we leave appointments remembering the question we forgot to ask or downplaying what daily life with IBD feels like because suffering in silence has become our normal.

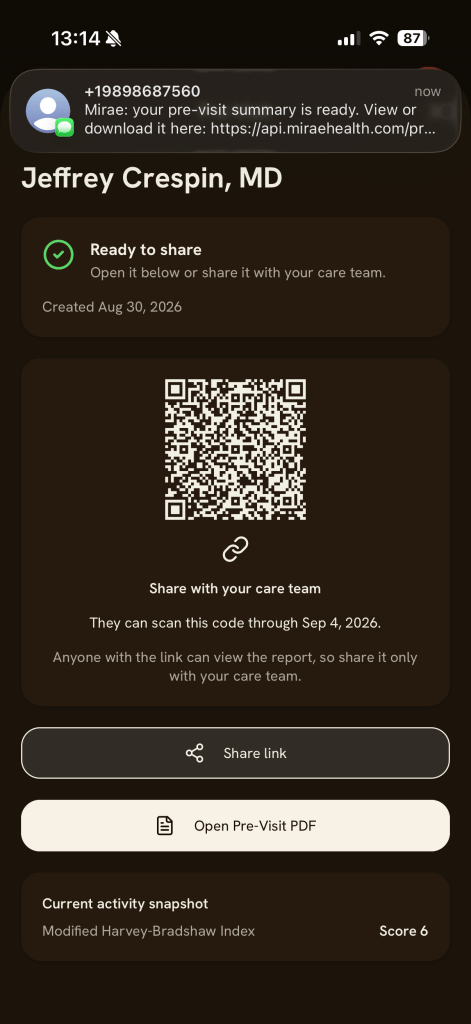
“Throughout the weeks between visits, the app makes it easy to capture questions and concerns as they come up, instead of hoping to remember them later. Before an appointment, it helps pull everything together into pre-visit notes: what has changed, what’s worrying you, what you want to ask, and what you want out of the visit,” explains Anuj.

When you arrive with that information in hand, the dynamic shifts. You’re no longer a passive recipient. You have an agenda backed by your own experience. That’s active participation in your care.

The Power of Pre-Visit Notes

One of my favorite Mirae features is the pre-visit process. You can capture observations about your health, answer targeted questions, and, most importantly, identify your biggest concerns going into the appointment.

Mirae then turns that information into a plain-language summary: what has changed, what has stayed stable, what’s worrying you, and the questions you want to address.

“You can edit anything, remove what doesn’t matter to you, and rank what you most want to discuss. You stay in control of what is shared. When you’re done, you have a short, clear document you can bring into the room or share ahead of the visit,” says Anuj.

An educated patient is an empowered patient. Taking a few minutes to prepare can help both you and your provider make the most of limited appointment time, something especially valuable when we’re juggling multiple specialists.

“The core principle is to change from your own baseline. A symptom level that is normal for one person may be a red flag for another, so relevance is always personal,” says Anuj. “The app looks at what is new since the last visit, what has been trending in either direction, or what has been persistent. Mirae also gives weight to things you have marked as important, medication changes and how they have gone, and anything that has come up repeatedly in your notes. Repetition is a strong signal that something deserves airtime.”

Input from Medical Providers and IBD Patients

Mirae was shaped with input from IBD clinicians, including advisors at Oxford and across the United States.

A consistent theme was where the appointment begins. Too often, the first minutes are spent reconstructing months of symptoms from memory. With organized pre-visit notes, that work is done, allowing more time for meaningful discussion, decisions, and care planning.

“Clinicians have also been clear with us about what they do not want: another screen, more unfiltered data, or anything that adds time. That feedback pushed us to keep the clinician-facing side short and structured. As the pilot progresses, we will let the results speak rather than getting ahead of them,” explains Anuj.

Dr. Simon Travis, Professor of Clinical Gastroenterology at the University of Oxford, sees Mirae as ‘stepping stones across a river, sometimes widely apart.’

He says, “Mirae acts as a bridge. It provides depth, credible advice, links to the evidence, informed comment, and guidance. It complements specialist advice by addressing complex factors such as fatigue or diet in detail, way beyond what is possible to cover during a consultation.”

Dr. Alissa Walsh, a Gastroenterologist at the Oxford University Hospitals NHS Trust and Nuffield Health, The Manor Hospital, Oxford, agreed to support Mirae because she believes people living with IBD deserve to be active partners in their own care, not passive recipients to it.

“Too often patients feel they’re navigating this condition alone, without the information or confidence to ask the right questions,” she says. “Mirae’s work has the potential to change that — empowering patients at every stage of their journey and, ultimately, improving the quality of care they receive.”

As an IBD patient advocate, I’m one of many who have helped to provide feedback and guidance through the app development process. Having patient and provider input is paramount to making sure the app works for us in real time. Multiple members of the Mirae team also have IBD themselves.

“It is hard to advocate for yourself on subjective terms such as “I feel like things have been worse lately.” It is much easier when you can say things have been different for six weeks, here is the pattern, and here is what I would like us to consider,” says Anuj. “When patients see their experience taken seriously, written down, reflected back, and brought into the clinical conversation, it reinforces that their observations matter.”

What Sets Mirae Apart from Other IBD Apps?

Most health apps are islands: you track diligently, but the information rarely goes anywhere. Mirae aims to close that gap in three ways:

  • Connected to clinical care. Mirae is designed to work with a patient’s existing care team. The information gathered is intended to inform care rather than sit in a silo. Its first deployment is within a large academic medical center.
  • Built specifically for IBD. This isn’t a general wellness app with an IBD mode. Mirae was incubated at Oxford’s Computational Health Informatics Lab and shaped by IBD specialists and patients.
  • Designed for both patients and clinicians. Rather than making patients pay for premium features or clinicians pay costly software fees, Mirae is built to serve both sides of the care relationship.

The Goal Five Years from Now

Looking ahead, Mirae’s creators hope the platform will build something that doesn’t currently exist at scale: a rich repository of patient-reported symptoms connected to clinical data that could improve treatment recommendations and eventually inform drug discovery. Longer term, they envision expanding beyond IBD to other autoimmune conditions, where many of the same challenges exist.

“The goal for us is in five years, is that “Maya”, a newly diagnosed Crohn’s patient, is able to use our platform to have a trusted companion that helps her understand her condition and, alongside her gastroenterologist, precisely identify the specific type of Crohn’s she has, find the best therapy for that type, and get on her way to remission and stay there.”

For Mirae’s founders, success means making that experience the norm, so Crohn’s becomes one part of Maya’s identity, not something that consumes her life.

Final Thoughts

Mirae’s goal is to end the era of memory-based appointments where patients carry months of their lives in their heads, then try to summarize it all under pressure. For gastroenterologists, it’s a similar challenge: extracting that information while balancing an enormous amount of clinical knowledge.

Mirae is designed to fit into patients’ lives, especially during the hard weeks, helping turn real observations into a clearer picture of their health and a more personalized care plan.

“We hope Mirae shifts some weight off patients’ shoulders. Managing IBD will never be effortless, but the administrative and cognitive load, the tracking, remembering, and preparing is something technology can genuinely carry. If patients spend less energy managing their disease and more living their lives, we have done our job.”

Download Mirae for FREE! Learn more about Mirae here.

Apple Store

Android

Cyclospora and IBD: Should You Still Be Avoiding Fresh Produce?

Since mid-July, I haven’t had a salad with lettuce, fresh berries, grapes, you name it. It may seem extreme, but as someone living with Crohn’s disease, I’ve been fearful of contracting Cyclospora.

It’s been making headlines for weeks, but for those who may not know, Cyclospora is a foodborne parasite that causes an intestinal infection. Symptoms can include watery diarrhea, stomach cramps, bloating, fatigue, gas, nausea, and loss of appetite.

For someone with inflammatory bowel disease (IBD), the tricky part is that Cyclospora can mimic an IBD flare because the symptoms can be so similar. This week on Lights, Camera, Crohn’s, we’re taking a deep dive into the current Cyclospora concerns and hearing from three well-respected gastroenterologists about how our community should be navigating them.

What the Community Has to Say

I shared a poll on my Instagram (@natalieannhayden) asking my followers: “If you have IBD, are you still refraining from eating lettuce, berries, cilantro, jalapeños, etc. due to Cyclospora?”

Of the 421 people who responded, 47% said “yes,” 33% said “no,” and 20% said they “never stopped.”

Hearing this didn’t entirely surprise me. When I went out to dinner with my family over the weekend, I was shocked to see almost every table with people eating salad. It made me wonder: Am I being too extreme? Should I start eating my normal diet again?

I should note that I’ve continued cooking vegetables for my family, and we’ve still been eating apples, bananas, and melons. But I’ve personally been avoiding many of the foods that have made me nervous during this outbreak.

And judging from the responses I received, I’m certainly not alone.

Madison: “Ugh, I so badly want a Jimmy John’s sandwich after pregnancy, but I’m so worried to get Cyclospora and flare.”

Amanda: “I never stopped eating fresh produce because I get my food from the farmers market.”

Katie: “Never been so happy for my garden than this summer!”

Jaclyn: “I think I may start eating the Little Leaf brand lettuce again. They have publicly stated they are not affected and have shared their production process. It’s been months of not eating produce, so I’m reallllly missing it. Also, I need my fiber!!”

Phoebe: “I’m only buying from my local farmers market, and I took my family berry picking to be safe.”

Sarah: “Only pre-bagged shredded lettuce, but I’ll probably give up on refraining from eating it, as I’m not seeing as many patients with it now.”

Lyndsie: “They told me at chemo prep to avoid the diarrhea lettuce…but I did just have Chipotle last night (which uses cilantro and jalapeño) …so wish me luck!”

Rachel: “It’s killing me! I really want my fruit and lettuce back! However, I don’t want to risk anything like a flare or the potential to flare due to an illness. It is such a scare when you have been in remission for a while!”

Madison: “I have just started to eat lettuce and blueberries again since early June. It’s scary for sure! From what I’ve read, they identified the source of the lettuce issue, and I just had berries yesterday for the first time in almost two months. We’re washing them very well and hoping for the best.”

Laura: “Only eating fresh veggies from my garden and currently sticking to melon and bananas for fresh fruit mostly.”

From the Experts

I wanted to hear from gastroenterologists I know and trust. I asked them how they’re guiding their IBD patients through these uncertain waters and what advice they have for our community about whether we still need to be mindful of what we put on our plates.

“The outbreak of Cyclospora appears related to certain produce, for example, lettuce. While the distribution of these foods seems to be better understood, it’s still reasonable to take precautions in the preparation of certain foods,” says Dr. Miguel Regueiro, MD, Chief of the Digestive Disease Institute (DDI) at Cleveland Clinic. “General guidance for anyone with fresh produce is to wash vegetables and fruit thoroughly with water and practice hand washing with soap and water before and after handling. This is true for IBD patients and those without IBD.”

Dr. Matthew Ciorba, MD, Director of the Inflammatory Bowel Disease Center at Washington University School of Medicine, agrees, saying it isn’t necessary for most people—including most people with IBD—to give up entire categories of foods such as all lettuce, berries, jalapeños, avocados, cilantro, or parsley.

“What makes more sense is to pay attention to the specific products named in an active outbreak or recall, avoid those while the outbreak is ongoing, and relax once the implicated product is off the market. Cyclospora is also seasonal in the U.S. (roughly late spring through summer), so the highest-alert window is limited,” he explains.

One important nuance for our community: if you’re taking immune-suppressing medications, including biologics, immunomodulators, or steroids, it may be reasonable to take additional precautions during an active outbreak. That could mean leaning toward cooked or peeled produce rather than raw leafy greens and soft fruits. This is a personal decision and one worth discussing with your own GI doctor, since recommendations can depend on your medications and individual circumstances.

“Washing helps, but it is not a guarantee. Cyclospora oocysts are tiny and sticky, and they resist the chlorine-based rinses used commercially,” Dr. Ciorba says. “So, scrubbing your salad at home reduces the load but can’t be counted on to make contaminated produce ‘totally safe.’ Cooking is far more reliable than rinsing. So ‘wash thoroughly’ is good advice, just not a force field.”

How to Tell Cyclosporiasis Apart from an IBD Flare

Cyclosporiasis typically causes watery, sometimes explosive, frequent diarrhea, cramping, bloating, nausea, poor appetite, fatigue, weight loss, and sometimes low-grade fever, all symptoms that can be mistaken for an IBD flare.

“Two clues point toward Cyclospora rather than IBD: symptoms often start about a week after an exposure, and they tend to wax and wane, dragging on for weeks if untreated. The biggest red flag is diarrhea that doesn’t improve when you and your doctor step up your usual IBD treatment. That’s a signal to test for something else,” says Dr. Ciorba.

Cyclospora is not picked up by every routine stool test or GI panel. Your doctor may need to order a Cyclospora-specific test. Because the parasite can be shed intermittently, more than one stool sample collected a couple of days apart may improve the chances of detecting it.

“We are now doing this for our patients, and patients can ask their doctors if they plan to order the special stool study,” says Dr. Ciorba.

The practical takeaway: new or persistent diarrhea during outbreak season, especially if it isn’t responding to your usual flare plan, is a reason to talk with your doctor about Cyclospora testing rather than automatically assuming it’s your IBD.

Other Precautions and Warning Signs Worth Knowing

The good news is that when Cyclospora is identified, it is treatable. The standard treatment is an antibiotic called trimethoprim-sulfamethoxazole, with alternatives available for people with a sulfa allergy.

Dr. Uma Mahadevan, MD, Director of the Colitis and Crohn’s Disease Center at the University of California, San Francisco, says fortunately, California has not been hit as hard as some other states.

Dr. Mahadevan recommends:

  • Avoiding recalled products, such as implicated iceberg lettuce.
  • If you are significantly immunosuppressed, such as during a flare or while taking steroids plus a biologic, consider cooked vegetables over raw salads.
  • Being particularly careful with raw salads at restaurants.
  • Washing fruits and vegetables thoroughly under running water and scrubbing produce such as melons.

“For pregnant women, I would use the same cautions as listed above. I would not recommend overly restricting diet. It seems like there is a greater risk in the Great Lakes/Midwest area, so those patients should be more careful. It is a tough one as the tracking of the infections is not great,” Dr. Mahadevan says.

The Bottom Line

If you’re living with IBD, it’s completely understandable to feel uneasy when an intestinal infection like Cyclospora is making headlines. When you’ve worked hard to manage your disease or achieve remission, the last thing you want is an infection that could potentially trigger symptoms or leave you wondering whether you’re experiencing an infection or an IBD flare.

But the experts I spoke with agree on an important point: this doesn’t mean you need to eliminate fresh fruits and vegetables from your diet. Instead, stay informed about active outbreaks and recalls, practice careful food preparation and handwashing, and talk with your gastroenterologist if you develop persistent diarrhea, cramping, or other symptoms that could indicate either an infection or a flare.

For me, that may mean slowly becoming a little less fearful of the produce aisle. I’m not sure I’m ready to dive headfirst into a giant salad just yet, but knowing what the experts are recommending makes me feel much more comfortable making informed decisions rather than letting fear dictate what I eat.

As with so many things in life with IBD, knowledge is power and finding that balance between being cautious and still living your life matters, too.

Eighteen Years of Humira: The Treatment That Helped Me Build a Life, Not Just Manage a Disease

Eighteen years ago, when I was 24 years old, I gave myself my very first Humira injections following a hospitalization for an abscess the size of a tennis ball in my small intestine. The loading dose involved four painful injections, in my GI office. While much of my patient journey tends to be a blur, the day I started Humira is crystal clear in my memory. I remember how I was sitting, what it felt like, the emotions, the tears, the worry about starting a biologic medication, and the desperation to be well.

I don’t have any photos of the day I started on Humira, but this was the month after my loading dose, while still on 60 mg of prednisone.

At the time, I wasn’t thinking about anniversaries or milestones. I wasn’t wondering if I’d still be taking this medication nearly two decades later. I was simply hoping it would work. This week on Lights, Camera, Crohn’s I reflect on what I’ve learned and what I wish I knew all those years ago.

Would life ever be the same?

When you live with Crohn’s disease or ulcerative colitis, hope can sometimes feel like the most powerful prescription of all.

Back then, my disease had already taken so much from me. I had endured three years of on and off flares, hospitalizations, procedures, uncertainty, and the emotional weight that comes with wondering if you’ll ever feel like yourself again. I went from being a perfectly healthy person to being diagnosed with Crohn’s at age 21, put on 22 pills a day, and not knowing what the future would hold.

Humira didn’t cure my Crohn’s disease. There is still no cure, of course. But it gave me something I desperately needed: stability. Over the past 18 years, this injection has quietly stood beside me through nearly every major chapter of my adult life.

It helped me continue my career as a television journalist and keep my IBD private from the public, thanks to the medication being a self-injection. It was there as I found my voice as a patient advocate and launched Lights, Camera, Crohn’s. It was there when I fell in love, got married, and became a mom to three children. It’s been there through pregnancies, postpartum life, sleepless nights, school drop-offs, family vacations, soccer/baseball/basketball games, dance recitals, and countless ordinary moments that aren’t ordinary when you’re living with a chronic illness.

Because chronic illness has a way of making the ordinary feel extraordinary.

My youngest child was ironically born on the anniversary of when I started Humira (July 14th)!

Not all sunshine and rainbows

There have certainly been bumps along the way. People are often surprised to hear that I still had multiple bowel obstructions and hospitalizations prior to my bowel resection surgery in 2015, despite being on Humira. More recently, I experienced firsthand how disruptive a forced switch to a biosimilar in 2024 was before successfully appealing to return to Humira. And like anyone living with inflammatory bowel disease, I still have difficult days, anxious moments, unexpected symptoms, and reminders that remission doesn’t always mean life is symptom-free.

But through it all, Humira has remained the foundation of my treatment and a crutch in my life. I recognize how fortunate I am to still be on the same therapy all this time.

No two journeys look the same

One of the greatest lessons patient advocacy has taught me is that no two IBD journeys look alike.

I know many people who have cycled through medication after medication searching for relief. Reminder: The medications are failing you; you aren’t failing anything. Others have exhausted every available therapy, no fault of their own. Some are preparing to start clinical trials because approved treatments have stopped working. Many have endured multiple surgeries, ostomies, prolonged hospital stays, or years of uncontrolled inflammation despite doing everything right.

Their stories matter just as much as mine.

When I share that one medication has managed my disease for 18 years, I don’t do so to suggest this is typical or attainable for everyone. I share it because it represents what every person living with IBD deserves: a treatment that allows them to live life fully. When I started Humira 18 years ago, I had no idea if it would help control and manage my Crohn’s.

I never take that for granted. I don’t know if a year from now I’ll still be in the same boat or if this is a medication I will be on for the rest of my life. I’ve gotten to the point where it’s difficult to imagine life without it, which can feel a bit daunting.

Science changes lives

Every injection is a reminder that science changes lives.

Years ago, biologic medications transformed what was possible for people like me. Back in 2008, there were only two options for IBD patients (Remicade or Humira), now the landscape for treatment options is so vast. Before these therapies existed, many patients faced repeated surgeries, lengthy hospitalizations, and significantly fewer treatment options. Steroids were the go-to. Today, the landscape continues to evolve with new biologics, biosimilars, small molecules, and research that offers hope to the next generation of patients.

I’ve had a front-row seat to that evolution, not only as a patient but as an advocate and journalist interviewing physicians, researchers, and fellow patients around the world. I’ve learned that medicine isn’t just about controlling inflammation.

It’s about allowing someone to chase a career.

To become a parent.

To celebrate birthdays.

To travel.

To make memories.

To simply say yes to life more often than no.

Final thoughts

For me, Humira became more than a medication. It became a bridge between the life Crohn’s disease tried to take away and the life I was determined to build.

If you’re reading this and your current treatment isn’t working, please don’t lose hope.

I’ve met far too many people who found the right therapy after believing they’d run out of options. Research continues to move forward. New medications continue to emerge. Physicians are learning more every year about how to personalize treatment and truly target our disease. Your next chapter may look very different from the one you’re living in today.

And if you’ve found a treatment that works, whether it’s been six months, six years, or eighteen years, I hope you pause to appreciate what an incredible gift that is. Not because the journey is easy. But feeling well enough to live your life and discover a new normal is something worth celebrating.

Today, I’m incredibly grateful.

Grateful to the physicians who believed in biologic therapy long before it became commonplace. Grateful to researchers who dedicate their careers to continuing to advance IBD care. Grateful to my family for standing beside me through every injection and every flare. And grateful for a medication that has helped me experience so many beautiful moments I once feared Crohn’s disease would steal.

Eighteen years later, I’m still here. Still advocating. Still telling stories. Still raising my family. Still chasing dreams. Still injecting every other week.

And I am still profoundly thankful that this self-injection that I’ve given myself 480 times, has helped me live a life that has been so much bigger than my diagnosis.

The Whiplash of Living with IBD: When Remission Doesn’t Feel Like Remission

Just when you start to trust your body again, inflammatory bowel disease (IBD) has a way of reminding you who’s in charge. Last week, my bloodwork was perfect. My inflammatory markers were normal. By every measurable standard, I was doing well. Remission was validated.

Then Thursday evening hit.

What followed was nearly three days of constant, debilitating abdominal pain that left me glued to the couch with a heating pad, exhausted, frustrated, and questioning everything I thought I knew about my disease. Each night I went to bed and woke up with the same pain. By Sunday morning, out of nowhere, the pain suddenly lifted. As I write this (Monday), I’m back to feeling like myself. Luckily, I had a Humira injection today!

If you’ve lived with Crohn’s disease or ulcerative colitis for any length of time, chances are you’ve experienced this type of whiplash. One day you’re making plans, feeling strong, and celebrating remission. The next, you’re wondering if a flare is brewing, if your medication has stopped working, or if you’re headed back down a road you’ve traveled before. And the hardest part? Sometimes there are no clear answers. This week on Lights, Camera, Crohn’s a look at the behind-the-scenes reality of life with IBD, even when you’re in remission.

When the Tests Say One Thing and Your Body Says Another

One of the most mentally exhausting aspects of IBD is that symptoms and objective disease activity don’t always line up and they often show up unannounced.

You can have:

  • Normal bloodwork
  • Normal fecal calprotectin
  • A recent clear colonoscopy
  • Therapeutic levels of your biologic
  • No evidence of active inflammation

And still experience significant symptoms. That’s not to say the pain isn’t real. It absolutely is. For some people, symptoms can stem from scar tissue, adhesions, visceral hypersensitivity, altered gut motility, stress, infections, dietary triggers, or other gastrointestinal conditions that coexist alongside IBD. Sometimes it’s a temporary viral illness. Sometimes it’s something that remains unexplained.

When I saw my GI today, he wasn’t overly concerned given my recent normal labs and the fact that the symptoms had resolved. The only change he made was moving my surveillance colonoscopy up a few months, from December to August/September, to provide some additional reassurance and make sure nothing is missed.

While I appreciated the precaution, I’ll admit part of me still wonders what caused all of this to happen. I’m left with something many IBD patients know all too well: uncertainty.

The Mental Toll Nobody Talks About

The physical pain was difficult. The mental spiral was challenging. When symptoms appear out of nowhere, it’s easy to immediately jump to worst-case scenarios:

“Is my medication failing?”

“Am I flaring?”

“Did I do something wrong?”

“What if I’m hospitalized this summer with all three kids out of school?”

“Is this the beginning of something bigger?”

Living with a chronic illness means carrying years, sometimes decades, of medical trauma and memories. Next month marks 21 years since my Crohn’s diagnosis, as a veteran patient, I consider myself to be well-versed on not only IBD, but how my symptoms speak to me and when I truly need to listen. Ironically, the month of July has historically been my “worst” month. I’ve had several hospitalizations during that month, so this time of year, I’m always a bit weary.

A bad pain day doesn’t just exist in the present moment. It can instantly transport you back to previous flares, hospitalizations, surgeries, or periods when your disease wasn’t controlled. For many of us, the fear isn’t about today’s symptoms. It’s about what those symptoms might mean tomorrow.

You’re Not Alone

If this experience sounds familiar, you’re in good company.

Many people living with IBD report episodes of abdominal pain or GI symptoms despite being in clinical or even endoscopic remission. In fact, symptom burden remains one of the biggest quality-of-life challenges in the IBD community. We often hear the word “remission” and imagine a finish line.

Since I reached surgical remission in August 2015 following bowel resection surgery (18 inches of my small intestine + appendix), I’ve come to realize the reality is much messier.

Remission doesn’t always mean symptom-free. It doesn’t mean every stomachache disappears or that you may not urgently have to run to the bathroom 5+ times a day. It doesn’t mean you’ll never have a bad day or week. And it certainly doesn’t mean your concerns aren’t valid. I think one of the most challenging parts of remission is that friends and family just think you’re 100% well all the time because the average person thinks remission is perfect, normal health, when in fact it’s not.

How to Navigate the Whiplash

When symptoms strike unexpectedly, here are a few strategies that can help:

Don’t Panic on Day One. Easier said than done, I know.But not every symptom equals flare. Give yourself permission to gather information before jumping to conclusions. I typically allow 2-3 days of symptoms before I reach out to my GI team over the patient Portal.

Reach Out to Your Care Team. Even if symptoms resolve, it’s worth documenting what happened and notifying your GI. Patterns matter. Taking notes whether handwritten or on your phone/computer will help you keep track of the good days vs. the rough days. Oftentimes when we’re in clinic, we tend to gloss over the hard times not because we’re being evasive purposefully, but because our normal isn’t normal, but it becomes our normal. You get what I’m dropping.

Focus on Trends, Not Moments. A few rough days may be less concerning than symptoms that steadily worsen over weeks.

Ask yourself:

  • Is this getting better, worse, or staying the same?
  • Are symptoms recurring?
  • Am I seeing new symptoms?

Trust Your Experience. Normal labs are reassuring, but they don’t invalidate your symptoms.You know your body.You don’t need abnormal test results to justify seeking support.

Keep a Symptom Journal. Documenting pain levels, diet, stress, sleep, and bowel habits can sometimes reveal patterns that aren’t obvious in the moment.

Consider Seeking Help from a GI Psychologist. My GI brought this option up to me in clinic today. Even though we may feel like we have a good handle on it all, living with IBD can be heavier than we realize and managing our anxiety and coping mechanisms with a professional can help us take life on more effortlessly. There are many amazing psychologists who specialize in IBD, many with virtual visits available right at our fingertips.

Remember That Remission Isn’t Fragile. One bad weekend doesn’t erase months or years of progress.This is something I’m reminding myself of right now.

Moving Forward

IBD has taught me many lessons over the past two decades, but one of the hardest is learning to live in the gray area. Not every symptom has an immediate explanation. Not every setback becomes a flare.

And sometimes the most difficult part of this disease isn’t the inflammation itself, it’s the uncertainty. This past weekend was a reminder that even in remission, Crohn’s disease can still mess with your head. But it was also a reminder that symptoms can pass. That normal labs still matter. That one difficult chapter doesn’t automatically predict the rest of the story.

If you’ve ever experienced the whiplash of feeling healthy one day and terrified the next, know this: You’re not overreacting. You’re not imagining it. And you’re certainly not alone.

Hydration and IBD: Why Summer Can Be More Complicated Than It Looks

As temperatures rise, so can the challenges of living with Crohn’s disease and ulcerative colitis. For people with inflammatory bowel disease (IBD), summer heat (and heat in general) isn’t just uncomfortable, it can amplify symptoms, increase dehydration risk, worsen fatigue, and make everyday activities feel far more difficult.

And while everyone is told to “drink more water” during the summer, hydration with IBD is often much more complicated than that. Living in St. Louis, I’m no stranger to extreme heat and humidity!

Between diarrhea, ostomies, inflammation, medication side effects, and nutrient absorption issues, those of us with IBD are already operating at a hydration deficit before stepping outside into 90-degree-plus weather. This week on Lights, Camera, Crohn’s a look at what patients need to know about staying safe, hydrated, and feeling their best during the hottest months of the year.

Why People With IBD Are More Vulnerable to Dehydration

Dehydration happens when your body loses more fluids than it takes in. While that can happen to anyone in the heat, people with IBD face unique risks.

Some of the biggest contributors include:

  • Frequent diarrhea
  • Active inflammation
  • Vomiting
  • Excessive sweating
  • Reduced appetite
  • Short bowel syndrome
  • Ileostomies or J-pouches
  • Certain medications
  • Avoiding fluids due to bathroom anxiety

For patients with Crohn’s disease affecting the small intestine, the body may also struggle to absorb fluids and electrolytes efficiently. Meanwhile, people living with an ostomy can lose significant amounts of sodium and fluids throughout the day, especially in extreme heat. The result? We can become dehydrated faster than we realize.

Signs of Dehydration Can Look Different in IBD

Many symptoms of dehydration overlap with symptoms those with IBD already experience regularly, which can make it harder to recognize when something is wrong.

Common warning signs include:

  • Dizziness or lightheadedness
  • Fatigue or weakness
  • Headaches
  • Muscle cramps
  • Dry mouth
  • Rapid heartbeat
  • Brain fog
  • Dark urine
  • Nausea
  • Increased GI symptoms

For some, dehydration can trigger a vicious cycle: diarrhea leads to fluid loss, dehydration worsens fatigue and weakness, and patients feel too sick to adequately rehydrate.

Why Water Alone May Not Be Enough

One of the biggest misconceptions about hydration is that drinking plain water is always sufficient.

In reality, many IBD patients lose electrolytes (especially sodium and potassium) along with fluids. Drinking large amounts of water without replacing electrolytes can sometimes leave us feeling even worse.

Electrolytes help the body:

  • regulate fluid balance
  • support muscle function
  • maintain blood pressure
  • keep nerves functioning properly

That’s why your gastroenterologist may recommend oral rehydration solutions or electrolyte drinks during flares, illness, travel, heat exposure, or high-output ostomy periods.

Be mindful that some sports drinks contain large amounts of sugar or artificial sweeteners that can aggravate symptoms. I’ve personally had luck with DripDrop and Liquid IV.

Summer Activities Can Add Another Layer of Stress

Summer doesn’t just bring heat; it brings logistical anxiety. Long car rides and flights for fun travel. Outdoor festivals. Pool days. Sporting events. Theme parks. Beach vacations. Going to parks with the kids that don’t have bathrooms. The list goes on and on. I know I feel extremely anxious every time I get on my in-law’s boat and just pray, I don’t run into any bathroom issues!

We often become hyper-aware of where bathrooms are located, whether they’ll have access to safe foods, and how quickly heat exhaustion could escalate symptoms. And unlike others, people with chronic illness often can’t simply “push through” dehydration or fatigue.

Medications Can Complicate Heat Tolerance

Certain medications commonly used in IBD management may affect how patients tolerate heat. Steroids can increase sweating and cause fluid shifts within your body, some medications can cause nausea (Zofran to the rescue!), and fatigue from chronic inflammation can worsen when temperatures rise (especially if you’re anemic)!

Tips for Staying Hydrated With IBD This Summer

While every patient is different, experts often recommend:

Hydrating Before You Feel Thirsty. Thirst can be a late sign of dehydration. Consistent hydration throughout the day is key. I make a point of making a water bottle for myself before I even have breakfast or my coffee each morning. As an IBD mom, we can get so busy taking care of everyone else that we can put eating and drinking on the backburner for ourselves.

Focus on Electrolytes During High-Risk Situations

Especially:

  • outdoor events
  • travel days
  • exercise
  • active flares
  • ostomy output increases
  • stomach illnesses

Carry “Safe” Hydration Options: Many people find certain drinks are easier to tolerate than others. Trial and error matters. What may help someone else, may not sit well with you.

Eat Hydrating Foods: Foods like watermelon, lettuce, celery, zucchini, bell peppers, cucumbers, broth-based soups, smoothies, and fruits can contribute to fluid intake. If you’re currently flaring or have active stricturing disease, talk with a registered dietitian about how to navigate this (ex. Cooking the veggies so they’re tender or chewing to applesauce consistency).

Be Careful with Alcohol and Excess Caffeine: Both can worsen dehydration for some people.

Watch for Heat Exhaustion: If symptoms escalate to severe dizziness, fainting, confusion, rapid heartbeat, or inability to keep fluids down, medical attention may be necessary. Be vigilant and proactive as best you can.

The Emotional Side of Summer With Chronic Illness

There’s also a mental load that comes with navigating summer while living with IBD.

Many of us want to participate fully in vacations, outings, and family activities, but may quietly spend the entire day navigating bathroom access, our energy levels, finding safe foods, and staying on medication schedules. That invisible planning can be exhausting.

And for parents with IBD, summer can feel even more physically demanding. I’m gearing up for that with my three kids! The combination of heat, disrupted routines, increased outdoor activities, and caring for children often leaves little room for rest and recovery. Now that my kids are 9, 7, and almost 5, I know that everyday doesn’t need to be an adventure and that low-key days at home can be just as fun for everyone, too. There’s all this hype about bringing back the 90’s summer. Listen to your body and if it means staying home and having the kids ride their bikes, run through the sprinkler, and have popsicles versus going to parks, pools, and amusement parks—that’s ok. Give yourself grace, your body will thank you!

The Bottom Line

Hydration isn’t just a wellness trend for people with IBD, it’s a critical part of symptom management and overall health and something to discuss with your care team.

As summer temperatures climb, patients may need to be more proactive about fluids, electrolytes, rest, and recognizing the early signs of dehydration. As always, listen to how your body speaks to you through symptoms and do your best to address those needs before they become an acute issue.

Because while summer is often portrayed as carefree, many people living with Crohn’s disease and ulcerative colitis are dealing with an entirely different reality behind the scenes: one that requires constant awareness, preparation, and self-advocacy just to feel well enough to participate.

News You Can Use

Electrolytes and Hydration for IBD: What You Need to Know — Stacey Collins Nutrition

The Connection Between Ulcerative Colitis and Dehydration

Inflammatory bowel disease (IBD): Staying hydrated – AGA GI Patient Center

Dehydration: How to Avoid It If You Have IBD

4 Ways To Avoid Dehydration and Balance Electrolytes With Crohn’s and Colitis | MyCrohnsAndColitisTeam

Inside IBD Pregnancy with a GI Psychologist: What Patients Need to Know

Finding out you’re pregnant can be one of the most profound moments of one’s life; and, if you’re living with Crohn’s disease or ulcerative colitis, that moment is almost immediately followed by a flood of questions that others don’t have to think about. Will my IBD flare? Is my medication safe? What does this mean for my pregnancy? Can I even do this?

The answer to that last question is yes, absolutely, yes. But it takes a team, a plan, and attention to more than just your GI symptoms. As an IBD mom of three, I’ve been in your shoes and know how it feels to bring a life into this world with so many unknowns.

This week on Lights, Camera, Crohn’s we hear from Licensed Clinical Psychologist, Dr. Antonia Repollet, who specializes in gut-brain health at GI Psychology. Dr. Repollet is a fellow Crohnie and a mother. She works with people navigating exactly this intersection every day. She shares what she wants every person with Inflammatory Bowel Disease (IBD) to know about pregnancy: the medical side, the emotional side, and the parts that often get left out of the conversation entirely.

Your Gut Is Already Under Pressure

Pregnancy is a full-body experience. Hormonal shifts in progesterone, estrogen, and cortisol affect mood and energy, and they directly shape how the gut functions. Progesterone relaxes smooth muscle, slowing the movement of food through the digestive tract (Alqudah et al., 2022). Estrogen influences gut permeability and the composition of the gut microbiome (Chen et al., 2025). Cortisol, the body’s primary stress hormone, can heighten GI sensitivity and drive inflammation (Cherpak, 2019). Together, these hormonal changes can increase bloating, reflux, and constipation even in people without IBD. Add a growing uterus physically displacing digestive organs, and it’s no wonder the gut feels unsettled!

Whether you’re a first-time mom-to-be or someone who has had several children, we know how complicated it can feel to navigate these changes in your body on top of IBD. It’s not unusual to feel a bit overwhelmed.

“For someone with Crohn’s or ulcerative colitis, these changes land on an already-sensitive system, and the hormonal picture matters more than people often realize. Hormones are among the key messengers of the gut-brain axis, the two-way communication highway between the digestive tract and the nervous system,” explain Dr. Repollet. “During pregnancy, when hormone levels are shifting, this axis is working overtime, and stress often amplifies this further. For example, anxiety about your health, your pregnancy, your body, your medications: all of it feeds back into the gut through hormonal and neurological pathways, and the gut sends it right back to the brain. Thus, pregnancy can disrupt this loop.”

Why Remission Before Conception Matters

Here’s something important: research consistently shows that the best predictor of IBD staying stable during pregnancy is whether disease was well-controlled at the time of conception (Abhyankar, 2013). Studies have found that approximately 66% of IBD patients who conceive during active disease experience continuing or worsening symptoms throughout pregnancy (Hashash & Kane, 2015).

Dr. Repollet says, “Remission going in doesn’t guarantee smooth sailing, but it does dramatically improve the odds for both the pregnant person and the developing fetus.”

Looking back, I’m grateful for the timing of my bowel resection surgery when I was engaged, because it put me into surgical remission, and helped prep my body for pregnancy after I got married. Prior to surgery, I had never heard the word “remission” from my gastroenterologist. With IBD pregnancies, this is where the “rule of thirds” comes in. One third of women experience an improvement of IBD symptoms, one third stay the same, and one third see an uptick.

Active disease during pregnancy is associated with increased risks of miscarriage, preterm birth, low birth weight, and other complications (Boyd et al., 2015). This is why the conversation with your gastroenterologist needs to happen before you start trying to conceive, not after a positive pregnancy test.

The Medication Questions

Please don’t stop without talking to your doctors!

“One of the most common things I hear from IBD patients considering pregnancy is some version of: “I thought I should stop my medication just to be safe.” The instinct makes complete sense, because you want to protect your pregnancy. But stopping IBD medication without medical guidance can put you and your fetus at greater risk by triggering a flare,” Dr. Repollet advises.

Many IBD medications, including biologics like infliximab, adalimumab, and certolizumab, are considered safe during pregnancy and are recommended to maintain remission (Mahadevan et al., 2019; Peifer, 2024). Some, like methotrexate, do need to be stopped well before conception, and this applies regardless of which reproductive organs you have (Peifer, 2024). This is important for both partners, as medication safety around conception is a conversation for anyone planning to conceive, regardless of gender. Your GI and obstetrician (OB) should be making these decisions together, with your input.

Build Your Team Before You Need Them

A whole-person approach to pregnancy with IBD means your care team should include more than just your GI and OB. Depending on your history, you may also benefit from a maternal-fetal medicine specialist (an OB with advanced training in high-risk pregnancies), a dietitian who understands IBD and prenatal nutrition, a lactation consultant familiar with chronic illness, and a mental health provider who specializes in the gut-brain connection. According to findings from the Global Consensus on IBD and Pregnancy, all IBD pregnancies are deemed “high risk.”

Dr. Repollet tells me the last one matters more than people realize.

The Part That Doesn’t Get Talked About Enough: Your Mental Health

People with IBD are two to three times more likely to experience anxiety and depression than people without (Neuendorf et al., 2016). Rates of anxiety in IBD hover around 32%, and depression around 25% (Barberio et al., 2021). These numbers don’t go down during pregnancy. If anything, the uncertainty, the body changes, the fear of flares, and the weight of managing a chronic illness while growing a new life can make them go up.

“And here’s what’s easy to overlook: your emotional state is not separate from your physical symptoms. Stress releases hormones that increase inflammation. Anxiety heightens gut sensitivity. When you’re scared that every cramp might be a flare, that fear itself can worsen symptoms. The mind and the gut are in constant conversation,” says Dr. Repollet.

This is why mental health support isn’t a “nice to have” treatment during pregnancy with IBD and should be part of the medical plan.

Evidence-based approaches like Cognitive Behavioral Therapy (CBT) for GI conditions (CBT for GI) (Gracie et al., 2017) and gut-directed hypnotherapy (Keefer et al., 2013) have been shown to reduce GI symptoms, lower flare frequency, and improve quality of life in IBD patients. These approaches are safe during pregnancy, non-pharmacological, and can be genuinely life-changing for anyone who feels like they’re white-knuckling through their pregnancy.

A Story That Might Sound Familiar

“One of my patients (I’ll call her “Alex”) was 12 weeks pregnant and living with Crohn’s. Inflammation was well-controlled, but daily abdominal cramping and pain, diarrhea, and racing thoughts about whether symptoms were affecting the pregnancy had taken over. The response from providers (e.g., “It’s just pregnancy hormones.”) left Alex feeling dismissed and alone.”

With gut-brain therapy, Alex learned to track symptom patterns, practice diaphragmatic breathing, and use clinical hypnosis to interrupt the anticipatory anxiety that was amplifying physical symptoms.

Dr. Repollet says, “Over eight weeks, symptoms decreased, sleep improved, and (maybe most importantly) there was a renewed trust in the body’s signals. Feeling prepared going into delivery and postpartum was something Alex hadn’t expected to feel, but did. This is a reminder that emotional care is physical care. They are not separate things.”

What to Watch For and When to Reach Out

Consider seeking mental health support if you are:

  • Struggling to eat or sleep due to GI symptoms or anxiety
  • Experiencing GI symptoms that feel emotionally overwhelming, are hard to separate from anxiety, or seem to worsen with stress
  • Experiencing distress (whether related to your IBD, your pregnancy, or both) that is interfering with daily life
  • Having fears about flares, delivery, or being a high-risk patient that feel consuming
  • Dealing with resurfacing trauma from prior pregnancy loss, difficult medical experiences, or a complicated diagnosis journey
  • Simply wanting a space to process this enormous thing you are navigating

Please know that you don’t have to be in crisis to deserve support.

The Postpartum Chapter

Pregnancy often gets most of the attention, but postpartum is its own significant transition for people with IBD.

“Hormonal shifts after delivery, sleep disruption, feeding decisions in the context of your medication regimen, and the emotional adjustment to new parenthood can all influence disease activity. Having a plan for the postpartum period, including who on your care team you’ll check in with and how, should be part of a complete prenatal plan,” explains Dr. Repollet.

I remember during all my pregnancies how fearful I was about how I would feel after delivery. By staying on my medication (Humira), it helped keep symptoms at bay not only during my pregnancies, but also after my scheduled c-sections. I required a short burst of steroids after my second child was born, but luckily never experienced a full-blown flare.

It can be easy to place all your focus on your baby but be mindful of how your body is speaking to you through symptoms so you can communicate this directly to your care team, before you’re dealing with an acute flare. Trust that by sharing what you’re going through you’re doing what is not only best for yourself, but what’s best for your family.

You Deserve Coordinated, Whole-Person Care

Pregnancy with Crohn’s or ulcerative colitis is possible. Many people do it every year with the right support, effective communication between providers, and attention to both the physical and emotional layers of what they are carrying.

“At GI Psychology, we specialize in helping people with IBD and other GI conditions navigate exactly these kinds of life transitions. Our clinicians are trained in gut-brain therapies including CBT-GI and gut-directed hypnotherapy, and we work via telehealth across all 50 states + Washington D.C., so support is accessible wherever you are. We also offer an 8-week virtual IBD Psychotherapy Group for adults living with Crohn’s and ulcerative colitis, designed to provide evidence-based tools alongside community with people who truly get it,” says Dr. Repollet.

If you’re planning for pregnancy, currently pregnant, or navigating the postpartum period with IBD, you don’t have to figure it out alone.

Learn More About GI Psychology:

Participate in IBD Pregnancy Research

References

Abhyankar, A., Ham, M., & Moss, A. C. (2013). Meta-analysis: the impact of disease activity at conception on disease activity during pregnancy in patients with inflammatory bowel disease. Alimentary pharmacology & therapeutics, 38(5), 460–466.

Alqudah, M., Al-Shboul, O., Al Dwairi, A., Al-U´Datt, D. G., & Alqudah, A. (2022). Progesterone inhibitory role on gastrointestinal motility. Physiological research, 71(2), 193–198.

Barberio, B., Zamani, M., Black, C. J., Savarino, E. V., & Ford, A. C. (2021). Prevalence of symptoms of anxiety and depression in patients with inflammatory bowel disease: a systematic review and meta-analysis. The lancet. Gastroenterology & hepatology, 6(5), 359–370.

Boyd, H. A., Basit, S., Harpsøe, M. C., Wohlfahrt, J., & Jess, T. (2015). Inflammatory bowel disease and risk of adverse pregnancy outcomes. PloS One, 10(6), e0129567.

Chen, M., Wang, J., Yang, Y., He, Y., & Li, L. (2025). The interplay of estrogen, gut microbiome, and bone immunity in osteoporosis. Cell communication and signaling : CCS, 23(1), 516.

Cherpak C. E. (2019). Mindful Eating: A Review Of How The Stress-Digestion-Mindfulness Triad May Modulate And Improve Gastrointestinal And Digestive Function. Integrative medicine (Encinitas, Calif.), 18(4), 48–53.

Gracie, D. J., Irvine, A. J., Sood, R., Mikocka-Walus, A., Hamlin, P. J., & Ford, A. C. (2017). Effect of psychological therapy on disease activity, psychological comorbidity, and quality of life in inflammatory bowel disease: a systematic review and meta-analysis. The Lancet Gastroenterology & Hepatology, 2(3), 189–199.

Hashash, J. G., & Kane, S. (2015). Pregnancy and inflammatory bowel disease. Gastroenterology & Hepatology, 11(2), 96–102.

Keefer, L., Taft, T. H., Kiebles, J. L., Martinovich, Z., Barrett, T. A., & Palsson, O. S. (2013). Gut-directed hypnotherapy significantly augments clinical remission in quiescent ulcerative colitis. Alimentary Pharmacology & Therapeutics, 38(7), 761–771.

Mahadevan, U., Robinson, C., Bernasko, N., Boland, B., Chambers, C., Dubinsky, M., … & Kane, S. (2019). Inflammatory bowel disease in pregnancy clinical care pathway: A report from the American Gastroenterological Association IBD Parenthood Project Working Group. Gastroenterology, 156(5), 1508–1524.

Neuendorf, R., Harding, A., Stello, N., Hanes, D., & Wahbeh, H. (2016). Depression and anxiety in patients with Inflammatory Bowel Disease: A systematic review. Journal of Psychosomatic Research, 87, 70–80.

Peifer, R. (2024, January 26). IBD and pregnancy: What you need to know. Crohn’s & Colitis Foundation. https://www.crohnscolitisfoundation.org/blog/ibd-and-pregnancy-what-you-need-to-know