Healthcare for those with IBD in the LGBTQIA+ community looks a bit different. IBD often affects young adults, many of whom are just beginning to become comfortable in their sexuality and gender identity. This can be especially hard for LGBTQIA+ folks, who have already had to work through stigma and discrimination, and then have the additional burden of a new diagnosis of IBD. The LGBTQIA+ community is a big, diverse group of people and each person is unique.
This Pride Month on Lights, Camera, Crohn’s a close look at the most common concerns and patient experiences, helpful guidance to support the LGBTQIA+ community, tips for finding and communicating with your care team about your sexual orientation, and exciting news about how the University of California-San Francisco Medical Center is working to provide a safe space for patients.
You may not be aware that IBD symptoms can affect sexual function, colectomy and J-pouch surgeries can impact receptive anal sex, transgender people with active pelvic inflammation may have issues undergoing bottom surgery as part of gender affirming, and much more. The mere act of communicating with your care team can be an overwhelming and daunting experience.
Coming soon: An IBD Clinic specifically serving the LGBTQIA+community
Dr. Justin Field, MD, University of California, San Francisco, is passionate about supporting IBD patients who are part of the LGBTQIA+ community, as a gay man himself, he’s on the forefront of making the UCSF Medical Center one of the first in the country to have an IBD clinic geared towards treating IBD in the LGBTQIA+ community.
Currently there are two other clinics in the U.S. that specialize in treating LGBTQIA+ IBD patients, the Mayo Clinic in Rochester, Minnesota, run by Dr. Victor Chedid and Capital Digestive Care in Washington D.C. Dr. Jessica Korman, MD, specializes in LGBTQIA+ patients with all GI issues, including IBD. She also does anal cancer screenings.
“The clinic at UCSF is set to open this Fall and will offer comprehensive IBD care to anyone who is interested and will be a safe and inclusive environment where everyone involved in patient care will have special training in the unique needs and concerns of LGBTQIA+ patients. The clinic will offer screening for anal cancer, which is increased in patients with IBD, in men who have sex with men (MSM), patients living with HIV, those who have receptive anal sex, patients with prior cervical or vaginal cancers, and in those on long term immunosuppression,” said Dr. Field.
The clinic will also offer coordination between Gastroenterology and other specialties such as Colorectal Surgery and Transgender Care. For people who are interested, UCSF will offer the ability to participate in research that adds to the knowledge base about the unique needs of LGBTQIA+ people who have IBD.
“This clinic came from the realization that LGBTQIA+ folks often have unique needs that aren’t always addressed in other traditional settings. Also, patients often feel hesitant to fully discuss their sexual orientation and gender identity with healthcare providers due to fear of stigmatization or being treated differently. I wanted to create a safe space where patients can feel comfortable and empowered to be open with their healthcare team, and where they can receive the relevant expertise to meet their needs,” says Dr. Field.
Because LGBTQIA+ people have so often been left out of research (by not including sexual and gender diverse identities in research studies), having a dedicated LGBTQIA+ IBD clinic helps improve medical knowledge about how IBD affects LGBTQIA+ individuals, by allowing more patients to choose to participate in research.
“I have received incredible support from the University of California – San Francisco to start the clinic. The clinic continues to be a work in progress, and I’m continuing to seek out a wide variety of patient and provider input to ensure the clinic effectively serves the community,” explained Dr. Field.
Living with the stigma of IBD and being LGBTQIA+
CC Springhetti was diagnosed with ulcerative colitis when she was 12. She’s has an ileostomy and says sometimes she jokes that the universe keeps punishing her with stigmatized labels.
“I’m a woman, gay, AND I have a disability now?! In all seriousness, I try to view all my labels as gifts. They each make me who I am, and though it’s taken me some time to get to this point, I’ve learned to be proud of who I am and what I have. I know that sharing my life helps normalize and de-stigmatize IBD and queerness. Representation is so important, and being able to show up exactly as I am to show that you can be queer with IBD and still live a full life is a precious gift I have been given.”
CC and her wife share their life online and have been the target of extreme hate and prejudice. They’re received hundreds of threats.
“It can be draining to keep up with the amount of comment/message removal needed to keep our internet pages safe for young viewers and it’s incredibly disheartening on a regular basis. I sometimes give myself several days away from social media just to clear my mind – the hate and threats cause so much stress, and it can be difficult to separate internet life from real life. Those of us with IBD know how stress can affect our bodies, so this is a constant issue I am still working through every day.”
CC says when she’s admitted to the hospital, she’s dealt with the stress of her partner not being taken seriously of being allowed to make big decisions during emergency situations.
“We live in the south in the United States – it sometimes can be difficult for us to know who is able to separate their work life from their personal beliefs. When you’re in a hospital setting there really is no knowing, and this is something we always try to stay vigilant about and are very communicative with our care teams about what our needs and wishes are.”
The impact of IBD on sexual function
Brad Levy started to experience IBD symptoms in January 2022. He was diagnosed with Crohn’s the following month. His dad has ulcerative colitis, which sped up the diagnosis process significantly. Along with having Crohn’s Brad is a married gay man and a dad. Shortly after his diagnosis, Brad started to worry about how his disease would impact not only his life in general, but his intimacy with his husband.
Dr. Field explains why IBD can have such a big impact on the sex lives of LGBTQIA+ people.
“Receptive anal sex is an important part of sexuality for both LGBTQIA+ and non-LGBTQIA+ people but is especially important in this community. IBD often involves inflammation around the anus or in the rectum and this can make sex difficult or painful. For transgender folks, active inflammation in the pelvic area can affect their ability to undergo gender affirming surgery, so it’s especially important to address any pelvic inflammation.”
Brad says, “There is some shared stigma around IBD and being a gay receptive partner. Specifically, within the gay community there can often be some unrealistic expectations about how “cleaned” out you should be before engaging in receptive sex. The reality is though that shit happens, quite literally. The shame and judgment around a critical and natural bodily function such as elimination needs to end.”
Overcoming the fear of judgement and finding a care team you can openly communicate with
Talking about sex, sexual orientation, and gender identity can be scary as a patient, because often those in the LGBTQIA+ community have prior experiences telling people about their sexual orientation or gender identity which may have been met with rejection or judgement.
“Historically, the medical community has treated the LGBTQIA+ community poorly and considered LGBTQIA+ identities as pathologic. This historical context is important because there are very logical reasons patients aren’t comfortable talking about this with their doctors. In some areas, it truly isn’t safe for LGBTQIA+ individuals, especially the trans and non-binary community,” said Dr. Field.
Now more than ever, there are lots of affirming healthcare providers. Individual providers and practices can take measures to ensure a LGBTQIA+-friendly healthcare setting (For example, by following these recommendations put forward by the American Medical Association.
Demonstrating to patients that they are in a safe space to talk about their sexuality or gender identity can go a long way in facilitating sensitive conversations. Providers can seek additional education on sexual health in gender and sexual minority patients, so that they feel more capable of addressing the needs of the IBD community.
Dr. Fields says, “Providers should know it’s ok to make mistakes when it comes to addressing diverse sexual orientations and gender identities. What’s most important is that we acknowledge the mistake, apologize, and move on.”
CC is a firm believer that your doctor should be someone you never lie to. Honesty will help you navigate problems and solutions in a sensitive manner.
“I remember I was nervous to share with my gastroenterologist that I was gay. Whenever I referred to my partner and he responded back to me with questions or comments, he would always say “boyfriend” or refer to my partner as “he”. It felt scary to correct him (especially after all of these years) so I just didn’t. I was nervous it would embarrass him or make him feel silly, and I always want to protect people from that when I don’t feel they deserve it,” she said.
Then one day, CC was at a different doctor and she made sure to share to share that she was married to a woman and had been in a same-sex relationship exclusively for a number of years.
“I had this doctor add this information to the top of my medical chart. Now when I go to any doctor and they pull up my chart, they can see that I’m gay and can provide sensitivity to me in that way when speaking to me.”
Seeking out LGBTQIA+ affirming healthcare providers
Patients can feel empowered to seek out LGBTQIA+ affirming healthcare providers like Dr. Field.
Find providers with a special interest in LGBTQIA+ health. Patients can also look at lists such as the LGBTQIA+ Healthcare Directory.
Patients should feel empowered to be their own advocate. It’s a patient’s right to have their sexual health needs met and to receive care that is affirming of all genders.
Patients can bring a list of items that they want to discuss to a visit, and it’s best to mention those at the beginning of a visit to help set the agenda. It’s also always ok to seek a second opinion if you feel like your provider hasn’t gotten a satisfactory answer to your questions or if you feel another provider perspective would be helpful.
“Having a GI doctor you trust and feel comfortable enough to discuss your sexuality with is so important. When having receptive anal sex, things happen sometimes, such as tears, and you want to be able to talk with your GI doc openly so you can triage whether something is related to your IBD or not,” said Brad.
Additional IBD screenings for the LGBTQIA+ community
According to Dr. Field, men who have sex with men that are living with HIV should be screened for anal cancer.
“Other at-risk groups for anal cancer are men who have sex with men over age 40, people with prior cervical or vulvovaginal squamous cell cancer, patients that have receptive anal intercourse, and those with multiple sexual partners,” he said.
The risk of anal cancer is increased in patients with IBD, and doctors are continuing to learn more about this risk through ongoing research studies. Screening for anal cancer is with a rectal exam and a swab of the anal canal, called an anal pap smear. If these are abnormal, they must be followed by a procedure called a High Resolution Anoscopy, which is the best test for detecting anal cancer and its precursor.
“Anal cancer is caused by HPV, and there is a vaccine against HPV. Anybody who has not received the HPV vaccine, regardless of age or gender, can talk to their doctor about HPV vaccination. Currently, the CDC recommends HPV vaccination regardless of gender up to age 26 to prevent HPV related cancers, and the vaccine can be given up to age 45 on a case-by-case basis, if it’s felt it would benefit,” said Dr. Field.
Brad lives in the Chicago suburbs. As a result, he says the attitudes towards the LGBTQIA+ community are generally that of acceptance and love.
“I have always had a gay primary care physician because I want to make sure I am comfortable discussing any health issues with them. My GI is also aware of my sexuality, and we’ve had candid conversations about what intimacy looks like during a flare and what vaccines I should consider. For example, my GI recommended I receive the Gardasil HPV vaccine based on my sexuality and increased risk.”
Other cancer screenings to keep in mind are Colon cancer screening for all patients, Cervical cancer screening for patients who have a cervix, and skin cancer screening for all patients who have received immunomodulators, small molecules, and biologics.
“Much of the existing research on things like sexual health and surgery in IBD didn’t ask participants about their gender identity, sexual orientation, or typical sexual practices. This can leave both patients and providers at a loss for answers to sexual concerns,” said Dr. Field.
More and more, sexuality and gender identity are being included in research studies, and this will paint a clearer picture about how many LGBTQIA+ people are impacted by IBD, and how the course or experience of IBD is similar or different between LGBTQIA+ and non-LGBTQIA+ individuals.
Juggling a love life and fatherhood with IBD
Brad and his husband have been together for 13 years, so luckily communicating about his IBD has come easy.
“But I can recognize for others, in shorter relationships or dating, this isn’t always the case. All I can recommend is transparency and having a partner you feel you can be honest with. There will be times (such as a flare) where intimacy will look different. You want your partner to know that it’s because of your IBD activity and not because of them or some issue with your relationship,” said Brad.
As the years go by, Brad says the more authentically he lives, the happier he is. For him, that means living as an out gay man who has an amazing family. It also means living with Crohn’s disease, Anxiety, and Depression. Brad is open about his health struggles with family, friends, and close colleagues/bosses. He says transparency has served him and his relationships well.
As an IBD Dad to a five-year-old girl who is on the spectrum, Brad says focusing on self-care to help manage stress makes all the difference.
“Focusing on self-care enables me to show up as an active and healthy dad. My self-care includes hopping on my Peloton (#ThatDadBrad for the Peloton readers), bi-weekly therapy, monthly massages, and getting my nails professionally done. While not all these activities are for everyone, I strongly encourage folks to pour into their own cup or put on their own mask first. You can’t fully show up for you me kids and your family if you’re not grounded and the healthiest version of yourself, whatever that looks like for you.”
Brad wants to reiterate that his experience as a cis gay white man is “only one voice (and a privileged one at that) out of the vast and vibrant LGBTQIA+ community.” You can connect with Brad on Instagram at: @bssl.
CC says there are a number of ways our IBD community can show support. You can follow CC on Instagram at: @ccspringhetti.
“We’re all human, and I would encourage the IBD community just like I would encourage any community to show your support during Pride month and all year long through any means appropriate for your situation. Support LGBTQIA+ owned businesses, hang a Pride/Progress flag, post your support on social media, or even attend your local Pride events! If you’re ever looking to support a good LGBTQIA+ charity, I always suggest The Trevor Project.”
Certain roadblocks and issues that are a concern to one person, may not bother another. Just like every IBD patient, regardless of sexuality, the experience is unique. We all need to feel seen, understood, and respected, as one united IBD family.
Dr. Field’s views are his own and do not represent the University of California San Francisco.
July marks 15 years since I started my journey taking a biologic injection to manage and treat my Crohn’s disease. Since that time, I’ve had routine “safety labs” every 3-6 months, depending on my gastroenterologist. You may be familiar with safety labs, or you may wonder what I’m talking about. I’ve been seeing my current GI for almost 8 years, and she’s adamant that I get labs every 3 months to make sure my disease is closely monitored. If I fail to get labs every 3 months, per her orders, my prescription for Humira is unable to be filled by my specialty pharmacy.
I ran a poll on Instagram and asked, “If you are on a biologic, do you get safety labs every 3 months?” Of the 175 people who responded, 41% said “yes”, 36% said “no”, and 23% had no idea what safety labs are. This week on Lights, Camera, Crohn’s we take a closer look at the reasoning and purpose behind safety labs, and we hear from esteemed and world-renowned gastroenterologists Dr. David Rubin, MD, Section Chief of Gastroenterology, Hepatology, and Nutrition at the University of Chicago Medicine and Dr. Miguel Regueiro, MD, Chair, Digestive Disease and Surgery Institute, Professor in the Department of Medicine, Cleveland Clinic.
What is a safety lab?
Safety labs are to ensure that patients are not developing a complication from a medication that they may not feel.
“For example, kidney or liver function tests that may show an abnormality before a patient has damage to those organs, or problems. Or a white blood count that lowers in a patient on certain immunosuppressive therapy – something they may not “feel” until the immune system gets low enough to develop an infection,” explained Dr. Regueiro.
The periodicity of labs for “safety” are often taken from the clinical trial designs, rather than the likelihood that something is going to change within that period of time.
“Routine labs while on therapies for IBD is important and patients can and should keep track and ask for them at least twice a year for most of our therapies. For many of these, there are gaps in our understanding whether the interval (every 3 months for example) is the right one or makes a difference. We certainly know it takes time for patients to do this and costs money too. Some of my colleagues withhold refills as a safeguard to make sure patients get their labs. This may be more punitive than necessary, but it is one way to make sure this is getting done,” said Dr. Rubin.
When I get my labs done every 3 months the following blood tests are ordered by my GI:
CBC w/Auto Differential
Hepatic Function Panel (Liver Panel)
Vitamin D 25 Hydroxy (I am deficient, so we keep a close eye on this)
If there is concern about inflammation or anemia, then my GI also adds:
Sedimentation Rate, automated
High Sensitivity CRP
Iron Profile with IBC + Ferritin
In the past, if there’s concern about my response to Humira we do a “trough level” to see if I’ve built up antibodies to my therapy and to measure how much medication remains in my body right before I am scheduled to do another injection.
It’s important to know, since I started seeing my GI two months after my bowel resection surgery in 2015, I have been in remission. So, the concern about inflammation and needing to take fecal calprotectin tests has been few and far between. When we were in the middle of the pandemic, rather than an annual colonoscopy, my doctor had me do a fecal calprotectin test at home to limit my risk of being exposed to germs in a hospital setting while my disease was well-managed.
“We recommend certain labs on patients taking IBD medications. Each medication will require a different safety lab monitoring strategy. Some brief examples, for mesalamine, checking kidney function tests within a couple of months of starting a medication and then once or twice a year. For thiopurines (6MP and Imuran) and methotrexate more frequent blood work initially, e.g., complete blood count and liver function tests weekly to every other week in the first two months after starting and then every few months thereafter,” said Dr. Regueiro.
Safety labs as a disease monitoring strategy
Generally, safety labs are done for medical health reasons to make sure that everything is ok while taking the medication.
“Safety labs are “driven” by the physician or provider caring for the patient. The insurance company may require certain labs before starting or continuing a medication. For example, a tuberculosis (blood) test before starting an anti-TNF medication and then yearly while a patient is on the medication. Otherwise, the insurance company usually does not require safety labs for medication approval or continuation. Each case is different, and each insurance company is different,” said Dr. Regueiro.
“More important than pharma-drive lab recommendations—is that every patient should have a customized strategy to monitor their disease stability to detect relapses before there are clinical consequences. This is my new take home message for most of my lectures- in addition to “treating to a target” we must have “disease monitoring” as something that every patient has as part of their care,” said Dr. Rubin.
Chronic diseases like IBD tend to “drift away from control”, so it is good to keep an eye on things and this enables proactive preventive care.
Getting my safety labs in the thick of the pandemic
“For low-risk patients, that might be once a year, but for those who are on advanced therapies (biologics and the novel targeted small molecules), they likely need this approach more frequently. It is true that “knowledge is power,” and knowing that the disease has activated enables much better care,” explained Dr Rubin.
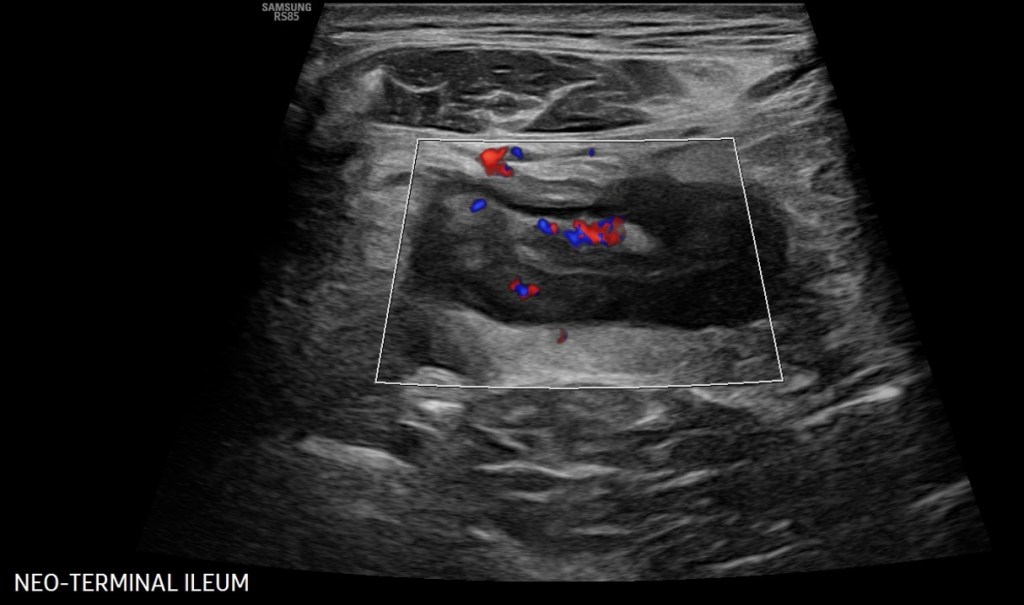
Disease monitoring may involve blood or stool markers (calprotectin) or depending on where you live, intestinal ultrasound. Colonoscopy or CT scan/MRI is also recommended. Dr. Rubin tells me the key is identifying what is appropriately benchmarked and reliable and which approach is feasible and makes the most sense for the patient.
Why the onus is often on us
As you can imagine, 3 months comes quickly. If you’re like me, I see my GI in clinic two times a year (every 6 months). When I was pregnant, she would see me in the office every 3 months. Given that I see her twice a year, that checks off two of my four lab visits. As an IBD mom juggling life with three young kids, time can often slip away. I’ve found I must alert my nurse and GI about when and where they need to submit lab orders so I can take care of them the other two times a year at a Quest or LabCorp nearby. In the past there have been a few times where I’ve dropped the ball.
Coordinating life with chronic illness can truly feel like a full-time job. Just this week I spent an hour on the phone with my specialty pharmacy trying to organize my next shipment because there was an issue with my patient savings card. At the time, all three of my kids were running around like little banshees, yelling, and making it hard for me to hear the phone representatives. At one point, I had to lock myself in my laundry room. These aren’t calls that can wait. Patients need their medication; we can’t just hang up and re-visit the snafu at another time because it can mean we receive our biologic shipment late. This is one small example—of a behind-the-scenes look at life with IBD as a mom.
While getting labs four times a year may not seem like a lot, it does involve planning, time, and coordination for patients. My kids have joined me countless times in the stroller as I get labs done. Then, reading the results on the Patient Portal and seeing certain results too low or too high can cause anxiety and added stress. It’s a never-ending cycle.
Talking with your care team
If you’re only getting labs done once or twice a year, it may be worth having a conversation with your GI about the reasoning why and what you feel most comfortable with. Your care is not a one-way street. If you feel like you need a more hands-on approach, talk about this with your doctor. In talking with fellow IBD patients, many who are on infusions every 8 weeks, tell me they get labs every 16 weeks.
If you’re only getting labs done once a year, Dr. Regueiro says you don’t necessarily need to be alarmed.
“For a patient who has been on a medication like mesalamine or a TNF inhibitor for a long time, in remission, and doing well without prior lab test abnormality, once per year lab testing may be ok. However, a patient on Imuran or 6MP may need lab testing more frequently.”
As a veteran patient, who was diagnosed with Crohn’s nearly 18 years ago, safety labs have become part of how I manage my IBD. While annoying at times, these labs also give me a sense of relief. One final recommendation I have—don’t try and get labs done before or after your colonoscopy—I’ve tried this twice to try and kill two birds with one stone, and with being so dehydrated, it was not a pleasant experience. Being closely monitored through safety labs takes away much of the stress and worry that can come because of being on a biologic, and the possible side effects that can happen now and into the future.
A special thank you to Dr. David Rubin and Dr. Miguel Regueiro who took the time to offer their expertise for this article on the heels of Digestive Disease Week (a HUGE conference they both actively participate and present at). Having their insight on topics like this that matter to patients means so much.
One in three people with inflammatory bowel disease (IBD) has iron deficient anemia. This common, but often underrecognized and undertreated extra-intestinal manifestation impacts so many of us. You may wonder why. The reason is three-fold.
First being that long-term irritation and inflammation in our intestines can interfere with our body’s ability to use and absorb vitamins and minerals properly. When our intestines don’t absorb enough iron, folate, B12 and other nutrients, our bodies are unable to create more red blood cells. Those with IBD are also at risk for blood loss—both visible and microscopic and we often don’t eat as much iron-rich foods. So, what can we do to boost our reserves and increase our energy? How as patients can we better advocate for ourselves to stay on top of screenings? This week on Lights, Camera, Crohn’s an in-depth look at anemia in both adult and pediatric patients and input from Dr. Alka Goyal, who recently co-authored a major study on pediatric anemia.
Symptoms to watch out for
As someone who was diagnosed with Crohn’s disease in July 2005, I experienced anemia long before my diagnosis. I often wonder if my anemia was a warning sign of the larger issue, my IBD. In fourth grade, I fainted on the teacher’s desk while waiting for her to look at an assignment. Throughout my life I’ve experienced light-headedness, weakness, black outs, and extreme fatigue. My symptoms were never addressed prior to finding out I had Crohn’s. A simple lab test would have shown all along. When I was diagnosed with IBD and hospitalized my hemoglobin was a 7. To give you an idea, people are given blood transfusions once they drop to 7 (or below). Throughout my 18 years with IBD, my hemoglobin was rarely ever in “double digits”—and I took over the counter iron supplements for years.
Once I had my bowel resection surgery in 2015, my iron panel slowly started to improve. It takes time. Last month, I had my “highest” hemoglobin since diagnosis, ever—12.9 (which really isn’t that high, but I’ll take it!). It’s difficult to put the fatigue caused by anemia into words, but you can physically tell such a difference when your iron panel is where it needs to be.
When you have anemia, you have less blood carrying oxygen throughout your body. The most common symptom is feeling tired or lethargic. Other symptoms include dizziness, headaches, feeling cold, pale skin, being irritable, and shortness of breath. Not everyone experiences symptoms, so it’s important as a patient to speak with your GI about making sure that when you get labs, an iron panel is part of the workup.
Screening for Anemia
Anemia screening is driven by patient symptoms and/or a care provider’s recognition of lab abnormalities. It’s important to note that anemia is not *just* a low hemoglobin, all the lab figures matter. With iron deficiency anemia (IDA), red blood cells are smaller and paler in color. Your hematocrit, hemoglobin, and ferritin go hand in hand. Ferritin helps store iron in your body. Iron deficiency anemia is the most common type of anemia and is caused by a lack of iron-rich foods, malabsorption, and blood loss.
Other types of anemia include vitamin deficiency anemia and anemia of chronic disease. Vitamin deficiency anemia is a result of poor absorption of folic acid and vitamin B12. My GI has me on daily folic acid. Luckily my B12 has never been an issue, but it’s worth a discussion with your care team. If you’re deficient, you can receive B12 injections. Diseases such as IBD and other inflammatory diseases can interfere with the production of red blood cells. When this happens anemia can often only be resolved once remission is reached or inflammation calms down.
In order to address the need for improved patient management, the Crohn’s and Colitis Foundation created the Anemia Care Pathway (ACP) to standardize clinical management of anemia in IBD. This pathway helps to identify high-risk patients so that timely intervention and care can be provided. The hope is that this pathway will improve patient outcomes and our quality of life. Patients are assessed based on the severity of their anemia and iron stores to determine the type of iron therapy (intra-venous or oral) that is best suited.
The importance of accurately diagnosing the type of anemia you have
According to the PubMed study, Management of Anemia in Patient with Inflammatory Bowel Disease, despite iron deficiency anemia impacting one third of IBD patients, “more than a third of anemic ulcerative colitis patients are not tested for IDA, and a quarter are not treated with iron replacement therapy.” While oral iron tablets are effective for treating mild IDA, it’s not for everybody. The study also notes, “it is important to recognize that ferritin is elevated in chronic inflammatory states and among patients with active IBD, ferritin levels less than 100 are considered to be diagnostic of iron deficiency.” Iron infusions have a solid safety profile and can be used to help boost your iron stores and prevent future iron deficiency.
While treatment goals are well-defined, selecting a treatment is often not as straightforward. The PubMed study previously mentioned recommends that all IBD patients with IDA should be considered for oral supplement therapy, whereas someone with clinically active IBD, or someone who is not tolerant of oral iron, with hemoglobin levels below 10 g/dl be given IV infusions therapy. While oral iron is safe and affordable, some people experience GI issues from oral iron, it can also increase inflammation and contribute to flares in patients who are not in remission.
“Though intravenous (IV) iron is substantially underused, it’s considered first-line treatment for patients with active disease, severe anemia, oral iron intolerance, and erythropoietin (a hormone secreted by the kidneys that increases the rate of production of red blood cells in response to falling levels of oxygen in the tissues.)
Anemia in pediatric IBD patients
The most common cause of anemia in children with IBD is iron deficiency. It results from chronic blood loss, poor absorption, and less intake of foods that are rich in iron due to poor appetite, food selection or intolerance. According to the World Health Organization’s definition of anemia, prevalence in the pediatric IBD population ranges from 44% to 74% at diagnosis and 25% to 58% at 1 year follow-up.
Anemia can be both a biomarker of disease activity and a subtle or debilitating extraintestinal manifestation. According to, Anemia in Children With Inflammatory Bowel Disease: A Positi… : Journal of Pediatric Gastroenterology and Nutrition (lww.com), “newly diagnosed children with IBD are more likely to have IDA in contrast to anemia of chronic disease. No significant improvement in the hemoglobin was observed when patients were assessed after 13 weeks of induction therapy with conventional drugs that included nutritional therapy, azathioprine, steroids, and 5-ASAs. Despite the recognition of anemia, fewer than half of anemic patients received indicated iron therapy.”
Dr. Alka Goyal, MD, Clinical Professor of Pediatrics, and Interim Associate Chief of Clinical Affairs at Stanford University of Medicine, co-authored this study on pediatrics and tells me the key message is that anemia is the most common extraintestinal manifestation in patients with IBD.
“More than 2/3rd of children with IBD are anemic at the time of diagnosis. The treatment of IBD alone does not resolve anemia, which can be associated with a variety of symptoms. Persistent anemia indicates a more aggressive disease course,” said Dr. Goyal.
Hemoglobin levels across genders and race
According to the study, hemoglobin levels are similar in preteen boys and girls; however, after menstruation, the cutoff hemoglobin in girls is lower than in boys and is even lower in pregnant versus nonpregnant women. The African American population tends to have lower hemoglobin concentration compared with Caucasians.
“Although the normal range of hemoglobin varies with age, gender, and race, a hemoglobin level below 10 g/dL is considered to be consistent with moderate anemia and below 8 g/dL as severe anemia, whereas in young children below the age of 5 years and pregnant women, a hemoglobin level below 7 g/dL is deemed as severe anemia.”
Dr. Goyal says it’s important to monitor anemia regularly in all patients with IBD.
“Anemia can be an early indicator of active disease or an impending flare of IBD. When the body has inflammation, the iron stored in the body cannot be metabolized to help manufacture more hemoglobin and additionally there is suppression of normal blood production, resulting in anemia of chronic disease.”
Other causes include vitamin deficiency, medication side effects, or breakdown of red blood cells due to other inherited or disease-related complications.
“Patients should be monitored not just by symptoms, but also by blood tests like complete blood count, Ferritin, and markers of inflammation like CRP every 3 months when they have active inflammation and every 6 months when patients are in remission,” Dr. Goyal explains.
Bringing a dietitian on board to help
Registered dieticians who specialize in IBD can advise patients and families about foods that contain iron naturally. The iron in meats is more readily absorbed than that present in a plant-based diet.
Dr. Goyal says another important concept is food pairing.
“With food pairing, iron-rich foods like spinach, kale, and Swiss chard are ingested with citrus fruits, melons, or vegetables like bell pepper, broccoli, beans, carrots, tomato, etc. Avoid simultaneous ingestion of foods rich in dietary fiber, soy, cereals, coffee, tea, and animal protein like milk, and eggs. Children should consume at least three servings of iron-rich foods like fortified cereals, red meat, tofu, etc. The recommended daily intake of iron in healthy children is 7-11 mg daily,” says Dr. Goyal.
Treating anemia in the younger IBD population
When it comes to treating anemia, Dr. Goyal has helpful tips. She says it’s important to recognize and treat anemia along with the treatment of IBD and vice versa.
Oral iron can be tried in mild anemia when the hemoglobin is above 10 gm/dl, preferably given with juice or citrus fruits.
Avoid taking oral iron multiple times a day or in high doses.
Brush your child’s teeth after taking liquid iron.
If your child experiences side effects including abdominal pain, nausea, or constipation, and/or has no significant improvement with oral iron, it is safe to give intravenous iron.
Timely treatment may save a blood transfusion. excessive unabsorbed iron is not healthy for our digestive system, so avoid overdosing on oral iron.
Patients with persistent anemia lasting for three or more years were noted to have a higher prevalence of more severe and complicated disease (stricturing and penetrating phenotype) with a greater need for surgical intervention.
Whether you’re an adult patient or a caregiver to a child or young adult with IBD, be mindful of the importance of keeping tabs on whether anemia is creeping in and hindering you or someone you loves quality of life. Have the conversation with your GI and make sure you are being vigilant and proactive about doing all you can to prevent, manage, and treat anemia.
Life with IBD is constantly waiting for the other shoe to drop. Expecting more trauma. Knowing in your heart of hearts the results won’t be in your favor. Preparing yourself mentally and emotionally for the worst. Gearing up for the next unexpected roadblock or hurdle. I felt all these things walking into my first-ever bone health specialist appointment Friday (4/7/2023). My bone scan in December 2022, days before Christmas, showed some remarkable deterioration in my lumbar spine since my previous scan in 2019. My GI called me a bit alarmed the same day I did my scan, and let me know it was imperative I follow up with a bone health doctor.
I felt nervous about what this meant for my future and let’s just say Google was not my friend. When you’re 39 and a busy stay at home mom of three young children, osteoporosis doesn’t really go with my flow. When I went to make an appointment, the bone health specialist was booked until December 2023…a whole YEAR from my previous bone scan. I felt helpless and didn’t know what I should do proactively to maintain my bone health and try and improve it. Reading up, it sounded like a simple abdominal crunch could cause vertebrae to compress and fracture. I felt scared to exercise or put any additional strain from my day-to-day on my back.
The week of Christmas I wrote to the bone health specialist directly by email about my health history and my concern for waiting a whole year. I received a phone call from her office shortly after the New Year and they got me in April 7, 2023…instead of December 2023. I was over the moon, but also a bit anxious about what this appointment would mean for my future.
What the experience at the bone health doctor entailed
It was a crisp, sunny, spring day in St. Louis as I parked my car, took a deep breath, and said a little prayer before walking into the medical building. The office required me to do another bone scan as their machine and readings are different from the hospital where my previous scans were taken from (even though they are the same medical system). When I laid on the table for the bone scan my mind raced a bit, I felt a little anxiety creeping in. I figured the results were going to be the same as before and that I was going to be approached about starting an additional biologic (which I was planning to push back on).
When the doctor walked in, she said I have “low bone mass” for my age. At this point, unless I’ve had a fracture, she said they wouldn’t use the term “osteopenia” or “osteoporosis”. According to the Crohn’s and Colitis Foundation, as many as 30 to 60 percent of people with Crohn’s disease or ulcerative colitis have lower-than-average bone density. Being that I am almost 40 and pre-menopausal, there’s what’s called the Z and the T-score. I wasn’t aware of this and needed to do research to understand this better.
According to the Bone Health and Osteoporosis Foundation, T-Scores compare bone density with that of a healthy person, whereas Z-scores use the average bone density of people of the same age, sex, and size as a comparator. Although both scores are beneficial, most experts prefer to focus on Z-scores for children, teenagers, premenopausal females, and young males. These scores are helpful for diagnosing secondary osteoporosis, which stems from underlying medical conditions (such as IBD), rather than primary osteoporosis which results from a person aging.
So my Z-score was -1.8…while zero would be optimal, given my nearly 18-year history living with Crohn’s, past steroid use, and the fact I’m Vitamin D deficient, the doctor was not overly concerned by that number.
We went through my patient journey with Crohn’s disease—each hospitalization, timing of steroids, family history, timing of pregnancies and breastfeeding, whether I have ever used birth control, if I had ever had a kidney stone…this doctor genuinely listened and wanted to get details about my full health history. I felt validated, seen, and heard, but also comforted that the main “concern” is moreso my Vitamin D deficiency than anything else.
What this means moving forward
To strengthen bones and slow down the rate of deterioration, lifestyle is key. Vitamin D and Calcium are vital. My GI currently prescribes me 50,000 IU of Vitamin D once a week, along with 2,000 IU of Vitamin D3 daily. The bone health specialist told me after I get my routine labs done in June, if my Vitamin D doesn’t improve that she would suggest going on 50,000 IU two times a week. Like many of us in the IBD community, we tend to have malabsorption problems due to past surgery.
Along with my typical labs from my GI, this doctor also added additional labs—Vitamin D, Renal Function panel, and parathyroid hormone (PHT) test.
As far as Calcium, she recommended trying to get it through diet versus a supplement. She suggested eating yogurt daily, cheese, fortified cereals/oatmeal, and drinking milk/almond milk, OJ with calcium, and eating leafy greens. With my age, the goal is to consume1,000 mg of Calcium a day. It’s important to note she said Calcium can cause constipation and bloating. Calcium is absorbed best when taken in amounts of 600 mg or less per dose.
In a helpful folder provided by my doctor, I learned that our bodies need Vitamin D to absorb Calcium. When you’re Vitamin D deficient like me, our bodies cannot absorb enough calcium from diet and take it from our skeletons, where Calcium is stored. This weakens existing bone and prevents the formation of new bone. You can get Vitamin D from different sources: through the skin, with diet, and by taking supplements.
When it comes to exercise, I have no limitations. My doctor recommended I avoid high risk activities like extreme snowboarding or powerlifting, which isn’t an issue for me!
Given that I do have lower bone mass, I have another bone scan scheduled for April 2024 along with another bone health appointment immediately following the scan. It does my heart good to know that we’re being proactive with annual scans, but conservative in our approach. Everyone who has IBD should be given a bone scan in order to get a baseline read and follow up with repeat scans every 2-3 years, unless there’s concerning findings. If you’re reading this and your GI has not communicated with you about bone health, it’s time to start the discussion.
Simply saying and hearing “low bone mass” from a patient perspective has a much better connotation than “osteoporosis”. The entire experience and appointment with my new specialist felt like a big win. The news was unexpected, and I felt like I could breathe a sigh of relief. One less health issue to worry about, but something that I’ll continue to keep tabs on.
Reliable Sources of Bone Health Information to Check Out
When was the last time you popped an aspirin or an Aleve for body aches, abdominal pain, or a headache? Chances are, if you have IBD, you’ve been told to refrain from doing so. People with Crohn’s disease and ulcerative colitis are told to stick to acetaminophen, or Tylenol, as it’s gentler on the stomach and not known to cause ulcers or aggravate IBD. While we’re still not supposed to take NSAIDs all the time, research is going on about whether it’s ok to take on an “as needed” or “short term” basis and if they truly put IBD patients at risk for a flare.
I ran a poll on Instagram asking those with IBD if they take NSAIDs. Of the 350 responses, 68% said no, 14% said yes, and 18% said only short term.
After my bowel resection surgery and three c-sections I was told short term NSAIDs were “safe” to help manage pain postoperatively. In full transparency, over the last year or so I’ve dealt with back pain that comes and goes and have felt the need to take NSAIDs on several occasions, but in the back of mind I know I probably shouldn’t be. I try and limit how often, and only took Tylenol for nearly 17 years. But, when the pain gets to be a bit much and I have to manage life with three little ones, sometimes I feel like I have no other choice. There’s been more and more talk lately about NSAIDs and IBD, so I wanted to take a deep dive and share what I’ve learned.
Dr. Shirley Cohen-Mekelburg, M.D., M.S., gastroenterologist and research scientist at University of Michigan and Director of the Inflammatory Bowel Disease Program at Ann Arbor VA Healthcare System, recently conducted a study that looked into how NSAIDs impact the IBD population. She says the best research questions come from clinical experience and this is a topic that comes up quite a bit from patients.
“We have been discussing the question of whether NSAIDs cause IBD flares for years, and there is no strong evidence directing us to conclude that NSAIDs definitely cause flares, nor that they are safe for use in IBD. As opioid use and abuse continues to rise, it is becoming more and more important to consider our non-opioid analgesic options. Ultimately, the idea for this study came about from discussions between the co-investigators on this study as to the clinical implications of this work, and the methods we have available to further investigate this important research question,” she said.
What the study found about NSAIDs and IBD
The study findings were not necessarily surprising.
“It is very difficult to study the impact of NSAIDs on IBD flares because prospective comparative studies are difficult to conduct for an over-the-counter medication such as NSAIDs, which is widely available to patients in various forms. Therefore, to demonstrate equipoise and justify the need for further safety and effectiveness work, we leveraged a large national database of patients with IBD.”
Dr. Cohen-Mekelburg and her team used a multimethod approach to understand the associations between NSAIDs and IBD flares.
“First, we looked at a traditional statistical method for examining associations between an exposure (i.e., NSAIDs) and an outcome (i.e., IBD flare). We then used more advanced techniques to demonstrate that this observed association may potentially be due to bias rather than a true association. These biases are well-established and important to consider when conducting observational research.”
It’s important to note that just because there’s conversation, interest, and research going on about NSAIDs and IBD, doesn’t necessarily mean there’s a change in clinical practice or current recommendations.
“This moreso inspires us to question our current knowledge in order to justify that further work is necessary to establish the safety of NSAIDs in IBD, and specifically, for what patients and in which contexts,” she said.
Why not taking NSAIDs as a patient isn’t necessarily clear-cut
Dr. Cohen-Mekelburg wants patients to know there is “no universal recommendation” for the “best way” to take NSAIDs if you have IBD, which is why many patients get mixed messages from clinicians and their peers.
“In practice, we see that some patients take NSAIDs routinely without any adverse effects, and others may take NSAIDs for a short period of time with serious adverse effects. Ultimately, more research is necessary to better understand the safety and effectiveness of NSAIDs for IBD-related pain control.”
Just as IBD presents uniquely in each of us, our response to NSAIDs and what is safe or harmful needs to be further studied.
Dr. Cohen-Mekelburg says, “COX-2 inhibitors are NSAIDs that are more selective in their mechanism of action and are thought to carry a lower risk of gastrointestinal bleeding. However, they may carry a higher risk of other adverse effects, such as cardiac problems. Some clinicians have questioned whether these selective COX-2 inhibitors may be “safer” in IBD, but this is not known based on current evidence.”
Ultimately, the goal of Dr. Cohen-Mekelburg’s study was to bring attention to the topic of NSAIDS in IBD and to inform future work to better answer these important questions that both patients and clinicians need to improve IBD care and pain management.
Aspirin and IBD pregnancies
As an IBD mom of 3—ages 6, 4, and 20 months I recently learned that it’s recommended for women with Crohn’s or ulcerative colitis to take a baby aspirin during pregnancy. I was pretty shocked by this. Dr. Uma Mahadevan, M.D., Director, Colitis and Crohn’s Disease Center at UCSF, and Chair of IBDParenthoodProject.org, recommends all pregnant women with IBD start around week 12 of gestation. For those who don’t know, Dr. Mahadevan is at the forefront of the latest research and guidance when it comes to IBD and pregnancy research with the PIANO study (Pregnancy Inflammatory Bowel Disease and Neonatal Outcomes).
“Women with immune mediated disease, like IBD, are at higher risk of pre-eclampsia and related disorders (gestational hypertension). Going on baby aspirin has been shown to reduce that risk. The original trial was done in Europe with 162 mg, but in the U.S., we use 81 mg,” said Dr. Mahadevan.
She says this conversation is started with women during pre-conception counseling.
“Prior to these discussions, many of my patients were surprised and always checked with us. I tell them to take the baby aspirin with food and let us know if disease flares. Anecdotally they have all done well with respect to IBD. As an FYI, aspirin can increase calprotectin, so that’s something to keep in mind if you are monitoring that,” said Dr. Mahadevan.
The idea NSAIDS trigger IBD flares is controversial. Are patients taking NSAIDS because they have a flare or did the medication trigger a flare? Dr. Mahadevan says it does seem that short term (a few times a month for headaches, menstrual cramps) is low risk for triggering a flare.
In summary, if you ask most GI’s, they will tell you that a “short course” (5 times a month or less) of NSAIDS when you have IBD is “ok”. If your symptoms worsen or do not resolve, then it’s time to communicate with your care team and possibly get some lab work to get to the bottom of what’s going on. When I was in pelvic floor therapy last year, my therapist recommended T-Relief Arnica +12 Cream. It’s a game-changer for me and alleviates pain in minutes. I rub a little on sore joints and my lower back and lay on the heating pad and don’t feel the need to take any medication. Tylenol Arthritis also helps with joint pain.
The jury is still out about whether NSAIDs exacerbate Crohn’s and ulcerative colitis, and further studies are needed. For general aches and pains, most GI’s recommend taking acetaminophen instead of NSAIDs if you have IBD. Have the conversation with your care team and be open and honest about how you are managing your pain whether it’s related to IBD, extraintestinal manifestations, or a completely different ailment.
Mental health often takes a major hit when you’re diagnosed and live with a chronic illness like IBD. I ran a poll on Instagram and Twitter this past week and the results were extremely eye-opening. Not only for the patient community, but for any caregivers, friends, or family who know people with Crohn’s disease or ulcerative colitis.
On Instagram—out of 350 people polled over 24 hours, a resounding 93% responded “yes” to IBD impacting their mental health and causing depression and anxiety. On Twitter, I ran the same poll for 48 hours, of the more than 205 votes, 86% of people responded “yes”.
Dr. Yezaz Ghouri, MD, Director of Inflammatory Bowel Disease Services, University of Missouri School of Medicine at Columbia, offered helpful insight on the topic. I had the pleasure of meeting “Dr. ZaZ” (as he commonly goes by) in person at the Crohn’s and Colitis Foundation’s Mid-America Chapter Gala in November. Dr. ZaZ was awarded the 2022 Catalyst for Mission Advancement award and I was so inspired and intrigued by his work as I was emceeing the event, that I knew we would have to collaborate on Lights, Camera, Crohn’s! We made it happen.
Here’s my interview with Dr. ZaZ about how our IBD can impact our mental health.
NH: “During the first day of the Crohn’s and Colitis Congress 2023 conference it was shared that rates of anxiety and depression are about twice as high in the IBD community compared to the general population–why is that?”
Dr. ZaZ: “The exact cause of IBD is not known. There are some common theories that have been suggested, these include genetic factors, changes in gut microbiome, alteration in immune function of the body, and effect of certain environmental factors. Interestingly, some of these factors have also shown to be associated with mental disorders like anxiety and depression. The gut-brain axis is a nervous system-based pathway that connects the nerve cells from the brain to the gut. This gut-brain axis has been found to play a role in the release of nerve cell chemicals (or neurotransmitters) in the intestines. One such neurotransmitter is Serotonin, which has a well-established role in several psychiatric disorders like anxiety, depression, bipolar disorder, etc. Studies have pointed out an alteration in serotonin activity in the intestines of patients with IBD 1.
The gut microbiome comprises of trillions of species of organisms mainly consisting of bacteria. The healthy gut-microbiome is altered in individuals with several conditions like anxiety, depression, Alzheimer’s, Autism, etc. This alteration is also seen in IBD and has been a subject of active research to better understand the various changes in the bacteria of the gut. Some of these bacteria produce chemicals that can serve as neurotransmitters in the gut. It is unclear if these chemicals could influence the gut-brain axis and contribute towards the occurrence of mental disorders. Last year we published a study that showed this association of increased prevalence of anxiety and depression among IBD patients 2. The added burden and distress was not just limited to IBD patients, the study also showed an overall increased healthcare cost and burden to hospital systems. It is in the best socio-economic interest of the government and the public to address mental health issues in society, especially among those with chronic illnesses like IBD.”
NH: “How can patients best articulate their concerns and communicate with their doctor about their mental health?”
Dr. ZaZ: “IBD patient sometimes suffer from anxiety, depression, sleep disturbances, and other mental conditions like eating disorders. Your GI doctor hopefully has established a healthy physician-patient relationship where you are comfortable to bring up any issues that you would like to discuss with your GI specialist. During my clinic visits apart from addressing the medical aspects of IBD, I frequently have a friendly conversation about my patient’s life in general with a focus on their overall well-being, including talking about their mental health. In addition, several individuals have a primary care provider (PCP) with whom they generally have a good relationship and feel comfortable bringing up any health-related concerns.
Psychiatric conditions can manifest with sleep disturbances, fatigue, loss of appetite, lack of interest in activities that you previously enjoyed, depressed mood, suicidal thoughts, etc. Sometimes IBD flares can contribute to some of these symptoms, especially sleep disturbances due to night-time diarrhea or constant abdominal pain. Use of biological medications can be frequently associated with fatigue that may last a day or two after taking the biologic. In a large-scale UK based study, presence of a diagnosis of IBD was associated with a higher likelihood to cause deliberate self-harm, anxiety, depression, and insomnia. Interestingly, the risk was higher among those with Crohn’s disease than with ulcerative colitis 3.
Remember, mental stress can also contribute to an IBD flare. Frequently I see some of my IBD patients go through an uncontrolled spell of psychological stress, maybe related to personal relationships or their place of employment. This when unchecked can precipitate an IBD flare, and in some cases develop psychiatric illnesses like anxiety or depression. Hence, it is important to have a stress-free life or mitigate stress to minimize its effect on your mind and body.”
NH: “I know you see a lot of college students; how do you navigate these concerns as their care provider? Do you tend to see this more with your younger patients—or is it across the board?”
Dr. ZaZ: “College life of a freshman can be quite stressful. The move away from the comforts of their homes to a new city or town and being surrounded by strangers can be overwhelming. This can cause psychological stress which may precipitate an IBD flare. Moving to college can also disrupt the continuity of care received from their established pediatric or adult GI specialist. Students may skip their medications due to storage issues, changes in insurance, feeling of shame of having IBD or fear of not being able to ‘fit-in’. All these factors can contribute to inadequate management of their underlying IBD. We at the University of Missouri try our best to accommodate college students in our clinics so they are cared for and IBD flares are prevented from occurring. The student health clinics are efficient in recognizing students with chronic illnesses and referring them to GI clinics. I frequently encourage students that they continue to see their primary GI specialist but also establish care in our clinic/hospital system, so in case there is a medical emergency or if they experience a flare, we will be well-informed beforehand about their medical history and have a plan in place to adequately treat them.
In a large study comprising of more than one million IBD patients, it was shown that being a female, having diagnosed with IBD as a child or a young adult and having a diagnosis of Crohn’s disease have been associated with higher likelihood of suicide attempts and suicide death 4.
Mental disorders in IBD are seen across all age groups but are somewhat more pronounced in those individuals whose disease is not well controlled or have not achieved remission since their initial diagnosis. Majority of IBD cases are generally diagnosed at a young age, several times in college students. Unfortunately, we also see frequent occurrence of mental disorders in younger age groups. Students have additional mental stressors when they have a chronic bowel condition like IBD. Many feel that they the lack of freedom in choosing to eat anything they like when they go out with friends or their need for frequent bathroom breaks, which can sometimes hinder them from participating in activities they choose or in making new friends. Many feel embarrassed to disclose their medical conditions to new friends or acquaintances, this perhaps cannot be stressed enough among those with an ostomy bag.
This leads to a state of inadequate social/family support which may push at risk students into developing mental conditions like depression, anxiety or eating disorders.”
NH: “Any advice for caregivers of young patients–who may have concerns about their child/teen/young adult and are unsure how to make sure their child is not dealing with anxiety/depression, but don’t want to overstep or upset their loved one?”
Dr. ZaZ: “It is very important for not just the physicians but also the caregivers involved in managing IBD in young patients to recognize signs of depression or other mental disorders. Do not always assume that if an individual is constantly tired, has disturbed sleep or looks depressed, that it is due to their IBD. Several times these are early signs of depression, and these young individuals need the support and help that they deserve to address these issues. Perhaps adult patients who have depression may recognize it and seek help, but kids or teens generally do not perceive these signs as an abnormal expression of behavior and may not even disclose them to their loved ones. Caregivers who attend clinic visits with pediatric specialists should bring up any unusual behavior they notice about their child and discuss it with the provider.”
NH: “How can mental health issues exacerbate IBD symptoms?
Dr. ZaZ: “Studies have shown that individuals with mental disorders who have IBD have a higher chance of developing IBD flares, they require escalation of their therapy and have increased incidence of death 5. (See Reference 5) This is quite alarming and should be brough to the attention of providers who take care of IBD patients. “Providers are not just prescribers”, simply writing prescriptions for medications, some of which are very expensive, is not enough to heal the patient. IBD is a chronic disease which lasts a lifetime, and medications alone cannot be the solution. Providers need to step up and participate in the mental well-being of their patients. If they are not able to address the mental health related issues themselves then referring to experts in the field is perhaps the best alternative approach. Depression may cause patients to skip their infusion visits or physician visits, uncontrolled anxiety or paranoid states may make them apprehensive about any therapy that they have been appropriately prescribed and may even stop the treatment. IBD patients with eating disorders may starve themselves or eat uncontrollably causing worsening of their bowel condition. These eating disorders are commonly present among young and female IBD patients who have body image disturbance 6.”
NH: “How is anxiety and depression typically managed in patients with IBD? (Medication, talking to a psychologist, etc.?)”
Dr. ZaZ: “The first step to treating anxiety and depression is to approach a provider with whom you are comfortable to freely express your medical complaints, problems, or any issues that you would like to discuss. Psychotherapy or behavioral therapy is probably the preferred approach in mild cases but in individuals with more profound symptoms, medications may be preferred in addition to psychotherapy. Finding a good therapist and setting up sessions at frequent intervals is important. In severe cases with suicidal ideations or attempts perhaps hospitalization may be required.
Multiple medications are commonly used for treating anxiety and depression. A PCP or psychiatrist may be able to find the right one for you, and please make sure you follow up with these providers since these medications may need to be monitored for their side effects and to adjust the dosage. Sometimes GI physicians may feel comfortable to prescribe these medications, but that may generally not be true for majority of gastroenterologists.”
NH: “As a GI, how do you try and facilitate positive relationships with your patients to help ensure they feel at ease with taking on their disease, managing it, overcoming flares/surgery, etc.?”
Dr. ZaZ: “My first step towards approaching IBD is to make sure that the symptoms that my patients are complaining of are truly from IBD and not from IBS or any other illness. Once IBD is diagnosed, I have a detailed visit with my patient with their new diagnosis. I usually encourage them to read up as much as they can and write down questions about their illness prior to this clinic visit. During the visit I start by giving a broad overview of what IBD is and the mechanism of disease process.I do this little exercise of talking about mechanisms by which IBD develops because I have noticed in my experience that several patients feel guilty about having their illness, and believe that in some way it was ‘their fault’ that they developed IBD. We then focus our attention on what are the available treatments why I think the recommended treatment would be a good fit, so the patients can make an informed decisions about their choice of therapy. I highlight the signs or symptoms they need to look out for that could suggest a complication or flare up of IBD. We provide them access to communicate with our clinic team if they have any questions; if they are concerned about a flare or if they suspect side effects from their therapy. Next, I answer questions they may have come up with during my discussion or from their personal research prior to the visit. Once the questions are answered I provide them with written material about their illness. I frequently encourage our patients to join patient support groups and direct them to online sources for information about IBD like the website for the Crohn’s and Colitis Foundation.”
NH: “Why is it so important to focus on whole person care–and recognize that IBD impacts more than the GI tract?”
Dr. ZaZ: “If we understand the mechanism by which IBD develops in the body, we can say that a dysfunctional immune system perhaps has the central role in the disease process. This immune system is connected to the entire body, it’s in our blood, guts, and other organs. Abnormal functioning of this immune system is likely to affect the entire body, although in IBD this abnormality primarily targets the bowels. But we frequently encounter what are called the “extra-intestinal manifestations of IBD”. These are referred to conditions that cause joint pains, skin rashes, eye redness, oral ulcers, liver disorders and other symptoms or signs that can be encountered in patients with IBD. Beyond these, patients with IBD are shown to be associated with higher incidence of mental disorders, pregnancy-related complications, chronic fatigue, and vitamin/mineral deficiencies. The effect on the bowels by this disease has a major impact on what one can eat, thereby limiting their nutritional intake. It is only fitting to treat these individuals as a whole, and not just their bowels. In terms of methods of treatment, apart from allopathic medical therapies, several other modalities of treatment are now being explored and accepted. Addressing diet and exercise is an important aspect to maintain healthy lifestyle in general, and especially so in patients with IBD. Running or other forms of cardio-based exercises have been shown to have a positive impact on the disease. Consuming healthy dietary supplements, like probiotics have been shown to be beneficial. Relaxation techniques and meditation also help keep oneself stress free, and perhaps prevent development of mental disorders as well.
One last thing we must also remember is that in today’s world social media can contribute to a lot of mental stress and anxiety, especially where disinformation campaigns can lead to confusion and poor choices in life. Hence it is important to have reliable resources to gain knowledge about IBD and its therapies. Sources like the Crohn’s and Colitis Foundation and its members like Natalie have been leading in educating several individuals through various platforms. In summary, eat healthy, exercise regularly, educate yourself about IBD, try to relieve stress and follow up with your doctor for medical care.”
I hope this article sparks a conversation and allows you to feel less alone in your mental health struggles. The findings show it’s anything but “just in your head.” Your feelings, fears, and struggles are valid. You are loved. You are not a burden. You are worth it. You matter. We need you here. Remember that.
If you’re thinking about suicide, are worried about a friend or loved one, or if you would like emotional support, call 988 any day of the week, any time. The 988 Suicide and Crisis Lifeline (formerly known as the National Suicide Prevention Lifeline) provides free and confidential emotional support to people in suicidal crisis or emotional distress 24 hours a day, 7 days a week, across the United States.
Reference Guide List
1: Coates, M. D., Mahoney, C. R., Linden, D. R., Sampson, J. E., Chen, J., Blaszyk, H., Crowell, M. D., Sharkey, K. A., Gershon, M. D., Mawe, G. M., & Moses, P. L. (2004). Molecular defects in mucosal serotonin content and decreased serotonin reuptake transporter in ulcerative colitis and irritable bowel syndrome. Gastroenterology, 126(7), 1657–1664. https://doi.org/10.1053/j.gastro.2004.03.013
2: Tarar, Z. I., Zafar, M. U., Farooq, U., Ghous, G., Aslam, A., Inayat, F., & Ghouri, Y. A. (2022). Burden of depression and anxiety among patients with inflammatory bowel disease: results of a nationwide analysis. International journal of colorectal disease, 37(2), 313–321. https://doi.org/10.1007/s00384-021-04056-9
3: Umar, N., King, D., Chandan, J. S., Bhala, N., Nirantharakumar, K., Adderley, N., Zemedikun, D. T., Harvey, P., & Trudgill, N. (2022). The association between inflammatory bowel disease and mental ill health: a retrospective cohort study using data from UK primary care. Alimentary pharmacology & therapeutics, 56(5), 814–822. https://doi.org/10.1111/apt.17110
4: Xiong, Q., Tang, F., Li, Y., Xie, F., Yuan, L., Yao, C., Wu, R., Wang, J., Wang, Q., & Feng, P. (2022). Association of inflammatory bowel disease with suicidal ideation, suicide attempts, and suicide: A systematic review and meta-analysis. Journal of psychosomatic research, 160, 110983. https://doi.org/10.1016/j.jpsychores.2022.110983
5: Fairbrass, K. M., Gracie, D. J., & Ford, A. C. (2022). Relative Contribution of Disease Activity and Psychological Health to Prognosis of Inflammatory Bowel Disease During 6.5 Years of Longitudinal Follow-Up. Gastroenterology, 163(1), 190–203.e5. https://doi.org/10.1053/j.gastro.2022.03.014
6: Stoleru, G., Leopold, A., Auerbach, A., Nehman, S., & Wong, U. (2022). Female gender, dissatisfaction with weight, and number of IBD related surgeries as independent risk factors for eating disorders among patients with inflammatory bowel diseases. BMC gastroenterology, 22(1), 438. https://doi.org/10.1186/s12876-022-02526-0
It’s considered the most common surgical procedure for ulcerative colitis patients when medication fails to keep IBD under control. The ileal pouch anal-anastomosis (IPAA) or j-pouch, is created after a surgeon removes your colon and rectum and uses the end of your small intestine to form an internal pouch, which looks like the shape of J.
This week on Lights, Camera, Crohn’s we hear from a colorectal surgeon and IBD patient himself, along with several women with j-pouches about their experience, what they’ve learned along the way, and what they hope others know who are living similar realities.
What does the j-pouch procedure entail?
Before we dig deeper, a short “lesson” on what the j-pouch procedure involves. It’s typically a one, two, or three stage process.
According to the Crohn’s and Colitis Foundation:
The first surgery removes your colon and rectum and preserves your anus and anal sphincter muscles. The ileum is made into a j-shaped pouch and connected to the top of your anal canal.
A temporary ileostomy is typically created to give your newly formed pouch a chance to heal. A loop of your small intestine will be pulled through an opening in your abdomen, called a stoma, to allow waste to exit your body into an ostomy bag.
During this time, you will need to always wear an ostomy bag, and it will need to be emptied several times a day.
You will have your second surgery eight to 12 weeks later, once the pouch has healed.
The second surgery will reverse the temporary ileostomy and reconnect your small intestine. Your internal pouch will then collect waste and allow stool to pass through your anus in a bowel movement.
Some surgeons choose to perform this surgery in just one stage, in which the pouch is created and joined to the anus without a temporary ileostomy. This is done less often than the two-stage procedure because of an increased risk of infection.
This topic resonates with Dr. Stefan D. Holubar, MD, MS, FASCRS, FACS, IBD Surgery Section Chief & Director of Research for the Department of Colorectal Surgery at Cleveland Clinic, for many reasons. He was diagnosed with Crohn’s colitis when he was 7 years old and was on and off steroids (the only treatment at the time) for many years.
“I had learned to live with chronic embarrassing urgent incontinence, as well as being small and skinny, and with a swollen face from the steroids. I was offered an end ileostomy as a teenager (not a J-pouch as it was Crohn’s) and was lucky to get a second opinion with the famous Dr. Daniel Present (RIP) at Mount Sinai. I went on NPO and TPN for one year which helped get me into remission and grow about a foot in one year. Somehow, I made it through college and got into medical school, but it turned out I hadn’t had a colonoscopy in about a decade.”
Over Christmas 1999, Dr. Holubar had a colonoscopy and received a call a few days later while he was skiing that he had colon cancer.
“That same day, the tumor swelled from the biopsies, and I developed a large bowel obstruction. I had emergency subtotal colectomy w ileosigmoid anastomosis without an ileostomy. After chemotherapy and completing medical school, I needed the rectum removed (due to risk of rectal cancer) and underwent a modified 2-stage J-pouch without ileostomy one month before surgical residency. I’ve been great ever since, not perfect as I have had some complications over the years, but great, with three kids, the best job and wife in the world.”
During the second half of medical school, Dr. Holubar was considering going into GI or Medical Oncology and learned that colorectal surgery was a specialty.
“Once I learned Colorectal was a specialty and they are the IBD experts, my future path was set in stone. It’s rare to know that you want to be a colorectal surgeon that early in training. I’m blessed to share my successful story and give patients with complicated IBD like me hope every single day of my life. My experiences have also influenced me to do clinical research to try to change care more broadly and ideally, globally. My IBD history is a source of endless inspiration for our innovative work.”
I asked Dr. Holubar what advice he has for patients who are on the fence about getting a J-pouch. His most important advice—is to seek expertise.
“I would recommend looking for surgeons who specialize in IBD. J-pouch surgery is a niche these days (hence “IBD Surgeons”), and your care team should be expert in taking care of the complications that may develop. A majority (>90%) of patients with a pouch would do it again and/or recommend it to a friend or family member.” (Fazio et al., Annals of Surgery, 2013, PMID: 23299522).
Dr. Holubar wants to highlight a couple important points in terms of this article:
Only about 10% of people who are deemed candidates for a pouch choose not to have it, for personal reasons such as work, or lifestyle-related reasons such as lack of access to a toilet for many hours at a time, or those who prefer a one-and-done approach (Holubar, Inflamm Bowel Dis, 2009, PMID: 19266572). We have a new article on this, but it has only been published as an abstract so far (Total Proctocolectomy with End-Ileostomy Versus Ileoanal Pouch for Ulcerative Colitis: Who Doesn’t Pouch, And How Do They Do? Dis Colon Rectum 64;5; Meeting AbstractPOD169)
On the other hand, the overall long-term pouch survival is about 90-95% which is very high (in other words, it works out most of the time, but not always) (Fazio et al., Annals of Surgery, 2013, PMID: 23299522).
In the current digital era, we are blessed to have support groups on social media and active discussions on #SoMe4IBD. That said, it’s important to know that not everyone who has a pouch – whether the experience is great, or they have complications – is vocal on social media. It’s important to check with your care team to discuss the best treatment options for you.
When it comes to the risk and benefits of having a J-pouch, Dr. Holubar says each patient needs to chart out the pros and cons of end ileostomy (or rarely a continence ileostomy aka Kock pouch) vs. IPAA as the risk-benefit profiles are quite different.
“The main benefit is that a patient can maintain transanal defecation and avoid a permanent ileostomy and care of the ileostomy. An added “benefit” of having a pouch is that you can almost always go back to an ileostomy if it doesn’t work, or you are not satisfied with the function. Going back into the belly is of course with some risk of further surgical complications,” he explained.
The j-pouch patient perspective
Jackie was diagnosed with ulcerative colitis in March 2009. She was 24 years old and had been given a multiple sclerosis diagnosis before that. At the time, her care team was concerned a biologic could set off her MS.
“Less than a year after my diagnosis, I was told that I’d run out of medication options and I’d need to have my colon removed and opted to schedule surgery at that time to work towards a j-pouch,” said Jackie.
Getting acclimated to having an ostomy didn’t come easily. She says her biggest obstacle was getting over her own biases.
“I didn’t know anything about ostomies except from what I read online from other patients at the time and the consensus in the online forums was not good. I was nervous, but I learned almost immediately that I felt better, was healthier, and could do more. After my first surgery, I traveled across the country and hiked through some parks in Oregon. None of that would have been possible before my ostomy. It only took a few experiences like that to realize how much the ostomy had really given me.”
Of course, there’s a learning curve. There’s new terminology to learn, you must find what works on your body, and that can be frustrating.
“I was curious from day one. I knew that I was sent home in the appliance the hospital had set me up with, but I wasn’t convinced that was the best one for me, so I took it upon myself to test lots of brands and products to get the one that worked best for me.”
Jasmine was diagnosed with ulcerative colitis in 2017 when she was 19. She was a freshman in college. Two years later she dealt with a flare she started Entyvio, but the drug failed her shortly thereafter. She switched to Remicade in January 2020 and had the same problem, even after receiving the highest possible dosage every 4 weeks. Her health continued to rapidly decline, and she was hospitalized in March 2020.
“This was the first-time surgical intervention, an ostomy, and a j-pouch were mentioned to me in a real way, however, the doctors continued to say they felt cautiously optimistic Remicade would pull me out of my flare. Throughout these months, I tried a variety of diets including SCD and AIP, visited multiple dieticians and nutritionists, met with natural health doctors, sought out second opinions, and followed a robust supplement regime that was continuously updated by my functional health doctor.”
Despite every effort, by April of 2020, her health was the worst it had been her my entire life. Weighing 105 pounds, she lived in constant, excruciating pain, unable to sleep or eat, too weak to stand in the shower for longer than five short minutes.
“IBD completely ruled my life. When I spoke with my doctors in early May, they told me I had two options: I could try Stelara, the last drug available to me, which my team was 99% sure would not work and would result in emergency surgery since the drug takes months to kick in and provide relief. Otherwise, I could have surgery immediately. My options hardly felt like options when both resulted in the same outcome, just at different times. I opted to have surgery sooner rather than later. If it was inevitable, I wanted to begin the process and start feeling better as soon as possible, rather than continuing to needlessly suffer.”
A few days later, Jasmine met with a surgeon, and less than a week after that appointment (and the morning after her college graduation), she was rolled into the operating room to have my colon removed.
“No life experience prepares you to look down and see an internal organ on the outside of your body. A stoma is far outside the lines of normal human experience, and despite all the preparation in the world, your brain can’t fully process what it will be like until it’s happened. I found the transition to be difficult; while the nurses in the hospital were helpful, the nurses sent to my home barely seemed to know what to do. I had to teach myself how to empty the bag, and at first, it often took me an hour to change the ostomy. However, with time and as my body healed from surgery, I became more confident and able to quickly take care of the ostomy in under five minutes,” said Jasmine.
Even though the physical acclimation was challenging, Jasmine says the mental acclimation was even harder.
“At the time, I was 22 years old and had never in a million years imagined my life to involve a bag of waste attached to my stomach. I felt like I was constantly grieving the life I’d imagined and the life I’d never get to live. The ostomy felt like a reminder of all that had been taken from me that I couldn’t ignore, concrete proof of how different I was from all other 22-year-olds and how far my life had diverged from the normal college experience. I spent many days looking in the mirror and crying at what I saw, struggling to accept the ostomy as the life saver it was. Over time, as I began to regain more freedom and control over my life, eating the food I wanted, sleeping through the night, exercising, and traveling, I slowly began to make peace with the ostomy through the lens of all it enabled me to do.”
Aimee was diagnosed with ulcerative colitis in 2011 when she was 22 years old. She struggled responding to medical intervention and dealt with severe abdominal cramping and high levels of blood in her stool which destroyed her quality of life.
“I had to give up my job, my life, my apartment, my social life and moved back to my hometown to be taken care of by my parents. In one hospital admission 9 months after first symptoms, the surgical team advised I do the ostomy to avoid a tear or rupture to the colon which could lead to emergency surgery or worse, sepsis.”
The ostomy relieved Aimee’s constant cramping and she felt instant relief from her chronic pain. Going into surgery the plan from the start was to do a three-step surgical journey over 12 months that resulted in a j-pouch May 2012.
“There is so much help in the hospital that it was only the day I was leaving that it hit me that this was going to be something that would be hard to get used to. I was 22 and I was embarrassed to tell everyone and conscious of my looks, so there was a vanity piece that was hard to overcome. When I was home, I felt alone. I wanted to manage the bag all by myself, I didn’t allow anyone to see the stoma or my bags or anything. Looking back at my young self, I wish I had let my family and friends in more to help me, I didn’t need to hide it.”
Elissa was initially diagnosed with ulcerative colitis when she was 14 years old, back in 1994 and years later, Crohn’s, in her small intestine. Her diagnosis journey was a difficult one. She was told she was lactose intolerant, had food allergies, IBS, anxiety, and a nervous stomach.
When Elissa was 20, she underwent emergency surgery to remove her colon. She was one of the first patients to participate in a clinical trial for Remicade back in the day. Unfortunately, the medications kept failing her, she became dependent on high doses of steroids, and she had precancerous cells in her colon.
“I was in college at the time and didn’t feel comfortable telling most people. There were a few occurrences of my bag leaking (one especially memorable experience in the middle of a fraternity party), and I was mortified. However, my recovery also highlighted the thoughtfulness and generosity of my best friends and family members who would drive me to the pharmacy to pick up medical supplies, drive me to doctor appointments, even just sit with me and rest. People really come out of the woodwork – sometimes asking for help is the hardest part.”
At times Elissa felt very alone. She wishes she had known the Crohn’s and Colitis Foundation was available, along with support groups. She says, now, there are so many amazing resources available for people in recovery, including the forum j-pouch.org.
Dani was diagnosed with ulcerative colitis in 2005, when she was just 8 years old. She was initially managed on oral medication then switched to biologics and went through Remicade, Humira, Xeljanz, Stelara, and Entyvio.
“I always knew that surgery was on the table, and I felt like I was always buying time until a new medication came out. In January of 2021 I became extremely sick and was admitted to the hospital for IV cyclosporin to try to lessen my immune response. I was ok enough to leave the hospital and was feeling ok for about four days out of the hospital and then I started to become sick again. My surgeon came around a few times to check on me and introduce himself. He said, “I just want you to know that I’m not the scary man with a knife.” At that time, I didn’t know he would be my surgeon. When I started to get sick again after leaving the hospital, I knew that surgery was going to be the next step.”
From then on, Dani met with her GI doctor and Colorectal surgeon (who work together), and they scheduled her for a subtotal colectomy a few weeks later. She began the 3-step surgical process in March 2021.
“It was a huge adjustment. I constantly felt my bag and it felt so foreign to me. At the same time, it gave me an independence that I had never had before. My plan was to go through all 3 j-pouch surgeries to have an ostomy for nine months and then have a j-pouch. I felt confident that I could adjust to an ostomy again if necessary and that I wanted to give a j-pouch a try.”
Dani got her take down surgery J-pouch in December 2021.
The hope of reversing from the start
Jackie: “The plan was to reverse, but I did have a major panic moment a few months before I was supposed to have another surgery. A friend of mine who had started his journey to a -j-pouch around the same time I did, was one step ahead of me in his surgical sequence, and he was having some major problems. I figured the ostomy was the devil I know, better stick with what you know, because I was afraid of what the other side looked like. But I knew myself, and I knew I had to at least try for a reversal, otherwise I’d spend the rest of forever wondering how it would have gone.”
Jasmine: “From the start, the colectomy was presented to me as a step toward the larger goal of getting a j-pouch. I went into the first surgery planning to try the j-pouch.”
Elissa: “I knew the ostomy would be temporary, but I really had no idea what to expect as far as recovery was concerned. My doctors and surgeons did not explain any potential complications. I wish I had known more questions to ask.”
For Elissa, a pouch was created at the time of surgery that removed her colon. Three months later, she had reversal surgery during college spring break – unfortunately, the reversal failed, she caught an infection and ended up in the ICU. The ostomy was placed again for her body to recover from an additional open abdominal surgery. She then went on to have a successful reversal in July of 2000.
Making the decision to go for a j-pouch
Jackie: “I knew that I could have chosen to keep my ostomy, but there was a real sense of “why wouldn’t you get a j-pouch” from the medical team. There was an undertone in what they said and did that insinuated the j-pouch was the more ideal situation and that I should clearly want to go that route. At the time, I was still regularly following most professional medical advice and didn’t really question it. But the option to keep the ostomy was never really discussed and it was always assumed I would reverse it.”
Jasmine: “Because I was young, otherwise healthy, and it had been confirmed many times through testing that I had ulcerative colitis, rather than Crohn’s disease, my doctors said I was a great candidate for j-pouch surgery. In general, my surgeon told me that close to 90% of j-pouch surgeries are successful, and I felt confident trying based on my background and the conversations with my medical team. By the time I’d had surgery, I’d only had ulcerative colitis for three years and had been in remission for two of them. The j-pouch felt like the best avenue for a life as close to normal as possible given the circumstances, and at 22, with (hopefully) a lot of life ahead of me, that sense of normality was important to me.”
How it felt leading up to reversal
Jackie: “I kept reading about all the things that could go wrong and it really freaked me out. I knew people personally who had some complications and it made it seem less like a potential statistic and more like a reality. The reality is that more people do well but are not often talking about it online. At that time there weren’t enough stories about people thriving after j-pouch surgery. I knew what life with the ostomy was like and I knew I could do that. Welcoming another major surgery and another major change just seemed really overwhelming.”
Jackie started the process in March 2010. She unfortunately had a few complications along the way which resulted in more surgeries and a longer sequence to the j-pouch, so her takedown occurred in mid-2012.
Jasmine: “I often worried something would go wrong that would prevent me from getting a j-pouch. Everything that could go wrong had gone wrong for me to even end up 22 and colon-less, and it was hard for me to imagine something could go “right.” I felt very distrustful after the variety of promises made to me by my medical team over the past year that never came to fruition and struggled with cynicism about what might happen. Coupled with all the negativity online about life with a j-pouch, I became very apprehensive about something either going wrong with my surgeries or my j-pouch failing.”
Jasmine’s j-pouch was created in December 2020 with a diverting loop ileostomy and was fully connected in February 2021.
Dani:“I had read about ‘butt burn’ and that when you first get a j-pouch you are going to the bathroom frequently, so I was concerned about that. I had just gotten used to being able to go where I wanted and not worry about the bathroom, and I was concerned that I was going to be putting myself back into a position where I was more limited.”
What j-pouch recovery was like
Jackie: “The takedown was one of the easier surgeries to recover from for me because that was the only thing they were doing in that surgery. Sometimes surgeons combine steps that can make certain parts more difficult to recover from, but for me it was just hooking up the plumbing, which had already been healing internally for months. Despite the complications I had that resulted in more surgery, it gave my body more time to heal, which I think is part of why my j-pouch has been so successful. The hardest part was understanding that the j-pouch can take a year or so to settle, which means you may still have some accidents here or there in the beginning. It wasn’t an immediate magical fix, but over time I learned to understand my j-pouch and to predict its behaviors.”
Jasmine: “J-pouch recovery is an exercise in endurance and mental fortitude, but I didn’t find it as terrifying as it seemed from reading online. From the beginning, I felt like I had far more control than I did with ulcerative colitis. There was almost no urgency, and I could take a minute or two to finish what I was doing before going to the bathroom, rather than having to drop everything and run. Although you do go to the bathroom quite often at the start, having that control makes a huge difference. One of the harder parts of recovery is the acidic stool – waste in the small intestine has more stomach acid in it, which usually gets broken down by the colon, however, without a colon, that acid creates burning on the skin. My skin was constantly raw and sore the first few weeks no matter how much butt cream or fluffy toilet paper I used. Sometimes the burning pain was so bad it would wake me up at night, but now, almost two years out, I rarely have butt burn.”
Aimee: “This was the hardest surgery because it was so long and so much handling of my intestines, my bowel lost function, so I vomited for eight days after my surgery. My doctors considered TPN, but luckily peristalsis started again, and I could eat!
Elissa: “Honestly, recovering from surgeries itself wasn’t too bad, especially after years of IBD flares. Getting rid of my colon provided almost immediate relief. I just had to be patient and let my body heal.”
Dani: “The recovery was the easiest in terms of there weren’t new incision spots. I had to get used to seeing my stoma hole as it closed in naturally and I was still very sore. I also was going to the bathroom frequently and wasn’t sleeping through the night for the first few weeks, which was hard. I was frustrated that I felt like I always needed to be near a bathroom, but that feeling was temporary. “
Pros and Cons of life with a j-pouch
Jackie: “Honestly…it has been so good. I have a total rockstar j-pouch. I eat anything I want (popcorn? yes! all the nuts? yes! spicy food? Yes, please!), I can hold my bowels for hours upon hours. I rarely have any urgency and in general have peace of mind that I can live my life, go where I want, and UC no longer can control that. The cons exist, but for me, they’re small. I’ve had pouchitis a few times, which feels like UC again, but it’s treated with antibiotics and then you’re back on your feet! I have accidents at night maybe once a year. I still use the bathroom more often than a person without IBD, but it’s mostly because I choose to for peace of mind. My digestive tract in no way resembles a normal one, it’s different how everything works now, but it’s not a detriment in my life.”
Jasmine: “My j-pouch has given me a level of freedom I never thought I’d experience with IBD. I don’t currently take any medications, and I don’t worry about flaring or failing a medication the way I would with my colon. Although I know there’s always the possibility of needing medication in the future, I’ve been given more freedom and autonomy over my life than I ever thought possible. I eat what I want when I want. I sleep through the night. I sit through meetings and classes without thinking about the bathroom. I go out with friends, travel, and exercise. For me, the j-pouch has brought me closer to my pre-IBD or deep remission self than anything else, and although there are permanent tradeoffs to having such major surgeries, I don’t regret my decision in the slightest. There is an adjustment phase and a new normal, but that new normal has enabled me to integrate IBD my life, rather than having my life completely consumed by my illness.”
Aimee: “I have had fistulae since at the anastomosis, so they have been tricky to manage, but Humira has been wonderful to me, keeping them at bay and giving me energy to live a full life. I also need to have the scar tissue at the anastomosis stretched surgically every 6 months.”
Elissa: “J-pouch life has been amazing! I was in the bathroom 20+ times a day before my surgeries and felt like a shell of a human being. I’m now 42 and have had my j-pouch for 22 years. I can do pretty much anything a “normal” healthy person can do, just need to take occasional extra precautions like electrolyte replenishment or dealing with occasional pouchitis or Crohn’s flares. (My Crohn’s diagnosis came after my j-pouch surgery).”
Dani: “The first few weeks/months with a j-pouch were tough. Your body needs to figure out how to function with a new man-made organ. I was only comfortable laying down for the first few weeks after the surgery. I really hit a turning point when I was able to start taking Imodium and Metamucil. They were helpful for me in the first few months and now I don’t need them. Three months after my final surgery, I had moved out of my house and was starting a new full-time job. So, the initial discomfort and increase in bowel frequency were very temporary!!”
What j-pouchers wish they knew prior to their reversal
Jackie: “I always say its trading a large set of problems for a smaller, more manageable set of problems. UC was awful for me and ended up being life threatening. It was no way to live. My j-pouch has given me my life back, but it’s not a cure. It’s not perfect. I still have some small problems here and there, but it’s all manageable and in no way resembles life before surgery.”
Jasmine: “It’s hard to find information on j-pouches, and I think many of us turn to the internet to learn about what life with one might be like. I personally found the internet to contain a lot of negative information, making me more fearful going into the surgeries than I would have been had I just listened to my surgeon. I would recommend limiting time spent online and trying to connect with individuals who have j-pouches/ostomies through your doctor or the Crohn’s and Colitis Foundation. These resources provide a more accurate peek into life with a j-pouch and can allow you to ask questions and connect with someone who’s been through the same thing. Most people who are healthy aren’t online complaining about their j-pouch, which skews the sample of information accessible to the rest of us. Whenever I started to feel overwhelmed by everything online, I reminded myself of something a nurse once said to me: the internet is a showcase of the best and the worse situations, more often than not, you’ll end up somewhere in-between.”
Aimee: “I was told this would be the end of treatment and medicine which wasn’t the case. As I had Crohn’s, not UC, I had many more hurdles ahead. Also, a new pouch is new so it’s behavior post op, is not your life. Your body adjusts to the pouch and output goes slower as the post-op weeks go by. The j-pouch is an alternative to an ostomy bag, but has to be adjusted to also. It’s different from having your colon. After a few months though, you will have longer periods between toilet runs and sleep through the night. I go 11pm to 6am with no pooping, which is so much better than those few months post-op when I thought oh dear, this is hard!”
Elissa: “When I had my surgeries, I was 20. No doctors discussed potential fertility issues. My daughter was born via IVF 9 years ago, though all additional efforts have failed. This is something I wish I had known about – I always wanted kids and would have frozen my eggs. Obviously, every person is different. Also, I still go to the bathroom 6-7 times a day. This is apparently normal (though again, everyone has different experiences).”
Dani: “I can eat salad for dinner with no problem!”
Advice for ostomates on the fence about going for a j-pouch
Jackie: “If you feel healthy and strong both physically and mentally, I would say, try it. I know it’s more complicated than giving a new restaurant a try, but I knew that I’d always have wondered. I knew on the bad days I would have idolized a life with a j-pouch, and I needed to know that it either would or wouldn’t work. I felt like the worst-case scenario was that my j-pouch would fail, and I’d return to an ostomy, which I already knew I could do, and I liked those odds.”
Jasmine: “I think it’s a personal decision dependent on the history and circumstances of each person’s illness. Going through the j-pouch surgeries means additional time spent in the hospital and recovering, which is worth it for some, but not others. Although I can share my experiences, everyone’s body is different, and you can’t always predict how someone else will respond. I think the best thing to do is find a colorectal surgeon skilled in these procedures and discuss whether they think you’re a viable candidate. Finding a skilled surgeon is the best way to hedge against future problems and increase chances of success. Beyond that, I would advise talking to as many people as possible with a j-pouch and permanent ostomy, to get questions answered and hear the pros and cons of each route. Having this information should help you feel more confident in your decision, and if you’re still undecided, you can always put off the decision until you’re ready.”
Aimee: “Tell them to get support, don’t expect instant results, give yourself time to adjust to yet another way of going to the toilet…reach out to the online community.”
Dani: “I think this is a very personal decision and there is validity to both sides. An important thing for me was to remember that people are more likely to write online if they have a bad outcome rather than a good outcome. Everyone’s instinct is to research things online and at some point, I felt like reading everything (both good and bad) was too overwhelming.”
Post-op expectations with a j-pouch
Like any surgery, recovery takes time and patience. The Crohn’s and Colitis Foundation shares the following on their website:
Some patients may experience an increased number of bowel movements, sometimes up to 12 times per day. This will typically decrease over time.
Some male patients may experience sexual dysfunction as a result of nerve damage.
Some female patients may develop scar tissue that surrounds their ovaries and fallopian tubes, which may lead to infertility.
Both men and women should discuss sexual function with their surgeon and ask when it is safe to resume sexual activity.
Ask your healthcare providers what supplies you may need at home, especially if you have a temporary ileostomy.
Your healthcare team will advise you on how to manage your temporary ostomy and how to keep it clean.
Final Thoughts
Jackie: “This is a weird one, but I had to use brain power the first time I had to poop after my takedown. It had been almost 2 years since I had used my butt, and I had to really think about how to use those muscles again. It was a little funny at the time.”
Jasmine: “In terms of recovery, the most important thing to remember is j-pouch surgery completely alters one of the body’s major systems and adjusting takes significant time. Recovery doesn’t happen overnight, and it can feel frustrating. I tried to give my body some grace and the time it needed to heal, while reminding myself that life with a j-pouch during the first few week’s post-op isn’t indicative of what living with a j-pouch will be like long-term.”
Aimee: “It’s a journey. I have a few good months, a few bad months. Part of me knows that quality of life could be better with an ostomy, but I’m not ready to say goodbye to my pouch yet. I have been unlucky with the scar tissue, but those small procedures are like going to the dentist for me, I’m so used to them.”
Elissa: “Do it! Healing takes time, but you will feel like a new person. Life is too short to be in pain all the time. So many improvements have happened over the past 10-15 years and awareness is absolutely the key. “
Dr. Holubar wants to remind patients, “The J-pouch cannot save your life – it is a lifestyle operation like cosmetic surgery in some way. Overall quality of life is excellent with both a pouch and with a permanent end ileostomy. Finally, we should think of surgery as an excellent “medical” therapy in patients suffering from colitis despite modern medicines. One of my expressions is that a good ileostomy (or pouch) is better than a bad colon, rectum, or anus (and a good ileostomy is better than a bad pouch). The great news is you cannot make a wrong choice.”
When the Pregnancy Inflammatory Bowel Disease and Neonatal Outcomes (PIANO) study first launched in 2007 the main goal was to understand the safety of anti-TNF biologics like Humira and Remicade, and thiopurines for women throughout pregnancy and postpartum. As an IBD mom of three, I was able to participate with my youngest who is nearly 16 months old. The experience was something I am extremely grateful for. This incredible research for our community that is going on daily, helps guide decision making for treatment, while easing our fears as we embark on motherhood while managing IBD.
PIANO 2.0 is now underway and this week on Lights, Camera, Crohn’s I share everything you need to know about the updates to the ongoing research project, how you can participate, what the findings have shown thus far, and the goals for the future. Esteemed gastroenterologist, Dr. Uma Mahadevan, continues to lead the charge and help pave the way by sharing discoveries and findings.
“With new funding from the Helmsley Charitable Trust, we are really able to transform PIANO and try to reach a broader group of patients and answer more challenging questions. These questions include the safety of small molecules (tofacitinib, upadacitinib, ozanimod) and the newer biologics (ustekinumab, vedolizumab, risankizumab) as well as expand into studying the placenta and the impact of IBD, the response to COVID vaccine in pregnant IBD patients, and following children out to 18 years of age to look at long term safety and outcomes. The more you know, the more questions that come up.”
What’s new with PIANO
All women with IBD who are pregnant in the United States are invited to enroll. Specific interest in enrolling women on newer biologics (Stelara, Skyrizi, Entyvio, biosimilars) and small molecules (Xeljanz, Rinvoq, Zeposia) even if it was within 3 months of your last menstrual period but not during pregnancy. PIANO 2.0 is also expanding to look at the safety of aspirin in pregnancy (to reduce the pre-eclampsia rate) and well as how IBD women heal after a c-section and vaginal delivery.
There are new and improved patient and site interaction updates as well. There’s now a patient portal that enables women to enter their data directly, a Twitter page (@PIANOIBD) for research findings and updates, and a website with outcome data right at your fingertips.
The medical sites participating have also expanded to include USC, University of Miami, and the University of Maryland. Dr. Mahadevan says they realized most patients in PIANO were Caucasian and of higher socioeconomic status.
“We know pregnancy outcomes differ by race and socioeconomic status and we need to understand if that also applied to IBD pregnancies – does it make those differences more extreme or is there no impact? By expanding to sites with a far more diverse population, we will be able to better answer those questions.”
As far as the Patient Portal, rather than filling out paperwork and participating in phone interviews, now women simply answer questionnaires on the portal when they enter the study, every trimester, after delivery, at months 4, 9, and 12 of baby’s life and then once a year thereafter. Thanks to the Patient Portal, women can enroll remotely across the United States and don’t have to be at an IBD Center to participate.
Pushing the research further
The overarching goal with PIANO 2.0 is to gather data points from newer biologics and biosimilars and look at the safety of small molecules. So far, 2,012 women with IBD have participated in PIANO. The hope is to have at least 150 newly pregnant women participate each year.
So grateful I was able to participate in the PIANO study during this pregnancy, with my youngest child, who is nearly 16 months.
“With biologics we generally feel they are all low risk as they won’t cross the placenta in the first trimester when the baby’s organs are forming. Small molecules, however, are more concerning as they will cross during that key period of organogenesis. However, for some women that is the only therapy that works, and they must make difficult decisions,” explained Dr. Mahadevan.
Once the baby is born, the research will look at if the child develops any infection issues, malignancies, neurological issues, and immune diseases like IBD. There are some questions about basic diet as well. Having long-term data and a fuller picture of the future for IBD moms is priceless. By participating we’re truly paving the way for IBD moms now and in the future.
Dr. Rishika Chugh recently shared a presentation at the American College of Gastroenterology conference that Dr. Mahadevan co-authored that looked at data on 47 women on Stelara (ustekinumab) and 66 on Entyvio (vedolizumab). Those women were compared to moms not on biologics/thiopurines and those on anti-TNF therapies.
“There was no increase in harm from being on Stelara or Entyvio compared to those groups. Interestingly, those on Stelara had lower rates of preterm birth and C section. Numerically, there were also less infections on Stelara though that was not statistically significant.”
Participate in a Townhall Discussion with Dr. Mahadevan: Starting a Family with IBD: What Men and Women with IBD Should Know about Conception and Pregnancy
Save the date for a discussion taking place Thursday, December 15 at 6:30 pm Pacific Time. Click here to register for the free event.
I’m excited to be serving as one of the IBD patient advisors on the project, alongside fellow IBD moms Jessica Caron, Brooke Abbott and Amber Tresca (from IBD moms). We’re looking forward to providing the patient perspective and helping to guide the conversation. Jess and I were on biologics in pregnancy and have previously participated in PIANO. I had the opportunity to participate in IBD research studies with all three of my kids and it’s extremely empowering to know you are helping to change the future of care for women in our community and providing women with the added support we need while navigating pregnancy and motherhood with a chronic illness.
They call themselves “Propellers.” They’re a team of volunteers, made up of IBD patients and caregivers who created a non-profit called Propel a Cure for Crohn’s in 2016. They are laser focused on preventing and curing Crohn’s disease and, on the heels of their first research project funded at Stanford University in the world-renowned lab of Professor Mark Davis, they’re now determined to make a meaningful difference through their Roadmap to a Cure for Crohn’s effort. During this month (September 2022), they’re aiming to raise $50,000 to help get their latest project off the ground and to provide a solid foundation to bring their global team together.
This is a grassroots effort fueled by patient and parent volunteers. Patients and caregivers have an opportunity right now to directly influence a brighter future without Crohn’s! This is a peer-to-peer fundraiser—it’s not just about the monetary donations, but also sharing the message with others far and wide. Not only are international researchers involved, there are people all over the globe participating. In addition to the English-language campaign, there are also Swedish and Portuguese online campaigns running as well.
The Patient/Caregiver Perspective
Ildiko Mehes recalls what it was like when her 9-year-old daughter received her lifechanging Crohn’s disease diagnosis in 2017.
“As a parent, a serious diagnosis like Crohn’s is a huge shock, and it’s absolutely devastating and heartbreaking. Even during periods of remission, we are always on high alert and waiting for the other shoe to drop. At diagnosis, my whole world stopped, literally and figuratively. As irrational as it sounds, as a parent, you wish the rest of the world stopped with you to help you address the crisis. You wish that all of modern medicine rolled up their sleeves and urgently worked together to precisely diagnose the problem and bring her back to long-term health.”
As a caregiver, Ildiko has a unique sense of urgency and determination. She feels we need and can do better for IBD patients.
“When an otherwise healthy child, with no prior medical history, suddenly presents with IBD symptoms during a routine winter virus, you ask yourself “what caused this switch to be flipped?” Not having any answers to the underlying mechanism of disease onset or perpetuation, having a trial-and-error approach to disease management, and being forced to consider serious immunosuppressive medications with modest clinical trial benefits feels unacceptable as a parent. This is what drives me.”
As a pharmaceutical executive with more than 20 years of experience, Ildiko uses that unique skill set to go after complex and difficult goals with Propel a Cure and feels a deep sense of obligation to help our community.
“While there is excellent research ongoing in IBD, it happens in silos. It lacks global coordination and a plan. We don’t yet understand many basic things about Crohn’s. We are all just hoping for a “eureka moment” that hasn’t come over the last 100 years. We are continuously enticed with headlines of a “promising” new pathway or new drug candidate, usually in mice. And then that great idea sits there, with no progress made, a decade or more later. I know we can do better,” she said.
Natalie Muccioli Emery was diagnosed with Crohn’s disease in 2011 and she’s also a Propel a Cure Board member. She started dealing with abdominal issues 26 years ago. Being a veteran patient has provided her with perspective about how far treating and managing IBD has come and how far we still have to go.
“Propel a Cure was the first organization whose mission resonated with me. I appreciate their mission to cure Crohn’s Disease, but I even more appreciate the fact that they have laid out a plan as to what the areas of knowns and remaining unknowns are in their Roadmap to a Cure for Crohn’s project. Complex issues like Crohn’s Disease will take a collaborative and systematic approach to address, and this cause has captured that,” said Natalie.
Not only is Natalie an IBD mom, she’s also an IBD aunt!
“I believe that as an adult with IBD, the way I embody the role of a “Crohn’s Warrior” is not for myself it is for the next generation. I have “been there and done all that” with Crohn’s. But just because I did it with Crohn’s doesn’t mean the next generation should have to. I grow increasingly concerned when I see the rising rates of IBDs like Crohn’s in younger people. I believe the rising rates of Crohn’s should create a sense of urgency and a desire for a better future.”
Putting the puzzle pieces together
The Roadmap to a Cure is an ambitious project but one that is needed to drive real progress toward cures and prevention of IBDs, not just talk about “cures” in some very distant future. Ildiko says the brilliant clinicians and scientists she has gotten to know all tell her that getting to a cure will take a grassroots effort, global collaboration, and involvement of patients and caregivers.
“We at Propel a Cure are deeply committed to doing exactly that. The first step in our project is to systematize what we already know about Crohn’s today. We know a great deal, thanks to research. But when we are talking about complex fields like genetics, epigenetics, immunology, microbiology, epidemiology, multi-omics platforms and artificial intelligence, etc. there is no way any one person or group can know everything. We need a large global group of dedicated and brilliant experts to put all the puzzle pieces we already have on one table so we can begin to then put the pieces together,” she explained.
Grabbing the attention of medical professionals and researchers
Propel a Cure grabbed the attention of Dr. Bram Verstockt, MD, PhD, Department of Gastroenterology and Hepatology, University Hospitals Leuven, on social media.
“I truly like the concept of joined forces across various stakeholders, including patients and caregivers. As clinicians and scientists, we can have ideas about how to move forward based on experiences and interactions with patients on a daily basis. However, the next step really is to involve patients actively in many of these projects, as is currently the case with Propel a Cure,” said Dr. Verstockt.
The “Roadmap to a Cure” aims to bring together expertise across many different fields and niches in IBD.
“Over the past decades, a lot of scientific evidence has been generated in multiple domains of Crohn’s disease, so now it’s time to bring all that evidence together and truly connect the dots. Only by doing so, one might unravel knowns and unknowns and highlight where the remaining key gaps are, and we can define the priorities and strategies of how to fill these gaps to significantly advance the field, to improve the lives of patients with Crohn’s disease,” said Dr. Verstockt.
Where the roadmap can take us
After the initial step of putting together the state of the art, the next step is identifying gaps in our knowledge: what puzzle pieces do we still need? The third step is to develop the plan, or the Research Roadmap, to get from what we know today to developing cures and prevention strategies.
“We truly believe in a future where we can prevent and cure Crohn’s and eliminate so much patient and family suffering,” said Ildiko.
The reason this requires a grassroots effort and all of us patients and caregivers to fund it, is that otherwise the current system largely doesn’t provide incentives for new ideas or cures or global collaborative efforts of this magnitude. A recent paper discusses how the same ideas have been funded for decades, with limited progress and that we urgently need new directions.
Ildiko believes the current research incentive model is broken. “If we want true progress and cures for Crohn’s and other IBDs, we need a new collaborative model among IBD foundations/nonprofits, patients, caregivers, researchers, clinicians, and others. I believe this can become a model for other chronic and immune-mediated diseases.”
Click here to watch a video where Ildiko explains the Roadmap to a Cure project further.
Hopes for the future
“I would really like to see more key opinion leaders be brave about acknowledging the risks and limitations of current therapies, avoid putting lipstick on a pig when discussing some newer drug candidates in trials with lackluster results and the same mechanisms, dispense with biased headlines like “safe and effective” when the data is much more nuanced or unclear, and openness to “outside-the-box” ideas, like microbiome manipulation, including via diet, infectious triggers like Epstein-Barr virus in Multiple Sclerosis, vagus nerve stimulation, Fecal Microbiota Transplant (FMT), hyperbaric oxygen, etc. and also adopt routine monitoring via intestinal ultrasound for many patients,” said Ildiko.
As of now (September 12, 2022)—more than $26,609 has been raised!
“I have been overwhelmed by the response so far, as has the entire Propel team. People are really connecting with our mission. We are getting donations from so many states and countries! We have received more messages of profound thanks and hope than I can recount. This fuels us so much,” said Ildiko.
Natalie feels a wide range of emotions each time she sees a donation come in or the campaign shared across social media.
“I go from feeling hopeful, to introspective, to sad. I truly wish we did not have to do this campaign and that in 2022 we knew what the underlying cause(s) of Crohn’s are, and that safe, effective, reliable treatments were available for all Crohn’s patients. But here we are. Crohn’s is still very much part of the lives of patients and caregivers, and we need to take action to change that. I am so grateful for the outpouring of support we have received so far, but there is more work to be done!”
Propel a Cure has virtually no overhead fees or salaries, so every single dollar donated to Roadmap for a Cure goes to research.
“We are all volunteers who work out of our homes. The donations will be put towards collaborative research teams worldwide. Each team will lead a contributing area to the development of Crohn’s Disease (environment, microbiome, immune system etc.) and highlight where the gaps in knowledge remain,” said Natalie.
“The ultimate dream obviously would be to cure and if not, to significantly improve the quality of life for millions of patients worldwide,” said Dr. Verstockt.
Click here to donate to this incredible cause or to join their team.
Innovation and changes in healthcare are propelled by patients and caregivers speaking up about improvements that can change the way IBD is treated and managed. This week on Lights, Camera, Crohn’s we hear from pediatric gastroenterologists Dr. Michael Dolinger, MD, MBA, Advanced Pediatric Inflammatory Bowel Disease Fellow, Ichan School of Medicine at Mount Sinai and Dr. Mallory Chavannes, MD, MHSc, FRCPC, Pediatric Gastroenterology, Hepatology and Nutrition, Children’s Hospital Los Angeles about the benefits of Intestinal Ultrasound (IUS) becoming a part of routine care, regardless of age.
The goal of IUS is to utilize a non-invasive method to monitor disease activity over time and it’s considered to be more precise than endoscopy in identifying both disease location and characterizing the severity of IBD. The IBD community—both patients and caregivers—can help fuel the adoption of IUS and gain access to receiving more information about their disease activity than ever before.
What is Intestinal Ultrasound (IUS)?
Intestinal Ultrasound (IUS) is an abdominal ultrasound performed during a routine clinic visit without preparation, fasting, or contrast to assess both the colon and the small intestine (terminal ileum most frequently) for the presence of disease activity. Probes are placed over the abdomen and the provider looks at images of the small and large bowel.
“The beauty is that, unlike procedures and other image modalities available to assess disease activity of inflammatory bowel disease, IUS can be performed without any preparation or fasting,” said Dr. Chavannes. “In the setting of active disease, patients can have a thickened appearance of the wall of the bowel (termed increased bowel wall thickness) in both the small intestine and the colon, which can be detected via ultrasound.”
In addition, by using color Doppler, a feature that assesses the velocity of blood flow within and around the bowel wall, gastroenterologists can demonstrate inflammatory activity in the bowel wall. IUS can also detect IBD complications, such as fistulas, abscesses, or strictures (narrowing) of the bowel.
“Our expectation is that, with effective therapies, the aforementioned features of disease activity should improve or even disappear over subsequent clinic visits. If they do not, we now have an objective tool available in the clinic that can assist clinical decisions, such as ordering further investigations or even optimizing or changing therapy. Improvement of bowel wall thickening or decrease in color Doppler signaling is a reassuring sign that treatment is working. Lack of improvement signifies that optimization or changes in therapy should be considered,” explained Dr. Chavannes.
“Intestinal ultrasound is precise, we monitor bowel wall thickness down to the 0.1 mm. We are now able to make informed decisions with patients together, assessing their disease objectively in real-time so we can be aligned with our treatment goals. This reduces misunderstanding and may lead to better treatment adherence and improved outcomes,” said Dr. Dolinger.
Why the delay in the United States?
While IUS isn’t the standard of care across the world, it is used in several Canadian IBD centers and in Europe (Germany, Italy, Norway, the Netherlands, and Australia to name a few). However, there are still many areas of Canada and countries in Europe where this is not used as part of routine IBD care.
“There have been several barriers to adoption in the USA, the biggest of which are reimbursement and the lack of training/expertise. However, that is changing, as there is a tremendous amount of interest from most major academic centers,” said Dr. Dolinger. “Through the International Bowel Ultrasound Group (IBUS) there is now a formal training, while intensive, that can be completed by anyone willing in the USA, which did not exist 5 years ago.”
IUS fits perfectly in the treat-to-target algorithm by adopting a monitoring strategy that helps to prevent flares and bowel damage.
“There is no other test for patients to see their disease dynamically with a gastroenterologist in real-time, which enhances shared understanding and informs decision making like never before. All of this will help break the barrier in the USA and around the rest of the world,” said. Dr. Dolinger.
A study conducted in 2016 explored why IUS is not standard of care in the United States. The
authors surveyed nearly 350 physicians, of which 40% were pediatric gastroenterologists. Although a minority of gastroenterologists were using ultrasound to assess and monitor IBD (either bedside or within the radiology department), over three-quarters expressed interest in using it more.
“The main limitation identified or perceived by gastroenterologists who responded to this survey was a concern for inter-observer variability, a lack of familiarity with ultrasound indications and techniques, and a lack of interest and access to pursuing additional specialized training. In addition, the survey identified a common message that I have received previously from some radiologists; that other modalities are more precise or effective in assessing IBD. All these reasons can hinder interest and implementation,” said Dr. Chavannes.
However, considering the multi-center effort in disseminating training, knowledge, and engagement that has been ongoing in the USA in recent years, Dr. Chavannes is hopeful that IUS will rapidly become the standard of care nationwide.
How Children’s Hospital in LA and Mount Sinai in New York Use the Technology
The Henry and Elaine Kaufman Intestinal Ultrasound Program at Mount Sinai is one of the first in the country to employ the training of gastroenterologists and regular use of intestinal ultrasound for both children and adults routinely in the IBD center for non-invasive disease activity monitoring.
“This would not be possible without the leadership of Dr. Marla Dubinsky, who has worked painstakingly hard to bring this to patients at Mount Sinai, overcoming every barrier to lead the way in the USA. We would like patients everywhere in the USA to be able to have tight control non-invasive monitoring with intestinal ultrasound and in turn, are working with International Bowel Ultrasound Group (IBUS) to host the first hands-on training in the USA at Mount Sinai in the fall. We have faculty from around the country signed up to learn and this will hopefully begin to fuel further adoption,” said Dr. Dolinger.
Intestinal Ultrasound was introduced at Children’s Hospital in LA in the summer of 2020. This was incredibly helpful during the pandemic when access to endoscopy time was difficult, considering cancellations due to active COVID infection and decreased daily procedures to allow for intensive cleaning protocols.
“We integrated using IUS for all patients coming to the pediatric IBD clinic. We have seen an immediate benefit in how we approach patient care and how timely clinical decisions can be made right at the time of the clinical encounter. One example is for patients presenting for a second opinion; these patients usually present with ongoing symptoms of varying degrees, yet incomplete or dated documentation of endoscopy, fecal calprotectin (a stool test helpful in indicating inflammation), and blood work,” said Dr. Chavannes.
During the visit, IUS gives an opportunity to understand the source of the symptoms experienced by patients and the degree of ongoing inflammation. Then, clinical decisions can be made that day, eliminating the need for additional testing. Dr. Chavannes says IUS even helps ease the discussions she has with parents and families.
“Many parents are stunned by the images they see and the changes over time. At the same time, they also notice when there is little difference from one appointment to the next, understanding the reason we are making the changes to the management plan that follows,” said Dr. Chavannes. “IUS has been invaluable for children under 6 years of age. This vulnerable population needs frequent objective reassessments, which is not possible otherwise. Using MR-Enterography would require general anesthesia, and access can be difficult. Similarly, for endoscopy, the prep can be poorly tolerated, and it also requires general anesthesia. IUS is non-invasive, painless, very well tolerated in young children, and available in real-time. Therefore, both parents and children are quite satisfied with their experience with IUS.”
Targeting treatment through IUS
Monitoring symptoms alone is not effective in reaching deep healing of disease in IBD, as many patients feel well despite having ongoing intestinal inflammation. IUS evaluates the inflammation that occurs within the thickness of the bowel wall (transmural inflammation).
“We often find that ultrasound is the only tool that shows continued inflammation when patients are in remission and labs have normalized. Optimizing therapies based on persistent inflammation seen on ultrasound may prevent us from falling into the trap of thinking our medications are working when our patients feel better and thus lead to better outcomes by not missing persistent inflammation that we have continued to miss with traditional monitoring strategies,” said Dr. Dolinger.
Although there are no fully established algorithms for the frequency of monitoring IBD using IUS, the best approach appears to have a baseline IUS at the time of IBD diagnosis or in the context of active symptoms or elevated inflammation markers on blood work (a flare).
“Then, the clinician can understand the features to follow over time. A repeat IUS can be performed at the end of induction treatment to assess how effective the management is. It would represent 6-8 weeks after the treatment was started. Provided that there is a marked improvement, the subsequent evaluations with IUS can be done every 3-6 months unless there are new concerns, with the closer timeline early in the disease course,” explained Dr. Chavannes.
In pediatric patients, this routine ends up matching most routine clinic visits. Therefore, as IUS becomes standard practice, and depending on how a patient is doing, their symptoms, and last assessed disease activity, patients can expect IUS as often as with each clinic visit. This modality would complement blood work and calprotectin stool tests in informing about disease activity and for complications of disease or flares.
What the future holds
Since a few IBD centers in the United States have already implemented regular IUS in their practice and have been disseminating knowledge about this technique, there is growing interest from pediatric providers to join the movement as well.
“Considering the challenges pediatric providers face in access to complementary imaging, operating room time, anesthesia exposure to endoscopy, and even the tolerance drinking contrast for radiology studies, IUS offers a fantastic way to assess disease activity in the pediatric IBD population. I am excited about the number of pediatric centers that have reached out about getting expertise in this field. The key is to promote buy-in from leaders in each institution to get the time and resources required for training and implementation,” said Dr. Chavannes.
Advice for patients and caregivers
It doesn’t hurt to bring up IUS at your next clinic appointment to gauge where your care team stands and if anything is in the works.
“If your provider is unaware of IUS and its benefit, it would be great to talk to them about the International Bowel Ultrasound Group. The curriculum for getting training involves three modules: an introductory module, a 4-week hands-on training at an expert center, and a concluding module and examination part of the European Crohn’s Colitis Congress,” said Dr. Chavannes.
She went on to say that hearing this request from patients may motivate administrators to provide the necessary time clinicians who are interested in getting expertise to implement the tool at their center would need.
Dr. Dolinger believes most major academic IBD centers in the United States will rely on IUS in the next 3-5 years.
“I would like to remind patients to be patient with their providers. Ensuring correct training and standardization is essential for adoption in the USA and this takes time and rigor to be done right and change the monitoring algorithm which has not been done in many years,” said Dr. Dolinger. “I began training in 2019 and it wasn’t until the second half of 2021 that we began using it very routinely for decision making, taking 2 years to become an expert. So, this will happen, but it will take some time.”
Patients and parents are big fans
The safety and efficacy of IUS can’t be matched. It’s also a big-time saver for everyone involved. A bedside ultrasound can be performed in a range of 20 minutes for the first thorough assessment, while an even more focused exam in a known patient can take less than 10 minutes.
“Both parents and children have been quite satisfied after their experience, as children can go back to school after the clinic despite undergoing this examination. Furthermore, the time saved in skipping additional appointments with the radiology department or procedures can be invaluable,” said Dr. Chavannes.
For parents, the imaging provides reassurance when there are improvements or when there are non-specific symptoms, yet the IUS is normal. IUS also bring validation when there are abnormal findings and helps to provide an explanation for why children are feeling a certain way.
“Children appreciate that it does not hurt and takes little time in addition to their clinic visits. In addition, they may not require additional appointments in radiology or endoscopy. Parents who had an opportunity of experiencing an ultrasound often request it afterward as part of their clinic visits. These families are more engaged and participate in shared decision-making. I am pleased and impressed at the engagement that actually “seeing” the disease together brings from families,” said Dr. Chavannes.
While the push is for IUS to be available to all IBD patients, both children and adults, it’s specifically beneficial for the management of pediatrics as it provides the unique opportunity to prevent bowel damage for a person’s entire life and reduce the need for invasive procedures, anesthesia, and sedation. IUS has the potential to alter scoping schedules in the future. While it will not replace the need for colon cancer screening or the assessment of mucosal and histologic healing, IUS can reduce the need for further follow-up scopes once those targets are achieved in between the need for cancer screening.