This article was sponsored by ImYoo. All thoughts and opinions shared are my own.
Precision medicine is a common term we hear when it comes to treating IBD now and into the future. But have you heard about citizen science as it relates to IBD? Citizen science gives everyone a chance to play an active role in research. Whether that’s coming up with research ideas or taking part in the experiments themselves, citizen science makes it possible for you to have a direct impact. A company spun out of Caltech is taking citizen science to a whole new level. ImYoo is debugging the human immune system by using at-home blood collection kits and single RNA sequencing to discover insights about autoimmune diseases.
Tatyana Dobreva and her co-founder, David Brown, worked at NASA prior to switching gears from space to focus on biotech.
“The COVID-19 pandemic accelerated the process and highlighted for us what was missing. Since the pandemic, people are paying more attention to their immune systems. Immunology is still as much a mystery as outer space, so that was the next frontier we wanted to get involved in. We feel that the best way to take on that challenge is by building a database across time, for every individual – that is what can make personalized medicine possible and that is why we’re so focused on making this research accessible.”
Since IBD presents uniquely in each person and changes over time, it’s a rollercoaster journey of highs to lows, flares to remission. With all the twists, turns, and complexities that ulcerative colitis and Crohn’s create for each of us in the patient community, following a roadmap can seem impossible.
“Precision medicine tries to apply scientific tools to take out some of this guesswork. A lot of those tools look at the genetic material you inherited from your parents. We’re adding another tool to that kit by looking at the expression of those genes. For IBD, we want to figure out which genes and cells are acting up during a flare,” said Tatyana.
By answering these key questions, clinicians have told Tatyana that it will help gastroenterologists make more informed decisions when it comes to treating and managing IBD and patients can feel more empowered every step of the way. While making the decision to start a biologic can be overwhelming for patients, precision medicine is a way to have powerful data to support the choice to move forward with that treatment plan.
Tracking the immune system over time
ImYoo’s focus is tracking a person’s immune system over time. Researchers do this by looking at RNA expression. Tatyana shared a fantastic analogy with me. She said that DNA is like the menu you get at a restaurant, RNA is your order, and proteins are your final meal.
“There are a lot of companies that look at your blueprint, or in this case your menu – all the possibilities. Our team at ImYoo looks at your cells’ orders over time. That way we can capture how the different immune cells in your blood are changing,” said Tatyana.
IBD flareups are of specific interest to both clinicians and patients. Even after living with Crohn’s disease for more than 17 years, the unpredictability of the disease is still one of my main struggles. The looming thoughts of a flare are always with you.
“There is not much literature on what happens in the immune system during a flare, and we think there are a lot of powerful biomarkers that could be discovered if IBD patients could track themselves during flares and when they feel “normal.”Our IBD study will ask IBD warriors to sample themselves both during and outside of flares,” said Tatyana.
ImYoo built a solid foundation for studying autoimmunity because researchers were able to build a database of “normal” immune systems.
“Being the first to do this for single-cell data means we can provide a helpful reference to enable more single-cell studies for the future. By having a large database of “healthy” immune systems, we can provide more context as to what having a flare means with respect to dysfunctional immune systems.”
How IBD Patients Can Participate
ImYoo’s IBD study was inspired by conversations researchers had across Reddit and in a Facebook group. Patients in the community offered invaluable insights about what to research.
Emily Harari works as a liaison between the scientific team at ImYoo and the patient community. She says if a person demonstrates interest in participating in the study, a screening process will take place to determine eligibility.
If you qualify, you are enrolled under an ethics-approved study protocol and sent a kit that includes a virtually painless capillary blood self-collection device called TAP II. The device allows you to participate in immune studies in the comfort of your home and send capillary blood samples directly to the ImYoo lab. The TAP II is placed on the upper arm and sticks with the help of a gentle adhesive, it barely penetrates the inner layer of your skin and feels like a suction cup.
“For the IBD study, we ask you to collect a few samples when you’re feeling well and a few samples when you’re flaring. The TAP II device is virtually painless and takes just a couple minutes to use. You’ll mail us the tube of your sample with the packaging we provide. After several weeks we’ll report updates from the lab and several weeks after that we’ll release our study’s findings to the community. Since the community is crowdsourcing the study for us, the least we can do is share what we discover. For example, we may find a new gene or an immune cell marker that helps your doctor better treat your flares,” said Emily.
The Power of Crowdsourcing
The best part about a crowdsourced study is that anyone can make a difference. By visiting the ImYoo crowdsourcing page and selecting “Participate in this Study!” you are making a powerful impact. The more people with IBD who join, the more attention we can attract for crowdfunding.
“If you’re eligible for the IBD study, we’ll reach out after we’ve hit our crowdfunding goal. To help us reach our goal, you can express an interest to participate or pitch in a donation to one of our Champions’ campaigns. There’s a network effect we’re going for, one person tapping into their community can open so many doors.”
If you’ve ever been told your labs or scopes look normal or there’s nothing more to do when you’re suffering through IBD, it’s simply not true. Everyone is on their own health journey and deserves a chance to take control of it.
“That’s why ImYoo is excited to put innovative science in peoples’ hands. This research isn’t possible without the IBD community, which is why we invite IBD Warriors to pitch in however they can – skip a coffee and donate $5, express interest to participate, or simply share to your network,” said Emily.
“Our goal is to empower the IBD community with more powerful tools. One of the biggest questions we hear from IBD folks is, “Am I in remission yet?” You might be feeling fine and think you’re good, meanwhile your immune system could be attacking your colon,” explained Tatyana. “We hope to help people track their immune systems when they are most vulnerable.”
By enabling the IBD community to crowdsource our own studies, the power is in our hands. ImYoo wants to explain their research findings every step of the way and keep people engaged, because it really is a partnership. From this IBD study, the ImYoo team wants to prove that the IBD community can make their own research happen. By studying flares, the hope is that sequencing the state of individual immune cells will uncover predictors and targets for more accessible precision medicine.
Connect with ImYoo, Follow and Participate in the Research
When it comes to the biologic, Humira (adalimumab), I am somewhat of an OG. I’ve taken Humira to manage and treat my Crohn’s disease since July 2008. We go wayyy back. Since my first loading dose 14 years ago, I’ve had hospitalizations, had bowel resection surgery, gotten engaged and married, traveled, worked full time, had three children, breastfed, been a stay-at-home mom…the list goes on. I’ll never forget how overwhelming it felt when I was lying in a hospital bed with an abscess the size of a tennis ball in my small intestine and when my GI at the time told me “It was time to break out the big guns.” The big guns being biologics.
My mom and I were upset. We were frantic. We were Googling. We were fearful of what this would mean for my childbearing years. I couldn’t fathom the thought of giving myself injections or getting infusions. My world came to a standstill. In that moment, I would have given anything to have a resource like this. An article that outlines patient experiences across the board. The good, the bad, the ugly. I write these articles, so you feel empowered and educated when you take the plunge or when you are forced to switch medications because another biologic fails you. I write these articles, so you feel confident in making informed choices and realize that the “big guns” are oftentimes necessary and not as scary as they sound.
As you read this article and others like it, please remember these are individual experiences. Just because one person had a terrible response or reaction doesn’t mean you will. Just because I haven’t had any side effects and have been able to stay on Humira for more than 14 years, doesn’t mean the same will be the case for you. Use these experiences to level your expectations and have a better grasp of what it’s like to be someone with IBD on a biologic drug and make an informed choice with your gastroenterologist.
If you haven’t done so already, be sure to check out previous Patient Experience articles I’ve shared on Lights, Camera, Crohn’s about:
For those who are “new” to Humira, those who are preparing to do their loading dose, or those who aren’t familiar with the drug—in the United States a new and MUCH improved Citrate-free formula came to market for pediatrics and adults in late summer/early fall 2018. I did my first Citrate-free or as many of us call them, “pain free” injection in September 2018 while pregnant with my second child. If you’ve been on Humira for a long time like me or tried it prior to that time, you know how painful the injections used to be and how much easier they are now. It’s a gamechanger. The loading dose used to be four injections—all in the same sitting that felt like liquid fire were going through your leg or abdomen. Fast forward to 2018, not only is the needle gauge smaller, but the formula no longer stings. Click here to watch the video of me experiencing Citrate-free Humira for the first time while pregnant.
I went from dreading my injections (even a decade in) to doing injections on my couch and smiling ear to ear while my kids watch me because I feel next to nothing. This is important context for this article. Some of the experiences you will hear will be from people who never had a chance to experience Citrate-free Humira, and others who say the shot is “easy” to do most likely started or were switched over to the pain-free version. This change in the formula has been an incredible win for anyone on Humira in the United States. The loading dose not only won’t hurt but is only two injections now versus the original four. The challenge is getting used to the mechanics of doing a self-injection and getting into the right headspace each time you’re due for a dose. Regardless of whether it hurts or not, you are still injecting a heavy-duty medication, which suppresses your immune system, into your body. I’m often asked if I get “sicker” being immunocompromised and being a mom of little ones—my answer to that is no. I am mindful of washing my hands and not eating or drinking off anyone. My GI has me do “safety labs” every three months to monitor my bloodwork, along with an annual colonoscopy.
Debbie: “I was on Humira for four years. I responded well at first and liked the ease of doing injections myself. The Citrate-free version was much better and less painful than the original version. I unfortunately ended up developing antibodies and have been switched to Stelara. I didn’t have any side effects with Humira other than some itchiness at the injection site. Ice helped a lot with that.”
Melanie: “After a reaction to Remicade, I was so anxious to try another biologic. This was in 2009 and Humira hurt so much. I had a massive panic attack trying to do the loading dose of the original version. I was 19 at the time. I couldn’t continue with it. Now, I’m on Cimzia, but had to take a mental health break from biologics for a few years.”
Brad: “I started Humira back in March of this year. It’s been a complete gamechanger for me. Humira has me in clinical remission as of my last colonoscopy. I don’t have much reaction to it. Sometimes, the injection can hurt a little bit, but usually not at all. I’m shocked at how easy it’s been. I was originally very nervous about starting an injectable.”
Jenn: “Humira was traumatizing. It took well over a year for me to self-inject without stressing and crying beforehand as the injection hurt so much. While it did provide relief from symptoms for a while, the reaction I ended up getting was significant, and impacted my ability to live normally. So not only had my Crohn’s symptoms returned, but they were also joined by additional symptoms caused from a reaction I was having to the medication. I will never not be a proponent of taking meds as they do help, but I will also never forget the experiences I lived due to them.”
Natasha: “I was in the pediatric trials for Humira. I don’t remember it doing much, but almost 15 years later, I’m still traumatized by the trigger mechanism and feel the phantom pains in my legs from doing them for so long. Anytime a new medication it brought up and it’s a shot, I ask if there are self-administered options vs the auto injector. The PTSD is bad.”
**It should be noted Humira can be administered with an auto-injector pen (where you press down on a button and there’s a clicking sound) or with a syringe where you draw up the medication. I have only used the auto-injector and prefer the ease of it, but it’s all personal preference and what you are comfortable with.**
A mixed bag of experiences
Sofia is now on Stelara after having surgery to remove some of her bowel. When she thinks back to her time on Humira, it’s not a pleasant memory.
“I experienced all the normal flare up symptoms while taking Humira and gained a lot of weight. I just remember my self-esteem plummeted as well as my hopes for remission.”
Kathy: “I was on Remicade, but I’ve been on Humira now for five years and have had great results with minimal side effects.”
Kaitlyn: “I have been on Humira for a few months to treat my Crohn’s disease and Hidradenitis Supprativa and it has been life-changing. My Crohn’s is in microbial remission, and I no longer have to get weekly, painful steroid injections for my HS.”
Jessica: “I’ve been on Humira for four years and my last colonoscopy showed there was mucosal healing and no active Crohn’s. I inject every 14 days and it has gotten easier, especially when I inject and tell myself that it is healing my body. Then, I don’t feel the shot. I’m very thankful for it!”
Myisha was on Humira for a year and then had a major allergic reaction.
“The last injection I gave myself, my face, lips, and mouth swelled up and I got lightheaded. My husband immediately called my GI and I had to be given an EPI pen along with 4 Benadryl intravenously after being rushed to the emergency room. I experienced hypersensitivity anaphylaxis and angioneurotic edema.”
Keyla: “When I was on Humira, it made me lose my hair. I felt terrible on it, and I never noticed much improvement with my IBD.”
Danielle has struggled to find a biologic that manages her disease. Both Humira and Entyvio failed her. She’s now on Stelara.
“I was on Humira for three months in 2021. It worked amazing right off the bat, then suddenly I had no response whatsoever. The injections were quite traumatic for me as I had one injection needle fall apart as I was giving the injection.”
Sarah: “Humira has improved my life and helped manage my Crohn’s symptoms and allowed me to eat a wider variety of foods then when on previous medications. However, there have been some compromises on my part. I’ve dealt with some bad injection site reactions that have caused me to have to take allergy medication prior to administering it to help manage the reaction. I’ve also experienced severe sinus congestion and uveitis that I did not have prior to taking Humira. I’ve lost some sense of smell due to how bad my congestion can get, and I can’t touch or rub my eyes without risking a flare up of uveitis. Overall, I would say that it has been worth taking Humira. I’ve learned to manage my side effects and have gotten over my fear or self-injection.”
Catie: “My experience with Humira was good at the beginning. The medicine helped me achieve remission. The injections were always so painful no matter what tricks I tried. I ended up getting drug-induced lupus from Humira, so I went off the drug. The drug-induced lupus took more than a year to recover from—it was awful.”
Hayley: “I was on Humira for a year and was doing great on it, practically in remission. Unfortunately, I developed psoriasis (which I’ve been told is a rare allergic reaction to the drug itself). My sister who has Crohn’s was also on Humira and had the same reaction. I wish I could’ve stayed on it longer because it was easy and helped me so much, but unfortunately, I had to come off it. It was my first biologic and gave me a lot of hope!”
Krista: “I was on Humira for about 6 months. It was working great—other than extremely painful injector pen that I dreaded using every month. I started to develop scaly patches on my legs, back, stomach, and scalp. My hair started falling out where the scaly patches came up on my scalp. My dermatologist thought I had biologic-induced psoriasis, so I stopped taking it. My biopsies came back negative for psoriasis, but I still ended up switching medications.”
Melissa: “I was on Humira in the past. It didn’t work for me and caused me so many issues. My body itched so badly while on it. I would scratch sores on my body from it. My joints ached all the time. And on top of it, my ulcerative colitis got worse while on it.”
Adriana: “I was on Humira for a year. I did weekly injections, but they wanted to increase my dosage to two injections. For me, it didn’t work (as with a lot of drugs I was on), but out of all of them, it worked best at making me feel better. I don’t remember having too many side effects from Humira besides slight bruising around the injection site, but definitely worth a try!”
Ellie: “I started Humira in 2019 after a four-month bout with steroids. I went into remission a month later after only two injections. I have remained in remission ever since.”
Dana: “I was on Humira for around 2 years. It put me into remission, and I was doing very well, but then I started to have Crohn’s symptoms. My doctor thought about increasing the frequency of my dosage, but my blood levels were adequate, and she didn’t want them to become too elevated with an increase in dosage. I also developed severe psoriasis on my scalp as a side effect. I ended up flaring and having to stop Humira to try something else.”
Jessica: “Humira has been great for me! Really no side effects. I did have to increase my dose to weekly because I metabolize medication too quickly.”
Phil: “I had a small bowel resection in 2004 and after a 10-year remission, my Crohn’s became active again. I was put on Humira, and it was amazing for about 7 years with a few side effects, biggest one being hypersensitivity to the sun. I miss being on Humira because it also helped my joint pain and psoriasis.”
Stacey: “Humira was my final effort to save my large intestine and felt pretty good on it! Aside from horrid cystic bacne, which isn’t listed as a documented side effect (but I swear there was an association there!), I had no side effects, and I felt great on Humira! It gave me a quality of life! I was on Humira when I made the hard choice to have a total colectomy, and the disease had spread since my scope four months prior. Goes to show that symptoms don’t always correlate with inflammation. But I’m grateful for my experience and the opportunity to safely take Humira.”
Pregnancy and motherhood with Humira
As an IBD mom of three, I stayed on Humira until 39 weeks pregnant with my oldest, and 37 weeks with my second and third child. I had scheduled c-sections with all three, so I was able to coordinate my injection schedule with my GI ahead of time. I breastfed my second child for about 6 months and supplemented and just finished exclusively breastfeeding my 14-month-old—all while on Humira. I have three, perfectly healthy children and had flawless, Crohn’s-free pregnancies. I also did not experience post-partum flares and I credit that to the fact I stayed on my medication and picked it right back up the day we brought the babies home from the hospital.
Check out these helpful resources for pregnancy and biologics and have long-term research that shows the safety and efficacy of staying on Humira through the entire family planning process, pregnancy, and beyond:
Dani: “My experience with Humira has been wonderful. I’ve been taking Humira for two years. The nurse ambassadors are so nice and helpful. I was nervous about the injections, but they really are so easy and don’t hurt. Humira has helped me to feel the best I’ve felt since my Crohn’s diagnosis 4.5 years ago. I stayed on Humira through my pregnancy, and I had no Crohn’s related issues during or after. It’s been a life-changer. Most days, I almost forget I have a chronic illness. I’m praying things stay like this, at least until we have another child.”
Stephanie: “I have been on Humira since 2016. I was diagnosed with ulcerative colitis postpartum after my first baby in 2015 and was incredibly sick. I had multiple blood transfusions, tons of steroids, etc. I had some reactions to Humira when I started taking it (skin rashes and almost withdrawal-like symptoms) before the two weeks was over, which almost presented itself like lupus, so I was put on weekly injections and have been doing that ever since. After I was put on Humira, it was a lifesaver. I felt the best I had in forever. Since having my second child in 2019, it’s been more up and down. At my next colonoscopy, we will look to see if I have inflammation still and if I do, I will go off Humira (which is so scary to me) and try something new.”
Katie: “I have been on Humira for 7 months. I was completely terrified to be on Humira, but I was so sick, and knew I needed to do something for not only myself, but my husband and my kids. Humira has gotten me back to the point of feeling back to my normal self. The only side effect I noticed for the first few injections is I would feel absolutely exhausted that next night. It’s super quick and I get on with life as usual!”
Sarah: “I have been on Humira for a little over a year now. I was on it while pregnant with my son. It was an easy process. But now that I’m 4 months postpartum, I am experiencing some weird side effects. My liver levels are elevated, and I am getting symptoms back. My GI and rheumatologist are thinking of moving me to once a week or adding another medication. I am fearful they will switch me off or add things and I won’t be able to breastfeed any longer. Humira has been wonderful, and I am just nervous my body has begun to build antibodies against it.”
Cece: “I have struggled with my ulcerative colitis symptoms on and off since I was 19. At 36 years old, after trying 3 years to get pregnant, I had a colonoscopy that revealed active inflammation. That was what finally pushed me to get on Humira. My symptoms settled down and luckily, I’ve been in remission and feeling great ulcerative colitis-wise through IVF, pregnancy, and breastfeeding.”
The Pediatric patient point of view
Emily is a 13-year-old who has been on Humira for three years. She says Humira has done a lot to help her get Crohn’s under control.
“Doing injections myself has helped. It feels better to “be in control” of giving yourself the shot. I’ve been having less stomach pains and less joint pains from Humira. My joint pain and stomach aches used to be really bad. I used to cry myself asleep at night because how bad the pain was for both my joints and stomach. Now that rarely happens. Yes, I still get joint pains, but not to the point where I start crying. I get a little tired after the shot, but it helps me a lot. So many positives.”
Celia is 15-years-old and started Humira in October 2021. About two months after her initial loading dose, she started to notice less bowel movements, but still had urgency and abdominal cramping. Her GI decided to increase her dose to 80 mg since her inflammation markers were elevated and she was flaring. (Typically, we are put on 40 mg injections, twice a month).
“I feel better! I still have my bad days and have had minor issues. I’m hopeful that this will be the medicine to get me into remission! On the mental side of things, I have struggled with injection anxiety. I have never been afraid of needles, and I’m still not, but I overthink every injection. That has been my greatest struggle on Humira, but I’m hopeful over time I’ll overcome it!”
Cindy’s 8-year-old daughter is on Humira. She says the various worries and challenges all give way in the end to gratitude.
“Humira is saving my daughter’s life and giving her a tremendous quality of life. Thirty years ago, an 8-year-old would have had such a different trajectory my she is experiencing and hopefully will continue to have. I love science.”
Struggles with access to Humira
Regardless of the biologic you are on, dealing with insurance, prior authorizations, and specialty pharmacies can make access to drugs like Humira a challenge. AbbVie (the maker of Humira) offers several programs to help streamline the process and take some of the burden off patients.
Once you enroll in Humira Complete, you are connected with a Nurse Ambassador who will speak with you directly (and even do in-person visits) to help you gain confidence and understanding about everything from administering your medication to any side effects you may be dealing with. Humira Complete offers a Patient Savings Card and Prescription rebates, and offers injection training through videos, an App to help you stay on track, and 24/7 availability should you need to reach someone. The phone number for Humira Complete is 1-800-4HUMIRA (1-800-448-6472).
Even though Humira Complete exists and has helped me many times, there are still many patients dealing with access issues or completely unaware of the fact that the programs and savings are available:
Emily: “I have been on Humira since October of last year and it has been both great and horrible for me. Remicade stopped working for me after 5 years and Humira was able to help calm down the flare I had been experiencing. I learned with time that at home injections weren’t something to fear. Humira is very convenient. Humira came with large bills and a battle with insurance and Accredo pharmacy. Every month, unnecessary stress had been added to my already full college schedule. In between classes I found myself calling multiple people to make sure my medication was going to arrive on time and that it didn’t cost me $4,000 each time. I’ve had issues almost every single time I refill my medicine. It almost makes me want to switch medicine just so I don’t have to deal with it, which is unfortunate because the medicine itself helps me.”
Sydney: “I just came off Humira. It worked great until it didn’t anymore. The formula changed a few years ago, which made it a lot more tolerable, but for a very tiny human, the auto injector caused some atrocious bruises. I ended up having to use syringes because of the bruising. It was a fight with insurance almost every time I needed a re-fill. The medication was good, but the stress trying to get it was almost not worth it. I only reached remission for about a year on it and then my body figured it out.”
Sam: “I have been on Humira for five years. I would say the issues aren’t the drug itself. Insurance companies make it so hard to get access. Ordering my medication from a specialty pharmacy is the worst.”
Christie: “I have been on Humira for three years after being diagnosed with ulcerative colitis in early 2019. The decision to begin taking Humira was a tough one, but I wanted to try anything to reach remission. While I have had a few insurance hiccups here and there, my experience with Humira has been great. I am enrolled in the Humira Complete Program, where I can track my injections and a nurse ambassador calls me once a month to check in. The resources AbbVie offers are incredibly helpful. Overall, I credit Humira for getting me into symptomatic and endoscopic remission.”
Final thoughts
All in all, you must always weigh the risks versus the benefits when determining a treatment plan with your physician, regardless of the medication. I personally have not dealt with side effects and have relied on Humira to help me maintain my remission and feel my best so I can be present for my family. What started out as a shocking change in my life, is now just part of my routine. Be patient with yourself and whether the injection hurts or not, reward yourself after. I usually enjoy some ice cream while watching reality TV. Giving yourself an injection isn’t easy, treat yourself to something for being a compliant patient who is doing all you can to help treat an unpredictable and complicated disease. And most importantly, remember you are not alone in your fears, your struggles, and your worries.
They call themselves “Propellers.” They’re a team of volunteers, made up of IBD patients and caregivers who created a non-profit called Propel a Cure for Crohn’s in 2016. They are laser focused on preventing and curing Crohn’s disease and, on the heels of their first research project funded at Stanford University in the world-renowned lab of Professor Mark Davis, they’re now determined to make a meaningful difference through their Roadmap to a Cure for Crohn’s effort. During this month (September 2022), they’re aiming to raise $50,000 to help get their latest project off the ground and to provide a solid foundation to bring their global team together.
This is a grassroots effort fueled by patient and parent volunteers. Patients and caregivers have an opportunity right now to directly influence a brighter future without Crohn’s! This is a peer-to-peer fundraiser—it’s not just about the monetary donations, but also sharing the message with others far and wide. Not only are international researchers involved, there are people all over the globe participating. In addition to the English-language campaign, there are also Swedish and Portuguese online campaigns running as well.
The Patient/Caregiver Perspective
Ildiko Mehes recalls what it was like when her 9-year-old daughter received her lifechanging Crohn’s disease diagnosis in 2017.
“As a parent, a serious diagnosis like Crohn’s is a huge shock, and it’s absolutely devastating and heartbreaking. Even during periods of remission, we are always on high alert and waiting for the other shoe to drop. At diagnosis, my whole world stopped, literally and figuratively. As irrational as it sounds, as a parent, you wish the rest of the world stopped with you to help you address the crisis. You wish that all of modern medicine rolled up their sleeves and urgently worked together to precisely diagnose the problem and bring her back to long-term health.”
As a caregiver, Ildiko has a unique sense of urgency and determination. She feels we need and can do better for IBD patients.
“When an otherwise healthy child, with no prior medical history, suddenly presents with IBD symptoms during a routine winter virus, you ask yourself “what caused this switch to be flipped?” Not having any answers to the underlying mechanism of disease onset or perpetuation, having a trial-and-error approach to disease management, and being forced to consider serious immunosuppressive medications with modest clinical trial benefits feels unacceptable as a parent. This is what drives me.”
As a pharmaceutical executive with more than 20 years of experience, Ildiko uses that unique skill set to go after complex and difficult goals with Propel a Cure and feels a deep sense of obligation to help our community.
“While there is excellent research ongoing in IBD, it happens in silos. It lacks global coordination and a plan. We don’t yet understand many basic things about Crohn’s. We are all just hoping for a “eureka moment” that hasn’t come over the last 100 years. We are continuously enticed with headlines of a “promising” new pathway or new drug candidate, usually in mice. And then that great idea sits there, with no progress made, a decade or more later. I know we can do better,” she said.
Natalie Muccioli Emery was diagnosed with Crohn’s disease in 2011 and she’s also a Propel a Cure Board member. She started dealing with abdominal issues 26 years ago. Being a veteran patient has provided her with perspective about how far treating and managing IBD has come and how far we still have to go.
“Propel a Cure was the first organization whose mission resonated with me. I appreciate their mission to cure Crohn’s Disease, but I even more appreciate the fact that they have laid out a plan as to what the areas of knowns and remaining unknowns are in their Roadmap to a Cure for Crohn’s project. Complex issues like Crohn’s Disease will take a collaborative and systematic approach to address, and this cause has captured that,” said Natalie.
Not only is Natalie an IBD mom, she’s also an IBD aunt!
“I believe that as an adult with IBD, the way I embody the role of a “Crohn’s Warrior” is not for myself it is for the next generation. I have “been there and done all that” with Crohn’s. But just because I did it with Crohn’s doesn’t mean the next generation should have to. I grow increasingly concerned when I see the rising rates of IBDs like Crohn’s in younger people. I believe the rising rates of Crohn’s should create a sense of urgency and a desire for a better future.”
Putting the puzzle pieces together
The Roadmap to a Cure is an ambitious project but one that is needed to drive real progress toward cures and prevention of IBDs, not just talk about “cures” in some very distant future. Ildiko says the brilliant clinicians and scientists she has gotten to know all tell her that getting to a cure will take a grassroots effort, global collaboration, and involvement of patients and caregivers.
“We at Propel a Cure are deeply committed to doing exactly that. The first step in our project is to systematize what we already know about Crohn’s today. We know a great deal, thanks to research. But when we are talking about complex fields like genetics, epigenetics, immunology, microbiology, epidemiology, multi-omics platforms and artificial intelligence, etc. there is no way any one person or group can know everything. We need a large global group of dedicated and brilliant experts to put all the puzzle pieces we already have on one table so we can begin to then put the pieces together,” she explained.
Grabbing the attention of medical professionals and researchers
Propel a Cure grabbed the attention of Dr. Bram Verstockt, MD, PhD, Department of Gastroenterology and Hepatology, University Hospitals Leuven, on social media.
“I truly like the concept of joined forces across various stakeholders, including patients and caregivers. As clinicians and scientists, we can have ideas about how to move forward based on experiences and interactions with patients on a daily basis. However, the next step really is to involve patients actively in many of these projects, as is currently the case with Propel a Cure,” said Dr. Verstockt.
The “Roadmap to a Cure” aims to bring together expertise across many different fields and niches in IBD.
“Over the past decades, a lot of scientific evidence has been generated in multiple domains of Crohn’s disease, so now it’s time to bring all that evidence together and truly connect the dots. Only by doing so, one might unravel knowns and unknowns and highlight where the remaining key gaps are, and we can define the priorities and strategies of how to fill these gaps to significantly advance the field, to improve the lives of patients with Crohn’s disease,” said Dr. Verstockt.
Where the roadmap can take us
After the initial step of putting together the state of the art, the next step is identifying gaps in our knowledge: what puzzle pieces do we still need? The third step is to develop the plan, or the Research Roadmap, to get from what we know today to developing cures and prevention strategies.
“We truly believe in a future where we can prevent and cure Crohn’s and eliminate so much patient and family suffering,” said Ildiko.
The reason this requires a grassroots effort and all of us patients and caregivers to fund it, is that otherwise the current system largely doesn’t provide incentives for new ideas or cures or global collaborative efforts of this magnitude. A recent paper discusses how the same ideas have been funded for decades, with limited progress and that we urgently need new directions.
Ildiko believes the current research incentive model is broken. “If we want true progress and cures for Crohn’s and other IBDs, we need a new collaborative model among IBD foundations/nonprofits, patients, caregivers, researchers, clinicians, and others. I believe this can become a model for other chronic and immune-mediated diseases.”
Click here to watch a video where Ildiko explains the Roadmap to a Cure project further.
Hopes for the future
“I would really like to see more key opinion leaders be brave about acknowledging the risks and limitations of current therapies, avoid putting lipstick on a pig when discussing some newer drug candidates in trials with lackluster results and the same mechanisms, dispense with biased headlines like “safe and effective” when the data is much more nuanced or unclear, and openness to “outside-the-box” ideas, like microbiome manipulation, including via diet, infectious triggers like Epstein-Barr virus in Multiple Sclerosis, vagus nerve stimulation, Fecal Microbiota Transplant (FMT), hyperbaric oxygen, etc. and also adopt routine monitoring via intestinal ultrasound for many patients,” said Ildiko.
As of now (September 12, 2022)—more than $26,609 has been raised!
“I have been overwhelmed by the response so far, as has the entire Propel team. People are really connecting with our mission. We are getting donations from so many states and countries! We have received more messages of profound thanks and hope than I can recount. This fuels us so much,” said Ildiko.
Natalie feels a wide range of emotions each time she sees a donation come in or the campaign shared across social media.
“I go from feeling hopeful, to introspective, to sad. I truly wish we did not have to do this campaign and that in 2022 we knew what the underlying cause(s) of Crohn’s are, and that safe, effective, reliable treatments were available for all Crohn’s patients. But here we are. Crohn’s is still very much part of the lives of patients and caregivers, and we need to take action to change that. I am so grateful for the outpouring of support we have received so far, but there is more work to be done!”
Propel a Cure has virtually no overhead fees or salaries, so every single dollar donated to Roadmap for a Cure goes to research.
“We are all volunteers who work out of our homes. The donations will be put towards collaborative research teams worldwide. Each team will lead a contributing area to the development of Crohn’s Disease (environment, microbiome, immune system etc.) and highlight where the gaps in knowledge remain,” said Natalie.
“The ultimate dream obviously would be to cure and if not, to significantly improve the quality of life for millions of patients worldwide,” said Dr. Verstockt.
Click here to donate to this incredible cause or to join their team.
This blog was sponsored by Mahana Therapeutics. All thoughts and opinions shared are my own.
Did you know that two thirds of people with inflammatory bowel disease (IBD) also meet the criteria for a functional GI disorder? Dr. Aline Charabaty, Dr. John Damianos, and Dr. Katie Dunleavy recently presented a paper at the 2022 Guild Conference addressing the substantial overlap between Crohn’s and ulcerative colitis and the gut-brain interaction. You may wonder what constitutes a functional GI disorder, irritable bowel syndrome (IBS) is the most common.
“What we know is that up to 30-40% of patients with IBD in remission (absence of gut inflammation) continue to have GI symptoms such as abdominal pain, bloating, diarrhea, constipation, and fecal urgency, due to disorders of gut-brain interaction (DGBIs, also known as functional gastrointestinal disorders),” explained Dr. Aline Charabaty, director of the IBD Center at Sibley Memorial Hospital.
As someone who was diagnosed with Crohn’s disease more than 17 years ago, I’ve been told by multiple gastroenterologists that I have IBS as well. At one point I was told, “you have a touch of IBS” …whatever that’s supposed to mean. I know I am not alone in believing I have both IBD and IBS, especially since having 18 inches of my small intestine removed for bowel resection surgery in 2015.
Dr. Charabaty says this is the case for many patients because of the following:
Structural damage to the gut caused by IBD. Crohn’s disease can lead to small bowel stricture, which can cause cramps and constipation (by blocking or slowing down the stool flow); Long standing UC can create a “lead pipe colon” (where the colon loses its normal twists and turns that typically slow the stool flow down and become like a straight tube which makes the stool “fall” straight down), which can cause diarrhea and urgency. Resection of part of the small bowel and colon decreases the surface of the bowel that can absorb the water and solidify stools, which leads to loose stool. Finally change in bowel anatomy from stricture or resection, abdominal adhesions from prior inflammation, abscess, or surgery, can lead to small bowel bacterial overgrowth (SIBO) which can cause bloating, pain, diarrhea, or constipation.
People living with IBD can become intolerant to certain foods or modify their diet. This can lead to change in gut flora that affect gut functioning and lead to GI symptoms.
Recurrent flares or previous severe inflammation can lead to change in the gut sensation. Visceral hypersensitivity, gut motility, gut microbiome, intestinal permeability, and how someone perceives and tolerates all the sensations (pain, discomfort) that come from the gut.
IBD affects people’s emotional and mental health and is associated with a higher incidence of depression and anxiety. We know that depression and anxiety can affect the gut functioning and lead to IBS symptoms.
“All these changes are similar to what we see in people living with IBS and can cause IBS and IBS symptoms in people living with IBD. Sometimes the way I explain it to patients with IBD, is that IBS is like the PTSD of the gut. The gut has been inflamed, traumatized, manipulated, changed from prior flare and now it can’t go back to functioning properly, even if it’s healed and it looks normal,” said Dr. Charabaty.
This is where Mahana IBS comes in. The main mission? To empower people with chronic conditions to lead fuller lives through digital therapeutics. That’s why they debuted their new prescription digital therapeutic app, Mahana IBS, in the fall of 2021. Their wish is to destigmatize IBS and bring hope and meaningful solutions to patients like you and me.
Steven Basta is the CEO of Mahana Therapeutics. He says the app is safe, FDA-cleared, and has been clinically proven in the world’s largest trial of its kind to reduce IBS symptom severity.
“Cognitive Behavioral Therapy (CBT) has long been recommended in clinical guidelines as a safe and effective treatment for IBS. Access to traditional CBT with a therapist has been a huge challenge due to the limited number of IBS-trained therapists (less than 300 in the US). Now patients can access CBT and learn the skills it provides to help a patient manage their disease by using Mahana IBS on their smartphone, with great results: 3 out of 4 patients find relief and results for most patients are lasting. Mahana users can complete the program in 90 days or less at their own pace with daily lessons on their phone to create a healthy brain-gut connection and live life more fully.”
Both IBD and IBS negatively impact our quality of life. Our mental health, our psychosocial health, and our financial health (increased health care utilization, missing days of work, medications to treat symptoms).
“Beyond treating the inflammation of IBD, and preventing IBD-associated complications, it is important to recognize and treat IBS when it is present, so people can recover and optimize their quality of life. CBT is an effective therapy for IBS and reduces or eliminates symptoms of abdominal pain, diarrhea, constipation, and bloating,” said Dr. Charabaty.
Unfortunately, access to a therapist who can provide gut-directed CBT can be limited: lack of therapists trained in CBT in someone’s geographical area, limited time availability (many therapists are not taking new patients, or have long waits to see someone; or from an IBD patients’ standpoint—lack of “extra” health care time available, when we often juggle many health appointments), deal with lack of insurance coverage, additional costs related to taking time off work and the expenses related to travel and participate in CBT sessions. Which makes the app even more useful and beneficial for the patient community.
Bringing up digital therapy to your GI provider
Digital therapy is new, and Mahana Therapeutics is working hard to spread awareness in the clinical and patient community to ensure everyone who could benefit, has access, and knows about Mahana IBS.
“It’s important for patients living with IBD to ask their doctor whether Mahana IBS is suitable for them and discuss how it can work with their treatment plan,” said Steve.
As a gastroenterologist who specializes in IBD, Dr. Charabaty says, “Having an FDA-cleared prescription app that provides CBT right at the patient’s fingertips is pure gold! Easy and effective access to CBT at a time that is convenient for the patient, in the privacy of their home, without the added extra time and cost burden of a visit to a clinician. I believe that with this technology/app, which removes many barriers to accessing therapy for IBS, that many more people living with IBS (whether they have IBD or not) will benefit from what CBT has to offer and will be able to improve their symptoms and regain their quality of life.”
Patients who are in IBD remission experiencing IBS Symptoms may want to ask:
“If my IBD is in remission and my symptoms are IBS related, could a digital therapy treatment such as Mahana IBS gut-directed CBT be suitable for me?”
GIs who want to understand more about the clinical evidence and indications for use for Mahana IBS can head this website to check out the medical provider welcome pack which contains all the clinical information they need to get started and to prescribe Mahana IBS.
While the app is a prescription, patients can also download the app on their own and show their gastroenterologist in clinic. But to gain access to the full program, patients need to get a prescription to unlock the benefits.
How the app is tailored to each patient
People experience IBS differently which is why Mahana IBS provides a personalized approach, regardless of type of IBS. In the early sessions of the app, patients create an IBS symptoms profile, take an IBS Symptom Severity Score assessment, and create their personalized model.
“This means people get to identify and capture their own symptoms and associated thoughts, behaviors and actions that arise as a result of these. As patients progress through the app and unlock tools and content, exercises are provided that are tailored to people’s individual IBS symptoms. Progress is recorded through the IBS Symptoms Severity Score at the beginning, the middle, and at the end of the program to measure results,” explained Steven.
Reframing thought process to reduce IBS symptoms
We can all relate to how feeling anxious can leave our ‘stomach in knots’ but in IBS there is a disorder of the brain-gut communication which causes and perpetuates symptoms. For example, our guts can release hormones that change our mood, and the brain in turn sends a signal to our guts to change our bowel functions which then sends more signals to the brain.
“Patients may develop habits or use ‘coping’ techniques that perpetuate the vicious cycle of brain-gut miscommunication without knowing it. The Mahana IBS app uses a gut-directed CBT program that was researched and developed over several decades. It is designed so you can understand your personalized patterns and then learn skills to help support a healthier brain-gut interaction. The program delivers a combination of education and exercises so that patients identify and reframe thoughts, feelings, and actions related to IBS. Through the Mahana IBS program, patients can gain tools and habits for managing symptoms long-term,” said Steven.
Along with learning to reframe our thoughts, the app also features visceral relaxation exercises like diaphragmatic breathing or belly breathing, which can reduce visceral pain and improve GI function. Mahana IBS has easy to follow animations to help patients learn and practice these techniques.
While Mahana IBS is a treatment program designed to be completed in 90 days or less with lasting results, Steve tells me some patients may experience relief from their functional GI disorder within a matter of weeks.
“Patients go at their own pace, so they may complete the program more quickly. Once the 90 days have elapsed, patients can still access their personal data (for example goal setting, IBS-SSS score or their personal IBS Model). Patients can return to the app at any time to find support in any of the lessons, tools, and exercises they have completed.”
Accessing Mahana IBS
Mahana is committed to affordable access. Some patients may be reimbursed by insurance. For those patients who are not covered by insurance, there is a subsidized program to ensure patients will pay no more than $90 out of pocket for prescription cost. That’s less than a single session with a therapist ($120/session) for the complete 10-session program.
Steven says it’s incredibly rewarding and a huge privilege to lead the Mahana team transforming access to treatments like this through digital therapy.
“As CEO of Mahana Therapeutics I am inspired by so many amazing patients with IBS. One patient who had struggled for years with IBS symptoms that made her feel truly hopeless expressed that Mahana IBS changed her life. With the lessons and skills she learned, she no longer avoids the food she loves, and the way she thinks about IBS has altered so completely, it no longer limits her life. Our team’s mission is to make this story a reality for millions of IBS patients.”
Mahana IBS is available for download directly from the Apple App store and Google Play store—and the first session is free to try! To unlock all the specific features and benefits, you’ll want to get a prescription from your GI. Once you’ve been prescribed the app by your doctor, you will get a message from Blink Pharmacy with instructions to get started.
**Disclaimer: This article is in no way meant to offer medical advice or guidance. Medication to treat and manage IBD is NOT a failure. Please understand this is one person’s experience and journey. Prior to going off medication, consult with your gastroenterologist and care team.**
She was diagnosed with Crohn’s disease in 1991 at 19 years old. As a veteran patient and IBD mom of two teenagers, Kelli Young says the COVID-19 pandemic, along with turning 50, inspired her to dig deeper into her health journey and look beyond the “cookie cutter” approach to treating IBD. After multiple surgeries and decades of biologics and other medications, she was determined to try a different approach.
Much like many of us in the IBD community, we often choose to hide our disease from others. Kelli says 15 years of that strategy often left her feeling misunderstood. Once she started sharing and opening herself up to support, her world changed for the better. Anytime someone is sympathetic and says, “you poor thing,” Kelli reminds them that Crohn’s disease molded her in the person she is today and that everyone has problems, hers just happens to be IBD.
“Having lived more than half my life as an IBD patient, I knew I didn’t want to live the second half of my life the way I did the first half.”
Taking a closer look into food sensitivities
It’s no surprise the importance of diet has become a larger part of treating IBD in recent years, but there’s still a lot of gray area.
“Diet is often the one thing that the medical profession overlooks or provides the same generic diet to everyone, assuming everyone is the same. Diet is the #1 factor that affects your health in every way imaginable. Your energy, sleep, weight, sex drive, bowel movements, heart rate, and mood, just to name a few.”
Prior to changing her diet, Kelli connected with her longtime friend of more than 20 years, Dr. Sean Branham, a chiropractor who specializes in functional medicine. Dr. Branham ordered the Oxford Food Sensitivity Test. The test measures inflammation in the body on a cellular level. Food sensitivities are unique to each person, so it’s impossible to determine what your sensitivities are without getting tested. Reactions can also be delayed or be dose dependent.
Kelli says, “The Oxford Food Sensitivity Test looks at all types of white blood cells (Neutrophils, Lymphocytes, Monocytes and Eosinophils) and measures release of all pro-inflammatory chemicals like Cytokines, Histamines, Prostaglandins and Leukotrienes. Certain groups of foods are pro-inflammatory to humans because we may not contain all the enzymes to thoroughly break them down (like dairy). Other foods are pro-inflammatory because of their processing, like many different forms of sugar. Some are inflammatory due to genetic modification like gluten. Some healthy foods can create inflammation once digestive damage has been done and these partially digested foods leak across the digestive barrier and trigger an immune response.”
Customizing diet with Food Sensitivity results
Kelli’s tests results showed mushrooms, cashews, trout, mangos, green peas, coconut, among other foods, triggered an immune reaction. Once Kelli had her Food Sensitivity results in hand, her and Dr. Branham started to customize her diet.
“We first started by removing the bigger classes of pro-inflammatory foods like; dairy, sugar, gluten and soy and then assessed specific foods that were causing a problem for me individually.”
Along with removing these food groups from her diet, Kelli did a whole-body digestive cleanse that involved a specific diet with supplements, a shake, and a cream to rid the body the body of toxins, decrease inflammation, and cleanse the liver and digestive tract.
“Testing revealed that there were more than just digestive issues going on. I also had a blood sugar regulation problem, Estrogen dominance, nutrient deficiencies, a need for: digestive enzymes, immune support, and microbiome support. Once I completed the cleanse, we customized a supplement regimen specific to me based on my test results. We started with what Dr. Branham considered the most important things first and then as we corrected those issues, we moved on and tackled the next issue and so on.”
Celebrating a “new way of life”
As a single mom of a 19-year-old and a 16-year-old who have supported her through her IBD journey every step of the way, Kelli calls these lifestyle changes her “new way of life”.
“When my son was between the ages of 8-12 years old, he was showing IBD symptoms, but he didn’t have IBD, he was experiencing empathic pains. He watched me, a single mother, battle with the daily struggles. I tried to hide it, but he saw right through me. Today he is 16, growing, thriving, and enjoying his healthy mother. My daughter, 19, the age at which I was diagnosed, is thriving as well. I am now able to truly be present in both of their lives.”
When Kelli and her husband divorced, her children were only 8 and 5 years old. As an IBD mom it made an already challenging time that much more complicated. She never dreamed she’d be at this place in her life health-wise.
“Back then I wondered how I was going to give myself my own shots, how I was going to care for two small children 50% of the time when I was always sick. Being a single mother with IBD forced me to take a good hard look at my life, not only for me, but for the sake of my children. My motto used to be “expect the unexpected” and “no expectations.” Today, I no longer worry about the future bad days or wonder if I’m going to be around to be a grandmother someday. Yes, it’s difficult at times to follow such a structured lifestyle, but it’s even more difficult living a life being chronically ill.”
Going off all meds
Kelli has been off all IBD medication since May 2021. She says her GI of 30 years is reluctantly supporting her decision to go this route on her patient journey. Kelli had a colonoscopy in June 2022, and after the scope in recovery he said, “Well Kelli, your new way of life is working. I’ve never seen your scope results look this good.”
While this lifestyle may seem “extreme” to some or difficult to follow, Kelli says she was sick and tired of being sick and tired.
“The definition of “remission” varies depending on who you ask. I am celebrating three years of a “disease free” diagnosis. The Crohn’s will ALWAYS be very much part of my life, but now, the only time I have a “bad day” is when I cheat on my new way of life, eating something I shouldn’t be eating, not getting enough sleep, not exercising, and not managing my stress.”
This blog article is sponsored by Portal Instruments. All opinions and experiences shared are my own.
I’ll always remember how I felt the moment I was told I needed to go on a biologic drug to try and manage and control my Crohn’s disease. It was Fourth of July weekend 2008. My gastroenterologist walked into my hospital room and told me it was time to “break out the big guns,” meaning starting to get medication through an infusion or through a self-injection. I was a morning news anchor at the time in Wisconsin, three years into my patient journey. I knew without a doubt, for privacy reasons, and keeping my chronic health issue under the radar, that doing an injection in the comfort of my apartment was the best choice. As I watched the fireworks reflect off the hospital room window with my mom, tears flowed down my face. I didn’t know how on God’s green Earth I was ever going to be able to give myself an injection for the rest of my life.
I was never a huge fan of needles prior to my diagnosis. Once you have Inflammatory Bowel Disease, needles unfortunately are all part of it. While we may get desensitized, patients would give anything to be able to treat their disease without needles. When I started on my biologic, my mom and I went to my gastroenterologist office and a nurse told me I needed to do four, painful injections in my thighs because at the time I didn’t have enough fat on my stomach. I was shaking like a leaf. I had no idea what to expect, I was about to inflict pain on myself, the injector felt so foreign in my sweaty palms, and I was scared about not only how much it was going to hurt, but also the long-term side effects the medication could cause to my body.
I did the first injection and it felt like liquid fire burning through my skin. I couldn’t believe I had to sit there and do three more, back…to back…to back. The experience was traumatizing. When I finally did all four, my mom and I walked into the hallway and I embraced her, crying because of my reality, and knowing that in two weeks I would need to inject two more needles into my thighs for the final loading dose. Since July 2008, I’ve done a self-injection every other Monday and for a short time weekly, while I was flaring. That’s more than 2,600 shots.
Dreading “shot day”
The first few years I would absolutely dread my “shot day” and deal with the looming dread each week. Early on I would get emotional during the process and feel bad for myself. I was only 25 years old. It made me feel like I was a sickly person. My peers couldn’t relate. It was isolating and overwhelming. Every time I open my fridge, the box of injections is staring back at me as a constant reminder of what’s to come.
Doing my injections as an IBD mom
Fast forward to present day, I’m now a 38-year-old mom of three. Luckily, the formula for the medication was changed in 2018, making the drug virtually “pain-free”, but there are times I still feel the needle. Even though I have my medication process down to a science, I still wish I didn’t have to do it and I usually wait until Monday nights to do it. The timing is moreso out of habit, because when I was a morning news anchor there was no way I was going to deal with an injection at 2 a.m. I started a tradition of doing my injection while watching the Bachelor/Bachelorette, and that’s carried over now that I have three young children, often waiting until after their bedtimes. Each time after I’m done with my shot, I text my mom to let her know how it went. She’s a nurse and has been my greatest support with my IBD since the day I was diagnosed.
Sometimes my 5-year-old and 3-year-old watch me do my injection and each time they are intrigued. I’m sure my 11-month-old will be the same once he starts to gain an understanding of what I’m doing. It makes me sad that they often witness me doing my injection, but they are also my greatest motivation to be strong and smile through it. Watching me doing injections has made my kids incredibly brave at the pediatrician when it’s time for them to get their immunizations. Because I have little ones, I have to be mindful of disposing of my medication properly and keeping the Sharps disposal container out of harm’s way. We keep Sharps Containers up high in a cubby hole in our laundry room and I dispose of the injector pen immediately.
As an IBD mom, my greatest fear is passing along my Crohn’s to my children. While the risk is low, it’s there. I hope and pray my children won’t ever need to receive a biologic medication whether it’s through self-injection or infusion. For me, there’s no end in sight, I’m expected to be on my medication (if it remains therapeutic) for the rest of my life. Thinking of my babies having to deal with needles and being forced to inflict pain on them would be difficult for me and only add to the guilt.
The future holds so much promise when it comes to drug delivery without a needle. My hope is that in the years to come, other people won’t have to succumb to the same anxiety, pain, and worry I’ve had to deal with for more than a decade.
When something traumatic happens—like the mass shooting in Uvalde that left 19 children and two adults dead last week, the stress, sadness, and overwhelming grief can cause IBD to spiral out of control. You are not alone if the heavy nature of what’s happening in the world causes your mind to race and your GI symptoms to be amplified. As May (Maternal Mental Health month) comes to an end, a look at how we can best navigate these emotions and how our thoughts impact the gut-brain connection.
Looming threat of flares and violence
With the constant news cycle that bombards us, added into our reliance on social media, and seeing everyone’s opinions and posts, it’s the perfect storm for feeling suffocated by sadness. Life with IBD, whether you are in remission or not, is living with the looming thought of when your next flare or hospitalization is going to be. You know in your heart of hearts that it’s not a matter of if, but when your IBD is going to rear its ugly head. These days with violence happening left and right, it’s a challenge not to wonder and worry when you’re out in public if you’re going to be in the wrong place at the wrong time or if your children are in harm’s way.
The anxiety of worrying about the “what if” and the pain of grieving can often correlate to actual physical pain in our bodies that are already fighting an uphill battle. It’s difficult to try and make sense of what’s going on in the world. It’s impossible to try and wrap your brain around how people can be so evil. As a mom, I found myself crying putting each of my kids to sleep last week. Snuggling them a little longer. Worrying about their wellbeing and praying as hard as I could over them.
As a former news anchor and journalist, I vividly recall the moment the news of Sandy Hook broke. I was standing in the newsroom, about to head out to the studio to anchor the Midday show, when the heartbreaking news came over the newsfeed. It was incomprehensible then and it’s even worse now as a mom of three. I have only been able to watch the news in short snippets right now because I felt like the sadness of it all was consuming me in an unhealthy way. There’s a guilt that comes with trying to tune out the coverage and feeling like you’re not giving the reality of other peoples’ heartbreak the attention it deserves, while trying to protect your own mental state and heart.
Dr. Lindsay Hallett (Zimmerman), PsyD, is a clinical psychologist in Indiana. Here is her advice for coping:
Give yourself half the grace you give to others. This can make a significant difference in your overall well-being and stress level.
Reach out. If connection feels like what you truly need, enlist a friend or relative. The higher the level of personal connection, the better- seeing a friend is preferable to FaceTime, a phone call is preferable to texting, etc. But also, any connection is better than none.
Make time to move. Time is a premium to everyone and even 15 minutes will do. Listen to your body and give it what it needs – stretching, a walk, an intense workout, gardening… any kind of movement that respects your body’s own capabilities.
Give yourself permission to check out. If everything feels to be “too much,” avoidance can be healthy. Communicate healthy boundaries with others that you can’t talk about topic XYZ right now.
Seek therapy. Your emotional house doesn’t have to be “on fire” to benefit. Ask your primary care doctor, contact your insurance company, or research PsychologyToday.com to find a therapist. In-person with occasional virtual supplementation is best, but online therapy platforms can be helpful if you aren’t having luck otherwise.
Give yourself permission to unplug and stop doom scrolling. While there is no “right way” to cope with traumatic events like what happened in Uvalde and so many times before, give yourself permission to feel whatever complex emotions you are experiencing while also giving yourself space and time to take breaks and turns off screens. When you have IBD, being cognizant of what triggers you and recognizing how your symptoms speak to you, can allow you to stay one step ahead of the game in managing your illness. Focus on what’s tangible, what’s right in front of you, and what you are able to control.
Innovation and changes in healthcare are propelled by patients and caregivers speaking up about improvements that can change the way IBD is treated and managed. This week on Lights, Camera, Crohn’s we hear from pediatric gastroenterologists Dr. Michael Dolinger, MD, MBA, Advanced Pediatric Inflammatory Bowel Disease Fellow, Ichan School of Medicine at Mount Sinai and Dr. Mallory Chavannes, MD, MHSc, FRCPC, Pediatric Gastroenterology, Hepatology and Nutrition, Children’s Hospital Los Angeles about the benefits of Intestinal Ultrasound (IUS) becoming a part of routine care, regardless of age.
The goal of IUS is to utilize a non-invasive method to monitor disease activity over time and it’s considered to be more precise than endoscopy in identifying both disease location and characterizing the severity of IBD. The IBD community—both patients and caregivers—can help fuel the adoption of IUS and gain access to receiving more information about their disease activity than ever before.
What is Intestinal Ultrasound (IUS)?
Intestinal Ultrasound (IUS) is an abdominal ultrasound performed during a routine clinic visit without preparation, fasting, or contrast to assess both the colon and the small intestine (terminal ileum most frequently) for the presence of disease activity. Probes are placed over the abdomen and the provider looks at images of the small and large bowel.
“The beauty is that, unlike procedures and other image modalities available to assess disease activity of inflammatory bowel disease, IUS can be performed without any preparation or fasting,” said Dr. Chavannes. “In the setting of active disease, patients can have a thickened appearance of the wall of the bowel (termed increased bowel wall thickness) in both the small intestine and the colon, which can be detected via ultrasound.”
In addition, by using color Doppler, a feature that assesses the velocity of blood flow within and around the bowel wall, gastroenterologists can demonstrate inflammatory activity in the bowel wall. IUS can also detect IBD complications, such as fistulas, abscesses, or strictures (narrowing) of the bowel.
“Our expectation is that, with effective therapies, the aforementioned features of disease activity should improve or even disappear over subsequent clinic visits. If they do not, we now have an objective tool available in the clinic that can assist clinical decisions, such as ordering further investigations or even optimizing or changing therapy. Improvement of bowel wall thickening or decrease in color Doppler signaling is a reassuring sign that treatment is working. Lack of improvement signifies that optimization or changes in therapy should be considered,” explained Dr. Chavannes.
“Intestinal ultrasound is precise, we monitor bowel wall thickness down to the 0.1 mm. We are now able to make informed decisions with patients together, assessing their disease objectively in real-time so we can be aligned with our treatment goals. This reduces misunderstanding and may lead to better treatment adherence and improved outcomes,” said Dr. Dolinger.
Why the delay in the United States?
While IUS isn’t the standard of care across the world, it is used in several Canadian IBD centers and in Europe (Germany, Italy, Norway, the Netherlands, and Australia to name a few). However, there are still many areas of Canada and countries in Europe where this is not used as part of routine IBD care.
“There have been several barriers to adoption in the USA, the biggest of which are reimbursement and the lack of training/expertise. However, that is changing, as there is a tremendous amount of interest from most major academic centers,” said Dr. Dolinger. “Through the International Bowel Ultrasound Group (IBUS) there is now a formal training, while intensive, that can be completed by anyone willing in the USA, which did not exist 5 years ago.”
IUS fits perfectly in the treat-to-target algorithm by adopting a monitoring strategy that helps to prevent flares and bowel damage.
“There is no other test for patients to see their disease dynamically with a gastroenterologist in real-time, which enhances shared understanding and informs decision making like never before. All of this will help break the barrier in the USA and around the rest of the world,” said. Dr. Dolinger.
A study conducted in 2016 explored why IUS is not standard of care in the United States. The
authors surveyed nearly 350 physicians, of which 40% were pediatric gastroenterologists. Although a minority of gastroenterologists were using ultrasound to assess and monitor IBD (either bedside or within the radiology department), over three-quarters expressed interest in using it more.
“The main limitation identified or perceived by gastroenterologists who responded to this survey was a concern for inter-observer variability, a lack of familiarity with ultrasound indications and techniques, and a lack of interest and access to pursuing additional specialized training. In addition, the survey identified a common message that I have received previously from some radiologists; that other modalities are more precise or effective in assessing IBD. All these reasons can hinder interest and implementation,” said Dr. Chavannes.
However, considering the multi-center effort in disseminating training, knowledge, and engagement that has been ongoing in the USA in recent years, Dr. Chavannes is hopeful that IUS will rapidly become the standard of care nationwide.
How Children’s Hospital in LA and Mount Sinai in New York Use the Technology
The Henry and Elaine Kaufman Intestinal Ultrasound Program at Mount Sinai is one of the first in the country to employ the training of gastroenterologists and regular use of intestinal ultrasound for both children and adults routinely in the IBD center for non-invasive disease activity monitoring.
“This would not be possible without the leadership of Dr. Marla Dubinsky, who has worked painstakingly hard to bring this to patients at Mount Sinai, overcoming every barrier to lead the way in the USA. We would like patients everywhere in the USA to be able to have tight control non-invasive monitoring with intestinal ultrasound and in turn, are working with International Bowel Ultrasound Group (IBUS) to host the first hands-on training in the USA at Mount Sinai in the fall. We have faculty from around the country signed up to learn and this will hopefully begin to fuel further adoption,” said Dr. Dolinger.
Intestinal Ultrasound was introduced at Children’s Hospital in LA in the summer of 2020. This was incredibly helpful during the pandemic when access to endoscopy time was difficult, considering cancellations due to active COVID infection and decreased daily procedures to allow for intensive cleaning protocols.
“We integrated using IUS for all patients coming to the pediatric IBD clinic. We have seen an immediate benefit in how we approach patient care and how timely clinical decisions can be made right at the time of the clinical encounter. One example is for patients presenting for a second opinion; these patients usually present with ongoing symptoms of varying degrees, yet incomplete or dated documentation of endoscopy, fecal calprotectin (a stool test helpful in indicating inflammation), and blood work,” said Dr. Chavannes.
During the visit, IUS gives an opportunity to understand the source of the symptoms experienced by patients and the degree of ongoing inflammation. Then, clinical decisions can be made that day, eliminating the need for additional testing. Dr. Chavannes says IUS even helps ease the discussions she has with parents and families.
“Many parents are stunned by the images they see and the changes over time. At the same time, they also notice when there is little difference from one appointment to the next, understanding the reason we are making the changes to the management plan that follows,” said Dr. Chavannes. “IUS has been invaluable for children under 6 years of age. This vulnerable population needs frequent objective reassessments, which is not possible otherwise. Using MR-Enterography would require general anesthesia, and access can be difficult. Similarly, for endoscopy, the prep can be poorly tolerated, and it also requires general anesthesia. IUS is non-invasive, painless, very well tolerated in young children, and available in real-time. Therefore, both parents and children are quite satisfied with their experience with IUS.”
Targeting treatment through IUS
Monitoring symptoms alone is not effective in reaching deep healing of disease in IBD, as many patients feel well despite having ongoing intestinal inflammation. IUS evaluates the inflammation that occurs within the thickness of the bowel wall (transmural inflammation).
“We often find that ultrasound is the only tool that shows continued inflammation when patients are in remission and labs have normalized. Optimizing therapies based on persistent inflammation seen on ultrasound may prevent us from falling into the trap of thinking our medications are working when our patients feel better and thus lead to better outcomes by not missing persistent inflammation that we have continued to miss with traditional monitoring strategies,” said Dr. Dolinger.
Although there are no fully established algorithms for the frequency of monitoring IBD using IUS, the best approach appears to have a baseline IUS at the time of IBD diagnosis or in the context of active symptoms or elevated inflammation markers on blood work (a flare).
“Then, the clinician can understand the features to follow over time. A repeat IUS can be performed at the end of induction treatment to assess how effective the management is. It would represent 6-8 weeks after the treatment was started. Provided that there is a marked improvement, the subsequent evaluations with IUS can be done every 3-6 months unless there are new concerns, with the closer timeline early in the disease course,” explained Dr. Chavannes.
In pediatric patients, this routine ends up matching most routine clinic visits. Therefore, as IUS becomes standard practice, and depending on how a patient is doing, their symptoms, and last assessed disease activity, patients can expect IUS as often as with each clinic visit. This modality would complement blood work and calprotectin stool tests in informing about disease activity and for complications of disease or flares.
What the future holds
Since a few IBD centers in the United States have already implemented regular IUS in their practice and have been disseminating knowledge about this technique, there is growing interest from pediatric providers to join the movement as well.
“Considering the challenges pediatric providers face in access to complementary imaging, operating room time, anesthesia exposure to endoscopy, and even the tolerance drinking contrast for radiology studies, IUS offers a fantastic way to assess disease activity in the pediatric IBD population. I am excited about the number of pediatric centers that have reached out about getting expertise in this field. The key is to promote buy-in from leaders in each institution to get the time and resources required for training and implementation,” said Dr. Chavannes.
Advice for patients and caregivers
It doesn’t hurt to bring up IUS at your next clinic appointment to gauge where your care team stands and if anything is in the works.
“If your provider is unaware of IUS and its benefit, it would be great to talk to them about the International Bowel Ultrasound Group. The curriculum for getting training involves three modules: an introductory module, a 4-week hands-on training at an expert center, and a concluding module and examination part of the European Crohn’s Colitis Congress,” said Dr. Chavannes.
She went on to say that hearing this request from patients may motivate administrators to provide the necessary time clinicians who are interested in getting expertise to implement the tool at their center would need.
Dr. Dolinger believes most major academic IBD centers in the United States will rely on IUS in the next 3-5 years.
“I would like to remind patients to be patient with their providers. Ensuring correct training and standardization is essential for adoption in the USA and this takes time and rigor to be done right and change the monitoring algorithm which has not been done in many years,” said Dr. Dolinger. “I began training in 2019 and it wasn’t until the second half of 2021 that we began using it very routinely for decision making, taking 2 years to become an expert. So, this will happen, but it will take some time.”
Patients and parents are big fans
The safety and efficacy of IUS can’t be matched. It’s also a big-time saver for everyone involved. A bedside ultrasound can be performed in a range of 20 minutes for the first thorough assessment, while an even more focused exam in a known patient can take less than 10 minutes.
“Both parents and children have been quite satisfied after their experience, as children can go back to school after the clinic despite undergoing this examination. Furthermore, the time saved in skipping additional appointments with the radiology department or procedures can be invaluable,” said Dr. Chavannes.
For parents, the imaging provides reassurance when there are improvements or when there are non-specific symptoms, yet the IUS is normal. IUS also bring validation when there are abnormal findings and helps to provide an explanation for why children are feeling a certain way.
“Children appreciate that it does not hurt and takes little time in addition to their clinic visits. In addition, they may not require additional appointments in radiology or endoscopy. Parents who had an opportunity of experiencing an ultrasound often request it afterward as part of their clinic visits. These families are more engaged and participate in shared decision-making. I am pleased and impressed at the engagement that actually “seeing” the disease together brings from families,” said Dr. Chavannes.
While the push is for IUS to be available to all IBD patients, both children and adults, it’s specifically beneficial for the management of pediatrics as it provides the unique opportunity to prevent bowel damage for a person’s entire life and reduce the need for invasive procedures, anesthesia, and sedation. IUS has the potential to alter scoping schedules in the future. While it will not replace the need for colon cancer screening or the assessment of mucosal and histologic healing, IUS can reduce the need for further follow-up scopes once those targets are achieved in between the need for cancer screening.
Whether you are a parent or not it’s heartbreaking to imagine how it would feel if you found out your child (no matter their age) was diagnosed with a chronic illness like inflammatory bowel disease. Of the more than six million people in the world diagnosed with Crohn’s and ulcerative colitis, approximately 25% of patients are diagnosed during childhood and adolescence, most of which are going through puberty. Impaired growth, pubertal delay, and low bone density are all common in children and teens with IBD. They can occur at diagnosis or at any time during a patient’s IBD journey.
As an IBD mom of three, who was not diagnosed until I was 21 years old, I personally don’t have the experience or perspective to share what it’s like to grow up with IBD or have a child diagnosed with it, so I tapped into several caregivers in our community, along with four leading pediatric gastroenterologists for input.
My hope is this article will serve as a helpful resource as you navigate the challenging waters of puberty with your loved one. Teen years are difficult enough without a chronic disease, taking a close look at how this impacts a young adult physically, emotionally, and mentally is something that deserves much more attention than a blog article.
Concerns from patients and caregivers
Before we get into the medical input, I want to share some of the messages I received this week from young patients and their caregivers so you can see firsthand how complicated this period of life is for everyone involved.
“I’m 14 years old. I was diagnosed with Crohn’s when I was 12, which marked an influential time in my life. It can be hard to cope with being diagnosed and having a chronic illness at that age. That year leading to my Bar Mitzvah, a cultural rights of passage from boyhood to manhood, was really challenging for me. At a time when changes are going on and puberty takes its course, learning to trust your body and that it is working is key. Rather than trusting my body, I had a lot trust issues. If my body could turn itself to work against me in my GI system, what’s to say it wouldn’t turn on me other ways? I am especially worried about my reproductive system. Since I was a little boy, I always knew I wanted to be a father when I grew up. Having kids and being a family man has always been my highest purpose in life. Since my Crohn’s diagnosis, I’ve felt anxious and worried about whether my Crohn’s or my body will stop me from fulfilling that dream.”
“I often worry about whether my son’s hormones will put him into a flare and wonder what the best way to approach the school about his Crohn’s is.”
“My biggest puberty concern is delayed growth or slowed growth and flares. I’ve heard a lot about puberty hormones really causing issues. Is there truth to this?”
“Will my almost 15-year-old son start puberty once his treatment kicks in or will he always look like a 12-year-old child?”
“My 15-year-old lost more than 15 pounds in the last year, we’ve checked all kinds of things, but can’t figure it out. He’s on renflexis (generic Remicade) and his colonoscopy came back clean. He gets full easily and deals with chronic constipation. I hope his IBD doesn’t stunt his growth.”
“The anxiety of managing IBD while combining that with the developmentally normal anxieties of the adolescent years can result in mental health issues that are hard to pinpoint. Body image issues that are normal as their bodies change, mixing with body image and food-related issues associated with IBD (good foods and bad foods, overly focusing on diet, etc.) which can lead into worrisome territory like disordered eating and worse. As children separate from their parents more with each passing year (which is normal), it becomes harder to monitor IBD symptoms and disease progression as a parent. As someone who has always been in the driver’s seat about IBD, this is a scary shift and I worry some symptoms will go unnoticed and become exacerbated.”
“That puberty will stop growth—growth has been severely impacted by Crohn’s before diagnosis and it did—hitting puberty early meant growth stopped and she only reached 4’9”/4’10”. Her periods also add to existing fatigue levels.”
“I worry about medication not working like it used to due to so much change in the body. I also worry about how she may feel about her image comparing herself to others at that age with so many scars or if she ever needs to have an ostomy bag. I worry her IBD will affect her cycles or make them more painful.”
“That my son will go into a flare requiring heavy intervention that goes far beyond our comfort zone, but we’ll feel trapped so he’s able to grow at the right time.”
“My 13-year-old son was diagnosed with Crohn’s a little over a year ago. He is doing ok now and on Humira bi-weekly. I’m mostly concerned about his growth, as he is small for his age. He has gained about 20 pounds in the last year, but he was malnourished as COVID made it difficult to get his diagnosis. Hoping he stays on track and continues growing and that his growth potential isn’t adversely affected by his IBD.”
“As a kid who went through being on high dose steroids while going through puberty, bless my mother!”
“Delayed puberty is a big thing. Also, how, and when is it appropriate to start transitioning responsibly for ultimate transfer of care. Mental health is often a concern for adolescents (anxiety/depression).”
“Flares. Many parents report puberty as being a challenging time for IBD. Imagine all the normal teen/puberty hormonal issues and then add IBD (and I say this as a lucky parent with our teens). I think every parent that makes it out alive should get a very long vacation. The #1 thing I hear from parents of kids with IBD is: “my heart breaks every single day”. Whether in remission or not, the disease is a persistent and heavy burden on patients and families. With all the noise, it’s important not to lose sight of this fact.”
“I was diagnosed with ulcerative colitis at age 13 and it all happened very quickly. I was in eighth grade – my body changed almost immediately after being put on prednisone. Being an early developer, puberty was a challenge for me. I didn’t look like most other girls in my grade. So when I started getting really bad acne and a swollen (moon) face from the meds, it was the icing on the cake. I remember ninth grade consisted of me coming home from school and crying to my mom because I felt what was happening to me was unfair. I’d have to excuse myself during classes to use the bathroom, so everyone knew what was happening. I was mortified. And although I was an “early bloomer”, I can’t help but wonder if I would have grown a bit more if I hadn’t been diagnosed, put on prednisone off and on for the first 3 years, or started on biologic treatment. There’s always the questions and mystery of what IBD has potentially taken away from me. But living with IBD also resulted in me growing up pretty quickly. I was able to navigate the healthcare system by the time I graduated from high school. I learned to talk about my body and my health – things that I don’t believe my peers could articulate by that time. So it came with some benefits – or at least things that I have been able to turn into positives. My experiences have made me a stronger person. And I’m thankful for that.”
Impaired Growth: Why it happens and what to watch out for
According to Dr. Sabina Ali, MD, Associate Clinical Professor, Director of IBD program, UCSF Benioff Children’s Hospitals, the most common extraintestinal manifestation of IBD in children is impaired growth, particularly in Crohn’s disease and that’s also what she hears from patients and their families when it comes to their greatest concern.
“Growth is a dynamic marker of overall health in children and adolescents, which occurs in 10-30% of cases. Short stature and failure to grow can precede IBD symptoms. It is important to monitor nutrition and growth closely and as this can lead to delayed puberty. Make sure the child is routinely getting height, weight and BMI measured. Growth impairment is more common in males than females with Crohn’s disease. It’s important to get disease in remission.”
Dr. Ali went on to explain that growth issues are more frequently seen in children who have never been in remission or for those who have dealt with flare ups in the pre-pubertal period.
“Pubertal delay may potentially decrease bone mineralization and affect quality of life in children who realize that their sexual maturation is different from their peers.”
Dr. Jonathan D. Moses,Assistant Professor of Pediatrics, Director, Pediatric Inflammatory Bowel Disease Program, UH Rainbow Babies and Children’s Hospital, agrees that remission is essential as a first step to ensure normal bone growth and pubertal development. Most of the time the concerns we hear about puberty and IBD is at the initial diagnosis when parents will note that young women have not started their menstrual cycle yet at the expected age or young men have not started their “growth spurt” yet.
“Growth is a key element of children diagnosed prior to puberty. Our goal is to provide the therapy that will allow them to be in continuous remission and achieve their final adult height and avoid any pubertal delays. If there are any concerns with this, we typically place a referral to the pediatric endocrinologist to help co-manage this.”
According to this University of California San Francisco study, boys are three times more likely than girls to deal with one of the conditions most devastating effects: the failure to grow normally. Researchers were surprised by this finding because the study also found girls had a more severe disease course than boys.
Dr. Ali says that a novel finding is that a high proportion of patients with ulcerative colitis exhibited continued growth, suggesting delayed skeletal maturation is also frequent in ulcerative colitis, contrary to common assumptions. For patients exhibiting continued growth, median final adult height was greater in males with ulcerative colitis than males with Crohn’s disease but did not differ significantly in females with ulcerative colitis, compared with females with Crohn’s disease. This finding supports the growing body of literature that statural growth impairment is more common in males than females with Crohn’s disease.”
Dr. Hilary Michel, MD, Assistant Professor of Clinical Pediatrics, Nationwide Children’s Hospital, explains the importance of monitoring pediatric GI patients’ weight, height, and pubertal development over time. She says measuring weight and height and asking about pubertal development helps make sure each patient is tracking along their growth curves and developing at an appropriate rate.
“In addition to monitoring IBD symptoms and checking labs, stool tests, and scopes, monitoring growth and pubertal development is another way to make sure we are treating IBD inflammation completely. If a patient is not going through normal stages of puberty, or is going through puberty more slowly than expected, it’s a hint that we should check on their IBD disease control! And if their disease is in control, then we need to think of other causes for delayed puberty and get them in to see the right experts to help.”
Dr. Sandra Kim, MD, Associate Professor of Pediatrics, Director, Inflammatory Bowel Disease Center, UPMC Children’s Hospital of Pittsburgh, says along with monitoring growth and nutritional status, it’s important to keep a close eye on emotional state and quality of life.
“It’s important children understand their disease, and for families and the care team to understand where the child is not only medically, but psychologically and developmentally. As a pediatric gastroenterologist, who focuses on the care of children and teens living with IBD, I know I have a unique relationship and responsibility as I watch “my kids” grow up.”
Dr. Kim says, “We see growth impairment in children and teens with Crohn’s much more so than with ulcerative colitis, especially with extensive involvement of the small intestine. Active inflammation in the small intestine can impact an individual’s ability to absorb nutrients. IBD also impacts appetite and can lead to inadequate nutrition.”
According to Dr. Kim, studies have shown up to 80% of children (males>females) have some degree of both weight and growth impairment when their Crohn’s is not controlled. While studies do vary in the range affected, it’s clearly a significant issue.
Medication and the pubescent years
In general all pediatric gastroenterologists try to limit and shorten the exposure of steroids in children.
Dr. Ali says, “Recent inception cohort studies in pediatric IBD have highlighted baseline phenotyping of patients to predict the severity of their disease course and help identify who will benefit the most from early biologic treatment. Biologic therapies have improved outcomes in pediatric IBD, including achieving mucosal healing as well as improved growth and pubertal development.”
Prior to this, the goals of treatment in Crohn’s disease were focused on controlling symptoms, enhancing quality of life, minimizing complications to prevent surgery, and restoring growth in pediatric patients. Evidence has shown that mucosal healing is associated with sustained corticosteroid-free clinical remission, reduced hospitalization, and lower surgery rates. According to Dr. Ali, biologics are the most effective in inducing and maintaining mucosal healing in this patient population.
Dr. Moses explains how biologics are decided upon with young patients.
“The age of the patient, in the context of the biologic era, does not seem to play a significant role at our center. If a child, regardless of age, needs a biologic medication, then we will typically proceed with this after shared decision making with the family. As a rule, for all ages, we work very hard to limit steroid exposure, both by planning out their maintenance therapy right away or using exclusive enteral nutrition (EEN) to induce remission in our patient with Crohn’s disease.”
Dr. Michel says it’s important to get IBD under control quickly since the window to achieve the goal of remission is so small.
“Because of this, growth and pubertal delay can be reasons to start a biologic as first line treatment. If steroids are used, they should be short-term (induction therapy only) to prevent negative impacts on growth and bone health. These patients may also be great candidates for exclusive enteral nutrition to treat their IBD, as it can help heal inflammation and address malnutrition without the side effects of steroids. Involving an experienced dietitian is key!”
While research has shown that disease activity may fluctuate with hormonal shifts (like those that happen with puberty, pregnancy, and even menopause), Dr. Michel says she is not aware of any specific data to connect loss of response to therapy because of puberty.
Puberty gets delayed
For pediatric patients in whom remission has never been achieved or for those who have frequent relapses, puberty is often delayed.
“The endocrine-hormonal mechanisms responsible for pubertal delay associated with inflammatory disease are incompletely understood. It is thought to be due to effect by both nutrition and inflammation,” said Dr. Ali.
Delayed puberty or delayed linear growth can be presenting signs of IBD to help clinicians make the diagnosis.
“Once these pre-teens achieve remission, they will begin to progress through puberty again and have improvement in their bone density, if it was low at baseline,” says Dr. Moses.
Dr Michel says, “The best way to ensure normal growth, weight gain, and pubertal development is to make sure their mucosa is healed. It’s also important we address low weight or malnutrition. If we’ve confirmed that IBD inflammation is resolved (through labs, stool tests like calprotectin, and scopes), and that patients are getting the nutrition they need, and we’re still seeing delayed puberty or slow growth or weight gain, this may prompt a referral to an endocrinologist, adolescent medicine doctor, or gynecologist to look for other causes of these problems.”
By adequately treating IBD and achieving mucosal healing, kids have the best chance to grow and develop normally and have healthy bones.
“Inflammation affects hormones important in growth and pubertal development, and delayed pubertal development is closely tied with poor bone health,” explained Dr. Michel. “Active inflammation can also worsen malnutrition and lead to low weight, which can delay puberty. These variables are often closely related; for example, a patient with active IBD may not feel well enough to eat regularly and lose weight or be malnourished. Or they may eat well but not be able to absorb the nutrients from their food. Or they may lose nutrients through stool or vomiting. So, treating inflammation and treating malnutrition are KEY to optimizing outcomes for kids and teens with IBD.”
Causes for the delay in puberty and decreased bone density can be multifactorial.
“Things we consider include nutritional deficiencies (not absorbing enough and/or not getting enough into your body), and the impact of inflammation (though pro-inflammatory cytokines – the “chemicals” produced by activated white blood cells – on sex hormone production, as well as growth hormone),” said Dr. Kim. “Other factors that can specifically impact bone density – decreased physical activity which leads to decreased muscle mass.”
When determining a course of therapy, a child’s quality of life and the impact of active IBD must be taken into consideration.
Dr. Kim explains, “Steroids have a great deal of side effects: external appearance (“moon” facies), psychological (can exacerbate underlying anxiety and depression; can impact sleep), bone health (decrease bone density and increasing risk of fractures), impact on wound healing, increased risk if long term on the GI tract (i.e. perforation), increased blood sugar (hyperglycemia), high blood pressure.”
What’s the deal with birth control and IBD?
Each pediatric gastroenterologist featured in this piece says they have heard from both patients and parents about oral contraceptives aggravating IBD. Dr. Ali says oral contraceptives are consistently linked to an increased risk of IBD.
Dr. Michel says since menstruating is a normal part of development for female patients, active inflammation, low weight, and malnutrition, can all play a role in delaying the onset of it. If a patient is flaring, they might have irregular periods or stop getting their period for some time. Once the problem is addressed—inflammation controlled, normal weight achieved, and malnutrition treated, menses typically resumes. IBD symptoms can also be exacerbated during menses for some women.
When it comes to choosing to go on birth control, and what birth control to choose, Dr. Michel advises patients and parents to be clear about their goals and weigh the risks and benefits.
“Goals for starting birth control can include regulating heavy periods or bad cramps, preventing pregnancy, improving premenstrual symptoms (mood, headache, fatigue), or even managing acne. There are some data about birth control pills increasing the risk of developing IBD, but research is conflicting about whether they increase the risk of flare. I would encourage any patient who is interested in starting birth control to talk with her gastroenterologist about what options might be best for her. An adolescent medicine doctor or gynecologist can also be extremely helpful to have these conversations, weigh pros and cons, and help young women and their families make informed decisions.”
Dr. Kim is no stranger to hearing concerns about the impact of oral contraceptives. She says it’s tough to determine whether birth control specifically aggravates disease.
“Women who have increased diarrhea and cramping around their cycles may have improvement in these symptoms when on birth control. Currently, there is not enough data to suggest birth control directly leads to aggravation of underlying IBD. However, there are other issues to consider when a young woman chooses the type of birth control. There is increased risk of venous thromboembolism (increased risk of forming blood clots) in individuals with IBD. There also is an increased risk for clots associated with combination oral contraceptives whether a young woman has IBD or not. Therefore, a woman who has IBD and goes on oral contraceptives not only has a higher risk of forming significant blood clots, but with more significant consequences from this.”
Dr. Kim’s recommendation? Avoid oral contraceptives with an estrogen component, if possible. Depo-Provera is an alternative, but you need to be aware that it can impact bone density. She says IUDs are safe and highly effective
How best to support young patients
Support groups: Discuss concerns regarding how a patient is coping with the IBD team. A social worker or psychologist on the IBD team can be a great resource.
Psychosocial assessments
Care coordination
Supportive counseling
Connection to resources
“As a pediatric gastroenterologist, my contribution is to manage their therapy as best I can to achieve remission. After that, we rely on our multidisciplinary team to address the psychosocial aspect of the disease and how this affects them at this stage in life,” said Dr. Moses. “Finally, we encourage the families to get involved with the Crohn’s and Colitis Foundation and attend Camp Oasis, if possible, to meet other children their age who also have IBD. This builds up their social support network in a way that can be life changing for them.”
Dr. Michel says, “I try to normalize their feelings, and reassure them that with effective treatment and achieving remission, we are working toward them reaching their full potential. I also think it’s a great time to involve experts like psychologists and child life specialists to help work through these concerns. Parents will often also ask about future fertility (kids and teens usually aren’t thinking of this yet)! It’s always a huge relief for families to learn that we expect normal fertility for our young folks with IBD and that the best way to ensure this is to get good control of disease.”
She advises parents to acknowledge how challenging it can be to go through puberty with IBD.
“Any feelings they’re feeling – frustration, anger, sadness – are ok. Then, I would encourage parents and patients to share these emotional and physical struggles with their healthcare team. Many centers have fantastic psychologists, social workers, and child life specialists that can help young people understand their disease, explore their emotions, and develop healthy coping skills that will serve them now and into adulthood. There are also fantastic resources online through ImproveCareNow and the Crohn’s and Colitis Foundation,” said Dr. Michel.
Dr. Kim advises parents and patients not to be afraid to ask pediatric gastroenterologists and their healthcare team for help.
“I really believe it takes a collective effort to support our children and teens. We are living in an unprecedented time with the COVID 19 pandemic (which has led to social isolation and new stressors with school, peers, and family dynamics),” she said. “Seeking our behavioral health resources (psychology, psychiatry, counseling, social work) is NEVER a sign of weakness – quite the opposite. One thing I would love to see: elimination of any perceived stigma when addressing issues around mental health. It is so crucial to address stress, anxiety, and depression. Besides the obvious impact on quality of life, we know that anxiety and depression can negatively impact an individual’s IBD itself. For the parents out there, I tell them they must check their own guilt at the door. The parents did NOT do anything to cause their child to develop IBD. I always say that you can be mad at the disease but never at themselves.”
Connect with these physicians on Twitter:
Dr. Sabina Ali: @sabpeds
Dr. Hilary Michel: @hilarymichel
Dr. Jonathan Moses: @JonathanMoses77
Dr. Sandra Kim: @SCKimCHP
Let this piece serve as a conversation starter as you discuss your child’s health with their care team. Ask the questions. Get empowered by learning and educating yourself more. As chronic illness patients and parents, it’s a constant learning curve—with each setback and triumph we gain newfound understanding and perspective. Stay tuned for an upcoming article on Lights, Camera, Crohn’s with guidance regarding making the transition from pediatrics to adult doctors.
As she fears for her life each day and every night in her homeland of Ukraine, ElenaSotskova thinks back to when her body started going to war against ulcerative colitis. She was 21 years old. Now, as a 47-year-old IBD mom, she shares firsthand experience of what it’s like to live in absolute chaos and devastation while trying to manage a chronic illness like IBD. Every morning Elena and her family wake up at 6 a.m. to the sound of explosions and gunfire. Oftentimes the internet and electricity go in and out, with repair workers constantly having to restore power.
Before we get into the utter heartbreak and unthinkable sadness, here’s some background. This isn’t the first time Elena has had to run from her home to try and reach safety. Shortly after her ulcerative colitis diagnosis, she fled with her 3-month-old daughter to Kyiv from Crimea, to avoid an abusive husband. At the time, she had the equivalent of 25 U.S. dollars in her pocket. Prior to becoming a mom, Elena worked for one of the largest banks in Ukraine, so she was confident she’d be able to land back on her feet in no time and support herself and her daughter. The stress of the divorce and being forced to start anew exacerbated her IBD.
“My condition was worsened by constant diarrhea, bleeding, low hemoglobin, and as a result, constant fatigue. I tried not to pay attention to it as I needed to work and make money for myself and the baby. My ulcerative colitis limited what I could do and where I could go. I used to be unable to go for walks unless I know where the restrooms were. I always had spare clothes with me and wet wipes, in case I did not make it in time.”
Since then, Elena has managed her ulcerative colitis with Mesalamine, in large doses (6-8 grams per day).
“In Ukraine at that time there was no biological therapy, and even clinical studies of such therapy did not take place. All that was available to patients were hormones and mesalamine. In addition, in Ukraine there is no compulsory insurance medicine (until now), there are no state programs for the treatment of patients with ulcerative colitis and Crohn’s disease, so I and other patients must buy drugs with our own money. And they are, as you know, not cheap. Compared to the level of income in Ukraine, it is expensive.”
How love found its way
Elena says she was working to buy her medicine. It felt like a vicious, never-ending cycle. But Elena’s luck in the love department took an amazing turn.
“I was lucky, I met a wonderful man, named Leonid who has a son. Leonid later became my second husband. I immediately told him about my illness. He accepted me, my IBD, and my child. He wouldn’t turn away from me or be ashamed when I had an accident at an event or in a public place. He helped me and supported me. And as a result, I stopped being nervous about my ulcerative colitis. I stopped worrying, and after I became calmer, the disease slowly began to subside.”
Leonid also started to take care of all the costs associated with her IBD treatments. Elena credits him for reviving her medically and emotionally, allowing her to reach remission after chasing after it for years. She was able to travel comfortably away from home and see the world through a different lens.
Prior to the war with Russia, Elena had big plans for herself. She aspired to begin her MBA and travel to English-speaking countries.
When the explosions hit
“All plans collapsed at 4 a.m. on February 24, 2022. We woke up to the explosions, saw the message “The Russians are bombing Kyiv, the war has begun.” That was more than a month ago, but it seems like we’ve been living in this nightmare for ages.”
Elena’s daughter, Alina, had recently arrived in Poland to study, but she happened to be home in Ukraine with family when the war started. Prior to this happening her travel plans were to fly back on February 27th. Of course, that all changed.
“She was supposed to fly back to Warsaw on Sunday, but war broke out on Thursday. Immediately, air traffic over Ukraine stopped. And hell began. Kyiv was bombed from the very beginning, we sat in the bathroom during the air raid, went down to the basement or went to the shelter. We did not turn on the lights in the apartment and taped the windows with duct tape so that they would not be knocked out by the explosions. We walked the dog for 5-10 minutes, near the house, so that if the shelling started, we could quickly hide. We live in Kyiv on the 7th floor, and most of all I was afraid that a bomb would hit our house, and we would either be overwhelmed or burned in a fire.”
Elena says for days on end she sat with her husband and daughter in their apartment. Alina would constantly cry. They learned that evacuation trains were leaving Kyiv for western Ukraine. At this point, they decided to send Alina back to Poland.
Nights spent at the railway station
“The most terrible were the three days that Alina and I spent in the basement of the railway station in Kyiv. There is a curfew, you cannot go outside in the evening, in addition, it was dangerous to go outside, because they are constantly shelling. My daughter and I got to the train station and decided to wait here until she could take the train to safety. My husband and son stayed home with the dog.”
The trains to leave Ukraine were like something out of a horror movie. Instead of a train car fitting the usual four people, they were packed with 20-plus people. People were ready to stand for an entire day just to leave Kyiv.
“Alina could not get on the train that was going to Warsaw, and we stayed overnight at the station. At night, the air alarm did not cease, explosions were heard, we went to the shelter (basement) of the station, which for three days turned into a home for us. We tried to sleep on the floor, it was warm, but the main thing was that it was safe. Finally, on the second day, we managed to put Alina on the train to Lviv. She left, and I was standing on the platform crying and praying that the train on the way would not be shelled, and my daughter would reach Lviv intact.”
Elena had to stay alone at the train station for an additional night because of the curfew in Kyiv. She was afraid her IBD would start acting up from the overwhelming stress and worry and terrified she was going to be killed.
“My gut understood me, it “behaved quietly”, and did not give me cause for concern. During the 21 years of illness, I learned to negotiate with him. On the fourth day, when the curfew was lifted, I was finally able to return home, wash myself and clean myself up. And my daughter had already reached Poland and was safe. We thought that somehow, we could adapt to this situation. We had food, water, gas, electricity, and Internet. We thought that we could somehow live in Kyiv. But this turned out to be unrealistic, as soon as dusk came, the city was pierced by an air alarm, it turned on several times during the night.”
Deciding to leave Kyiv
Bombing began each morning between 3 and 4. Elena and her family stayed in their clothes and didn’t sleep. She would take her dog and lock herself in the bathroom while her husband and son were standing in the hallway where there were no windows.
“Then a cruise missile hit a television tower, close to our house. It was afternoon, her son had just gone out to the store for bread, and there was an explosion, a crash, a fire. People who were nearby were killed. My husband said that we needed to leave Kyiv, it was extremely dangerous.”
So that’s what they did. They left for Elena’s mother-in-law’s house who lives in a village outside of Kyiv. There are no military or infrastructure facilities there, so they are hopeful it will not be bombed. As you are reading this, Elena is still there.
“In the village it is calmer, the battles are 30-40 kilometers (20-30 miles) away, we constantly hear artillery shots, gunfire, explosions, and flying missiles. But there is no air raid alarm, which was so exhausting in Kyiv. It’s still impossible to sleep normally. We are afraid that we will be occupied, and we are not where there are active battles.”
Running out of IBD medicine
But, Elena now faces another major issue. She will run out of her IBD medication this week and there is no way to buy it or receive it. Since the war started, she’s heard from countless other patients in the same bind. Doctors have fled, there’s no place to safely receive treatment, and for those who are now refugees or without jobs, they struggle to afford their medications. Elena knew she had to do something.
“I began to write to the European Crohn’s and Colitis Association, manufacturers of drugs, everyone who I could, to find out how to help our patients. Poland and Estonia immediately responded. They understand if Ukraine does not resist, the war will go on, to Poland, and the Baltic countries may also suffer. Now we are in constant contact with our European colleagues and are waiting for humanitarian assistance from them. Packages from Greece are supposed to arrive any day now.”
While Elena’s ulcerative colitis is under control now, she’s been forced to reduce her daily medication dose by half to try and keep medication in her body for as long as she can. She’s starting to feel that reminiscent pain we all know too well when our intestines are making themselves known. The pain, bloating, and diarrhea have been more consistent for her, but she doesn’t feel she’s flaring yet.
“I’m very scared that if I go into a flare, there will be no one and no place to treat me. I am afraid that this war will drag on for a long time, and then it is impossible to predict the condition of either mine or our other Ukrainian patients.”
Her friend was able to find her mesalamine in Kyiv. She bought the medication, but it’s been a week now and the package has not arrived to Elena’s new address. Tomorrow (March 31), Elena’s husband will venture back to Kyiv to try and get Elena the medicine she relies on.
She tells me she no longer cries or has emotions and that every day feels like déjà vu. Sometimes she feels like a robot in an out of body experience. Elena says the Ukrainian people are steadfast, strong, and remain hopeful they will be victorious in the end.
Tomorrow on Lights, Camera, Crohn’s you’ll learn about Elena’s inspiring patient advocacy prior to the Russian invasion, how she co-founded an IBD organization to support the patient community, and how she’s working day and night right now to help the approximate 11,000 Ukrainians who live with IBD and are struggling to manage a disease while living through a war.


















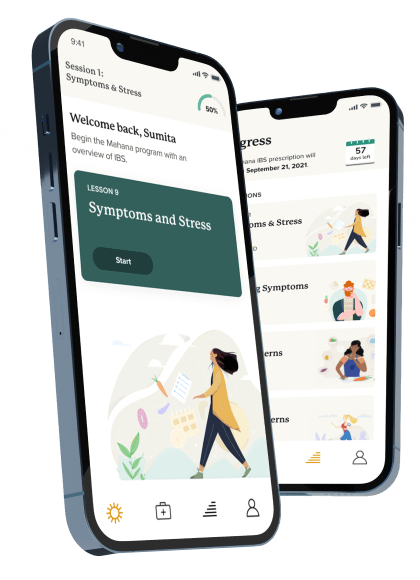
















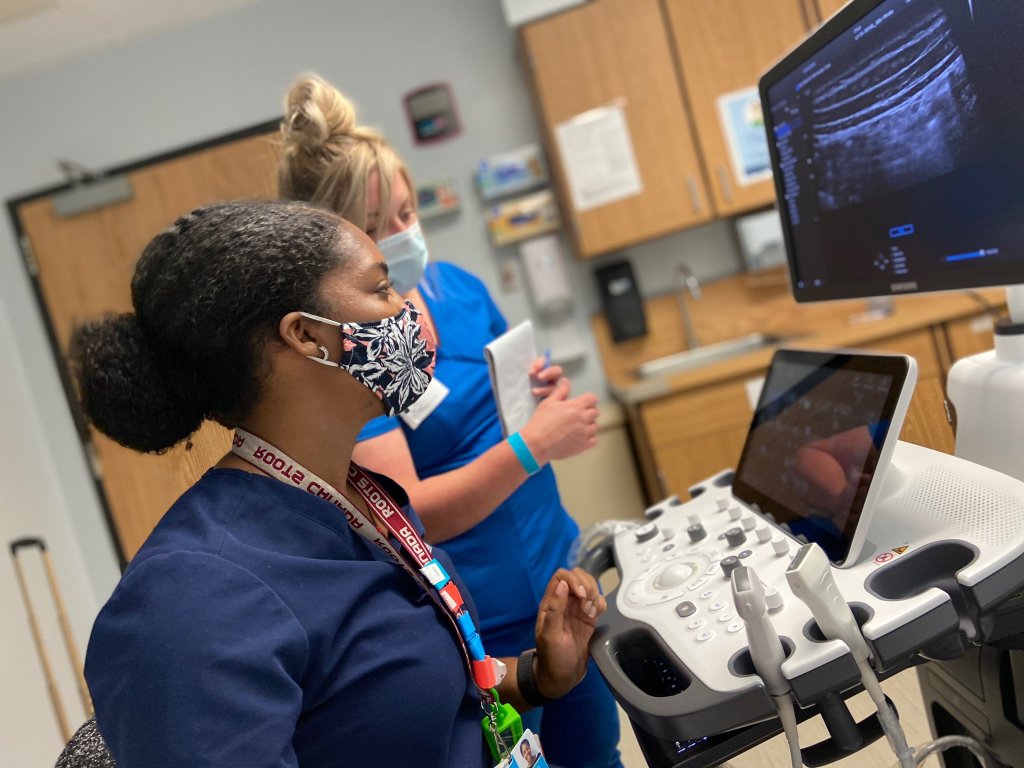
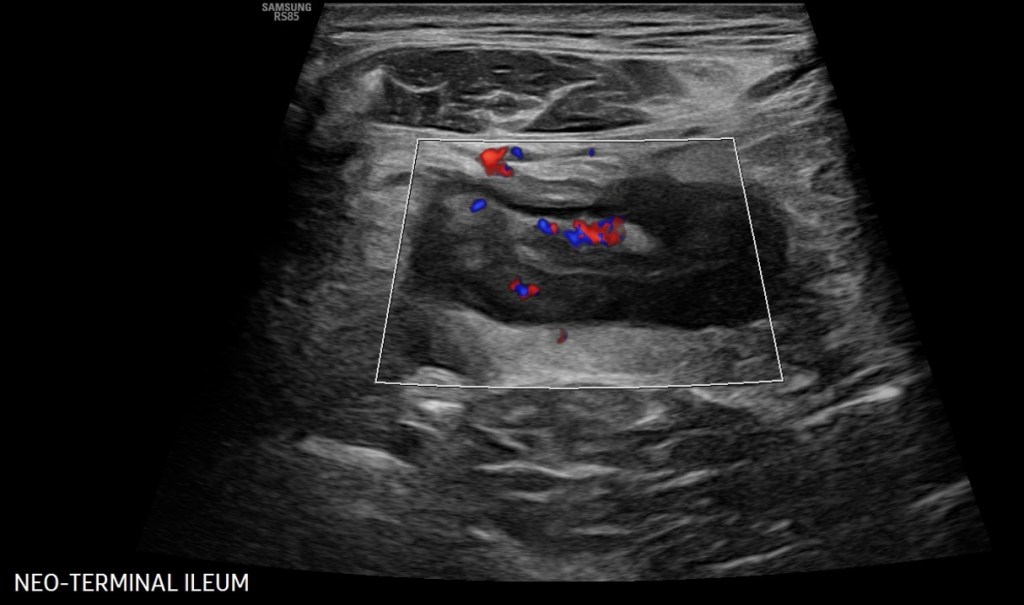
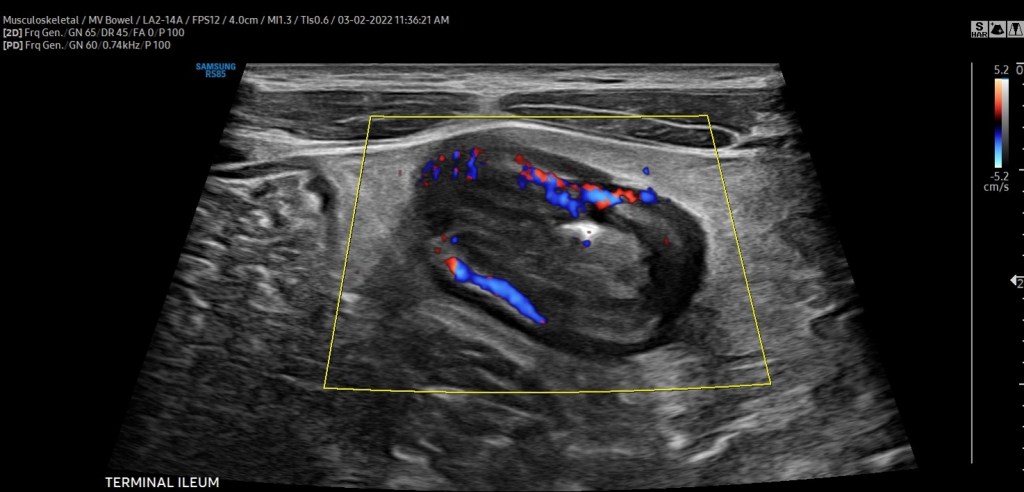


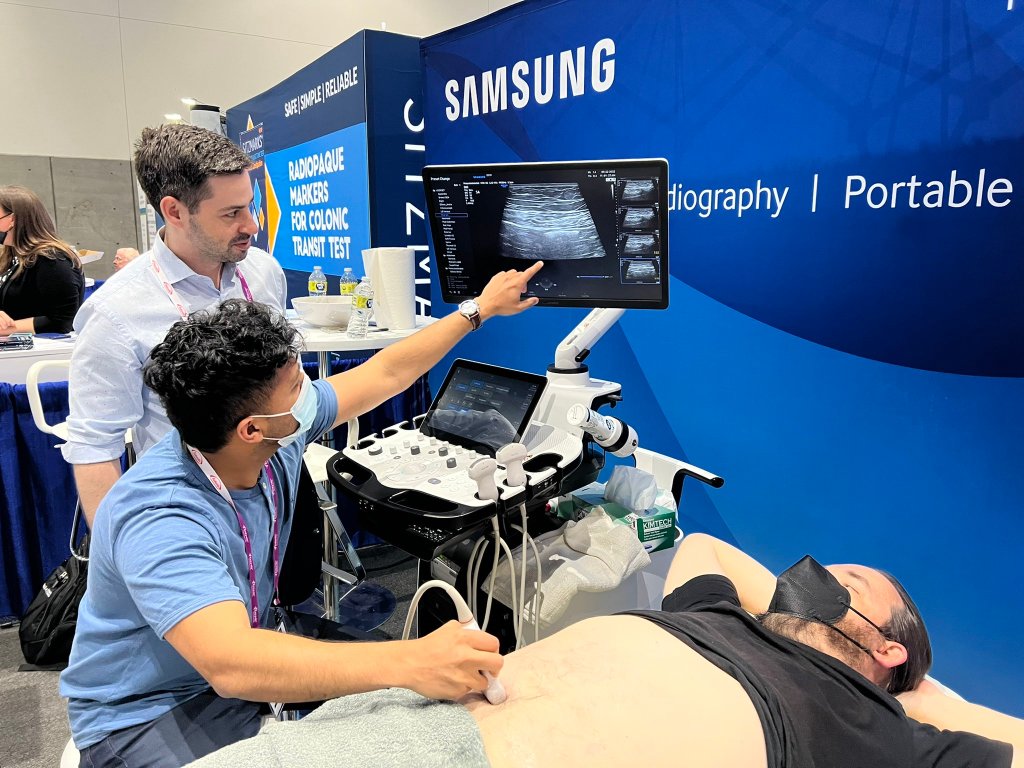















 lights camera crohn's
