How GI Symptoms Influence Food Choices in IBD Patients & Strategies for Managing Pain, Bloating, and Nutrient Intake

Imagine in a quick twist of events you go from having a wonderful day to dealing with IBD symptoms. Suddenly you go from feeling “fine” to having pain that’s gotten your attention quickly. You’re bloated and could pass for being 5 months pregnant, nothing sounds appetizing, you’re scared eating or drinking will further exacerbate your symptoms. The mere thought of ingesting anything makes you a bit nauseous. All your attention and focus is on tolerating the pain. Now pause. 

It’s no surprise these symptoms significantly impact food choices and nutrient intake, as we’re forced to navigate the delicate balance between managing discomfort and maintaining proper nutrition. Understanding how GI symptoms influence dietary decisions and implementing strategies for managing these symptoms is crucial for IBD patients to ensure overall well-being.

Even as a veteran Crohn’s patient of nearly 20 years, I’ve been struggling to manage my diet while living with unpredictable painful symptoms that started to arise when I was put on a biosimilar medication in July 2024. I’ll be honest, lately when I’ve been dealing with abdominal pain and bloating, I’ve been refraining from eating. Turns out—surprise, surprise… that’s the last thing any of us should be doing. This week on Lights, Camera, Crohn’s hear from trusted registered IBD dietitian and ulcerative colitis patient extraordinaire, Stacey Collins, about how we can better navigate these challenges. 

How have GI symptoms influenced your food choices?

If you’re in an active disease flare and dealing with an inflammatory response, you need protein and calories to overcome any risks for malnutrition. So how can we go about getting enough calories?

“Liquid calories aren’t always the tastiest—but smoothies and even nutrition shakes can be beneficial for those dealing with IBD symptoms and teetering on the line of a full-on flare. When you’re feeling well, try to designate part of one day a week where you make soups and smoothies ahead of time that you can freeze as a rainy-day investment to help you out on days when you aren’t able to expend the energy to prepare food,” says Stacey.

She also suggests “taking a holiday” from gut-health supplements you take—it’s not all or nothing. Take a break from your probiotic, prebiotic, anything that “helps with inflammation,” and enzymes (unless prescribed by your physician explicitly), and let your body relax from the burden of taking too many supplements.

Rather than avoiding eating altogether, which feels like the right thing to do when you’re in discomfort, try to maintain a consistent routine of eating to nourish your body to heal from a flare and avoid excess discomfort.

Our hypersensitive guts

When you live with IBD and you have a history of inflammation, visceral hypersensitivity, or an increased pain perception in the bowel, is a key factor to take into consideration. 

“Acknowledge that a smoke alarm is going off, and then try deep belly breathing if that’s an accessible movement for you. I often tell people to lay down on the floor. If you have children, invite them to join! They can lay down beside you and do this exercise with you. Together, you can select a favorite toy or teddy bear: one for you and one for themselves. Put the bear on your belly and BREATHE! You should see the teddy bear move with your inhale as you breathe deep into your belly–see who can make the teddy bear go the highest. This can help you to return to your breath and welcome a sense of calm into your body. If this isn’t a great option for you, pausing to notice the exhale portion of your breath, intentionally making it a bit longer than the inhale, can be impactful in helping to calm the nervous system,” explains Stacey. “Clinically everything may be checking out okay with lab work, scans, and scopes, but it’s important to recognize if you’re dealing with pain, not everything is right. It can feel disorienting to not have that pain validated by labs and tests, which is why cultivating tools like these can be helpful to ride the waves of the pain while feeling just a little bit better in your body.”
When I decided to have soup last week after not eating all day, I was really taken aback by my abnormally loud bowel sounds while I was digesting. Stacey reminded me that when you go a long time without eating and then choose to eat something, that your gut will be working extra hard. This can lead to loud bowel sounds or Borborygmi. Anyone, including people with IBD, can experience hyperactive bowel sounds. When I heard my abnormally loud bowel noises the other day, it brought me back to past bowel obstructions where I would eat and people could hear my stomach making sounds in the other room.

What’s the deal with bloating?

Bloating in Crohn’s disease or ulcerative colitis is often caused by a combination of factors related to the underlying inflammation and the altered digestive processes associated with the disease. Some key factors include:

  • Inflammation of the Gut: The intestinal lining disrupts normal digestion and absorption of food. When the gut is inflamed, depending on location and severity, it can lead to malabsorption, causing undigested food particles to remain in the intestines longer, which can increase gas production and bloating.
  • Altered Gut Motility: Inflammation can impair the muscles in the intestinal walls that are responsible for moving food through the digestive tract. Slowed or irregular gut motility leads to delayed digestion and fermentation of food by gut bacteria, which can result in gas buildup and bloating.
  • Imbalance of Gut Bacteria (Dysbiosis): People with IBD often have an imbalance in their gut microbiome (dysbiosis), meaning there are fewer beneficial bacteria and more harmful bacteria. This imbalance can lead to increased fermentation of carbohydrates in the colon, producing excess gas, which contributes to bloating. Not getting enough nutrition can make dysbiosis worse. 
  • Intestinal Gas Accumulation and Stool Burden: Inflammation in IBD can slow down the passage of gas through the intestines. This causes gas to accumulate in the gut, leading to bloating and discomfort.
  • Small Intestinal Bacterial Overgrowth (SIBO): SIBO, a condition where excessive bacteria grow in the small intestine, is more common in IBD patients who are not in clinical remission. This bacterial overgrowth can cause excessive fermentation of food, leading to bloating, gas, and diarrhea.
  • Dietary Factors: Certain foods, such as those high types of carbohydrates called Fermentable Oligo-Di-Monosaccharides and Polyols (FODMAPs), can sometimes be uncomfortable to digest and may temporarily need to be eliminated from the diet to help with bloating. Most often, this occurs in active Irritable Bowel Syndrome (IBS) flares.
    • If IBD is in clinical remission but you’re experiencing IBS-symptom overlap, you may benefit from identifying FODMAP triggers with a dietitian. Re-introduction is an important phase of FODMAP-trigger identification, because these foods are often rich in pre-biotics, which are beneficial for the gut microbiome.
      • Note: A low-FODMAP diet will not impact IBD-related inflammation. However, it may help with alleviation of symptoms. This diet is meant to be short-term and with the support of a registered dietitian.
    • Other dietary factors: sugar alcohols, chewing gum, carbonated beverages, sugar-sweetened beverages may also contribute to gas and bloating.
  • Food Intolerances: Food intolerances in IBD have not been studied adequately, but the most common food intolerance in IBD is lactose, where there’s a lack of enzyme available to help break down the lactose sugar, resulting in gas production and bloating. IBD patients can develop intolerances to certain foods, such as lactose, gluten, or high-fiber foods, which can trigger bloating. The gut’s reduced capacity to break down these components can result in gas production and bloating.
  • Inflammatory Strictures and Obstructions: Chronic inflammation can lead to scar tissue formation (strictures) that narrows parts of the intestines. This can cause a buildup of food and gas behind the narrow areas, resulting in bloating and abdominal discomfort. Discuss a monitoring strategy with your GI care team to ensure that you are not at risk for these complications.
  • Abdomino-phrenic dyssynergia (APD): this occurs when the diaphragm and abdominal muscles do not coordinate appropriately, which can lead to bloating, distention, constipation, and pain. Bloating may worsen throughout the day, even without food. Pelvic floor physical therapists (PFPT) can help evaluate and treat a person with APD.
  • Medications: Some medications used to manage IBD may contribute to bloating by altering the gut microbiome or affecting digestive motility.

Bloating can also be a result of constipation, but this certainly doesn’t feel like it makes sense when we’re going to the bathroom multiple times a day. 

“This [urgency] can happen as a result of overflow diarrhea, when stool actually moves around more solid stool within our intestines, agitating the nerves and muscles, until there is a complete evacuation of all stool,” Stacey explains. (source)

Addressing symptom alleviation related to bloating typically requires a combination of anti-inflammatory treatments, dietary modifications (including hydration), gentle movement, behavioral modification techniques, and, in some cases, probiotics and/or antibiotics to rebalance the gut microbiome. I’ve found not wearing a tight waistband or anything that buttons at the waist can help reduce bloating. Whenever I wear Spanx, I usually end up feeling bloated. 

A day in the life

I asked Stacey to walk us through a practice menu for making dietary choices to stay nourished when your IBD symptoms are getting in the way:

Practice menu
Note: this is not prescriptive; these are just some ideas. The key takeaway is to aim for consistent nourishment throughout the day in active disease flares, choosing nutrient-rich foods that will support you through a hard day. Work with a dietitian for personalization! No 2 diets necessarily look the same; no 2 days look the same.

Breakfast

  • Low-fat Greek yogurt that’s low in lactose, which is usually gentle on the gut and rich in protein, probiotics and bone health minerals. Add in some mashed raspberries and bananas with a nut or seed butter
  • Oatmeal—keep it simple, instant is fine. You can add a drizzle of olive oil to make it savory with additional omega-9 fatty acids for powerful anti-inflammatory support, soft boiled eggs, avocado, with a dash of thyme. 
    • If you simply can’t get over the idea of a savory oatmeal, just add some nut or seed butter and swirl it altogether with banana or applesauce and cinnamon
  • Smoothie: a liquid base, some frozen fruits (1 Cup or less at a time), and handful of greens, and a 3rd party-tested protein supplement may be a comfortable way to start the day, sipping slowly and gently

Lunch

  • cooked down starches, like squash, zucchini, cooked-down until fork-tender
    • you can recycle these starches by adding them into a sandwich on sourdough, using tahini as a savory spread that will provide you with even more nutrition
  • Salmon is easy to digest while providing a rich source of omega 3’s
  • a nice pesto sauce to drizzle over the salmon would be delicious and rich in calories, perfect when you need additional nutrition and are feeling low on energy

Or, for something much simpler:

  • never, ever underestimate the power of a pb + j 
  • a side of salty, simple-ingredient potato chips can replace any lost by diarrhea if you’re having an especially symptomatic day that causes you to make more bathroom trips

Dinner

  • Rotisserie chicken (you can buy this directly from the grocer- no cooking required!)
    • you can recycle leftovers into chicken salad to be used as a protein-rich spread for lunches or snacks
  • Roasted potatoes, or potato soup (made in a slow-cooker for easy prep and clean-up!)
  • Cooked green beans or carrots. (If lacking energy, throw some veggies in the slow cooker with broth for extra nutrition)

Snack ideas:

  • peeled, salty edamame
  • Hummus, cucumber and pita for dipping (can opt to peel cucumber if that feels better for you)
  • Hummus, tahini, or guac on a tortilla, roll up some rotisserie chicken 
  • Avocado toast (cheers, Millennials!) 
  • Maybe pour yourself a cup of peppermint tea (unless you also deal with acid reflux)- this could give you some bloat relief, too!

Here’s more food ideas!

Identifying the triggers

Many IBD patients identify certain foods that trigger symptoms like bloating, cramping, or diarrhea. For example:

  • High-fiber foods: If too many are added at once, this can exacerbate bloating or diarrhea, leading many patients to avoid whole grains, raw vegetables, and legumes.
  • Dairy products: Due to lactose intolerance, some individuals avoid milk and all dairy foods. 
  • Fried and fatty foods: These foods may slow digestion, causing discomfort or worsening symptoms.

The tendency to avoid certain food groups can result in nutrient deficiencies, especially if entire categories like fiber, fats, carbs, or dairy are removed from the diet. The unpredictability of IBD flare-ups can make patients apprehensive about eating. They may opt for bland or easily digestible foods, limiting their variety and nutritional intake. While this might offer temporary relief, it may not provide all the necessary nutrients, leading to long-term health complications such as malnutrition, weight loss, or vitamin deficiencies (e.g., vitamin D, B12, iron), or a poor food-related quality of life. 

Tips for Managing Pain and Bloating While Ensuring Proper Nutrition

  • Work with a Dietitian: IBD patients should work with a registered dietitian, preferably one who specializes in gastrointestinal disorders. A personalized diet plan and support can help patients identify trigger foods, balance nutrient intake, and minimize symptom flare-ups.
  • Small, Frequent Meals: Eating smaller, more frequent meals can help reduce bloating and cramping. By spreading out food intake throughout the day, the digestive system may be less overwhelmed, potentially alleviating pain and bloating while allowing for better nutrient absorption. Reach for simple ingredients.
  • Eat mindfully in a relaxed environment: chew thoroughly, allowing more time for enzymes in the mouth to aid in digestion, so food is more comfortable to digest as it travels down the GI tract. Mindful eating is also associated with 
  • Cooked and Pureed Vegetables: For patients struggling with fiber tolerance, switching from raw to cooked or pureed vegetables can provide some of the essential nutrients from vegetables without causing additional bloating or pain. Cooking helps break down the fiber, making it easier to digest. When in doubt, aim for “fork-tender” fruits and vegetables if you’re in a flare, rather than keeping them out of your diet altogether if you can.
  • Incorporate Nutrient-Dense Foods: Nutrient-dense, easily digestible foods like bananas, white rice, eggs, and lean meats (like chicken and turkey) can provide essential vitamins, minerals, and protein without aggravating symptoms. Incorporating bone broths, smoothies, and pureed soups can also help patients maintain a balanced diet while being gentle on the GI tract.
  • Stay Hydrated: Hydration is crucial, especially for IBD patients who experience diarrhea. Drinking water, broth, and electrolyte-rich fluids can help maintain fluid balance, prevent dehydration, and support digestion. Add salt to your food for hydration. If you’re struggling to maintain hydration, you may benefit from an oral rehydration solution (ORS).
  • Pain Management Techniques: Alongside diet adjustments, pain management techniques such as relaxation exercises, yoga, or gentle physical activity may help ease abdominal pain and bloating. Walking will help with bloating and gas. Don’t overdo it, even a walk to the mailbox after eating is beneficial. Additionally, medications like antispasmodics or anti-inflammatory drugs, as prescribed by a healthcare provider, can reduce inflammation and pain, allowing patients to eat more comfortably.

Final thoughts

IBD patients face daily challenges in managing symptoms like pain and bloating while trying to maintain adequate nutrition. During a Crohn’s flare, it’s essential to focus on easy-to-digest foods while maintaining hydration and nutrient intake. Consider how to alter the texture of colorful, nutritious fruits and vegetables for comfort, rather than taking them away altogether- your body needs the nutrition for healing! Working closely with healthcare professionals, including a dietitian and gastroenterologist, ensures that patients can minimize symptoms while meeting their nutritional needs, leading to better long-term health outcomes. The goal during a flare is to reduce irritation, manage symptoms like diarrhea, pain, and bloating, and to keep eating while welcoming more anti-inflammation through nutrition!

Helpful resources

Abdominal Pain in Inflammatory Bowel Diseases: A Clinical Challenge – PMC (nih.gov)

Chronic abdominal pain in inflammatory bowel disease: a practical guide | Frontline Gastroenterology (bmj.com)

What you need to know about diet and nutritional therapies for IBD patients – American Gastroenterological Association

Diet and Nutrition in Inflammatory Bowel Disease: A Review of the Literature – PMC (nih.gov)

Managing Pain & Fatigue in IBD (youtube.com)

IBD Diet Guide: Nutrition for Active Inflammatory Bowel Disease (uchealth.com)

Abdominal Pain in Inflammatory Bowel Disease: An Evidence-Based, Multidisciplinary Review – PMC (nih.gov)

Special IBD Diets | Crohn’s & Colitis Foundation (crohnscolitisfoundation.org)

What Should I Eat? | Crohn’s & Colitis Foundation (crohnscolitisfoundation.org)

The Gut-Brain Connection: Understanding Its Role in Inflammatory Bowel Disease

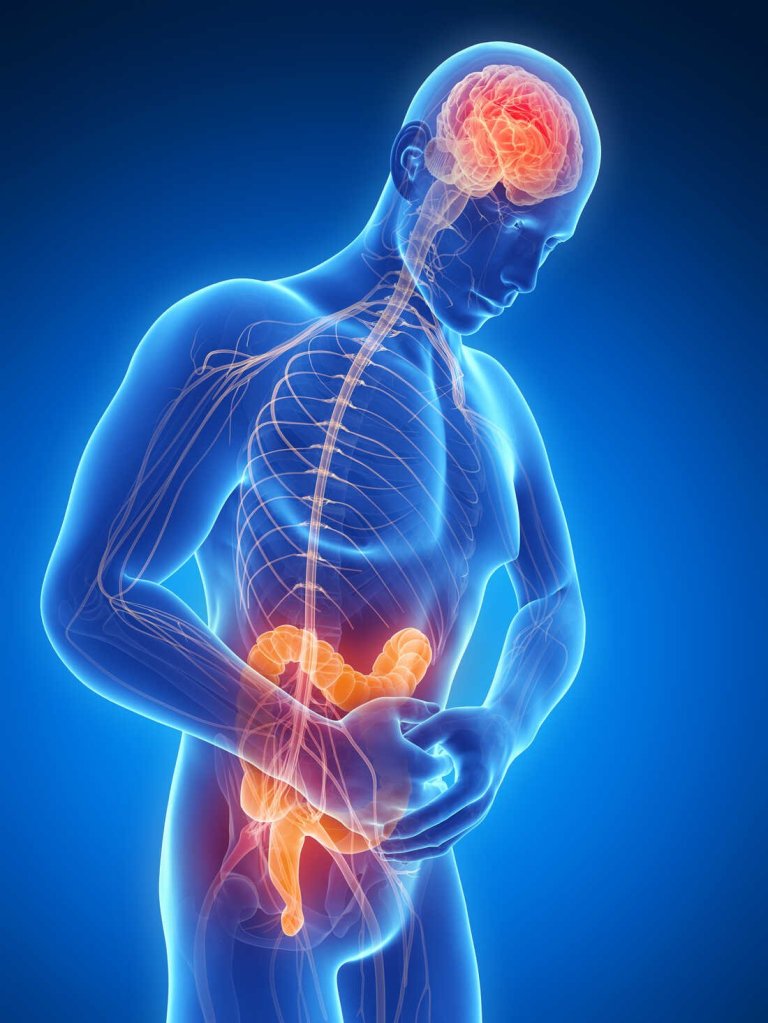
Ever have a feeling in your gut that says you can trust someone or to make a certain decision? Get diarrhea or constipation when you’re under a lot of stress or anxiety? Your gut is so sensitive and smart scientists call it your “second brain! The human body is a complex ecosystem, with various systems interconnecting in intricate ways. One of the most fascinating of these connections is between the gut and the brain, often referred to as the “gut-brain axis.” This communication network plays a crucial role in maintaining our overall health, influencing everything from mood and cognition to immune function and digestive health. Emerging research indicates that the gut-brain axis may significantly influence the development and progression of IBD. The big question being—how?

This week on Lights, Camera, Crohn’s a look into how the Gut-Brain Axis works and what this means for the future of IBD treatment and care. Whether it’s stress, people pleasing, avoiding emotions, or anxiety—there are many triggers aside from food.

The Gut-Brain Axis: A Two-Way Street

Before we get started, it’s helpful to understand what the gut-brain axis involves and the multiple pathways it impacts, including the nervous system, the endocrine system, and the immune system. The primary components of this axis are:

  • The Enteric Nervous System (ENS): Think of this as how it feels when you get “butterflies in your stomach”. The ENS is a vast network of neurons (nerve cells that send messages all over your body to allow you to do everything from breathing to talking, eating, walking, and thinking) embedded in the walls of the gastrointestinal tract. It operates independently of the central nervous system but communicates with it via the vagus nerve, which runs from the brainstem to the abdomen.
  • Neurotransmitters and Hormones: The gut produces and responds to various neurotransmitters and hormones, including serotonin, dopamine, and cortisol. These chemicals are crucial for regulating mood, stress responses, and digestive functions.
  • The Microbiome: Trillions of microorganisms reside in the gut, forming a complex and dynamic community known as the microbiome. These microbes play a critical role in digestion, immune modulation, and even the production of neurotransmitters.

The Gut-Brain Connection and IBD

Chronic inflammation in IBD can affect the enteric nervous system, leading to alterations in gut motility and sensitivity. Those of us with IBD often experience abdominal pain, cramping, and changes in bowel habits, which are partly mediated by the nervous system. Conversely, stress and psychological factors can exacerbate IBD symptoms. Stress activates the hypothalamic-pituitary-adrenal (HPA) axis, leading to the release of cortisol and other stress hormones, which can, in turn, promote inflammation in the gut.

The Role of the Microbiome

The gut microbiome is crucial in maintaining intestinal health and regulating immune responses. For those with IBD, the composition and diversity of our gut microbiomes are often disrupted, a condition known as dysbiosis. Dysbiosis can contribute to the chronic inflammation seen in IBD by impairing the gut barrier function and promoting an overactive immune response. Interestingly, the microbiome also communicates with the brain through the production of metabolites and neurotransmitters, which influences mood and cognitive function.

You can optimize your gut microbiome with diet by eating:

  • Green leafy vegetables (broccoli, kale, Brussel sprouts, asparagus, spinach, garlic, etc.).
  • Healthy fats (extra virgin olive oil, sesame oil, coconut oil, nuts, seeds)
  • Protein (eggs, fish, grass-fed meats)
  • Low sugar fruits (avocado, bell peppers, cucumber, tomato, zucchini, limes, and lemons)

*Before altering your diet or incorporating foods that could trigger disease activity, please talk with your care team and discuss this further with a registered dietitian who specializes in IBD.

Psychological Factors and IBD

IBD is often associated with psychological conditions such as anxiety and depression. According to the Crohn’s and Colitis Foundation,  we’re two to three times more likely to deal with anxiety and depression than the general population. These mental health issues can both contribute to and result from the physical symptoms of IBD. For instance, chronic pain and discomfort can lead to increased stress and anxiety, while anxiety and depression can exacerbate gut inflammation and symptom severity. It’s a vicious cycle that can often feel out of our control.

Therapeutic Implications

Understanding the gut-brain connection opens new avenues for the way we treat IBD. Traditional treatments focus on reducing inflammation and managing symptoms through medications and lifestyle changes. However, addressing the gut-brain axis could provide additional therapeutic benefits. Some potential approaches include:

  • Probiotics and Prebiotics: These can help restore a healthy balance in the gut microbiome, potentially reducing inflammation and improving gut health. Talk with GI about their thoughts on this, as each provider has their own opinion.
  • Psychological Interventions: Cognitive-behavioral therapy (CBT), mindfulness-based stress reduction (MBSR), and other stress-management techniques can help manage the psychological aspects of IBD, potentially reducing symptom severity. Tools such as breath work and gut-directed hypnotherapy can help to improve GI systems, while improving your mood and decreasing stress. This works by softening the body’s stress response, inhibiting the secretion of cortisol, decreasing inflammation, and supporting the immune system.
  • Dietary Modifications: Certain diets, such as the low-FODMAP diet, can help manage symptoms by reducing gut irritation and inflammation. Personalized nutrition plans based on an individual’s microbiome composition are also being explored. Connecting with a registered IBD dietitian can provide you with a personalized plan geared to where you’re at on your patient journey—this will differ if you’re recovering from surgery, pregnant, flaring, the list goes on. Diet is not a one size fits approach, it’s unique to you. Before you start eliminating entire food groups and putting difficult limitations on yourself, talk with a professional.
  • Pharmacological Treatments: Medications that target the gut-brain axis, such as those that modulate neurotransmitter levels, are being investigated for their potential to treat both the psychological and physiological aspects of IBD.

Final thoughts

Our gut and brain are in constant contact through nerves and chemical signals, and taking care of our mental health and our gut health goes hand in hand. The relationship between our gut and brain is a fascinating and complex one that significantly influences our overall health, playing a pivotal role in everything from mood and cognition to immune response and digestive health. For those of us living with IBD, understanding and addressing this connection can provide new insights into the management and treatment of our disease.

As research continues to uncover the complexities of the gut-brain axis, we move closer to a holistic approach to IBD care that considers the intricate interplay between mind and body. Know that there are psychologists who specialize in gastrointestinal illnesses as well as dietitians who do as well. By adding specialists like this to your care team, you’ll be better equipped to manage the unpredictability of life with Crohn’s and ulcerative colitis.

Additional Resources

The Gut-Brain Axis in Inflammatory Bowel Disease—Current and Future Perspectives – PMC (nih.gov)

Researching IBD and mental health through the gut microbiome – UChicago Medicine

The influence of the brain–gut axis in inflammatory bowel disease and possible implications for treatment – The Lancet Gastroenterology & Hepatology

The Gut-Brain Connection — Does It Go Beyond Butterflies? | Live Healthy | MU Health Care

Brain structure and function changes in inflammatory bowel disease – ScienceDirect

Crohn’s disease, gut health, and mental health: What’s the link? (medicalnewstoday.com)

Brain-gut connection explains why integrative treatments can help relieve digestive ailments – Harvard Health

An innovative app for all chronic illnesses: Meet Corra

This post is sponsored by Corra. All thoughts and opinions shared are my own.

For as long as Elya Lane can remember she had signs and symptoms of a health condition. It wasn’t until college that she received her official diagnosis of Ehlers Danlos Syndrome and POTS. She says her poor health started to spiral with other comorbidities popping up, the worst of which was chronic UTIs that left her whole body in crippling, burning pain and weak from the antibiotics. Elya’s personal journey with chronic illness inspired her to create the Corra App. This week on Lights, Camera, Crohn’s we learn about how she made her dream a reality and how she hopes to improve peoples’ lives.

The breaking point

“I was constantly plagued with fears of antibiotic resistance, infection complications, or complications from long term antibiotic use. I got to the point where I was so sick that I wrote letters to my kids and my family in case something happened to me. I started tracking all our passwords and making videos for my husband on where our important files were, how different things were stored, all the kids’ data, etc. While I tried to face this potential outcome bravely, I was devastated imagining my kids growing up without a mom,” said Elya.

As she navigated these dark and daunting days, the despair caused her to think about how she could fight back and regain control of her health.

“I started to religiously track my health in journals before transferring to Excel spreadsheets. I was so frustrated by how exhausting and impossible it felt to crunch that much data, so I turned to searching for a symptom track and correlative software to help me. I downloaded and tried every single one I could find – but none met my needs. Some even gave me back faulty data which made me angry. That’s when I decided to create a solution myself,” she explained.

In 2020, after losing access to all her healthcare management tools, and with her health declining rapidly, she decided to create Corra.

The meaning of Corra

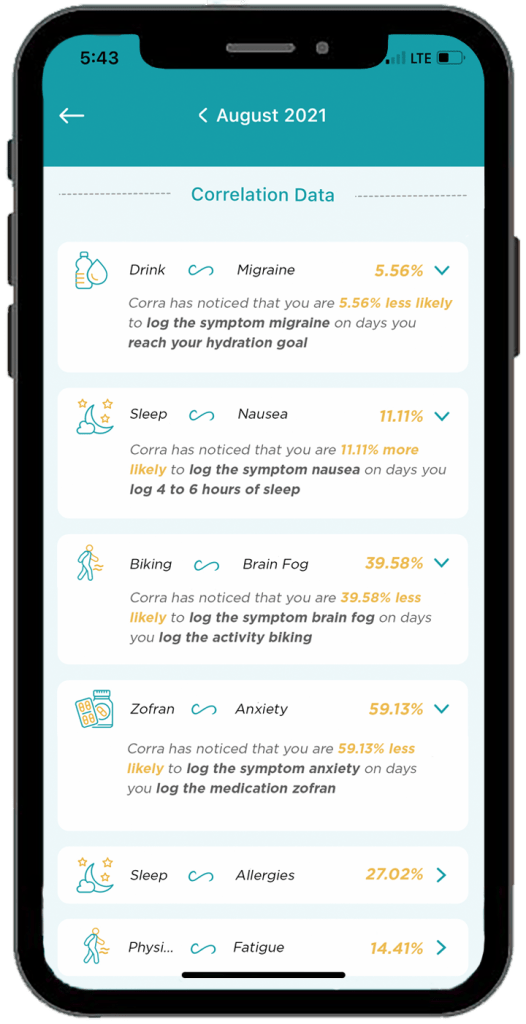
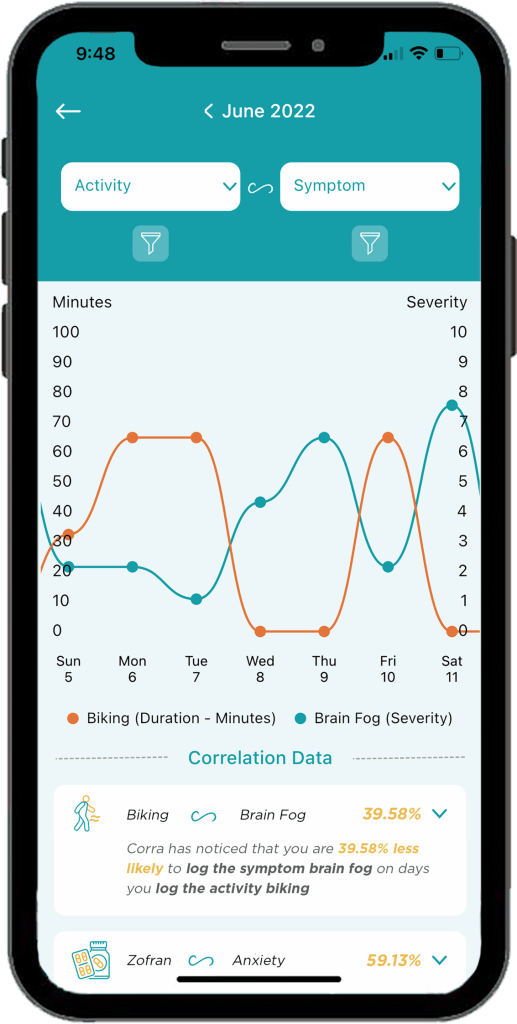
There are quite a few chronic illness apps on the market, some that even attempt to offer correlative insights. Corra is short for correlations. Elya wanted to identify correlations in her health so that she could find her triggers and optimize her lifestyle.

Here’s what sets Corra apart from other chronic illness apps on the market:

  • The algorithm was custom built by Corra’s chief data scientist, Simeon Wilson, who has a master’s in quantitative economics from UCLA. “We are not aware of any software that exists that compares to what Corra is currently offering with our correlative algorithm.”
  • Corra was designed by individuals with chronic illness. “Not just me! While the idea and original designs are all mine, we brought on more than 200 beta testers with various chronic illnesses to provide their feedback and help us tailor the app to the needs of the chronic illness community. Even now, we continue to rely on the insights and feedback from the community to enhance and adjust the app. I want Corra to always be designed by and created for our community.”
  • We correlate with nutrition in an accurate and helpful way. “I believe nutrition plays a massive role in our health so one of our key focuses with our algorithm was to be able to correlate seamlessly with nutrition inputs.”
  • Corra does not sell user’s data. “We don’t scrape your data from your device or browsing history, we don’t use your data to sell you anything, we don’t share your data with third parties. Your data is yours alone. As an individual with a chronic illness who often feels more like a commodity than a person, making sure people can receive personalized insights into their health without signing away their privacy is incredibly important to me.”

Corra’s bells and whistles to check out

  • The ability to track health data in one place without having to use five different apps to log information. “My favorite part of Corra is of course the correlations, because getting detailed insights like that about my health is equivalent to having a team of data scientists run extensive tests on my health and provide me reports. It’s life changing to be able to learn about my health overtime and create a custom-built lifestyle that caters to my future.”
  • Discovering positive and negative correlations. “You may receive insight that something has x% chance of increasing or decreasing a symptom. I think being able to get data on the things that are helping is just as important as being able to identify triggers.”
  • The ability to log appointments, download PDFs of your data to share with my doctor, track medications and supplements, track mood and stress levels, etc. “I’m also extremely excited about all the upcoming integrations we have in the works! Soon we will be connected to Fitbit and Apple Health with Garmin, Cronometer, Weather data, and hopefully Oura coming shortly after! Over time we will continue to integrate with as many devices and apps as possible so users can have all their data in one location!”

A promising future

Elya says being able to learn what foods, activities, supplements, and medications help or cause symptoms has enabled her to have a much better understanding of how best to manage her health conditions.

“I’ve been told to go vegan, cut out red meat, don’t eat dairy, sugar, gluten, eat paleo, try a carnivore diet, go vegetarian, and try cutting out leafy greens… what I found with Corra is that I didn’t need to make these drastic nutrition changes, I only needed to cut out some foods in each of those categories. For example, I discovered that I have a high trigger correlation with ground beef. I can eat steak and other red meat, but not ground beef. Similarly, chicken thighs are a trigger for me, but chicken breast is not. Same with gluten, there are some gluten products that are triggering for me, but not all gluten triggers me. Being able to identify exactly which foods to cut out, rather than willy nilly cutting out entire food groups or going on drastic diet changes, has been an absolute game changer.”

Elya has also discovered that cold and flu medications like Mucinex are major triggers for her. This helped her realize why she would get a horrible flare a few days after coming down with a cold or flu.

“Now, I try to manage my colds and flus with other medicine to try to prevent the flare on top of the cold. It’s also important to note that I’m not cured! I have to manage my diet and my activities and my supplements every day. The difference is, I’m no longer throwing shots in the dark, I now have the information I need to manage my condition to the best of my ability.”

Information really is power, and it has given Elya control over her life and reduced her anxiety. Because of Corra, she is now coming up on two years without the need for daily antibiotics. It’s been over 2 years since she visited the emergency room.

“I’ve found that medical providers are far more willing to accept unbiased data from an algorithm than trust my verbal expression of my experience, so in that way Corra becomes my advocate and backs up my statements,” said Elya.

She says her health conditions have caused her to go through depression, isolation, and hopelessness. But her hope for Corra is two-fold.

“First, I believe it can help others identify their triggers and optimize their life so that their conditions can become more manageable, but I also hope that Corra can be a beacon of light for those struggling to see they are not alone. There are so many steps between the start of symptoms and any kind of treatment let alone cure (depending on if your condition is even curable)… and I want to be the one that goes into the trenches and helps people who are suffering the most. So many people in the chronic illness community get forgotten or left with “your test results are normal” when they know there is something wrong with them. I want to create a company that comes alongside them and lifts them up and allows them to have their voices heard.”

Downloading Corra

You can download Corra directly from the App store or the Android playstore. There is a free version as well as premium access. The premium version is $7.99/month or $24.99 if you enroll for a 6-month subscription. Elya is looking for Corra Insiders who are interested in getting free access to the app. By joining the Insiders group, you get a first look at upcoming features. This provides you the opportunity to share feedback on what you do/don’t like or would like to see improved or added in the future. Sign up for the Corra Insiders program here.

Cedars Sinai’s IBD Dietitian Apprenticeship Program is Changing the Future of Nutritional Support for Patients

It’s the first of its kind program dedicated to training dietitians about IBD-focused nutrition. Cedars Sinai Hospital in Los Angeles, California launched its IBD Dietitian Apprenticeship in July 2023.

Registered IBD dietitian Stacey Collins was the first registered dietitian to be selected, participate, and complete the program. I’ve been amazed at all she does for our community and been excited to dig deep and learn what her key takeaways have been from this experience. As someone whose lived with ulcerative colitis since 2012, when she was 21-year-old, Stacey has a unique perspective and approach.

This week on Lights, Camera, Crohn’s we’ll hear about her firsthand experience and why this Apprenticeship program is just what our community needs. The hope is that registered dietitians who participate in the program can take their knowledge from the experience and be able to plug themselves into an IBD Center to build and strengthen an IBD program.

Going up against lack of education and funding

Stacey tells me there is little to no education that they receive in dietitian training on how to do nutrition specific to gastroenterology, much-less IBD, and she says this Apprenticeship program fills the gaps and then some.

“So much of what I learned was through self-study before this program. But in the Apprenticeship, whether I was part of the team rounding on patients in the hospital, or seeing a newly diagnosed patient in clinic, or sitting on the floor with a 3-year-old patient asking about their Paw Patrol toys, I left every encounter feeling that special kind of discomfort and gratification that comes with growth and learning. This was truly a hands-on learning experience from many different sides of the IBD rubix cube, and I’m so grateful I wasn’t learning it all by reading slides from a PowerPoint and taking a test- who learns that way anyway?!”

Addressing the unmet needs

Once registered dietitians complete the Apprenticeship they can work in an academic center or a private practice that values IBD nutrition and has the financial backing to justify the need for a dietitian.

“There are institutions and people in places of power who are advocates for the profession of IBD RDs, and this work is simply impossible without them. IBD RDs have the potential to support patients throughout their journey as an accessible, consistent member of their multidisciplinary care team. Unfortunately, a lot of this potential is systemically handicapped by the lack of funds: RDs are investments rather than quick money-makers for a clinic without physician advocates and creativity, and we NEED people at institutions to see our value,” said Stacey.

The main programmatic goals are to provide a structured, supervised training program for dietitians to learn a model wherein dietitians work together with physicians and advanced practice providers for the care of adults and children with IBD.

Places do exist (and many are coming) that support this multidisciplinary model of healthcare delivery, but there’s such an unmet need, especially for people who don’t have access to these IBD centers. The hope is for this Apprenticeship program to fill the gaps of that unmet need by signaling to physician advocates at these institutions that a nutrition professional with intense training and experience DOES exist, ESPECIALLY for more complex patients who have IBD.

So much to be done for patients
Registered IBD dietitians can assess people for malnutrition regardless of their stage of IBD, which is common even in remission and linked to poor health outcomes, along with so much more. Stacey says:

  • We can help catch micronutrient deficiencies or insufficiencies that many other care team members might miss, and we can correct and monitor them.
  • We can help patients experiencing food insecurity find ways to nourish themselves within their budget constraints with an eye toward prevention of other comorbidities.
  • We can help nutritionally prepare patients for surgery.
  • We can help patients in need of a medical or therapeutic diet intervention find a way to make it a sustainable intervention for themselves.
  • We can help patients nourish themselves using a whole-person approach, whether they are juggling multiple diagnoses, starting a new job, headed off to college, or too tired to eat: we have tools for helping patients feeling like they can handle it all
  • We can help prevent re-hospitalizations from small bowel obstructions or dehydration by giving patients IBD-specific tools for understanding their body.
  • We can save physicians time by inheriting questions about nutrition and/or supplementation regimens, and we can personalize these for each patient.
  • We can even show GI or IBD Fellows what it’s like to feel spoiled working with an IBD dietitian, and hopefully they’ll advocate to hire one of us wherever they make their final clinical stop

She’s confident IBD dietitians can make nutrition an accessible tool when it so often feels inaccessible with IBD!

Stacey’s top apprenticeship moments that left a lasting impression

Six months is a long time to pick up your life, move to another state temporarily, and fine tune your knowledge and expertise on nutrition and IBD. Here are the key takeaways Stacey says she took away from the experience:

1. Patience with patients is key; everyone is on their own timeline.

“I got to see a doctor celebrate with a patient who finally quit smoking cigarettes for good. After that encounter, he told me that he had been pleading with that patient for 20 years to stop, but he never blamed the patient for having a tough time stopping. He really was empathetic to the fact that they had a lot going on, and he knew they’d get around to it once life allowed. That was really enlightening to see: patients really are doing their best. How can I support them, especially if their timeline looks differently than the expectations that I have?” 

2. It doesn’t have to be all-or-nothing; don’t let perfection be the enemy of good nutrition.

“One day I was with Erin Feldman, RD (Cedar’s Pediatric GI and IBD RD). She was listening to a worried mom talk about how she didn’t want her kid to eat sugary cereal, but that’s ALL they would eat for breakfast: it was the sugary cereal, or it was nothing at all. The child was exercising their choice autonomy and exploring what that looked like around mealtimes, and it was a challenge for the parents. Erin had a rapport established with the family, and I could see that they really trusted her. Plus, Erin is a mom, too, so she speaks the same first language as parents, and she really empathizes with the fact that many IBD parents are blamed for their child’s symptoms or disease. She truly met the parents right where they were at that moment.”

“Instead of focusing on the PERFECT breakfast with beautifully-balanced macronutrients and color that the child certainly would refuse, she said, “What if you just added PLAIN Cheerios and a couple of raspberries to their sugary cereal, that way they’re getting some antioxidants from the berries and a more diverse source of grains into their breakfast?” It was TOO easy, and the parents were like, “YES. We can do that.” and just like that: not a perfect solution, but a practical intervention that would work for where the child is right now.”

And that’s the power in having multiple touchpoints to a dietitian: next time they see the doctor again, they’ll see Erin, too, and they can make more adjustments for how life is being lived around food at that stage, too. So often people have the ambitious idea of going from zero to specific carbohydrate diet (SCD) all in one encounter, and the reality is that often multiple conversations and coordination of resources are needed, and meeting patients where they are looks different for everyone.

3. Nutrition interventions can be hard, and multidisciplinary support really is key. 

“So often as dietitians, it’s easy to get stuck in the weeds of research and to get excited over interventions that have promising outcomes. This happened with a patient needing Exclusive Enteral Nutrition, but ~5-7 days into it, they were uncomfortable, and they really missed food. I was able to have a conversation with the patient alongside their doctor in the same room, who patiently reiterated our rationale behind the intervention and said, “not if it compromises your mental health. Let’s stop it if your brain is telling you we need to stop- we need to respect that. You should be proud that you tried this, and now you know!” And I could tell the patient was so relieved to have reassurance from their doctor that no matter what THEY chose for THEIR body they’d be supported by their doctor and by their dietitian. It really does take a team.”

4. GI Doctors REALLY do not get exposure to solid nutrition in their training

Kelly Issokson, MS, RD (Clinical Nutrition Coordinator, Course Director: DIET Executive program, Apprenticeship Director) arranged for Stacey to lead a learning session with the GI Fellows at Cedars, and in a room full of some of the smartest and most compassionate clinicians.

“They wanted to know all about the different nutrition interventions that we can recommend for patients. It felt like they had been rewarded for being the best of the best all by themselves their whole lives, and now they had an opportunity to learn more about how to collaborate effectively. They were all so enthusiastic.”

Stacey noticed after that session that the GI Fellows felt comfortable texting her while on rounds if she wasn’t there to ask if she’d stop by a patient’s room, or they’d text to ask about B12 supplementation after remembering to screen for a deficiency.

“They really understood the value that IBD RDs bring, and it’s not because I’m a great public speaker (I’m really not); it’s that they had this additional exposure to working with a dietitian with specialized training. This really made everything click for me: doctors don’t always know the right questions to ask patients about our nutrition needs, because most of them haven’t had the education OR the exposure to team members with the expertise to be truly helpful for patients. Working in silos keeps patients isolated, and I’m hopeful that the GI Fellows, when/if they leave Cedars become physician advocates to ensure that their patients have access to an IBD experienced RD.”

Plans for the future

When Stacey completed her Apprenticeship this winter, she did not envision returning full-time to her online private practice. She thought she’d start working at an academic institution, because the purpose of the program is for the dietitian to seamlessly integrate into a multidisciplinary GI care team.

“I am still holding out on hope that one day I could have both (but I’ll never give up my private practice- I love it so much). Truthfully, I’m thrilled to be back with such a passion for teaching patients how to implement some of the skills that I’ve learned into their own life, plugging it into their existing care teams, even if I’m on my own in private practice. I already helped patients through perioperative nutrition before this program, but now I’ve got some RICH resources to help make IBD surgery and nutrition really make sense for patients now in a much clearer way,” Stacey explained.

She’s able to take the research that they did from the perioperative IBD Nutrition program that exists at Cedars and put it into practice with her patients, and it’s a bit of a full-circle moment for her, having lived through IBD surgery with limited support.

“I’m a much better listener than I was before this program, a skill I learned from Kelly Issokson, MS, RD (Clinical Nutrition Coordinator, Course Director: DIET Executive program, Apprenticeship Director). Additionally, I’m more practical in my approaches and meeting patients where they really are, too, a skill I learned from Erin. I’m working on some ways to expand IBD RD accessibility, too. I’m a much more confident advocate on behalf of my patients now, too.”

Advice for the newly diagnosed

If you’re reading this and you or a loved one was recently diagnosed with IBD, ask your GI doctor to hire an IBD Dietitian. Stacey knows this doesn’t exist in most places, and as a patient, she understands how silly it is to constantly be burdening patients with requests. But the field of IBD Nutrition exists because enough patients asked, “What can I eat?” and enough doctors paid attention to it to be documented research. This is the next piece of the puzzle.

If your care team provides a registered dietitian who doesn’t specialize in IBD, that’s not going to cut it. Be assertive in asking your GI office to hire an IBD Dietitian, or invest in training their Dietitian,  if they really want to help their patients.

Stacey advises patients and caregivers to stay off online forums. There’s so much food fear there, and life is bigger than that. Lastly, she advises reaching out for help. Even if Stacey may not be a good fit for you, she’s happy to provide patients with other RDs that she’d enthusiastically see, because an informed decision is a good one.

You can also utilize the directory on the Crohn’s and Colitis Foundation’s website to find some dietitians, and the AGA will have a directory available soon, too. 

Exciting research nuggets

During her Apprenticeship, Stacey chose to do a research project to examine the effects of malnutrition and perioperative nutrition supplementation on surgical outcomes in people getting IBD surgery, whether that be for j-pouch, permanent ostomy, lysis of adhesions, or a resection.

“We had a small sample size (n=25). Regardless, we found that perioperative nutrition supplementation had a statistically significant impact on decreasing the length of stay, meaning that greater adherence to the nutrition supplementation protocol was associated with a shorter time spent in the hospital. Regardless of nutrition status (malnourished or not), everyone seemed to benefit from the nutrition supplementation protocol that we recommended for before and after surgery.”

Stacey is hopeful that more research with an even larger sample size will help inform these results so that this can be a resource more widely available for patients!

The future is bright

“If I dared to dream about what this could look like in the future, the closest possible model in existence is at UCLA under Dr. Niru Bonthala who is the Director for Women’s Health in IBD. Basically, I see the RD’s role evolving to cover every nutritional aspect of IBD with specialized knowledge to support patients in each life circumstance: from surgical prehabilitation to home nutrition support (TPN or EEN) and transitioning back to eating; to the overlap of eating disorders; to fertility and perimenopause; from anywhere along the spectrum of LGBTQIA+ care and/or transgender care; from peds transitioning to adult care, and even adults to aging adults; even athletics and/or eating disorders.”

There’s a rich opportunity within all these Venn-diagrams for a specialist interest and training to exist in IBD Nutrition, and this learning opportunity exists at Cedars.

“I’d also love to see the RD in an outpatient clinic even able to do community outreach: teaching basic cooking skills, procuring menu items for their medical diet (and beyond), and even showing patients and their families what this could look like by partnering with local food banks. Again, this is just me dreaming here in a world that I think should exist for people who have IBD and for RDs who are trained in IBD Nutrition,” said Stacey.

The current IBD Apprentice Yi Min Teo (@herbsandfood) came from both clinical and private practice backgrounds like Stacey. Yi Min will finish her training in July 2024. The program is supported by a grant from Leona M. and Harry B. Helmsley Charitable Trust.

In addition to dietitians wanting more IBD nutrition education, there’s also an Executive Program for MDs/DOs, APPS, and includes both virtual and in-person learning opportunities. You can apply here.